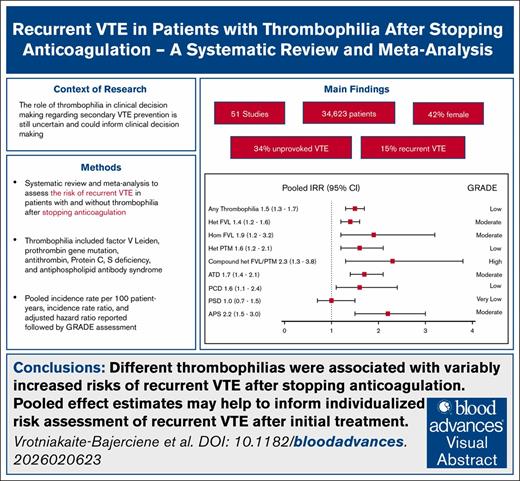
"Recurrent VTE in patients with thrombophilia after stopping anticoagulation: a systematic review and meta-analysis" read the full article in Blood Advances: https://t.co/0iMrB8Oz6z
How the hell did Rome lose 70,000 men in one afternoon in 216 BC? Machine guns?
Gunpowder was a thousand years away.
Hannibal did it at Cannae with iron blades and a deliberately bent battle line.
Consul Varro brought 80,000 Romans onto a flat plain in southern Italy. Stacked them up to 50 ranks deep.
Hannibal put his weakest infantry in the middle and let them give ground.
The Romans thought they were breaking through and kept shoving forward... until Hannibal’s African veterans turned in from both sides and his cavalry closed the rear.
Now the Roman army was inside a ring of death with no room to swing a sword.
The men in the middle couldn’t reach an enemy or get out, and a hot wind blew dust in their faces while the edges were cut down.
Livy says some dug holes in the dirt and buried their faces to die faster.
Polybius counts 70,000 dead, which works out to more than 100 a minute for hours.
On the first day of the Somme, the British lost 19,240 dead to machine guns and artillery. Hannibal’s army more than doubled that with hand-to-hand combat.
I had to check Livy twice on what came next. The consul who led them into it rode home, and the Senate thanked him.
Article in the comments on one of the biggest Roman losses in history, and how they bounced back.
Los tres grandes males de Latinoamérica:
La iglesia evangélica convertida en partido político.
El migrante que huye de la derecha y desde afuera vota por ella.
Y el pobre que cree que la derecha lo sacará de la pobreza.
Bro, Messi is a fuvking joke…
He retired as the 2026 FIFA World Cup best player dragging his nation to the silver medal,
He retired as the best Argentina player currently.
He retired as the best player in the world currently.
He retired as a Ballon d’or nominee.
at 39. 😭
#EcuavisaVerifica 🔎 | Imágenes oficiales muestran dónde se construirá el nuevo hospital del IESS 🏥 en Cayambe, #Pichincha; sin embargo, un equipo de #Televistazo se movilizó hasta el punto para corroborar cómo avanza la obra📌.
@diegopuente1 con el reporte 🎙️.
Más detalles 👉 https://t.co/1ly9woVC2g
Commercial CAR-T will remain a luxury item.
A Ferrari.
A mansion with a pool.
Vacations by private jet.
Aspirational for many. Accessible to few.
For the same reason you won’t find designer clothes at Walmart:
The big pharma model was never meant for everyone.
#CARTcells
🧠🩸 PML IN HEMATOLOGY
Progressive multifocal leukoencephalopathy: recognition, diagnosis, management & emerging therapies.
🧵 A practical review | Updated October 2026
1️⃣ 🦠 WHAT IS PML?
An opportunistic CNS infection caused by JC polyomavirus—JCV.
Infection of oligodendrocytes causes demyelination → progressive neurological disability.
🛡️ Impaired cellular immunity is central.
⚠️ Prior JCV exposure is common; PML remains rare.
2️⃣ 🩸 WHO IS AT RISK?
Think of patients with:
🔹 CLL and lymphomas
🔹 Other hematological malignancies
🔹 Previous hematopoietic transplantation
🔹 Prolonged or cumulative immunosuppression
The malignancy itself and its treatment may both contribute.
3️⃣ 💊 RELEVANT TREATMENTS
Reported associations include:
🔹 Rituximab and other B-cell–depleting treatments
🔹 Fludarabine-containing regimens
🔹 Brentuximab vedotin
🔹 CAR-T therapy
⚠️ Association does not establish the contribution of one drug in a heavily pretreated patient.
4️⃣ ⏳ RITUXIMAB PEARL
PML carries a boxed warning.
Most reported cases were diagnosed within 12 months of the last infusion.
🚨 New neurological symptoms warrant assessment even after treatment ends.
Confirmed PML → discontinue rituximab and reassess concurrent immunosuppression.
5️⃣ 🚩 CLINICAL PRESENTATION
Usually progressive over days to weeks:
💪 Asymmetric weakness
🗣️ Aphasia/dysarthria
👁️ Visual-field loss
🚶 Ataxia
🧩 Cognitive or behavioral changes
Fever and headache are not typical.
Seizures can occur.
6️⃣ 🧠 MRI PATTERN
🔹 Asymmetric subcortical/juxtacortical white-matter lesions
🔹 U-fiber involvement
🔹 T2/FLAIR hyperintensity
🔹 T1 hypointensity
🔹 Usually little mass effect or enhancement
⚠️ Early PML can be unifocal despite its name.
7️⃣ 🧲 IMAGING TRAPS
Restricted diffusion may occur at the advancing lesion edge and mimic infarction.
Enhancement does NOT exclude PML, particularly with immune recovery.
Marked edema or mass effect should prompt consideration of inflammatory PML/IRIS and alternative diagnoses.
8️⃣ 🧪 HOW TO CONFIRM?
Compatible clinical syndrome + characteristic MRI + CSF JCV-DNA PCR supports a definite diagnosis when alternatives are excluded.
Request a sensitive assay and ask the laboratory about its detection limit.
🧠 MRI alone is insufficient.
9️⃣ 🚫 NEGATIVE PCR ≠ EXCLUDED PML
Low CSF viral burden can produce false-negative results.
If suspicion remains high:
🔁 Repeat lumbar puncture
🔬 Send ultrasensitive JCV PCR
🧠 Reassess MRI and alternatives
🔎 Consider brain biopsy if uncertainty persists
Do not dismiss a convincing syndrome after one negative result.
🔟 🔬 BIOPSY PEARL
Classic findings:
🧩 Demyelination
🔍 Enlarged oligodendroglial nuclei with viral inclusions
⭐ Bizarre astrocytes
Demonstrate JCV in tissue using appropriate virological/pathological methods.
⚠️ Atypical astrocytes can resemble neoplasia.
1️⃣1️⃣ 🔄 DIFFERENTIAL IN HEMATOLOGY
Exclude:
🎯 CNS lymphoma/leukemic involvement
💊 Treatment-related leukoencephalopathy
⚡ PRES
🩸 Stroke
🦠 Other opportunistic CNS infections
After CAR-T, include ICANS and other delayed neurotoxicities—but also investigate infection.
1️⃣2️⃣ 🧬 CAR-T / HCT PEARL
PML has been reported after CAR-T, including a published case around 2 months after cilta-cel.
🚨 Progressive focal deficits or evolving white-matter lesions require a broad work-up.
The timing alone cannot distinguish PML from treatment-related neurotoxicity.
1️⃣3️⃣ 🚑 INITIAL MANAGEMENT
Urgent hematology + neurology + infectious-diseases review.
🎯 Aim to restore effective immunity:
🔹 Stop the implicated agent
🔹 Reduce other immunosuppression when feasible
🔹 Balance this against malignancy control and GVHD
No approved PML-specific therapy currently exists.
El que votó por Noboa y el que anuló "porque ninguno le convencía" hoy repiten lo mismo: "con Correa era igual". No era igual y lo saben. Pero admitirlo es aceptar que su odio, o su tibieza, nos trajo hasta aquí.
🧵🩸 SCT CONDITIONING: indications, doses & adjustments
A practical thread for hematology trainees 👇
1/ 🎯 WHY CONDITION?
Conditioning provides disease control and immunosuppression to support engraftment.
Select the regimen using disease/MRD, donor, graft source, fitness, HCT-CI and organ function.
📌 Adult dose examples below; final prescribing follows the validated transplant protocol.
2/ ⚖️ CHOOSE THE INTENSITY
🔥 Myeloablative conditioning—MAC: greater cytoreduction, greater toxicity.
🌡️ Reduced-intensity conditioning—RIC: less intensive; greater reliance on graft-versus-malignancy.
🪶 Nonmyeloablative—NMA: primarily immunosuppressive.
“Reduced toxicity” can still be MAC!
3/ 💉 BUSULFAN: KNOW THE TOTAL
Typical adult IV starting dose:
• 3.2 mg/kg once daily
• Alternative: 0.8 mg/kg every 6 hours
Bu4: 4 days → 12.8 mg/kg total.
Bu2: 2 days → 6.4 mg/kg total.
🧪 Subsequent doses may change after pharmacokinetic assessment.
4/ 🩸 FluBu4: A COMMON MAC PLATFORM
Example:
• Fludarabine 40 mg/m²/day IV ×4
• Busulfan 3.2 mg/kg/day IV ×4
• Both D−6 to D−3
Used particularly in AML/MDS and other selected myeloid diseases.
📌 Bu4 remains myeloablative despite fludarabine’s more favorable toxicity profile.
5/ 🌡️ FluBu2: A RIC PLATFORM
Example:
• Fludarabine 30 mg/m²/day IV, D−6 to D−2
• Busulfan 3.2 mg/kg/day IV, D−4 and D−3
An option when disease and patient factors favor RIC.
⚠️ Reducing intensity can increase relapse risk; fitness and disease risk must be balanced.
6/ 🧪 BUSULFAN: DOSE TO EXPOSURE
For protocols using therapeutic drug monitoring:
New dose = previous dose × target AUC ÷ measured AUC.
Example: target 5,000; measured 6,250 → calculated dose ≈80%.
⚠️ Use the same AUC units and interval; confirm with the PK team.
7/ 🚨 BUSULFAN AUC TRAPS
There is no single target for every SCT!
Document:
• Per-dose, daily or cumulative AUC
• Units
• Regimen-specific target
⬆️ Exposure → greater toxicity/SOS risk.
⬇️ Exposure → inadequate conditioning risk.
Daily and cumulative targets are NOT interchangeable.
8/ 🛡️ BUSULFAN SAFETY
• Anticonvulsant prophylaxis
• SOS/VOD risk assessment
• Review interacting drugs: metronidazole, itraconazole, deferasirox
• Renal impairment: no routine label-based reduction
• Hepatic impairment: limited data; reassess risk and exposure carefully
9/ ⚖️ BUSULFAN & OBESITY
One product-label approach uses:
Adjusted ideal body weight =
IBW + 0.25 × (actual weight − IBW).
📌 Confirm the center’s dosing-weight method, then apply PK guidance.
Do not use one obesity formula for every conditioning drug!
10/ 💊 CYCLOPHOSPHAMIDE: DIFFERENT CONTEXTS
• BuCy: 60 mg/kg/day IV ×2 → 120 mg/kg total
• Selected aplastic-anemia protocols: 50 mg/kg/day ×4 → 200 mg/kg total
• PTCy: commonly 50 mg/kg on D+3 and D+4
🚨 PTCy is post-transplant GVHD prophylaxis.
11/ ❤️ CYCLOPHOSPHAMIDE PRECAUTIONS
Assess cardiac function, renal function and fluid tolerance.
Use protocol-directed mesna/hydration; monitor urine, fluid balance and sodium.
⚠️ Cardiotoxicity, hemorrhagic cystitis and hyponatremia matter.
Severe organ dysfunction requires protocol-specific review.
12/ 🧬 FLUDARABINE: THINK KIDNEYS
Common conditioning schedules use 25–40 mg/m²/day IV for 4–5 days.
Renal dysfunction increases exposure and neurotoxicity risk.
📌 Estimate renal function using the protocol’s specified method; do not assume serum creatinine alone reflects clearance.
13/ 🧮 FLUDARABINE RENAL ADJUSTMENT
The IV CLL label uses:
• CrCl 50–79: 20% reduction
• CrCl 30–49: 40% reduction
• CrCl <30: do not administer
⚠️ These are NOT universal SCT rules. Conditioning protocols may use different reductions or an alternative regimen.
14/ 🛡️ ATG: IMMUNE DEPLETION
ATG supports engraftment and reduces GVHD in selected allogeneic platforms.
🚨 Rabbit ATG, rabbit anti-T-lymphocyte globulin and horse ATG have different dosing.
Product, donor, graft source, timing and lymphocyte burden all matter.
Preocupa mucho el acceso a Warfarina en el País, es necesario que @Salud_Ec tome medidas para evitar complicaciones relacionados con la falta de este medicamento en el Ecuador.
O fim inevitável de um narcicista.
Uma autêntica criança de 41 anos que não aceita ouvir um "não", um ativo tóxico em qualquer grupo de trabalho.
Teve azar. Desta vez apanhou um tipo com personalidade e não um fantoche como Martinez. Fim de carreira absolutamente patético.
Gellibert, la que quiso comprar tierras en Santa Elena por tres millones de dólares y utilizó a la hija de su empleada doméstica como testaferra; ahora es la nueva Presidenta del IESS ¿Cuál es su misión? Vender y Autovenderse todos los activos del IESS a precio de celular robado.