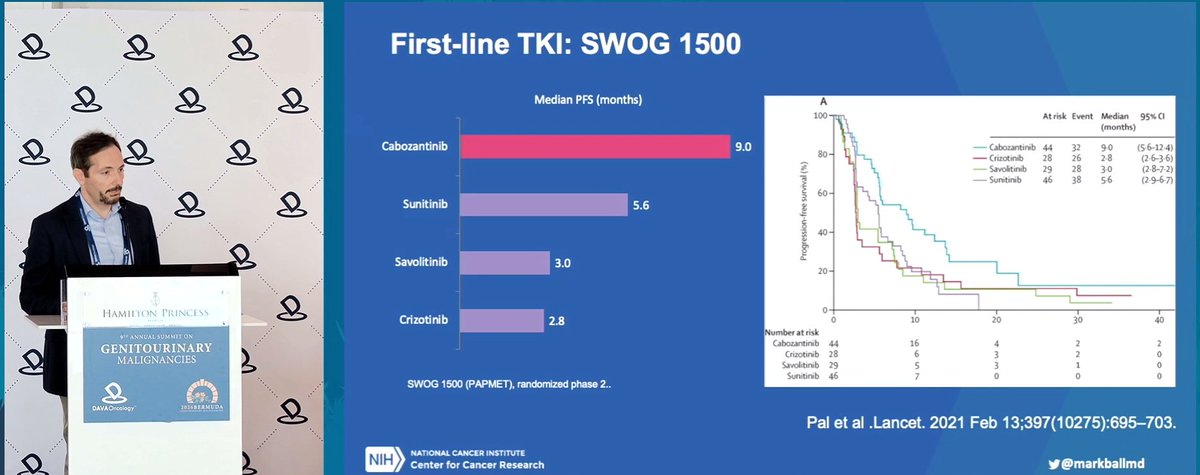
Dr. @markballmd of @theNCI reviews current approaches to papillary RCC, including PAPMET, KEYNOTE-B61 and phase 2 cabozantinib + nivolumab data, while highlighting molecular subtyping and MET-directed precision oncology as evolving strategies. CALYPSO: cRR was 32% overall and 53% in MET-driven papillary RCC; no new safety signals. #DAVAGU
Starting Soon: Advances in HIF Inhibitors in Advanced RCC
Moderator: Dr. Mark Ball @markballmd@theNCI
The session will explore belzutifan data (LITESPARK-011/033), emerging HIF-2α therapies & novel combination strategies in RCC.
#DAVAGU
With HLRCC, finding kidney tumors early matters. Yearly kidney imaging from age 8, often MRI, is recommended for people with or at risk of HLRCC. Ask your doctor what's right for you. Thanks to @markballmd and NCI for their work. Specialists: https://t.co/vMzpdGHVxl #HLRCC
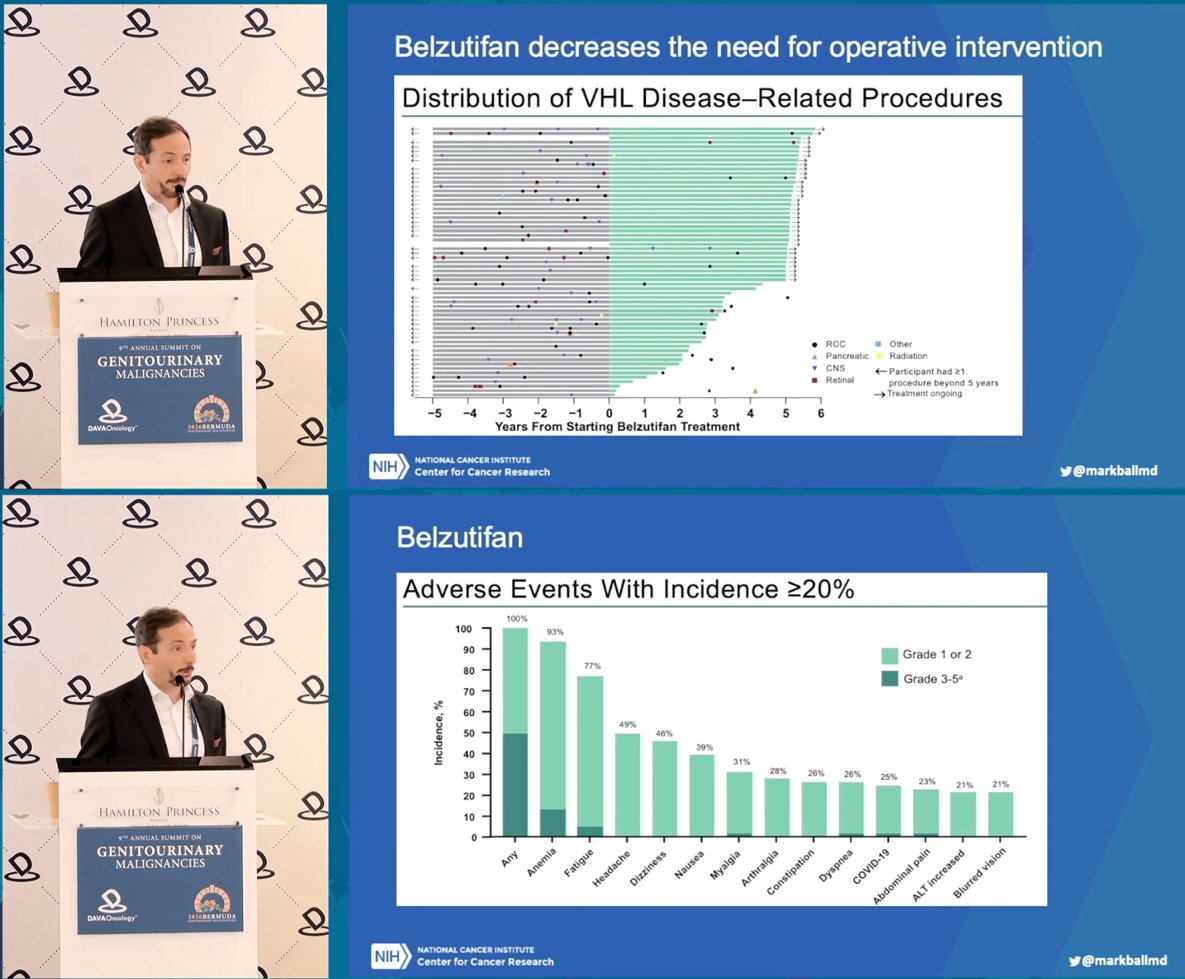
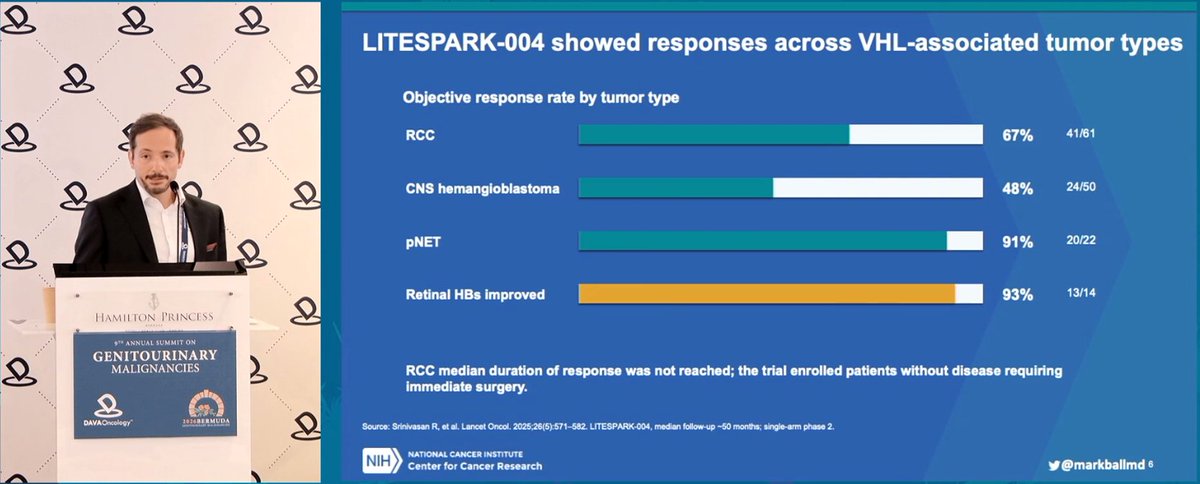
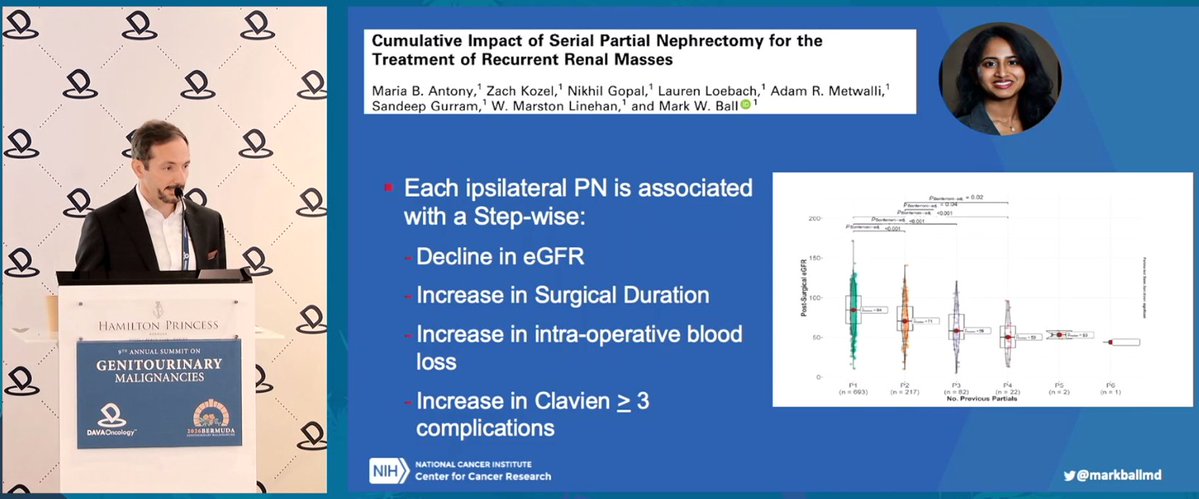
Surgery or belzutifan in VHL? Dr. @markballmd (@theNCI) weighs serial partial nephrectomy morbidity against LITESPARK-004 ORRs (RCC 67%, CNS HB 48%, pNET 91%) and discusses when tumorgrowth on belzutifan may warrant surgery. #DAVAGU
⚡️ On @EUplatinum 25-yr prospective NCI cohort of sporadic bilateral multifocal papillary RCC (n=89).
Growth was predominantly indolent (median 1.55 mm/yr). Metastases occurred only in patients whose largest tumor exceeded 3 cm. Repeat ipsilateral partial nephrectomy was associated with a decline in renal function.
Findings are consistent with active surveillance for small renal masses and nephron-sparing surgery when intervention is needed.
#KidneyCancer
https://t.co/scOxGzh8fO
🔬 What is the natural history of sporadic bilateral/multifocal papillary #RCC?
A 25-year prospective @theNCI
📈 Median growth: only 1.55 mm/year
⚠️ Metastases occurred in 6.7% — exclusively when the largest tumor was >3 cm
💡 These data provide important benchmarks supporting active surveillance for appropriately selected small tumors and nephron-sparing approaches when intervention is needed.
Congratulations to the authors for advancing our understanding of this uncommon clinical entity!
📖 Read here: https://t.co/FNxzMs9VVW
@HFu_MD@markballmd@SandeepGurramMD@montypal@kidneycan
@uretericbud Hmm…first thought is I don’t buy it. But if there is something there, AND this applies to previously biopsied pts, AND the effect is more pronounced in younger pts…what type of younger pts with SRMs are being biospied? More infiltrative, deep/high risk of radical? 🤔
Also a big shout-out to the @theNCI Urologic Oncology (SUO) fellowship 🙌
The fellowship gives us a platform not just to sharpen our operating, but to rethink GU cancer as a biology and a disease process. It also trains us to make careful, multidisciplinary decisions for every patient. NCI is a remarkable place to learn to think as a surgeon-scientist.
Our clinical year has been just as rewarding. We now rotate at Walter Reed, Sibley, GW, and MedStar Washington Hospital Center, which gives us broad exposure across the DC area.
Interested Applicants feel free to DM with questions!
@PeterPintoMD@markballmd@patmichael93@ztonysu@Moh_AhmedMD@Anis_Assad10@RubenBlachmanMD@SUO_YUO@UroOnc
#SUO #YUO #UroSoMe
@PGomellaMD It’s odd. Maybe it’s part of promotions activity. The other guy used to disparage fourth year medical students on AUA abstracts and he became a chair. 🤷♂️
Grateful for the chance to work on this unique project and share our experience. Big shout-out to the @theNCI@SUO_YUO@UroOnc fellowship — outstanding mentors, co-fellows, supportive staff, and a great city. Doing science and having fun. 🙌 @markballmd
New paper out in @EurUrolOncol! 🧬
We present the largest prospective cohort of sporadic bilateral/multifocal papillary RCC (89 patients, 25 years at the NCI).
Key findings:
📉 Slow, indolent growth (median 1.55 mm/yr)
🎯 No metastases when largest tumor <3cm
🔬 Low metastatic rate overall (6.7%)
🩺 Repeat ipsilateral partial nephrectomy = biggest hit to kidney function
Supports active surveillance for small renal masses + nephron-sparing surgery when intervention is needed.
@markballmd@RubenBlachmanMD@MillanBraden@patmichael93
Natural History, Tumor Growth Kinetics, and Renal Functional Outcomes... https://t.co/5dxZwl6Mbl
Thanks for sharing. Proud to finally show data to support the practice we have followed for a long time. @SUO_YUO fellow @HFu_MD put this together. Even when surgery is the the next step, my first ? is what life events do you have coming up - weddings, trips, etc. SRMs ≠ emergencies.
@EurUrolOncol
#kidneycancer ≠ automatic surgery
25-y prospective data from NCI @markballmd supports 3cm rule in bilat multifoc papillaryRCC
excellent onc outcomes & minimized cumulative harms of repeat tx
long-term natural-hist data to refine ##activesurveillance
https://t.co/tbBmUuN0O5
📅 New #Article in #Vol33_Iss8
📑 "Completion Nephrectomy Outcomes Following Prior Partial Nephrectomy in Hereditary Kidney Cancer Syndromes"
✍️ by Patrick D. Michael et al.
📍 Access the full paper here: https://t.co/0NuIu0OHcs
#HereditaryKidneyCancer#CompletionNephrectomy
📢We are pleased to announce that our 2025 IF is 2.8!
We extend our sincere gratitude to all authors, reviewers, readers, and members of the editorial team for their invaluable contributions and continued support!
#impactfactor@SUO_YUO@UroOnc@ElsevierConnect