passionate about Haematology, improving outcomes for myeloma patients. Also cycle +live in the most beautiful part of England and the best city in the world ...
So many great abstracts to be presented at ASH 2026. Here’s my top 10 in myeloma, with a focus on drugs with impending regulatory potential, novel agents/regimens, and updated data that’s relevant!
Let’s go!....
On Remembrance Sunday I spend the silence thinking of my grandfather who signed up aged 15, was wounded twice, survived and then spent 46 years as a Durham pitman. He survived when many didn’t and Remembrance Sunday was always an important day to us all especially him.
Useful side-by-side. The iber-dara-dex MRD-negative CR rate is impressive given about half of patients were len-refractory and 90% were IMiD-exposed, and it puts an off-the-shelf option near what we see with BsAbs and CAR-T.
The caution is the usual one: cross-trial comparisons, different MRD assays and timepoints, and MRD is a surrogate. As you note, PFS has to follow.
The next question is sequencing in practice. With this many options in early relapse, the choice will depend as much on what a site can deliver (CAR-T access, step-up monitoring, infusion capacity) as on the depth of response. We need a framework for that decision beyond MRD rates.
#MultipleMyeloma #IMS26 #mmsm
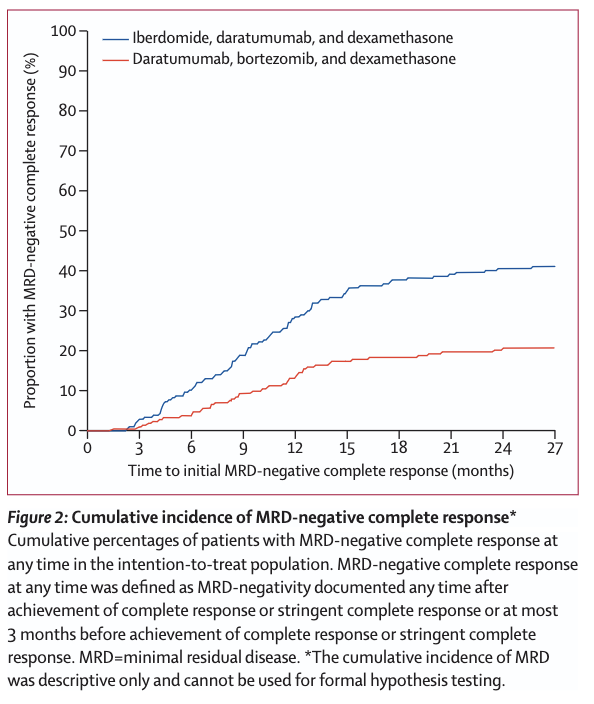
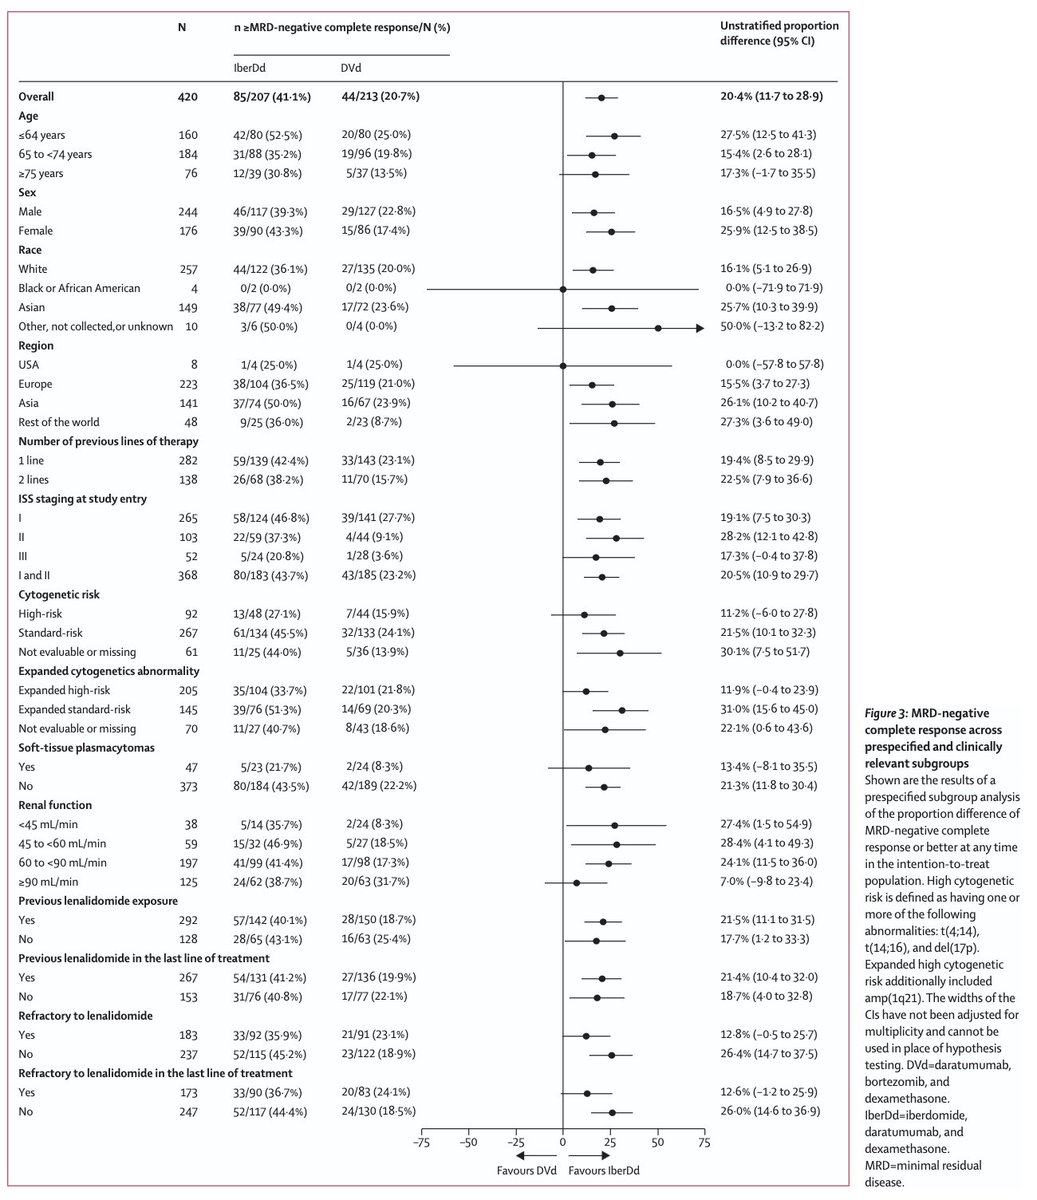
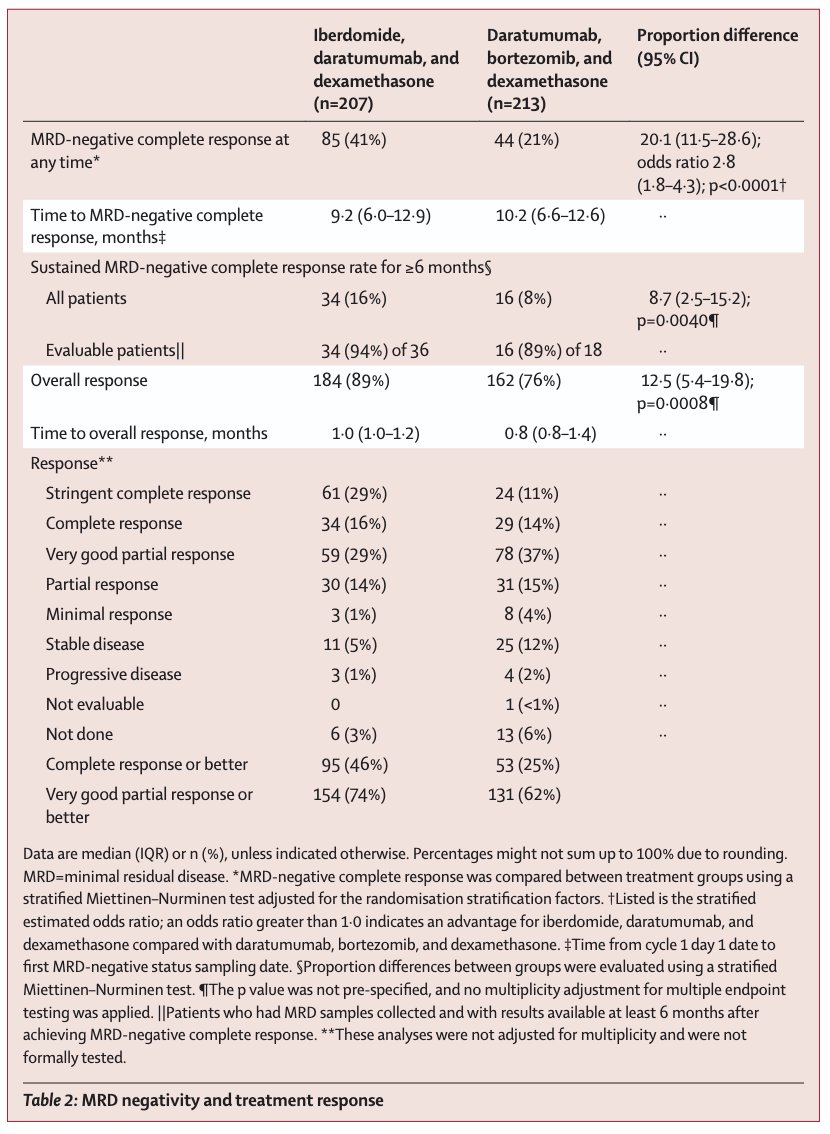
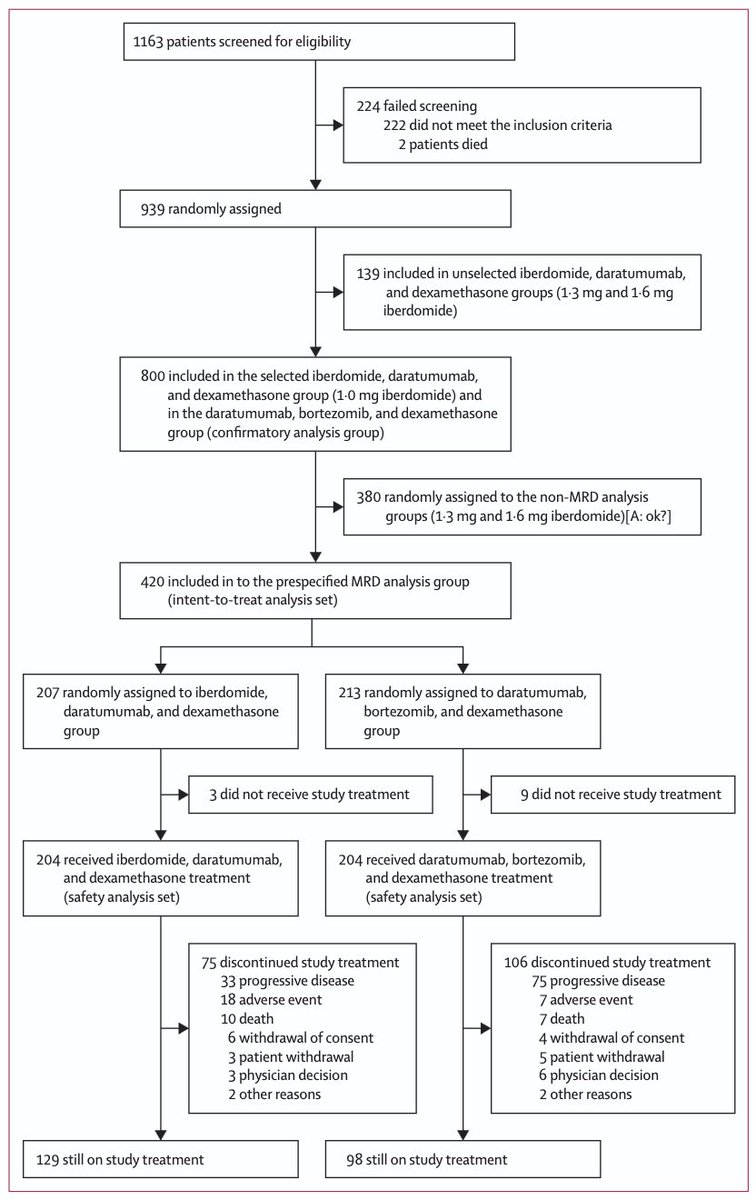
#Myeloma Paper of the Day: EXCALIBER-RRMM phase 3 of iberdomide/dara/dex vs dara/bortez/dex shows (median follow-up 15.7 mos) MRD- CR in 85 (41%) vs. 44 (21%); grade 3-4 AEs in 187 (92%) vs 143 (70%), neutropenia (84% vs 11%) & infxn (39% vs 22%): https://t.co/VQrAqPwxzU. #mmsm
Reflecting on the key themes of #IMS2026
- >5 yr remission for newly diagnosed and >3 yrs in relapse for most MM is becoming the standard
- High Risk MM is still a challenge, immunotherapy is key. Paucity of data in EMD and PCL. Agree with @VincentRK in adding PCL to HR definition
-Access is key- after meeting with several drug manufacturers, this is being thought of in the design, clinical trial, execution both for CART and BsAb. Can every patient get this within 60 miles of their home.
- TRM is more important esp. in the first 6 months
-Less is more- Newer CART's have lesser CRS, ICANS and newer BsAb's have less intense dosing schedule with lower CRS
-Dual Ag targeting is A way forward, a/w how it compares against good single agent targets
-There is a paucity and some progress in understanding rare toxicities- Colitis, cerebellar syndromes, oral toxicities, rare infections
-if we are going to give subsequent immunotherapies, we need to be more precise, with sequencing and T cell fitness, both of which are still in its infancy in MM
-Except celmods there are no other non targeted therapies [non BCMA, GPRC5, FCRH5]. Is this enough ? [I am aware of others but none in Ph 3]
-Cure - covered by @Mohty_EBMT already
Thx for the organizers @profghjackson@NikhilMunshiMD@NoopurRajeMD@IMFmyeloma for a wonderful meeting and looking forward to next year
OPTIMUM/MUKnine trial for HRMM: 5-year F/U. N=107, >/= 2 HRCA, HR GEP or PCL. RX: D-CVRd + ASCT + D-VRd + DR. With~6-year F/U, median PFS and OS not reached. In controls from Myeloma XI PFS/OS were 24.4/57.4 months #mmsm #bmtsm @T@TheLancetOncol@MyMKaiser https://t.co/tVeTeFyLiH
#IMS26 great empiric validation by Avigan et al of core IMWG/IMS principle for curing myeloma:
sMRD neg at 10^-6, not 10^-5, despite unequal 🌏 access to this depth.
Despite sMRD neg x24 mo, using 10^-5 portends much higher relative risk of late relapse. Get 10^-6 on board!
So, what should we take home from #IMS2026 in Glasgow?
This meeting illustrates a remarkable convergence. Basic science is revealing new vulnerabilities. Translational research is teaching us how to recognize pts with durable disease control. And clinical trials are showing that we can achieve unprecedented depth of response while beginning to ask a very different question: not only how much treatment can we give, but how intelligently can we use it, and when can we safely stop?
The word “CURE” was heard repeatedly. We should, of course, use that word carefully. In some settings, cure remains a statistical construct based on modeling. In others, it is beginning to emerge clinically as years of treatment-free survival in patients with sustained, deep MRD negativity.
But what is no longer in doubt is that the ambition has changed.
We are no longer discussing only how to prolong survival.
We are beginning to discuss how to achieve extremely durable disease control, and perhaps, for an increasing number of them, how to cure myeloma.
Thank you @Myeloma_Society@myelomaMD@NikhilMunshiMD@NoopurRajeMD@profBigG@ceriannbrown@profghjackson@mvmateos and P Moreau for a superb meeting. @TheIACH@COMyCongress
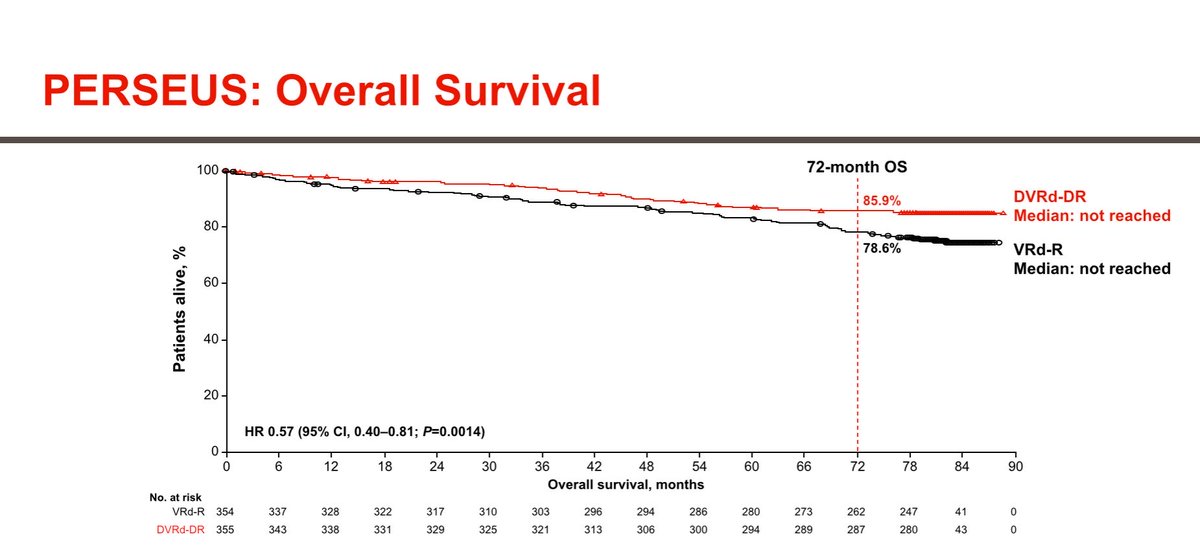
PERSEUS is the gold standard benchmark outcome for Newly Diagnosed Myeloma
6 year overall survival: 86%
6 year PFS 81%
with quad induction and Dara-Len maintenance.
As we test bispecifics, ADCs, CARTs etc, any new approach should be better. A new therapy CANNOT have even 5% all cause mortality in first 4 years.
There is no room for error with infection related mortality. No early drop off. No learning curve. As a field we have to establish preventive measures to prevent infection related deaths. #IMS26
Cassiopeia trial
One of the first trials of Quad therapy and two randomization. Shows some interesting data points
Evolving p value signifance from what we knew few yrs ago
Certainly an older Imid ; but value in LMIC ? Can we just do quad and not have any Dara afterwords ?
#IMS26 #mmsm @Myeloma_Society
Phase I results of Anito-cel and d-domain story published in NEJM! Exciting results and very delighted to be a part of this study @MedicalCollege@MCWCancerC2u8v
#IMS26 Elegant (post hoc) MajesTEC-3 analysis by @End_myeloma
Unlike other myeloma drugs, I bet real-world tec-dara OS will look *better* than MajesTEC-3 did.
Why? Because we now know PPx toci, PPx IVIG, etc - early BsAb deaths can be prevented, vs fatal PD with Dara-Pd can't.