Tremendous work by @drchrisyu@Coleenten to bring this pilot data together. This data along with feedback from the international #cardioonc community helped us design the ongoing RCT NCT061883437. Grateful for support of many colleagues & @CIHR_IRSC@ICOSociety@PMunkCardiacCtr
Dear #cardiooncology colleagues,
We are planning a RCT to test less frequent cardiac imaging during HER2 targeted therapy for #breastcancer. We want your input re study design. It will be of great value.
Pls consider completing a 5-min questionnaire at https://t.co/q81wrmFomE
1/2 Thanks Ron! I think you summarized our work perfectly "good rationale for RCT" – exactly as our conclusion. Given observational study, we used best poss methods (propensity matching, controls receiving a non-SGLT2 medication) to reduce confounding - impossible to eliminate.
Caveat emptor! These are observational data and patients were quite different, so should NOT start using SGLT2I' without current indications. Pls read the important limitations of this analysis.
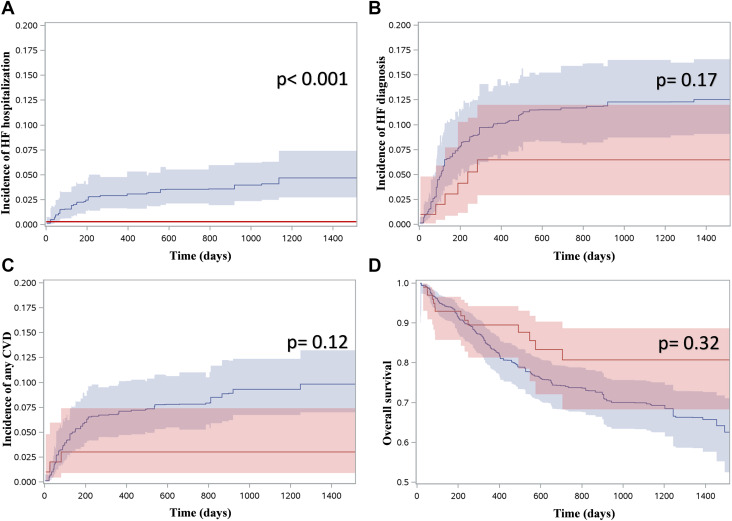
There were no safety signals. HR for death trended towards benefit (HR 0.63; 95% CI 0.36-1.11). Diabetes compl'ns, incl ketoacidosis, were rare. This is an underestimate of what to expect in RCTs as patients were stabilized on SGLT2I & admin data are less sensitive for these dx.
There were no hospitalizations for HF in the SGLT2i group (HR zero!). The HR any HF diagnosis indicated possible benefit (HR 0.55) but confidence intervals crossed one so the difference was not statistically significant.