For over two decades in different roles, I have seen Pakistan as a source of solidarity & solutions. But what has always stood out to me is the resilience of the Pakistani people & their determination to build a better future.
My message is simple:
The @UN stands with the people of Pakistan. And I thank the Pakistani people for standing up for the world.
Radiology used to have something that was almost invisible because it was so routine:
The reading room consult.
Rounding teams came down.
Surgeons pulled up their cases.
Internists brought the scan that didn't quite fit the clinical picture.
Sometimes the radiologist solved the problem.
Sometimes the clinician supplied one piece of history that completely changed how the images were interpreted.
And usually everyone simply walked away a little sharper.
But something else was happening during all of those conversations.
We were learning each other.
As a radiologist, I learned what individual physicians cared about.
I knew which findings mattered to a particular surgeon.
Which measurements an oncologist was following.
Which details a specialist wanted emphasized.
What questions they were really asking, even when the order just said "pain."
And they learned me.
They knew who was reading their study.
They knew they could walk in, point at something, challenge an interpretation, or ask, "What do you think?"
That relationship created context.
It created feedback.
It created trust.
And over years, it created a kind of institutional knowledge that never appears in the medical record.
When radiology becomes a report produced by someone hundreds or thousands of miles away, we don't just lose proximity.
We risk losing that entire feedback loop.
The report may still be technically excellent.
But the radiologist knows less about the physician.
The physician knows less about the radiologist.
The radiologist sees less of what happened after the report.
And both sides lose opportunities to make each other better.
The reading room was never just a room.
It was where imaging became part of the clinical conversation.
We should think very carefully before designing that conversation out of medicine.
Inspired by a conversation yesterday with @PaleoOnc . Also @909One and @brianchiong .
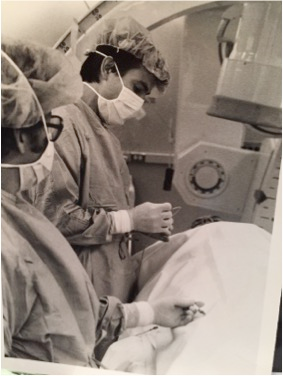
International Day for Interventional Cardiology: the first coronary #angioplasty
On 16 September 1977, Andreas Grüntzig & his team made history, and changed the lives of millions of patients forever.
Standing on the shoulders of the giants that came before him, this transformative vision led to an entirely new field of medicine.
What began nearly five decades ago with coronary angioplasty has grown into the broad field of interventional cardiology, transforming cardiovascular care through research, innovation and technological progress.
As the field has evolved, so has the need to learn from experience, share knowledge and shape what comes next. Join us in 2027 at #EuroPCR to mark this landmark moment!
📅https://t.co/OPA8J77TJ0
#medicalhistory #interventionalcardiologist #cathlab #cathlabteam
@NievesGonzalo1@CuissetDr@nicolasdumonte1@EmanueleBarba13
BIG NEWS: CMS final TAVR coverage decision, biggest change to TAVR coverage since 2012.
Here’s my summary from the long 105-page statement:
- Symptomatic severe aortic stenosis is now covered as standard care. No mandatory registry enrollment.
- Asymptomatic severe aortic stenosis is newly covered, but only for patients enrolled in Medicare-approved studies.
- The heart team stays. Every patient still needs input from both cardiac surgery and interventional cardiology (can be done through chart review), plus an in-person visit with one TAVR operator before the day of the procedure.
- The two-operator requirement is gone. Now one qualified operator can do the case alone.
- Two operators are still covered if the heart team decides they’re needed and that can be in any combination: surgeon + interventional cardiologist, two interventional cardiologists, or two surgeons.
- Volume requirements now apply to the operator, not the hospital: at least 20 transcatheter valve cases a year (15 of them TAVR).
- Hospitals still need on-site cardiac surgery program.
@6ayyeboon@AlkashkariWail@mirvatalasnag@BinAbdulHak_A@amrmohsen213@MarwanSaadMD@aelsab@MusaSharkawi@MohammedQintar@mhammadah@JDDCFratti@acamajmd@Almanfi_Cardio@scottiejj12
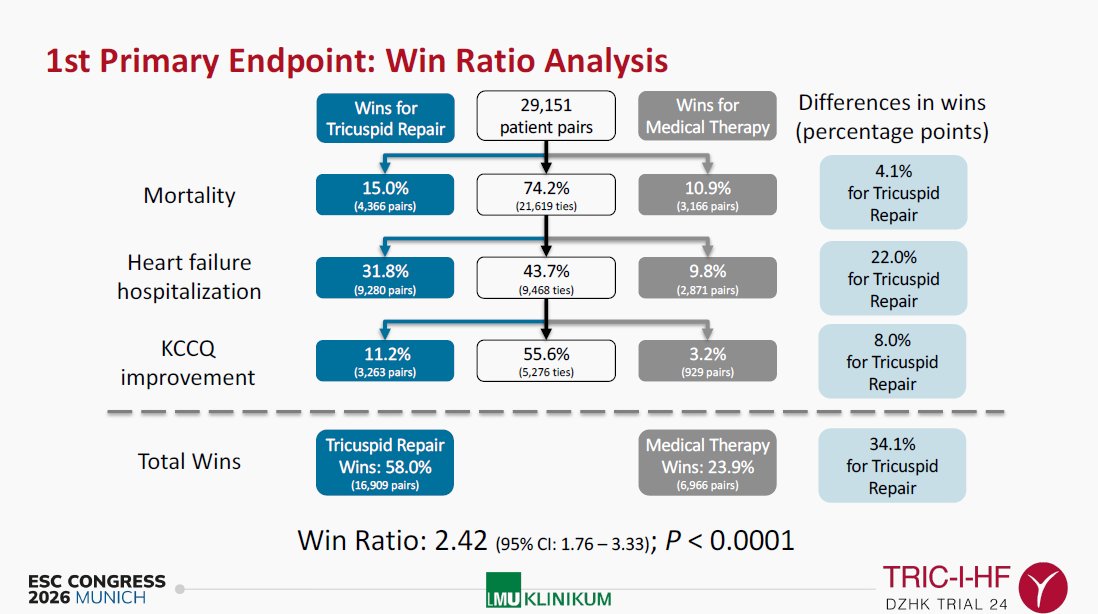
TRIC-I-HF trial: Transcatheter tricuspid repair plus medical therapy achieved a superior win ratio for mortality, HF hospitalization, and KCCQ improvement over medical therapy alone in patients with severe TR. Download slides here: https://t.co/AkV8t7dXZ8
Presented at #ESCCongress:
In patients with severe tricuspid regurgitation and heart failure, transcatheter tricuspid-valve repair plus medical therapy was superior to medical therapy alone in reducing hospitalizations for heart failure and deaths. Full TRIC-I-HF trial results: https://t.co/zJpLtFsASP
@escardio
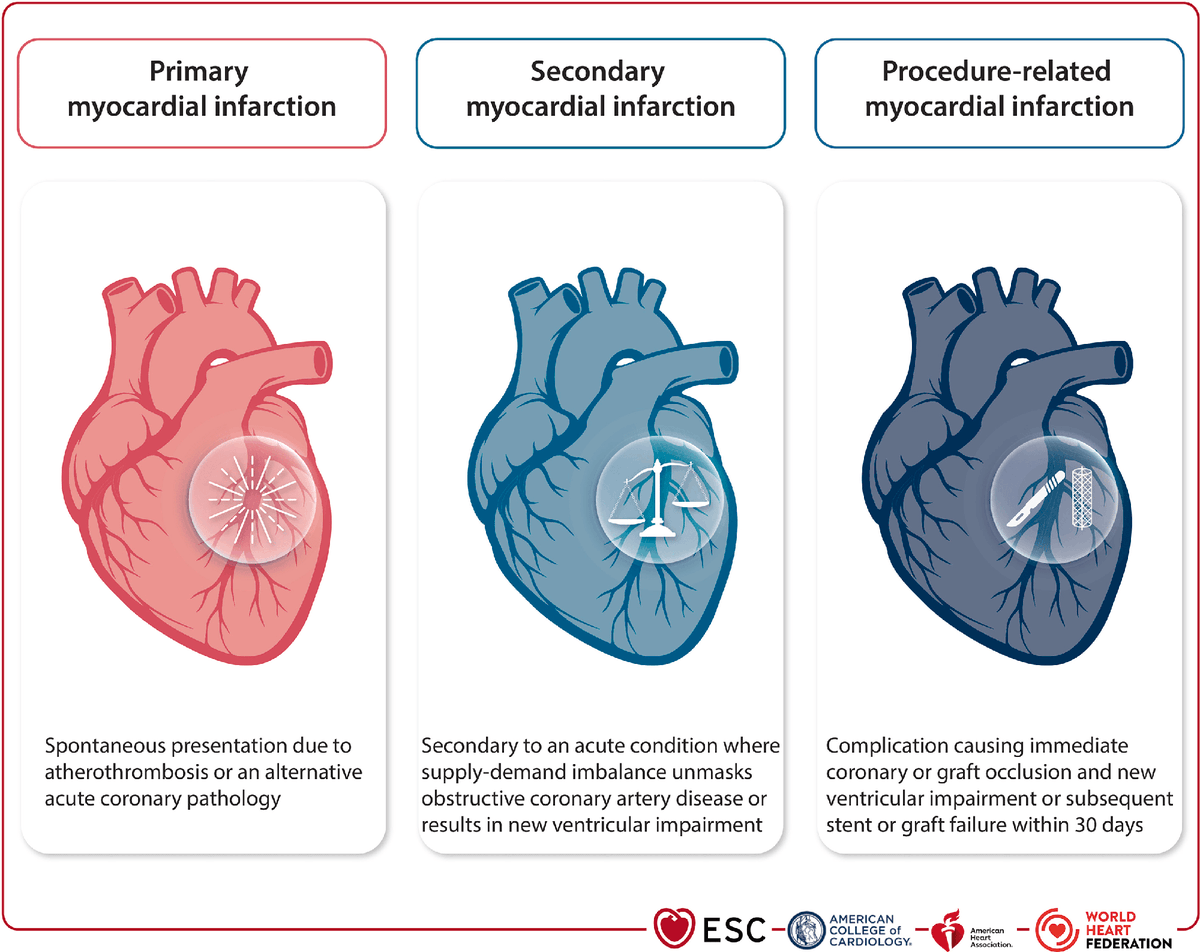
The Fifth Universal Definition of #cvMI, released by 🌏 CV societies, provides a 🆕 clinical classification of MI that is based on pathophysiology, aligns w/ clinical evaluation of patients & incorporates objective diagnostic criteria.
🔗 https://t.co/bfPRH5Ttbq #ESCCongress
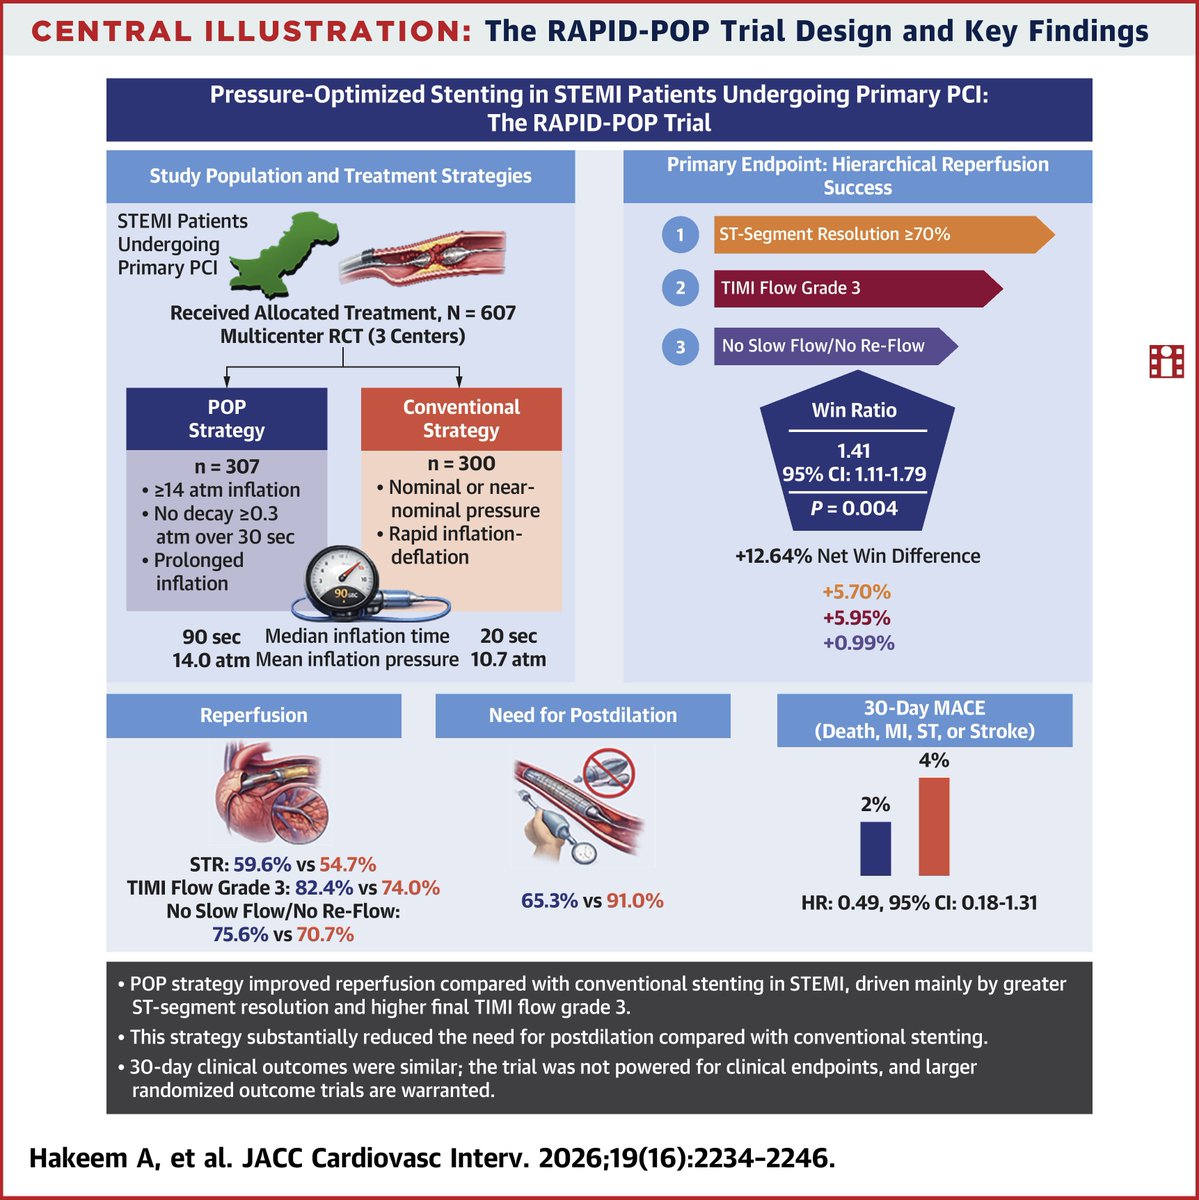
In the RAPID-POP RCT (n=607 #STEMI patients), pressure-optimized stent inflation improved reperfusion vs conventional inflation-deflation (WIN ratio 1.42; P=0.004), with less post-dilation & a trend toward lower 30-day #MACE (2.0% vs 4.1%). https://t.co/KKcR9RJWNs #JACCINT#PCI
Out in JSCAI today, our study examines 25 years of aortic stenosis–related mortality in the United States.
While overall aortic stenosis–related mortality has declined modestly, important disparities persist — particularly among men, adults ≥85 years, residents of nonmetropolitan areas, and individuals living in the Midwest.
Our findings highlight that improving outcomes in aortic stenosis is not just about advancing treatment — it is also about earlier recognition, timely referral, access to care, and addressing disparities in cardiovascular health.
Grateful to Drs. @mj_ricciardi and @AqamarMD for their guidance and mentorship!!
Read: https://t.co/FpHOc5gzhN
@LAzzaliniMD@JACCJournals Thank you for your analysis.
Dr. @LAzzaliniMD I always wondered is it possible that LOPP is an indicator that lowering EDP by force AKA taking away the “stretch forces” we learned in school is problematic leading to loss of pulsation?
A faculty member cut her research effort in half over three years. No one told her to. The comp plan did it for her. RVU-only compensation has destroyed more research capacity at academic medical centers than any funding cut.
Successful TAVI implantation relies on much more than accurate valve positioning, it requires an understanding of the relationship between the prosthesis and the cardiac conduction system.
@TAVRBot#cardioed#cardiotwitter
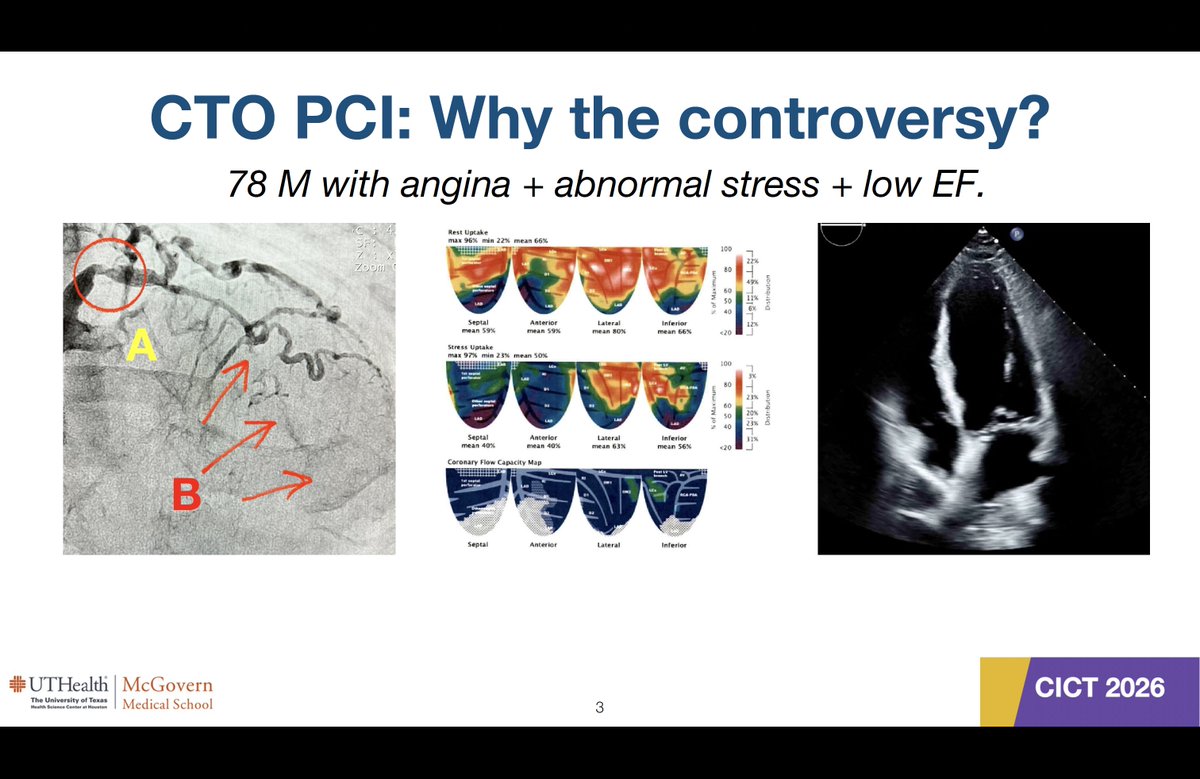
Proposition - OPTIMA-CTO Leaves No Doubt: CTO PCI Improves Symptoms
This was the title of my talk at #CICT2026 last week. I was debating good friend and fellow CTO enthusiast, @jbspadoni.
I only had 8 minutes - so a sophisticated analysis a la @SripalBangalore, @djc795, or @ihtanboga was out! 😅
Here are the slides...
@realarainmd@Hragy@GreggWStone@djkereiakes Great points as always and insightful❤️
- 90–100 ů experienced early arterial recoil, especially as thy broke down. PLA-based options like BVS tend to “collapse” (early discontinuity).
- “Pulling” force can possibly be explained by Bernoulli principle if any. Rest is pushing.
@realarainmd@Hragy@GreggWStone I’m curious if “stent” might be compared to these scaffolds.
Arterial recoil is always a factor—once the core weakens, the scaffold can ?collapse. We’ve seen this with POBA, and maybe DCB could face similar issues.
@djkereiakes might have some great insights here!
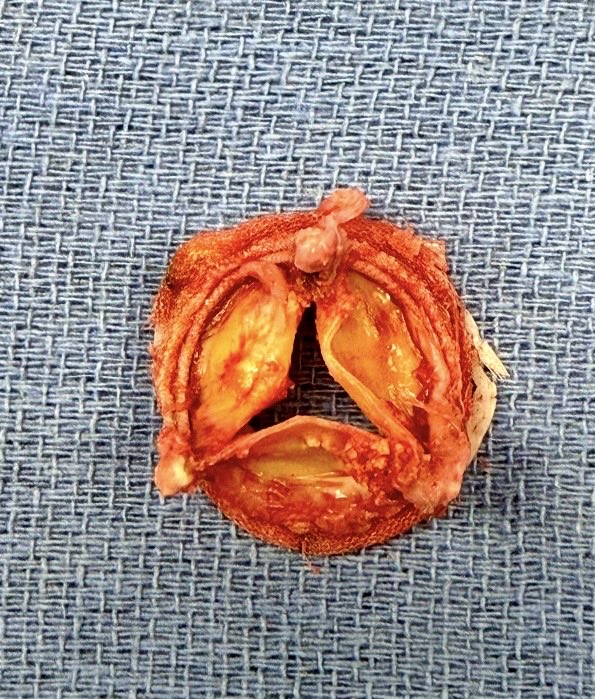
#inspiris implanted 6 years ago. There is very little clinical data to suggest this valve will be as durable as it's predecessor, Magna or MagnaEase. But certainly more expensive. @tomcnguyen@DrZeigler1@Abedeanda@APolancoMD