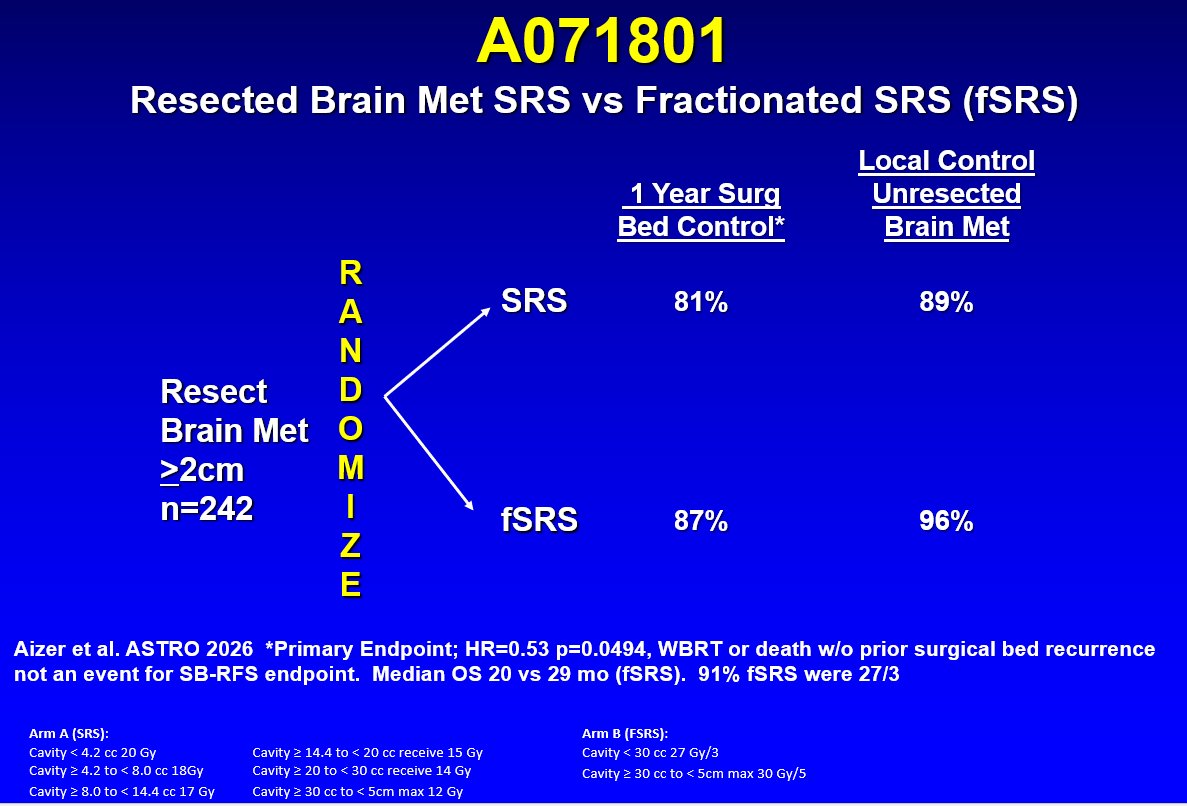
🚨🚨 Randomized Trial #ASTRO26 Resected Brain Met fractionated SRS vs single fraction SRS post-op cavity 🚨
• fSRS superior surgical bed control
• No diff AEs
• fSRS standard of care for resected larger brain met
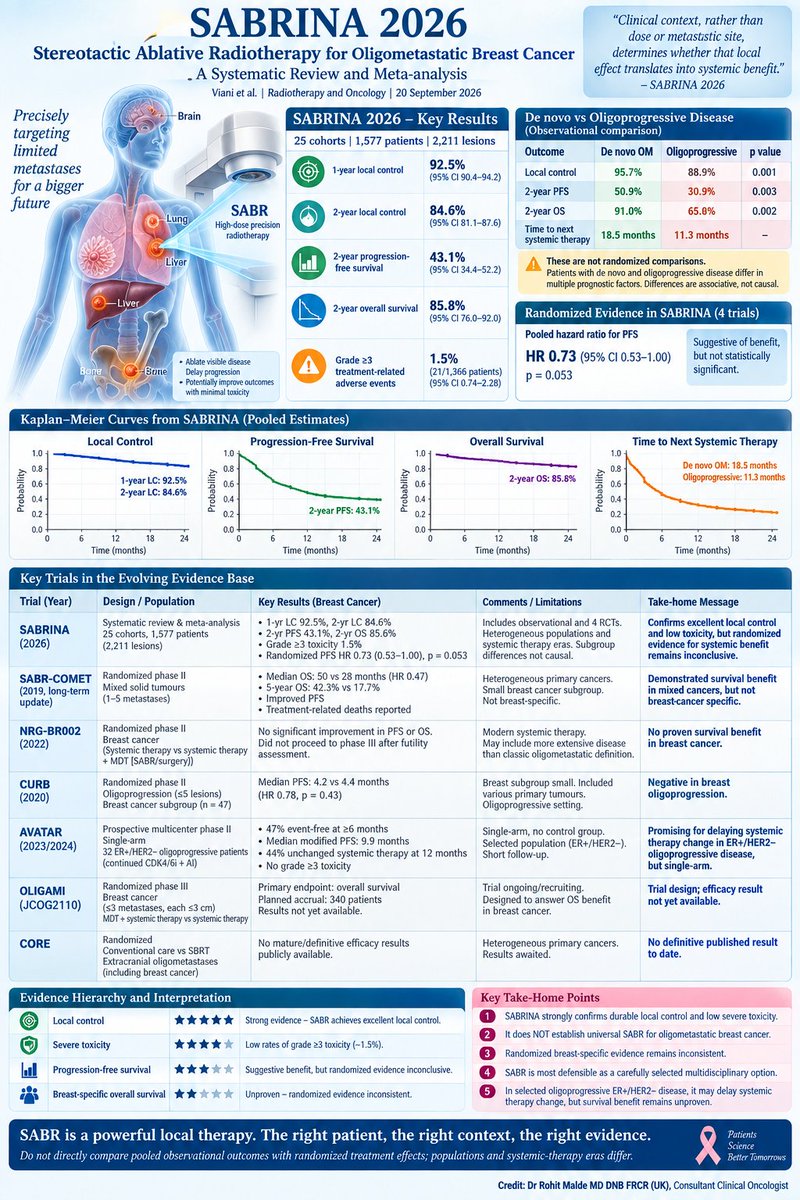
SABRINA 2026
Stereotactic ablative radiotherapy for oligometastatic breast cancer: a systematic review and meta-analysis
DOI 10.1016/j.radonc.2026.111789.
25 cohorts, 1,577 pts, 2,211 lesions
Good Local Control
minimal Toxicity
De.novo better than Oligoprogression
Highly practical ESTRO guidelines. Re-RT for locally recurrent rectal cancer should no longer be the "exception."
W thoughtful planning, re-RT (often 30–40 Gy BID, w SBRT in select cases) can safely 1) improve resectability, 2) definitively tx or 3) palliate symptoms. @OncoAlert
Adjuvant RT may finally be back in bladder cancer.
The phase III BART trial shows that modern pelvic IMRT after cystectomy significantly improves locoregional control in high-risk MIBC. 🚨
🇮🇳 Multicenter randomized trial
153 patients
90% received perioperative chemotherapy
🩻 Adjuvant RT vs Observation after radical cystectomy
📌 2-year LRFS
87.1% vs 76.0%
HR 0.43 (P=.04)
📌 2-year DFS
71.6% vs 58.7%
📌 2-year OS
70.4% vs 57.4%
Most striking finding:
❌ No isolated pelvic recurrence after adjuvant RT.
Despite historical concerns, toxicity remained low with modern IG-IMRT:
⚠️ Grade ≥3 acute toxicity: <5%
⚠️ No major increase in severe late toxicity
This is important because pelvic failures after cystectomy are often devastating and rarely salvageable.
The study strongly reopens the discussion around integrating pelvic RT into multimodality care for high-risk bladder cancer, especially in the modern immunotherapy era.
Could adjuvant RT + IO become the next frontier in MIBC?
📖 Full paper in comment ⬇️
#OncoTwitter #MedTwitter #BladderCancer #RadOnc @ASCO@myesmo@esmo_o@OncoAlert
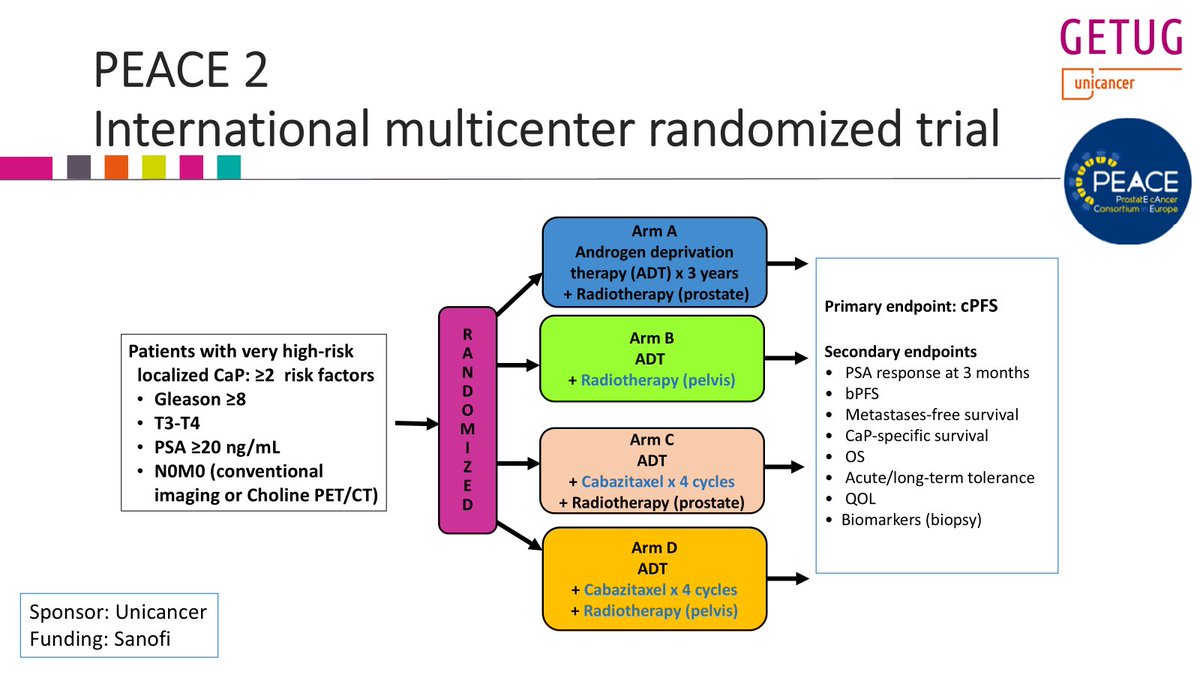
Yesterday, I presented the @GETUG_Unicancer PEACE 2 trial at #ESTRO26 on the role of pelvic RT in very high risk #prostatecancer pts (staged with conventional imaging).
Twittorial below
Key conclusion: pelvic RT did not improve clinical outcomes (cPFS, MFS, PCSS, OS)...
1/n
Dose–volume effects link multiple cerebral substructures to cognitive decline. Neurocognitive toxicity reflects distributed network injury beyond the hippocampus.
@ESTRO_RT CNS focus group on @RO_GreenJournal https://t.co/JptGO6G4zu
Here is Version 2.0 of when to hold systemic tx during RT. Updated & w 3 additional drug categories (ADCs, CDK4/6 inhibitors, PARPi).
More details on newer drugs in 🧵 below.
Please use this version as reference & thanks for all input/experience crowdsourcing! (1/3)
@ASTRO_org RPT Symposium kicked off in Palm Desert with Johannes Czernin from @UCLAHealth serving up a fantastic keynote on PSMA imaging & therapy, following Stephen Hahn’s inspiring keynote on innovation & teamwork. Exciting 2 days planned‼️ #MRPTS26#radonc
Do we always need upfront systemic therapy in oligometastatic disease?
This meta-analysis in @JAMANetworkOpen suggests not.
SBRT achieved 70% systemic therapy free survival at 1–2 yrs, rising to 78% in prostate & 87% in renal cancer, with low toxicity & preserved QoL.
Appropriate pt selection & tx sequencing matter.
https://t.co/NDu4xq2AIV @OncoAlert
🚨 ESTRO–ASTRO call for a paradigm shift in breast RT! 💥
📘 ESTRO Recommendations on Preoperative RT in Breast Cancer
-endorsed by @ASTRO_org & @myESMO
🔹 Why now?
Modern RT = safer, precise, hypofractionated
→ Time to rethink the “surgery-first” dogma 🔄
🔹 Potential advantages:
✅ Early-stage: sharper target, smaller volume
✅ Locally advanced: ↑pCR, ↑BCS conversion
✅ Pre-mastectomy: better reconstruction outcomes
✅ Synergy with IO, PARPi, CDK4/6i
✅ Possibility of surgery omission in select pts
🔹 Key data (27 studies, 2006–2024):
• pCR 4–60%, up to 71% in TNBC
• Feasible with modern IMRT/VMAT/SBRT
• Acceptable toxicity; fibrosis 9–13%, OS >90%
🔹 Still investigational — Phase III trials needed (Neo-RT, TOPAz, Neo-CheckRay, P-RAD…)
💡 Preop RT may reshape breast oncology-one protocol at a time.
What are your opinion is on this , please comments and let’s discuss⤵️
📖Zamagni et al. Radiother Oncol. 2025.
🔗 https://t.co/DAnDzDkYP9
#OncoTwitter #BreastCancer #RadOnc @ASCO@ASTRO@myESMO@ESMO_Open@OncoAlert
How far can we go with #reirradiation in #gliomas ?
Practical guidance from current evidence.
check our latest publication ⤵️
✅ https://t.co/0DvV4EZPbu
Important re-irradiation lesson for #radonc residents: when you look at your DVH in EQD2 (like in MIM), the "V20" that you need to look at will change.
Here's a DVH from a 60/30 plan shown as physical dose vs. EQD2. The DVH looks much better below 60 Gy & a bit worse above it.