He was a mentor
But departing from evidence, he had my dad w new angina wait 4wks for CABG: Cath/IVUS had shown 70% LM, tight ostial LAD+LCx lesions, RCA occlusion
My beloved dad died before CABG
The ensuing silence left me w #lessons I carry everyday1/
https://t.co/vxkKTIeenh
I am very pleased to share our latest publication as first author on management of coronary artery perforations in the Journal of American College of Cardiology(JACC).
Stepwise, case-based review from our UK centre.
🔗 https://t.co/gqxX7DSjIW
#JACC#cardiology#intervention
🧵 1/ First ever AHA/ACC/multi-society guidelines re: diagnosis & management of acute PE released today!
2 year effort with 38 authors from 10 specialties.
Link attached & summary in this thread:
https://t.co/uUUyUvz3pR
This state-of-the-art review provides an updated, physician-focused overview for PCI and CABG operators, summarizing evidence on established lipid-lowering therapies, emerging strategies to address residual lipid risk, and the evolving role of anti-inflammatory interventions in the comprehensive management of ASCVD. https://t.co/pGckwYIFhR
Boston.
700,000 people.
Home to some of the most celebrated academic medical centers on earth.
One ambulatory surgery center.
Senator Warren’s state banned ASCs for 47 years. Then gave health systems veto power over any that tried to open.
Do you know how Massachusetts tried to solve
healthcare?
They send all patients to the highest acuity health systems and bill them for the highest codes and then wonder why premiums are high.
This is the senator who wants credit for fighting the healthcare monopoly.
5 Pericardiocenteses over the last week (random 🤷♂️). My technique/approach: patient up at 30-45 degrees, sub-xiphoid, Echo and Fluoro, micropuncture, agitated saline injection, drain through radial sheath, suture sheath, foley anchor on drain. What’s your technique?…
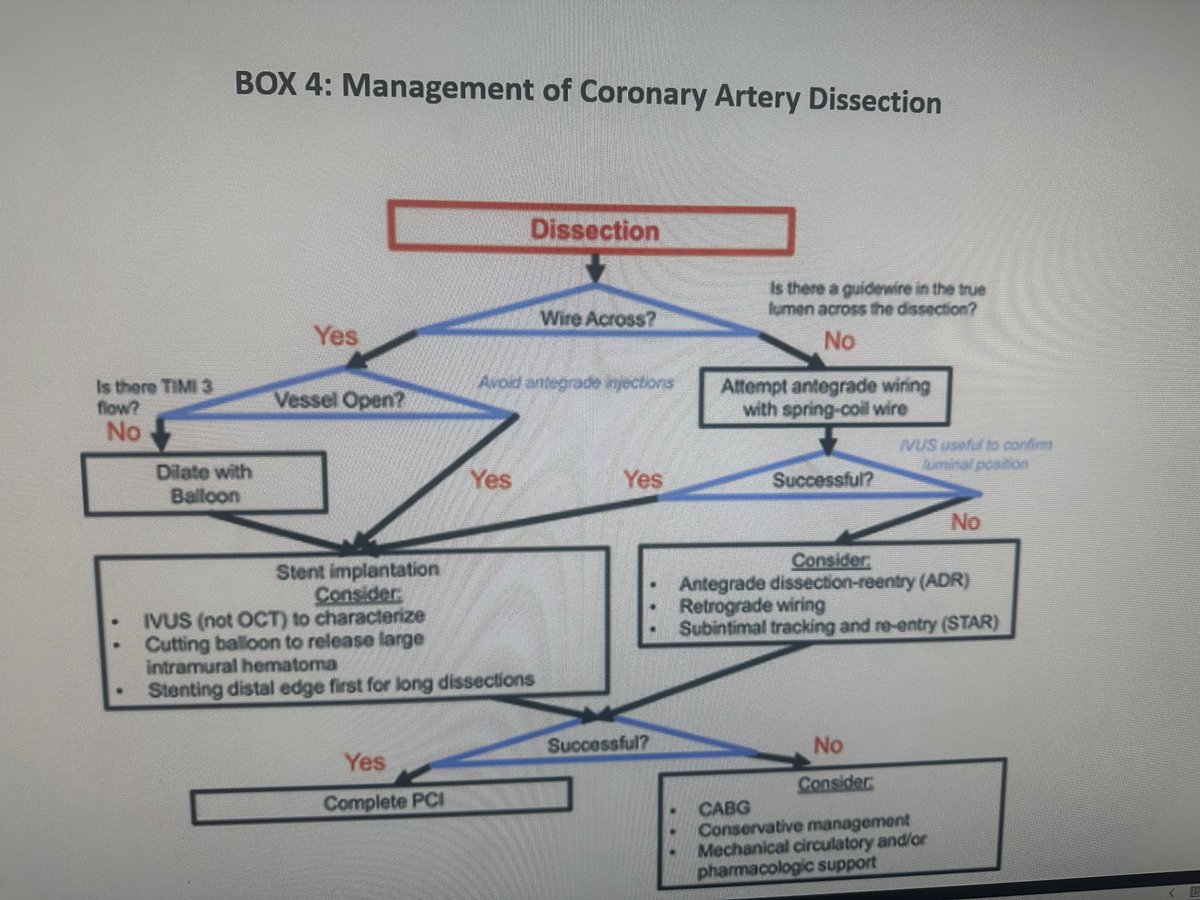
Coronary dissection management depends upon patient’s hemodynamics, dissection type & if wire across is present. If wire position is lost, use multiple wires to find the true lumen aided by IVUS. @PurumittalDr @benhibbertMDPhD Ben has published the largest series
Stenting the RCA ostium. But the stent is not where it was supposed to be but is floating around the guiding catheter in the aorta. Has anyone seen something like this? How could that happen? The stent is Megatron 4,0/8 mm, the guide is 6F Launcher. ##cardiotwitter@PCRonline@AGIKinterv
PS. The stent was retrieved easily, a new one was implanted w/o any issues with a good result
The final angio speaks for itself, but let us just say, well done Dr. Khurram Rasheed & Dr. @QasimMalikMD at @mystlukes in Bethlehem, PA! Beautiful result with kissing 7.0x60 #ShockwaveM5 balloons in heavily calcified iliacs.
ISI https://t.co/Q2peu4kDd6 #VascTwitter#ShockwaveIVL
@jtsaxon Knowing insurance companies, this “insurance TSA precheck” physician will be further scrutinized and made to wait even longer on hold so as to bring down his test approvals/annoy them..
@nyuniversity, how can you support this racist opinion piece by your faculty Lawrence Mead? I take offense to this, having read every sentence, left horrified. See excerpts below. This should be retracted. Shameful. https://t.co/s62Tab4GfY
1/7 Vascular Access for Shock-MCS. Do it the same way every time (“slow is smooth, smooth is fast”). Fluoro Femoral Head. US-guided Micropuncture access, observe micro wire advancement, perform access site angiogram (with wire left in), Preclose (single Perclose)...