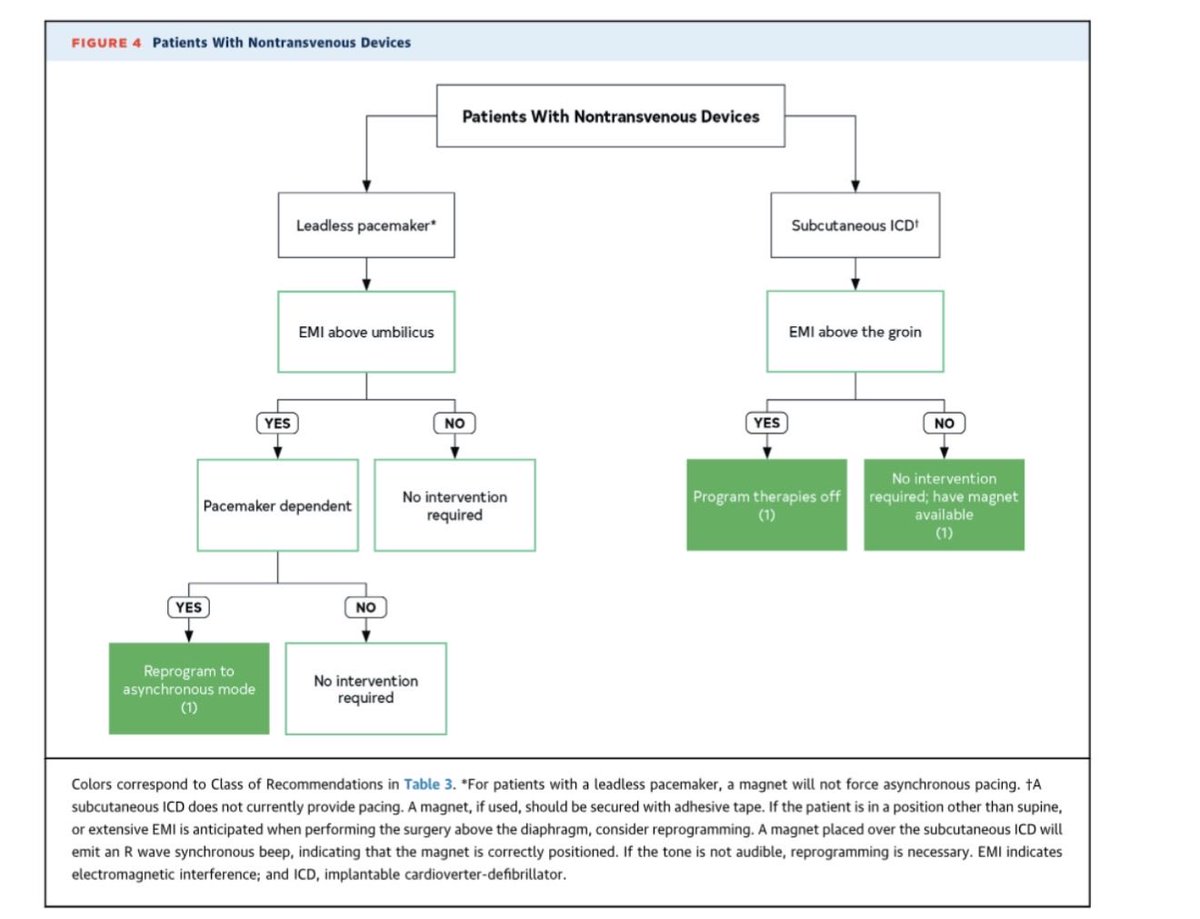
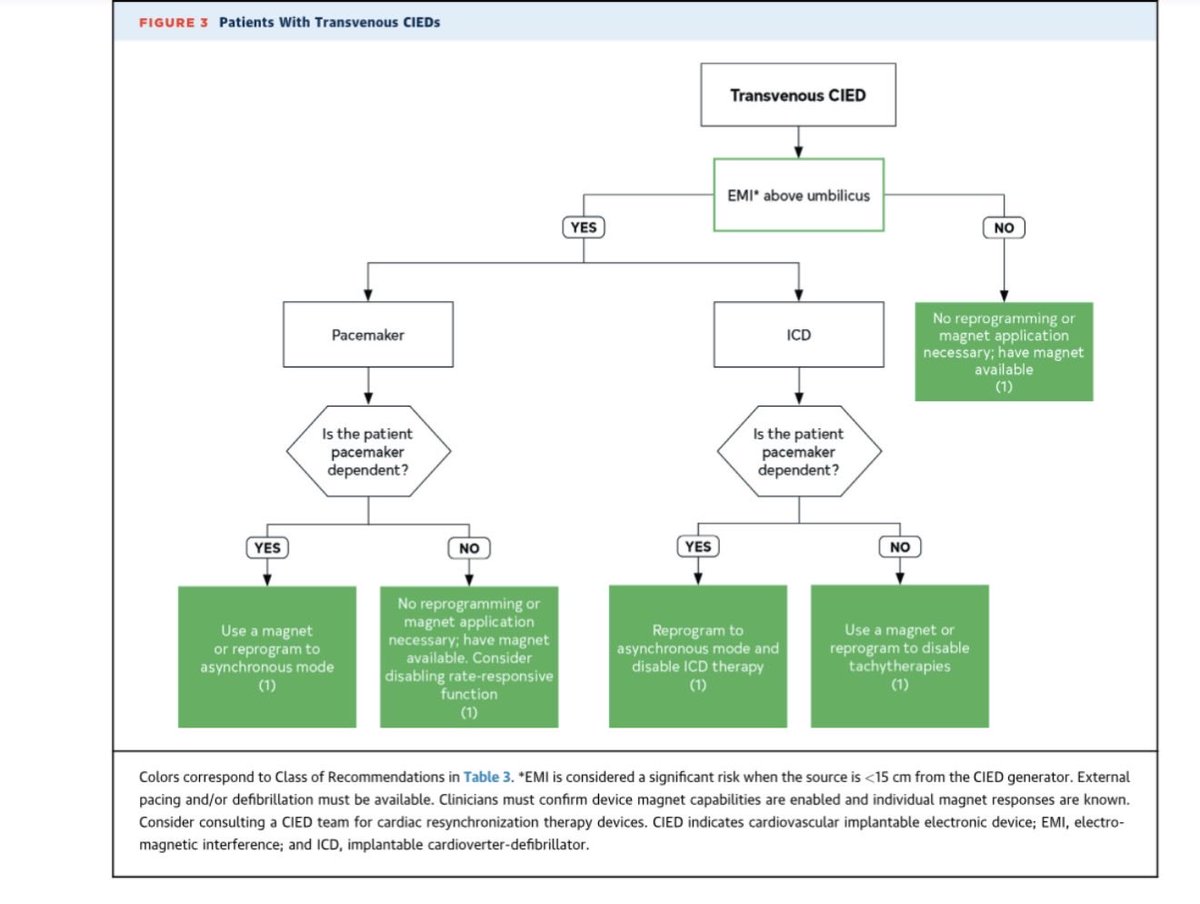
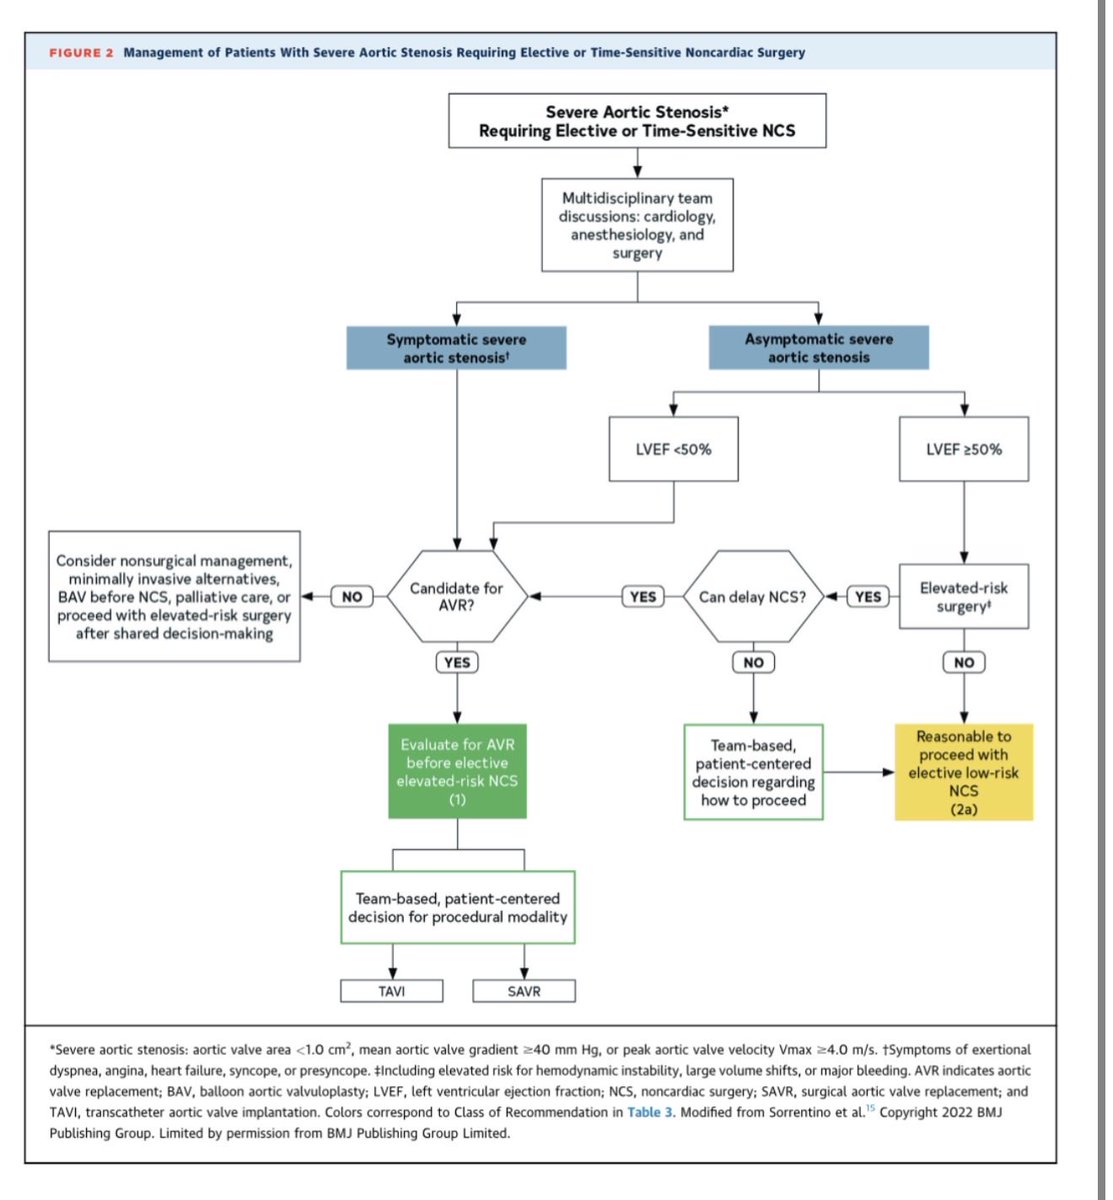
📘 2026 AHA/ACC Guideline for Perioperative Cardiovascular Management in Noncardiac Surgery
Thompson A, Fleischmann KE, Smilowitz NR, et al. | JACC 2026
Key recommendations:
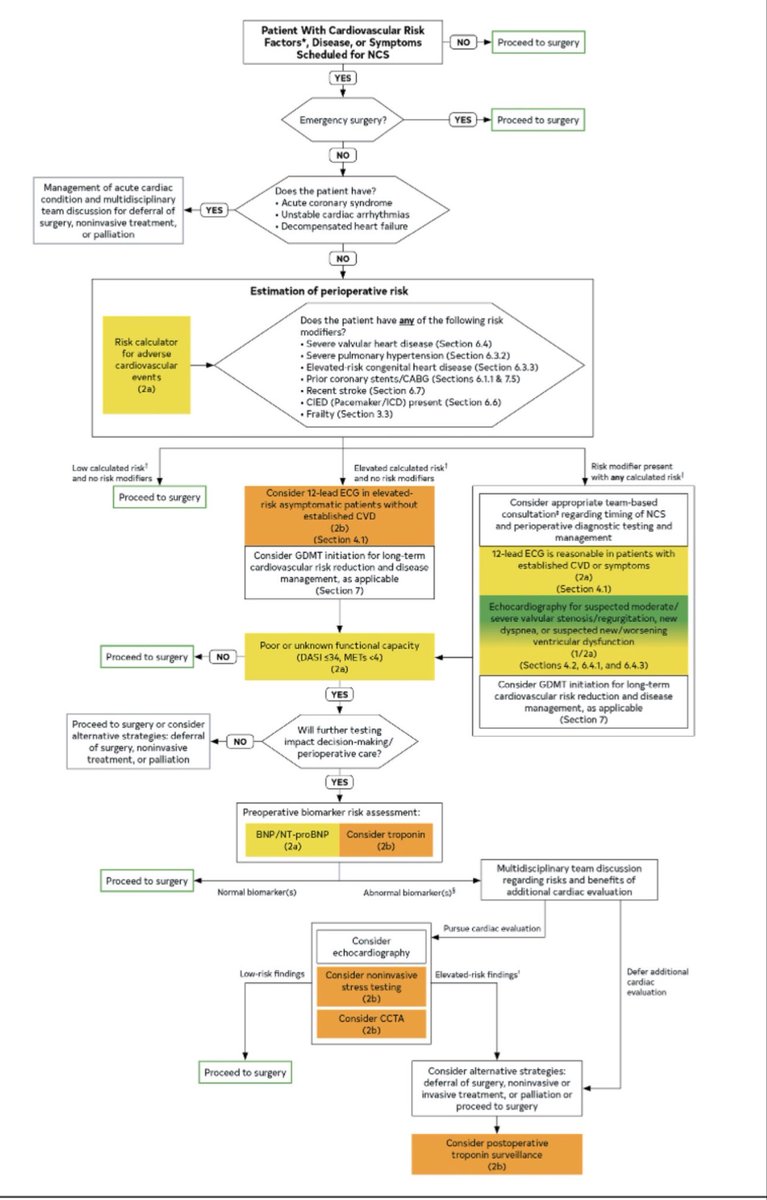
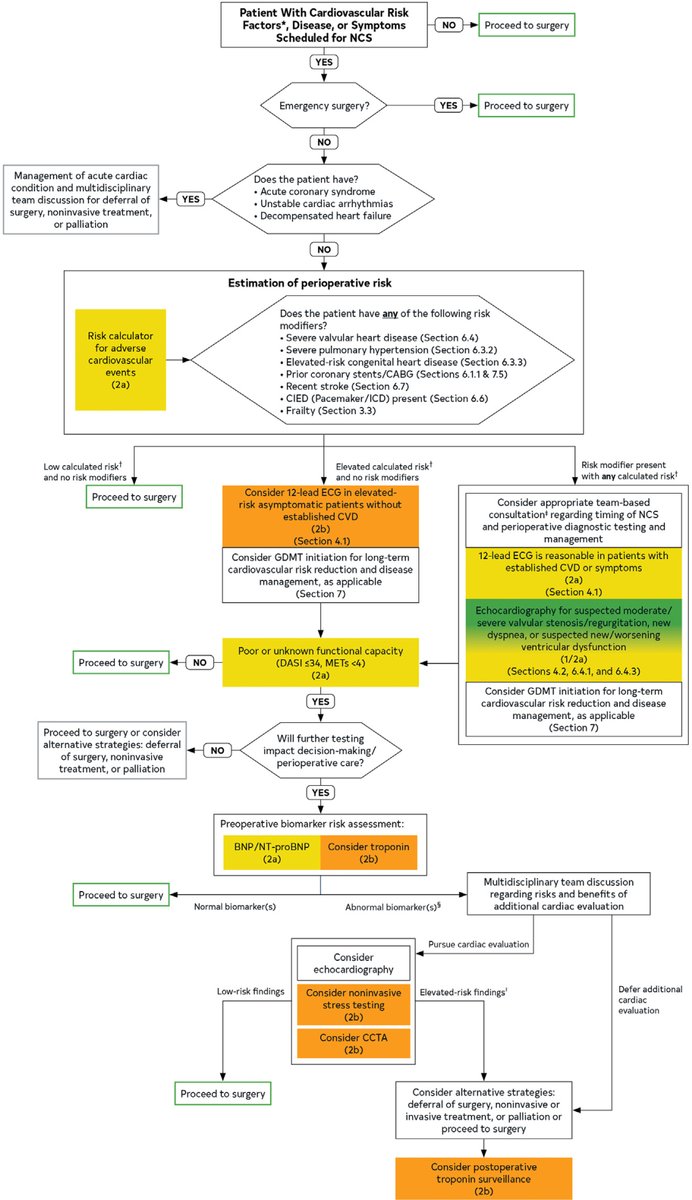
🔹 Use a stepwise approach to cardiovascular risk assessment, incorporating surgical risk, functional capacity, frailty, and cardiovascular risk modifiers.
🔹 BNP/NT-proBNP is reasonable before elevated-risk surgery in selected higher-risk patients; preoperative troponin may also help refine risk.
🔹 Avoid routine stress testing. Consider it only in selected patients with poor/unknown functional capacity and elevated perioperative risk when results would change management.
🔹 Coronary revascularization should not be performed solely to reduce perioperative risk. Revascularize when otherwise clinically indicated.
🔹 Continue chronic beta-blockers. If newly indicated, initiate them sufficiently before surgery—not on the day of surgery.
🔹 Continue statins and initiate them when otherwise indicated for long-term cardiovascular risk reduction.
🔹 Stop SGLT2 inhibitors 3–4 days before surgery to reduce perioperative ketoacidosis risk.
🔹 Routine anticoagulation bridging is generally avoided; reserve it for patients at particularly high thrombotic risk.
🔹 Consider postoperative troponin surveillance after elevated-risk surgery in selected high-risk patients to detect myocardial injury after noncardiac surgery (MINS).
🔹 Emphasis throughout: avoid unnecessary testing and use multidisciplinary, patient-centered decision-making.
📄 J Am Coll Cardiol. 2026;88:1543–1643.
DOI: 10.1016/j.jacc.2026.06.017
https://t.co/Wdu4ENZzbC
#Cardiology #PerioperativeMedicine #CriticalCare #Anesthesia #Surgery #AHA #ACC
The 2026 AHA/ACC Multisociety Guideline for #Perioperative CV Management for Noncardiac Surgery reaffirms the 2024 guideline. The title reflects the reaffirmation, while recommendations & supporting content remain unchanged. https://t.co/DsgvuOLEqp #JACC
Gastric vs Duodenal Ulcer - The Surgical High-Yields🩺
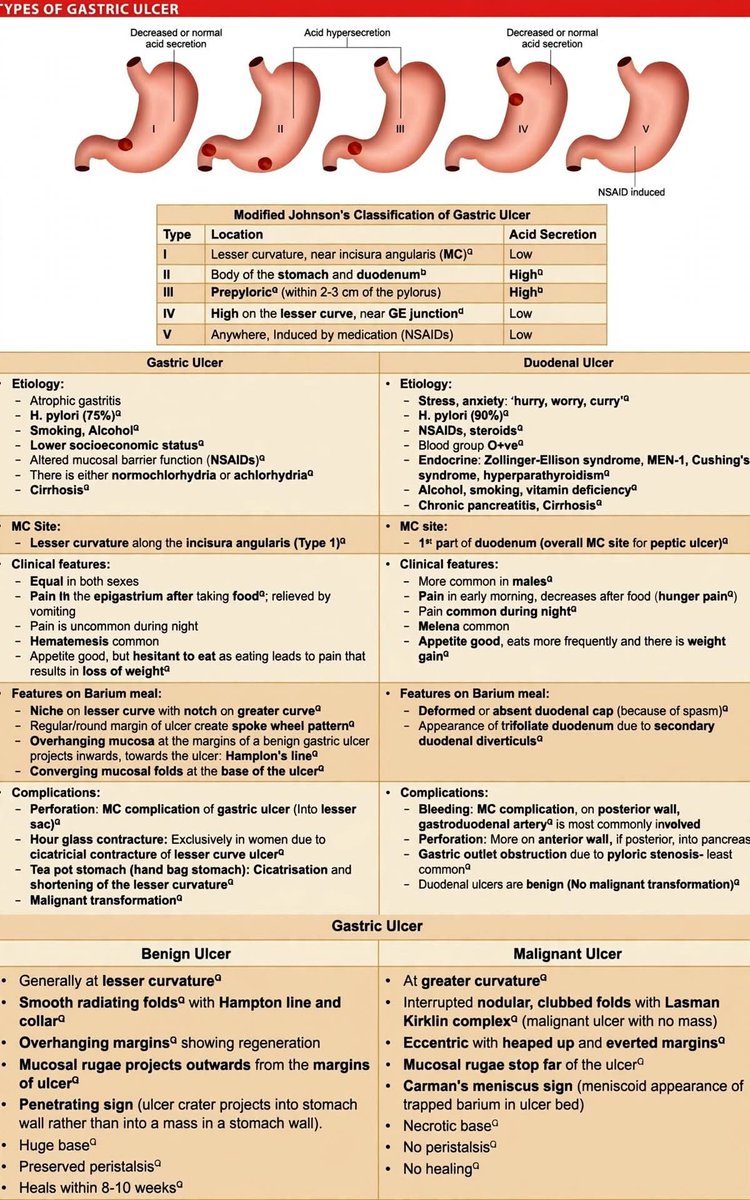
🔴 GASTRIC: Barrier failure. Pain AFTER food → fear to eat → WEIGHT LOSS 📉. Biopsy ALWAYS ⚠️- can be malignant.
🟢 DUODENAL: Acid hypersecretion. Hunger pain at night🌙, RELIEVED by food → weight GAIN 📈.Never malignant.
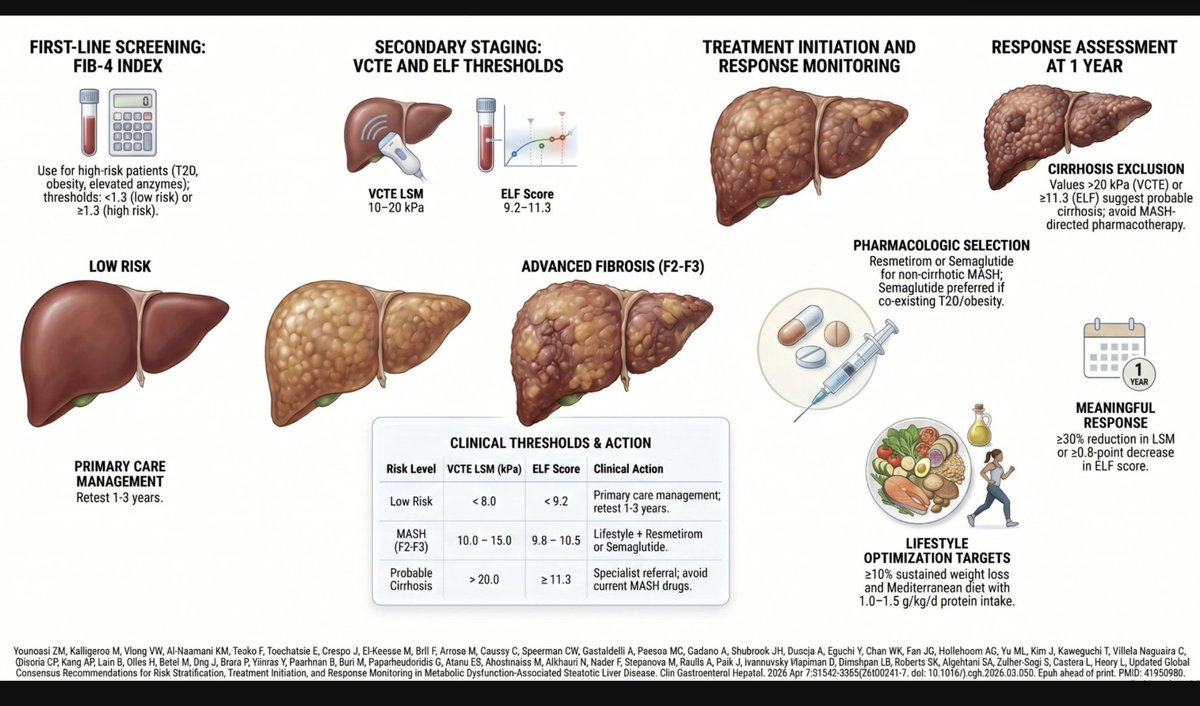
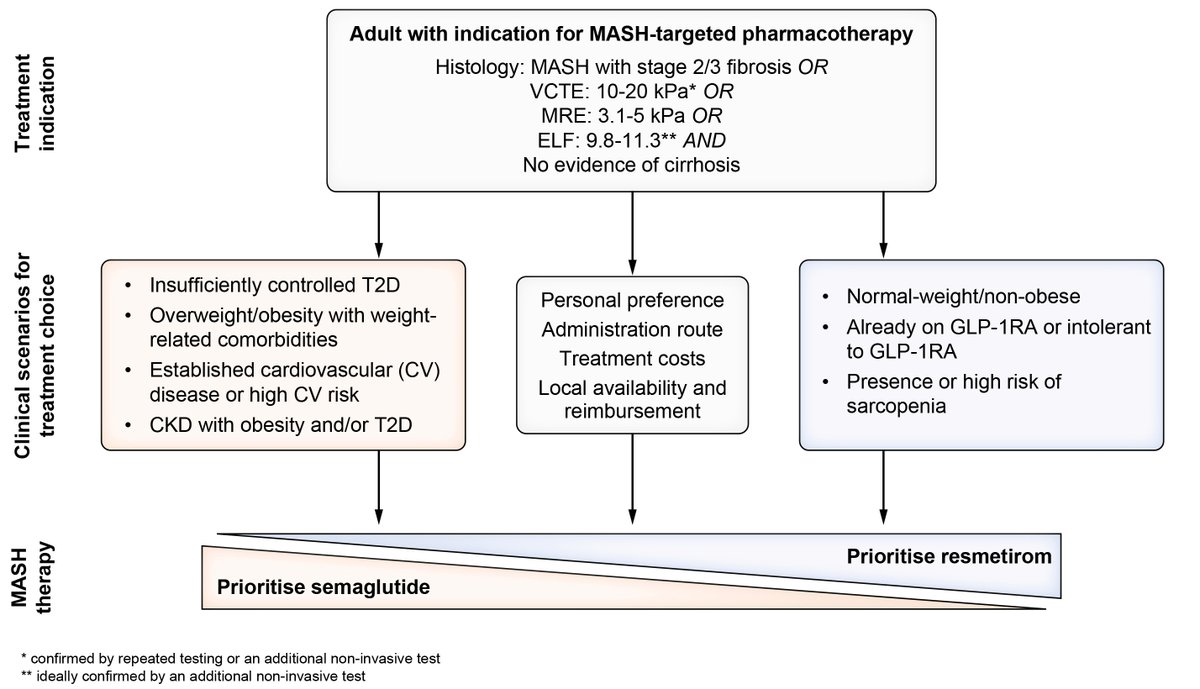
🆕 EASL-EASD-EASO guidance on resmetirom and semaglutide as #MASH-targeted therapy
💉#Semaglutide: preferred in patients with obesity, T2D or high cardiovascular risk
💊#Resmetirom: prioritised in those without obesity or unable to use GLP-1RAs
🔗https://t.co/od1gbcOKNA