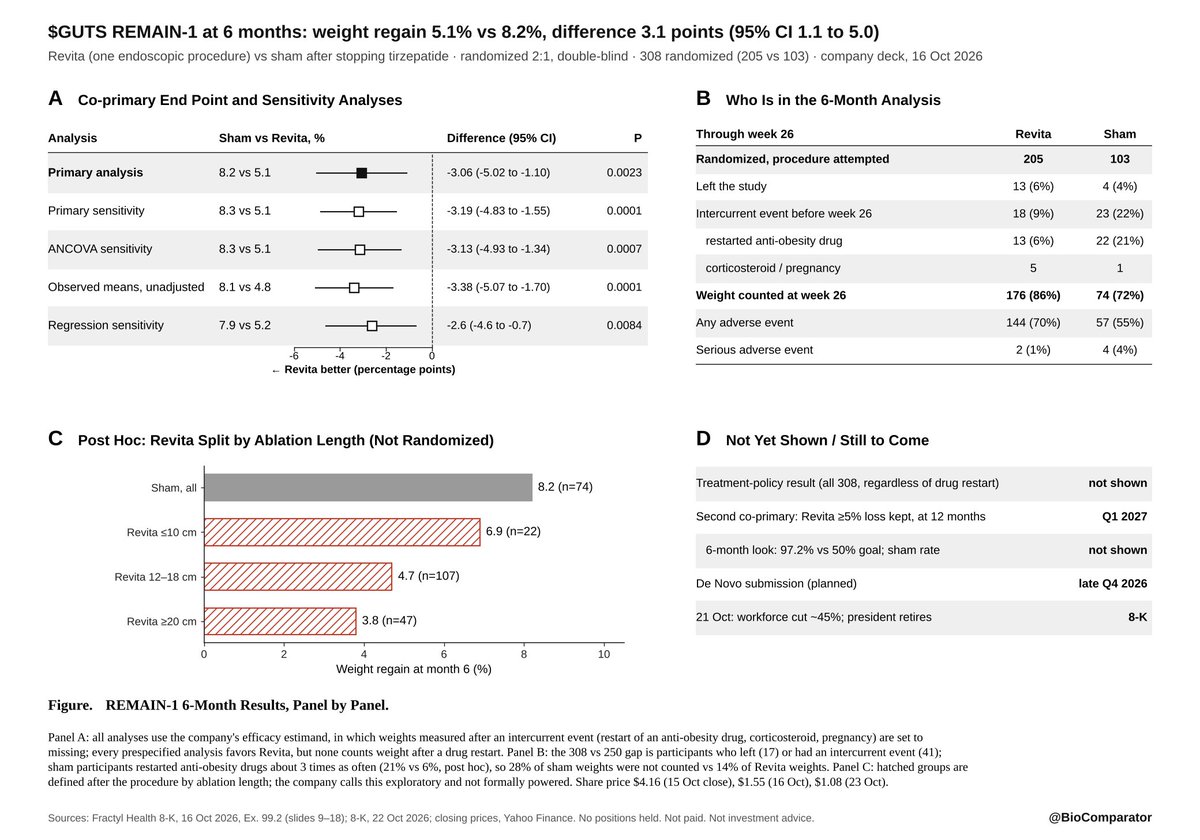
$GUTS REMAIN-1, from the company’s own deck: sham patients restarted weight-loss drugs 3x as often (21% vs 6%), and those weights were dropped from the analysis. The result counting everyone was not shown.
No positions held. Not paid. Not investment advice.
$GUTS met its primary endpoint and fell 60%. The randomised result: 5.1% vs 8.2% weight regain after stopping tirzepatide, a 3-point gap. The “53%” headline comes from 47 patients picked after the trial.
No positions held. Not paid. Not investment advice.
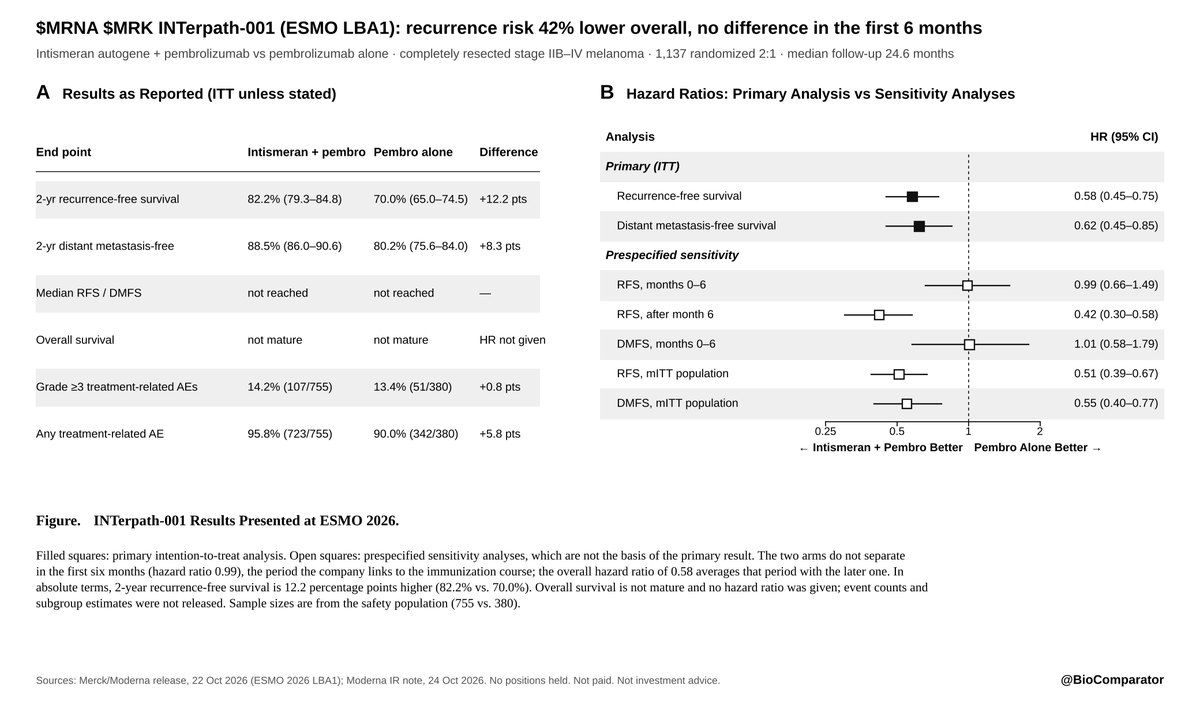
$MRNA $MRK : No difference between arms in the first 6 months (HR 0.99). The 0.42 after month 6 comes from a sensitivity analysis, not the primary result. Overall survival not mature. No positions held. Not paid. Not investment advice.
@b_chinnian5 Eligibility differs too: INTerpath-001 took resected, disease-free cutaneous melanoma only. IMcode001 took measurable metastatic or unresectable disease, including acral and mucosal subtypes
$BNTX’s personalised melanoma vaccine missed. $MRNA’s met its endpoints. Same idea, different patients: $MRNA treated after the tumour was removed, $BNTX with tumour still present. Full $MRNA data at ESMO on 24 Oct.
No positions held. Not paid. Not investment advice.
$MRNA options price about a ±20% move on the INTerpath-001 data at ESMO (24 Oct). The 30 Oct expiry carries 139% implied vol, 21 points above its neighbours. Most open interest sits in November and December, not the event week.
No positions held. Not paid. Not investment advice.
$GILD emvistegrast: X% vs Y% remission at week 12, about 57 patients per arm. Same chart: the other oral α4β7 (MORF-057, $LLY) beat placebo by 7.6 points, error bar crossing zero.
No positions held. Not paid. Not investment advice.
$GUTS met its primary endpoint and fell 60%. The randomised result: 5.1% vs 8.2% weight regain after stopping tirzepatide, a 3-point gap. The “53%” headline comes from 47 patients picked after the trial.
No positions held. Not paid. Not investment advice.
@DiscernedEd Neither is a pill. PAPZIMEOS is 4 injections over 12 weeks after surgical removal, with more surgery before doses 3 and 4 if papillomas are visible . INO-3107 is injected with INO’s device. INO’s China partner holds VGX-3100 for cervical HSIL, a different product and disease
$INO vs the already-approved $PGEN PAPZIMEOS, same endpoint (no surgery for 12 months): 28% vs 51% in year 1, 44% vs 43% in year 2. Accelerated approval needs an advantage over what’s already available. These numbers don’t show one.
In ulcerative colitis, 50.8% vs 42.6% looks like a win. The error bars overlap, and the placebo arms run from 10% to 25%.
No positions held. Not paid. Not investment advice.
$VKTX had positive obesity data this year, yet it is down 22% since late April. Market, biotech sector and obesity peers pointed to +13%. The gap built up quietly, day by day, with no SEC filing behind it.
No positions held. Not paid. Not investment advice.
Everyone’s talking about $VSTM’s “50% response” in pancreatic cancer. That’s 4 patients out of 8, and the true rate could be anywhere from 16% to 84%. Read the n before the %.
The sturdier signal is the dose: 41% (9/22) at 900 mg vs 15% (4/27) at 600 mg.
$KOD call: 80% that KSI-101 beats sham in PEAK, topline in December. An approved steroid injection gained 31 points over sham in a similar trial, and PEAK has about 100 patients per arm, enough to detect even half that.
$ZURA call: 60% that TibuSHIELD beats placebo in Q4. The IL-17A half is proven in HS (Cosentyx, Bimzelx). The open questions are an undisclosed dose and a trial of 82 patients per arm.
Scored on the primary endpoint at either dose. Void if no topline by year-end.
Adding: BAFF alone hasn’t been shown to work in HS. $NVS’s BAFF-receptor antibody ianalumab, phase 2: 52% vs 38% responders on placebo (16/31 vs 23/60), interval crossed zero. Registry NCT03827798.
$ZURA reads out its phase 2 in HS in Q4: 247 patients, BAFF + IL-17A antibody vs placebo. There’s no IL-17A-only arm, so even a win won’t show BAFF adds anything to $NVS Cosentyx or UCB’s Bimzelx.