5.1/ For beginners who cannot cut losses, close your positions and immediately reopen them. Your PNL on that position resets, and this exercise helps to clear biases from loss aversion. Still want to keep them on?
Radiology learning cross-sectional anatomy.
So I built a free tool for it: scroll real CT in three planes, or shoot a radiograph computed from tissue attenuation and list every structure the beam crossed.
https://t.co/h97FBz2Ii8
CC BY 4.0.
Interstitial lung disease is a challenging topic.
There are many available resources, but what most learners need is a clear framework and a structured way of thinking.
My book and ILD course focus on the essential high-resolution CT patterns you must know, helping you organize interstitial lung diseases into a logical mental model and apply a systematic, step-by-step approach in daily practice.
📘 The book is designed as a practical handbook
• Less than 240 pages
• Pattern-based and case-driven
• Easy to use during reporting and revision
🎥 The ILD course includes
• Around 14 hours of recorded lectures
• Practical high-resolution CT interpretation
• Real cases with structured reasoning
If you are looking for clarity rather than volume, this is exactly what these resources aim to provide.
We obsess over cancer screening, LDL, Zone 2 training — all for a few percentage points of risk reduction.
Meanwhile, 1,77,177 Indians died on the roads in 2024. A night highway trip is 5,000x more dangerous than a flight.
New piece 👇
https://t.co/ZjeYnxxMft
While everyone talks about radiologists being replaced with AI, I wonder though how many admin positions will be replaced by AI in hospitals - while a CEO might remain, CTO, CFO, HR, CIO, PR, marketing - all of these positions and people under them - will be much more affected than doctors, nurses, techs and patient caring staff.
You need people to take care of people. The backend jobs that have blown up beyond recognition are the ones that are in trouble. If your job is not patient-facing or patient-caring, you should be running scared. So if you as a CEO think that a radiologist could be made redundant, you too can become quickly redundant, perhaps faster, especially if you earn too much and don't bring value to patient care or bring value that is replaceable by AI.
In the stock market, you don't just pay for a company's current profits. This is the fallacy of obsessing about last quarter's earnings numbers. One does not benefit all that much from past numbers in this industry.
The needle-moving insights come from understanding that you will also have to pay a premium for future earnings and how fast those profits are expected to grow.
Figuring out just how much positive or negative expectations are embedded in the stock price is the rudimentary job of an investor.
Paying too much premium will ensure that you don't generate returns on the capital you invested, even if the company's operating performance does well years from now.
In simple language, you will not participate in successful operations since you've overpaid.
Commonly, this occurs due to FOMO (fear of missing out), overextrapolation (recency bias and performance chasing), social imitation (copying what the majority are doing) and other emotional & cognitive biases.
Investors who are capable of finding setups where there is a massive disconnect between the company’s operating performance (fundamentals) and stock prices (expectations) have a high likelihood of generating market-beating returns (formally referred to as excess return, or alpha).
79/M. Left otitis media with left facial palsy and hearing loss.
In suspected malignant otitis externa (skull base osteomyelitis), the earliest clue is often not bone. It is loss of normal fat.
Subtle asymmetry.
Blurring of intermuscular planes.
Fat disappearing where it should be crisp.
Around the stylomastoid foramen.Within the masticator space. Along the skull base.
Easy to overlook.
Easy to dismiss.
By the time bone is destroyed, you are already late.
Reporting pearl:
Loss of deep skull base fat planes should be considered skull base osteomyelitis until proven otherwise, even if the bone looks intact.
—Pearls, pitfalls and wisdom from today’s reporting list
من دواعي سروري كطبيب مصري أن أكون قد ساهمت بكتاب من تأليف فردي في المكتبة الطبية الدولية.
بعنوان «Challenging Cases in Interstitial Lung Diseases: A High-Resolution CT Approach» (CRC Press 2025)، يقدم الكتاب نهجاً عملياً منظماً لتشخيص أمراض الرئة الخلالية (التليف الرئوي) بدقة ومبكراً، آملاً أن يفيد الأطباء حول العالم و أن يساهم هذا العمل في تحسين رعاية هؤلاء المرضى وإدارة حالاتهم، مما ينعكس إيجاباً على حياتهم وتوقعاتهم المرضية.. أشكر كل من ساهم في إخراج هذا الكتاب إلى النور.
To all young, competent radiologists:
Don’t follow the herd. “This is how it’s always been done” by our respected seniors is a textbook case of failure — and we 40-year-olds are living proof of incompetence.
Forge your own path. You are the bright light at the end of the tunnel.
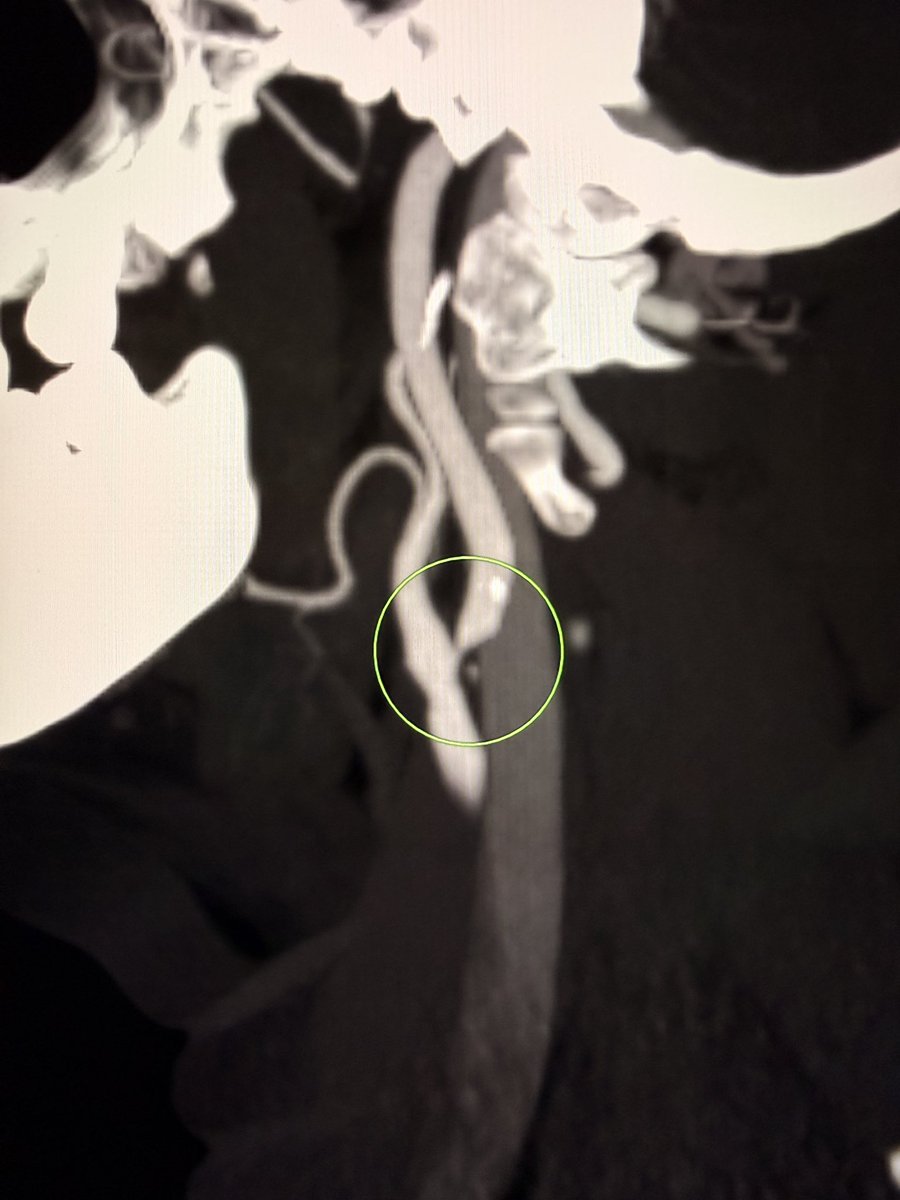
When deep (centrum semiovale) + cortical border zone infarcts coexist on the same side, the pattern strongly points to hemodynamic compromise, not embolic shower.
Check the ipsilateral vessels.
Look carefully at the carotid bifurcation and proximal ICA for high-grade stenosis.
In this case, the answer sat at the carotid bifurcation in the neck with high-grade stenosis. Intracranial vessels were clean.
Pitfall:
Labeling this as “embolic infarcts” and stopping there. You risk missing the real problem.
Wisdom:
Watershed pattern is a physiology clue. Follow it.
— Pearls, pitfalls and wisdom from Today’s reporting list
Case of tubercular lymphadenopathy.
Enlarged retroperitoneal lymph nodes involving peri portal, Porto caval, aorto caval, para aortic space, splenic hilum and b/L Iliaac region.
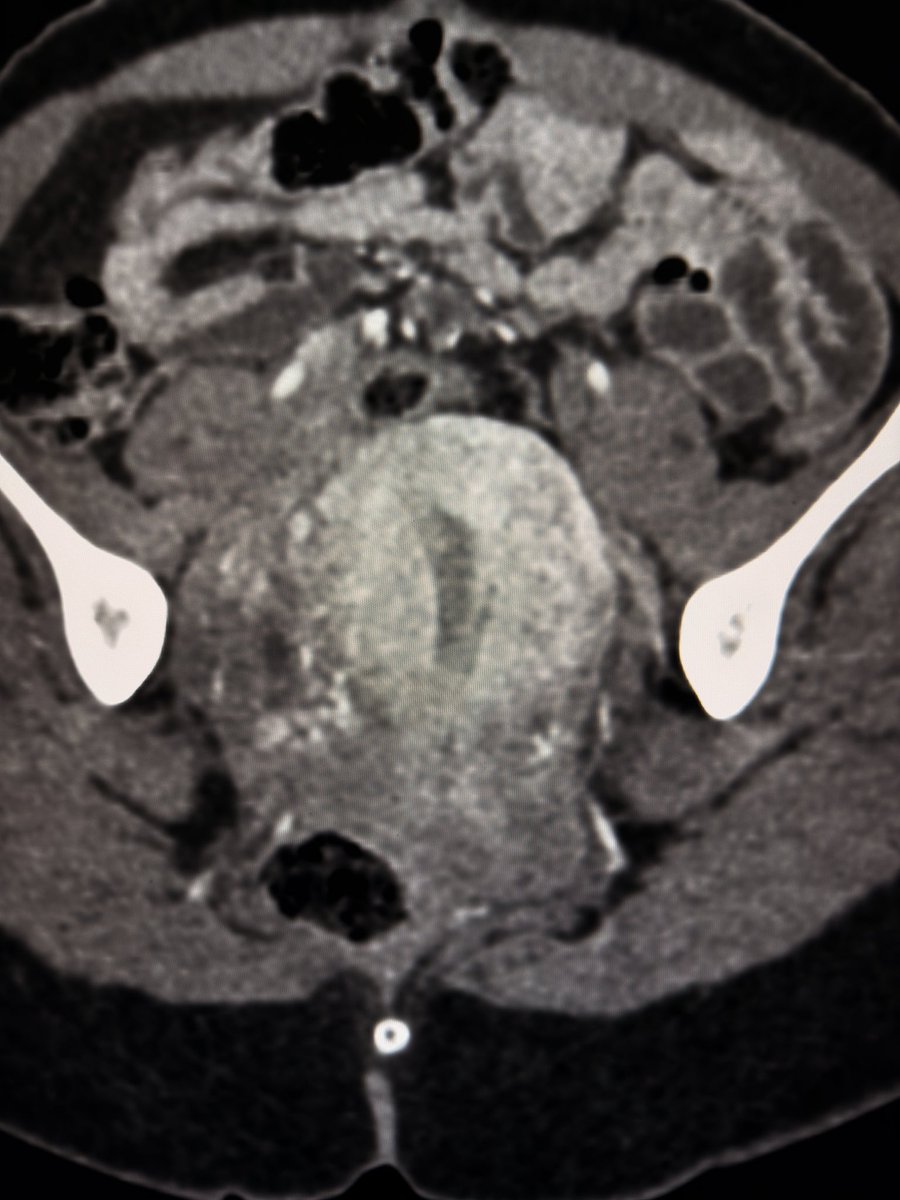
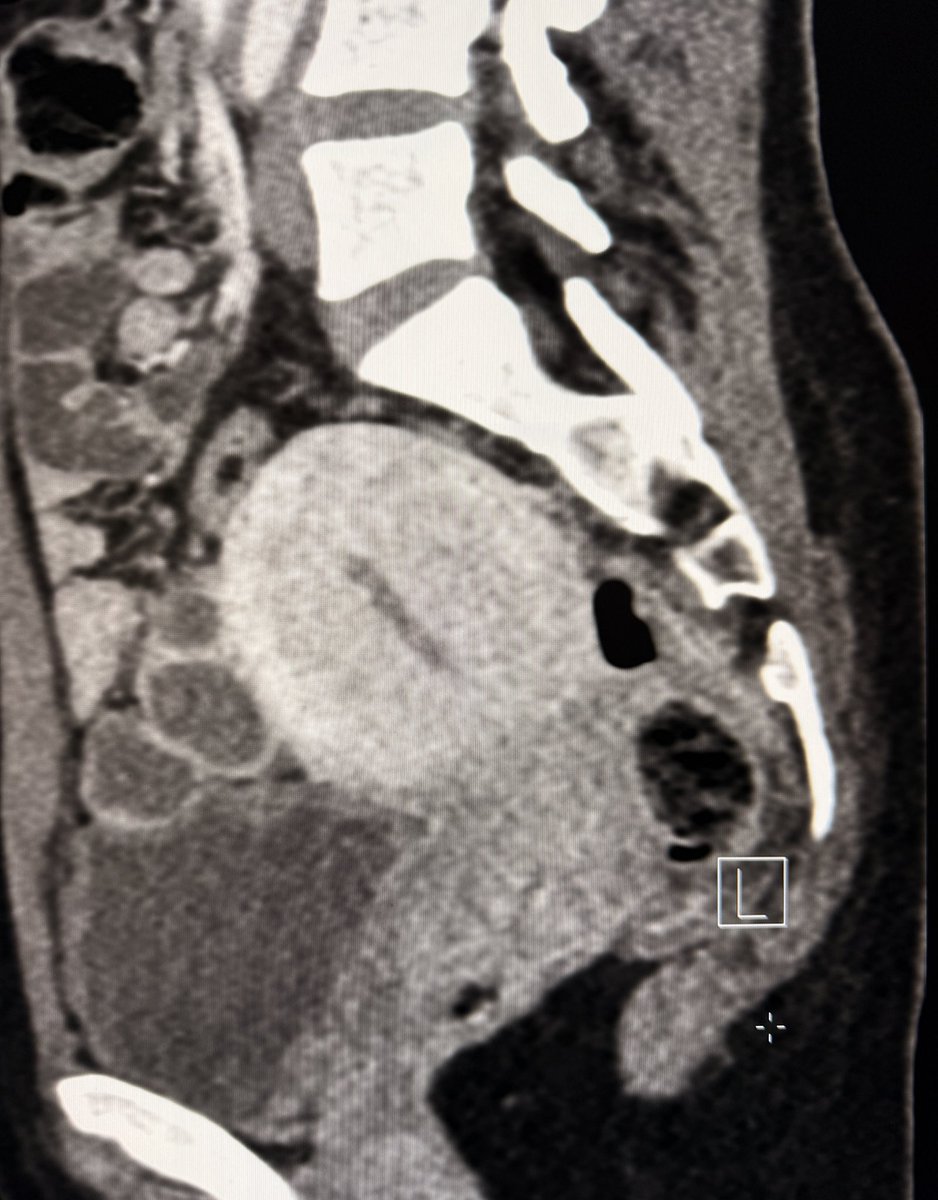
16yo F.
On portal venous phase CT, the uterus enhances more than the cervix. This differential enhancement is common and physiological. Yet it is often mistaken for cervical pathology.
The relatively lower attenuation of the cervix is often overcalled a cervicitis or a cervical mass.
Understanding normal enhancement patterns helps avoid these errors and keeps us from creating pathology where none exists.
—Pearls, Pitfalls, and Wisdom from my reporting list
Five Cases from February 2026
12th MarchREFTHURSday - 7 PM
Case 1: 25 years old with a prevascular space mediastinal mass
Case 2: 47-years old with a visceral space mediastinal mass
Case 3: 54-years old with a solitary lung nodule
Case 4: 65-years old man with a fibrotic ILD
Case 5: 63-years old woman with a fibrotic ILD
The cases will be discussed using Osirix with no Powerpoint. Each case will be discussed for 10-12 minutes from the description to the differentials and to the final diagnosis in an interactive manner.
Zoom Webinar
Webinar ID: 822 9652 6670
Passcode: REFTHURS
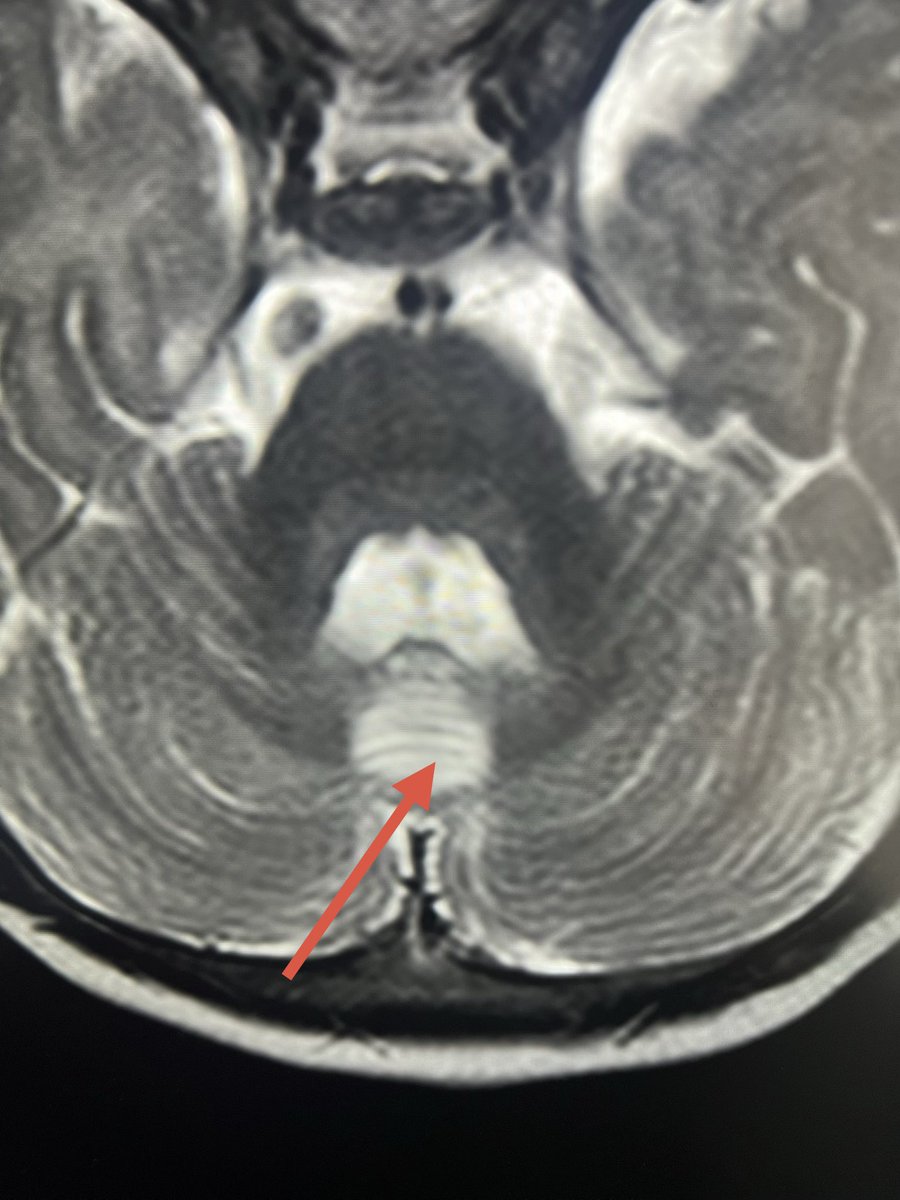
The weekend tip 💡: The lesser known sign of perinatal hypoxic ischemic injury- cerebellar vermian injury. Typically focal and rounded patch of gliosis picked remotely.
This weekend, stay attentive to detail.
Get ready, Dr. Usha Nagaraj is about to teach you everything you need to know about sellar, suprasellar, pineal, and intraventricular pediatric tumors. #ASPNR26