@VivekBuchMD@KarlDeisseroth@brainstimj Great work!
Many targets are nice innovations from basic science, notably sgACC and VMPo
A brazilian group noted a frequent marked lesional effect with posterior insula leads (Dongyang 2026). Did the pain come back at 100% after 5 weeks, or there was a residual lesional effect?
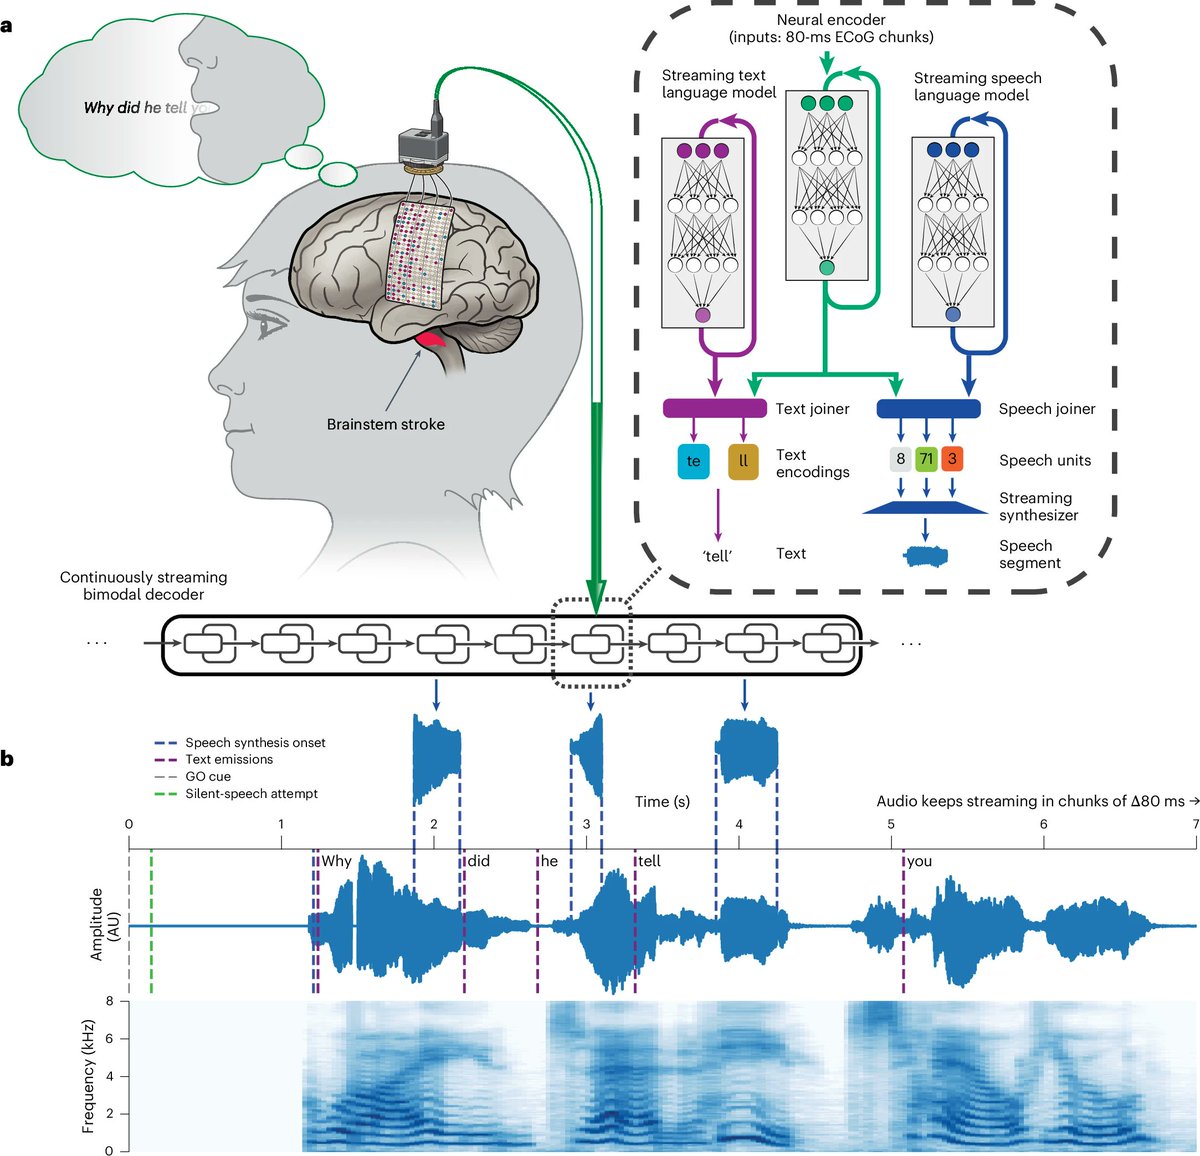
In this recent speech neuroprosthesis paper, published last month in @NatureNeuro, Littlejohn et al. used 253-channel ECoG array recordings of the speech sensorimotor cortex to translate thoughts into speech in a patient with brainstem stroke causing severe paresis and anarthria.
Takeaways:
- the main breakthrough is the continuous decoding of brain activity in 80ms increments, which lowered the latency between attempted speech and the speech output. In their previous work (Metzger 2023 Nature), waited until silent-speech attempts were completed before generating speech. In this work, the mean latency between the "go" signal and speech output was 1-2 seconds.
- speed was up to 90 words per minute with a 50-phrases vocabulary, and 48/min with 1,024-word vocabulary), which is excellent. In comparison, conversational speech rate is about 150 words per minute
- Accuracy is still a work in progress, with a word error rate of 12% with a 50-phrases vocabulary, and 59% with a 1,024 words vocabulary.
My take
- this is yet another demonstration of the performance of high-density Ecog BCI. At the brink of clinical implementation, this favors new players like @PrecisionNeuro_, who might achieve similar BCI performance without damaging the cortex with intracortical implantation, and without an expensive implantation robot.
- Ann, the participant of this study, suffered from a right pontine stroke at 30 years old (left vertebral artery dissection with basilar occlusion), leaving her with severe quadriparesis and anarthria. She is cognitively intact, but almost completely "locked-in", communicating with a gaze-tracking device. It is important for non-clinicians in this field to understand that the number of patients like Ann is extremely low. Patients clinically flagged as "locked-in" due to stroke are much older on average, and almost invariably choose comfort care. Some patients with severe TBI / DAI have a "locked-in" profile, but most often lack the attention/executive function to participate in much simpler technology-assisted communication programs. Patients with advanced ALS get quadriparesis and anarthria, but most often with concomitant cognitive deficits, and a limited life expectancy. Experienced ALS neurologists do not see great promise from BCI for these patients, except for the very rare, Hawkins-type very slow-progressing forms of ALS. In other words, although scientifically fascinating, this kind a speech BCI can only really benefit a handful of patients across America.
- the real holy grail of speech BCI (from a clinical standpoint) will be to help patients with aphasia from cortical stroke. This will very difficult in patients with large stroke involving Broca, but perhaps achievable in patients with subcortical damage and preserved primary language areas.
https://t.co/QCLaT6glrH
Important results from two phase 1-2 studies of dopaminergic cell transplantation for Parkinson’s Disease jointly published this week in @Nature:
- Tabar et al. implanted dopaminergic neuron progenitor cell product (bemdaneprocel) derived from human embryonic stem cells in the putamen of 12 patients with PD
https://t.co/H91VqYzhEX
- Sawamoto et al. implanted allogenic induced pluripotent stem-cell dopaminergic progenitor in the putamen of 7 patients with PD
https://t.co/HUk3C8qoYx
Encouraging results include the apparent survival of the grafts up to 24 months (increase in putamen 18F-DOPA intake especially in the high-dose group) even after immunosuppression was stopped, the absence of severe graft-induced dyskinesias as observed in previous trials (although slight increase in dyskinesias in many patients), the absence of tumoral transformation (slight increase in graft size on MRI but no sign of cell proliferation on PET), and the potential clinical improvement, especially in the high-dose groups.
Although the trials were not designed to measure clinical efficacy (insufficient statistical power, open-label design subject to placebo effect), the magnitude of clinical improvement is somewhat disappointing, variable among patients, mostly within placebo range, and not well correlated to the 18F-DOPA intake measured with PET.
Perhaps results could be improved by increasing the dose of implanted cells, or combining the therapy with DBS? The implantation of dopaminergic neurons during DBS surgery could provide excellent blinding to the treatment status (especially if asleep DBS) in the setting of a randomized double-blind study. It is unclear why patients recruited in these trials were not candidates for DBS in the first place, given their similar inclusion criteria (>5 years of disease, motor fluctuations, >30% levodopa response at UPDRS, 50-70 y-o)
I think it would be important, in the upcoming larger trial, to compare CL DBS to optimized pharmacological treatment.
If similar cognitive improvement can be achieved with medication, this would prevent patients from undergoing an invasive procedure with implanted material
(1/)Encouraging results from Schiff, @JaimieHenderson et al. in @NatureMedicine, on thalamic DBS (CL-DTTm) to improve cognition after TBI
However, there are important limitations that were not highlighted in the article discussion, Twitter/X comments or media coverage (See below)
Intriguingly, this is not mentioned in the manuscript inclusion criteria, nor is psychostimulant intake in the patients' demographics or supplementary. I am surprised reviewers did not ask for this information, or why it was not spontaneously showed
1. Phasic supra-threshold SCS stimulation @_NeuroRestore
2. Phasic supraspinal stimulation (motor cortex) with subthreshold SCS, coupled with rehab. Over time, spontaneous cortical activity may become enough to activate spinal motoneurons without cortical stim @_MartinezLab
Important clarifications on mechanisms of subthreshold tonic SCS for movement restoration in stroke and SCI.
In patients with more severe spinal lesions (hence reduced supraspinal input), parameters required to elicit movements are often supra-threshold. 2 solutions to that:
How do people with motor paralysis regain movement using spinal cord stimulation (SCS)? @genisprat and I studied the mechanisms that enable voluntary motor control during SCS after paralysis
https://t.co/QtYzJd3qeL
#scs
‼️Spoiler‼️: SCS does NOT facilitate supraspinal inputs…
Fun team-building experience at Montreal Esprit Triathlon! Full neurosurgery resident team for the relay - Olympic distance; 2h12 total, 7th/87 :D
Other programs up to the challenge? ;)
@vinsanitye @MarkMaclean10@FaithCRobertson @cathveille @eags36
Great study showing the scientific potential of LFP recordings with the Percept DBS device. STN LFP encodes muscle activation, walking states, locomotor vigor, and freezing of gait. Could this be used for closed-loop spinal cord stimulation? https://t.co/6FWtjPMjvi
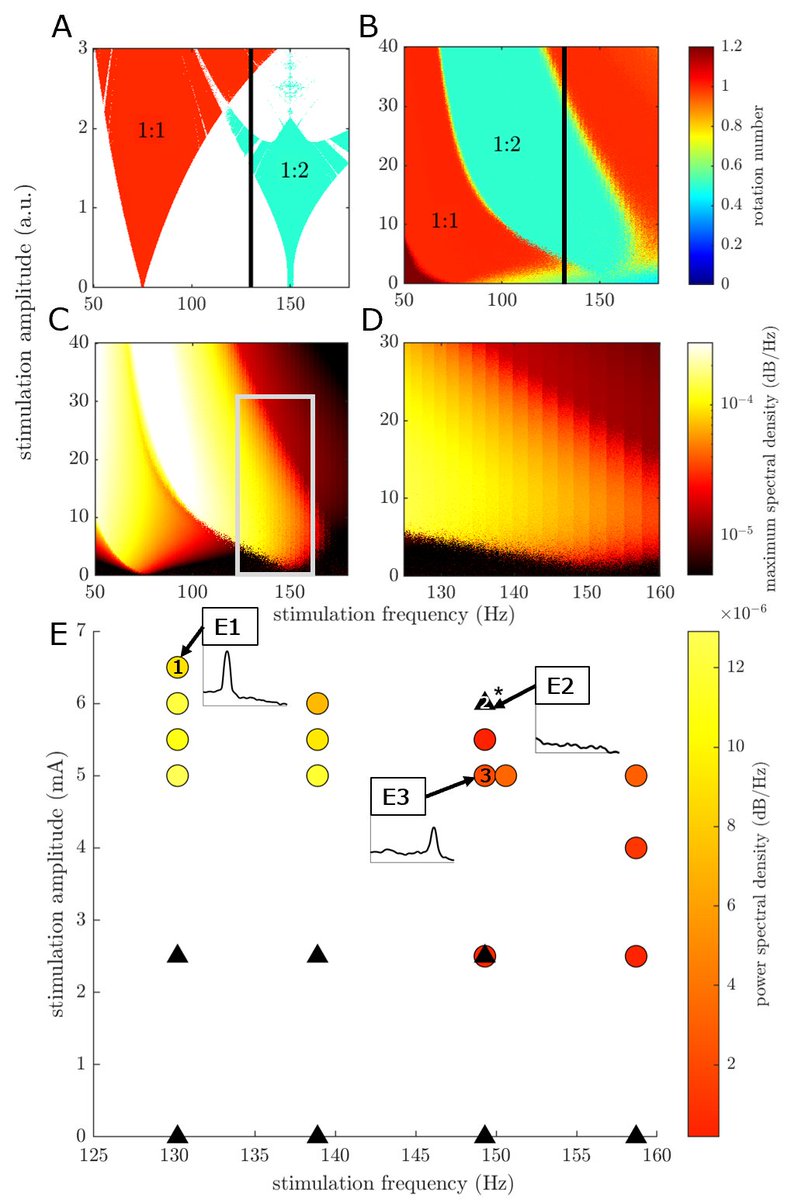
Can models fitted to patient data predict 1:2 entrainment of cortical finely-tuned gamma oscillations to deep brain stimulation in Parkinson’s disease? Check out our new preprint https://t.co/F1ajKJuHf7
5h24 on the half-Ironman at Montreal Esprit triathlon!
24 minutes slower than my PB, yet one of the races I'm most proud of, as the tough schedule of neurosurgery residency makes it harder to have a stable training routine. It's always possible to find time to exercise!