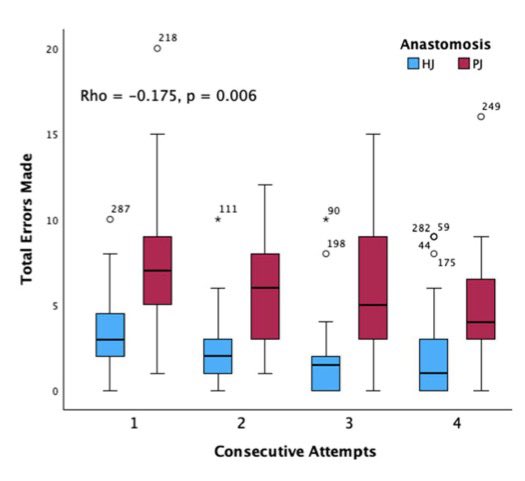
Pan-European 🇪🇺 Training Program for Robotic Pancreatoduodenectomy 🤖(LEARNBOT) out now in @AnnalsofSurgery
🏆 486 PD performed, operative time 475 min, blood loss 200 ml
🎓 Our @HPDsurgery successfully trained in 2023 by @MarcBesselink and team
https://t.co/05ajLeMAgB
@hpbsurgeon1@IHPBA This is an excellent point…. To expand what are the standards that we should be achieving, what numbers are needed to reach those, both centre and surgeon, what is the volume of cases to support a RPD practice assuming not all cases suitable?
Recurrence after resection of node negative p-net 🦓 How to predict?!
🇺🇸 770 pts 🍒 all node - recurrence 10%
🔮 Recurrence predicted by male sex, size > 3cm, lymphovascular invasion, grading
🤌 The debate about lymphadenectomy in p-net continues!
https://t.co/T5jQN3Qdp9
In IPMN-derived pancreatic ductal adenocarcinoma, a minimum of 10 lymph nodes should be harvested, and the optimal number to maximize survival is 20 lymph nodes. https://t.co/9oNn2BBmtT
@TheNotoriousHPB Completely agree, teleporting in a delayed PPH is horrendous, unlikely to see bleeding or establish any control.
IR first and quickly.
@SyedAAhmad5@MarcBesselink@DrJashDatta@NEJM I agree it’s too high. When exploring national datasets, eg this US,UK model hospital, Dutch national. Mortality is often 5-10% mark. Differences between high and low volumes exist in all data sets. Should there be minimum volumes? Centre/surgeon.