The most expensive part of a hospital bill may never touch the hospital at all.
A patient admitted for care has no way of knowing whether the price on a medical consumable reflects its actual cost or a markup fixed long before it ever reached the ward. That gap in information is, at its core, a public health issue.
A survey of hospital consumables in Maharashtra found an IV infusion set with a trade price of ₹11.05 carrying a printed MRP of ₹325 ; a markup of 2,841%. A syringe procured at ₹6.75 carried an MRP of ₹57.20. A catheter procured at ₹29.41 carried an MRP of ₹310.
These are not elective purchases. Patients cannot compare prices, seek alternatives, or question a number printed on a box while receiving care and the MRP itself is often fixed upstream by manufacturers and distributors, disconnected from the trade price by a wide, unexplained margin. The result is a system where the party bearing the cost has the least information to evaluate it.
The regulatory gap is structural: scheduled medicines are capped under the Drugs (Prices Control) Order, 2013. Most medical devices and consumables are not leaving both the pricing and the information around it almost entirely unmonitored.
A review of these findings and clear guidelines on the permissible gap between trade procurement price and declared MRP have been recommended to the Department of Pharmaceuticals and the NPPA ; a step toward closing not just a pricing gap, but the information gap patients are left to bear alone.
#PublicHealth #GoodGovernance #Leadership #TukaramMundhe
https://t.co/Ye9CVzr8qU
JUST IN: The report we always look for every year: CANCER STATISTICS, 2026
New milestone with 5y Survival of 70%!!! Still a lot of room to improve but also excellent progress !
@AmericanCancer@CACancerJournal@DanaFarber
https://t.co/ZtFDhFOGgU
Got to see THE @OncBrothers in action last night alongside these med onc all stars.
Great discussions & vibes - basically the oncology conference equivalent of WWHL w Andy Cohen (for any BRAVO fans out there). #GI26
Meet Samajwadi Party’s Iqra Choudhary.
She has been the Member of Parliament from the Kairana Lok Sabha constituency since 4 June 2024.
Her MPLADS work details are properly updated, which is rare and deserves appreciation.
A Thread🧵
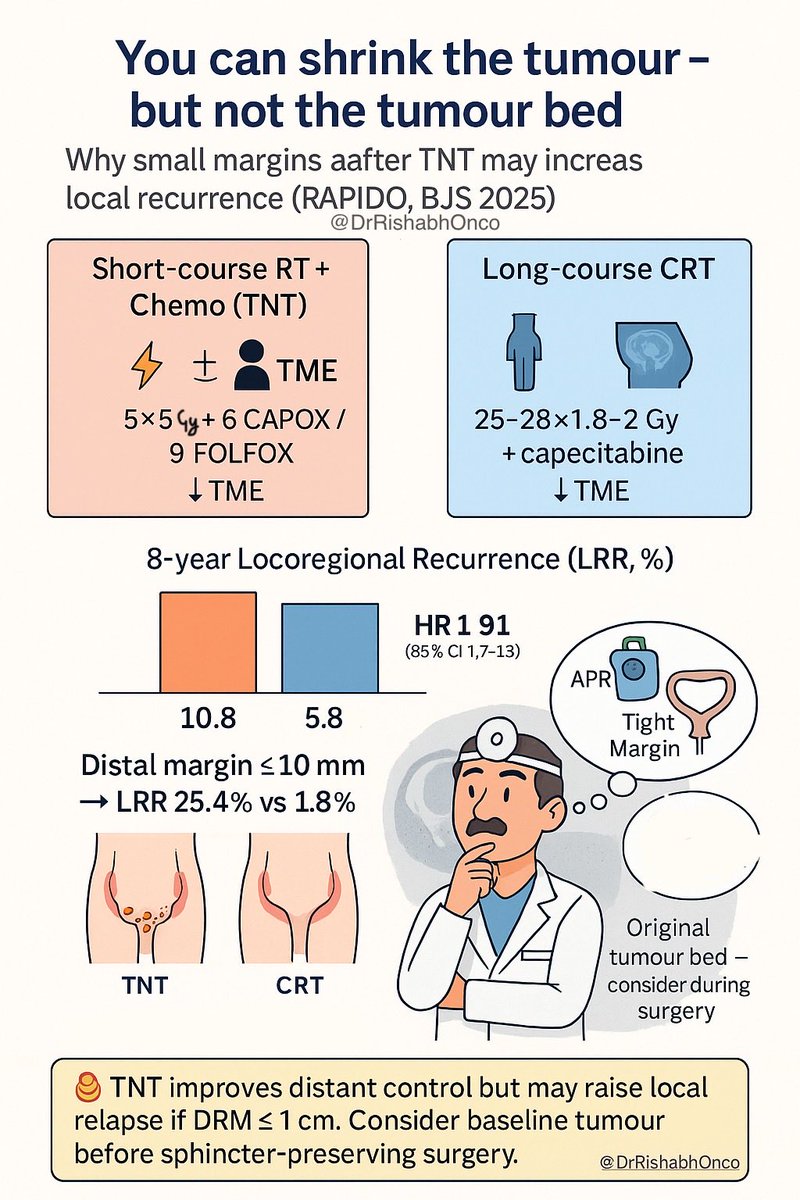
🧠 You can shrink the tumour—but not the tumour bed.
New RAPIDO analysis in BJS 2025 shows why small margins after TNT can turn dangerous 👇
💡 Trial: RAPIDO (n = 920, LARC)
🎯 TNT = 5×5 Gy + 6 CAPOX / 9 FOLFOX → TME
vs CRT = 25–28×1.8–2 Gy + capecitabine → TME
📊 8-year results:
• LRR 10.8% (TNT) vs 5.8% (CRT) → HR 1.91
• Spike seen only after sphincter-preserving surgery (SPS)
→ 12.1% (TNT) vs 4.8% (CRT) (HR 2.6)
• 🚨 If distal margin ≤ 10 mm → 25.4% (TNT) vs 1.8% (CRT) 💥 (HR 15.5)
🔍 Why?
TNT causes tumour shrinkage but leaves scattered viable cells in the original tumour bed.
✂️ Cutting “too close” (<1 cm) may slice through microscopic disease → higher local recurrence.
🇸🇪🇳🇱 Geography tells the story:
Sweden = more APR → no difference
Netherlands = more SPS & tight margins → higher TNT LRR
🩻 Takeaway:
TNT reduces distant mets ✅ but may raise local relapse if DRM ≤ 1 cm ⚠️
➡️ Surgeons must factor in baseline tumour bed, not just post-TNT shrinkage.
📖 Prata I et al. Br J Surg 2025
🔗 https://t.co/MqeM0xqH8i
#OncoTwitter #ColorectalCancer #RectalCancer #RadOnc #Surgery
@OncoAlert@esmo_open@BJSurgery@myESMO
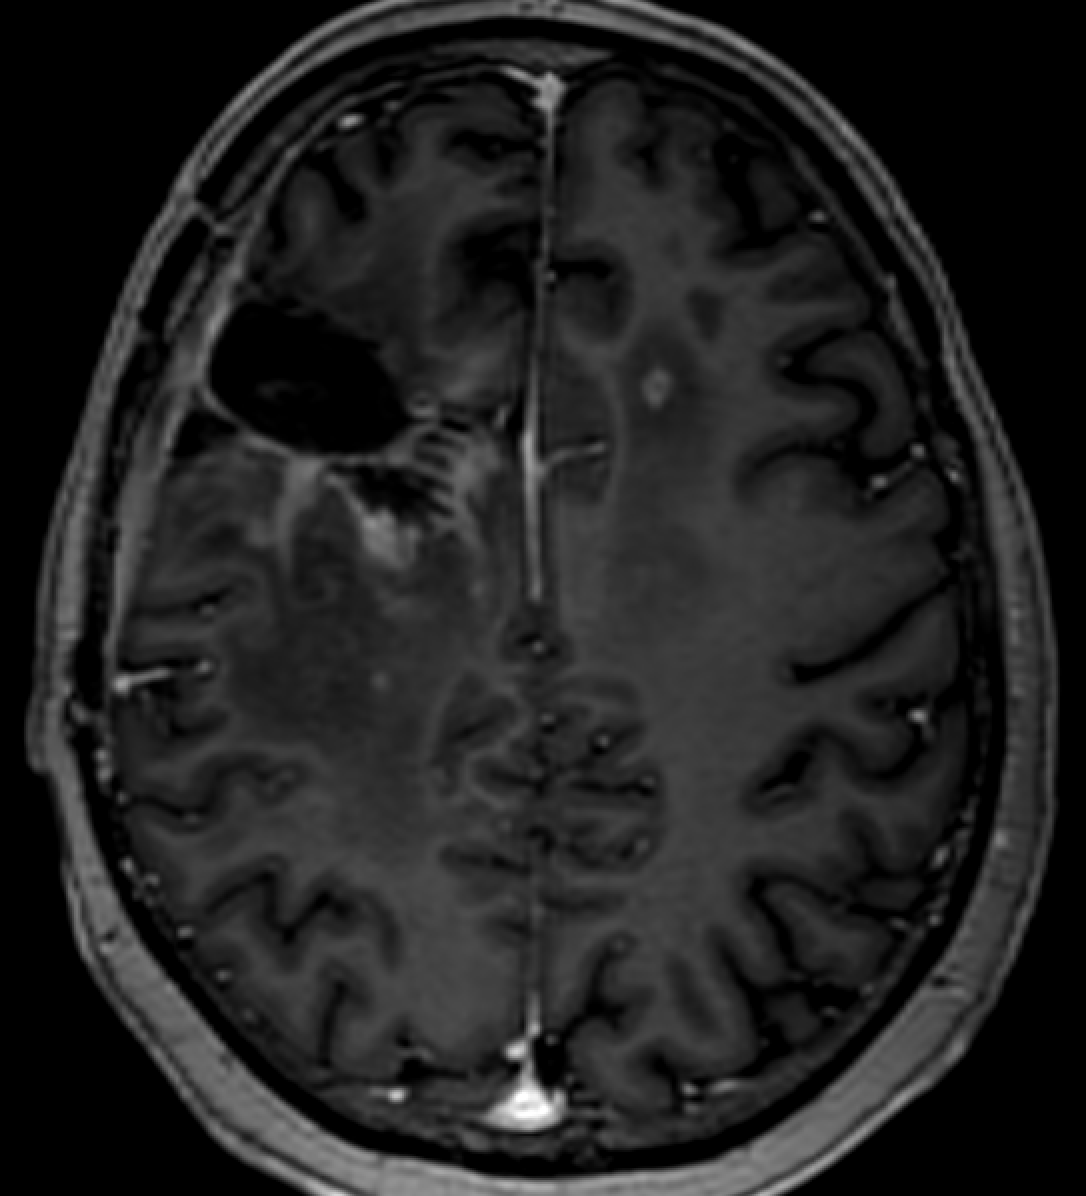
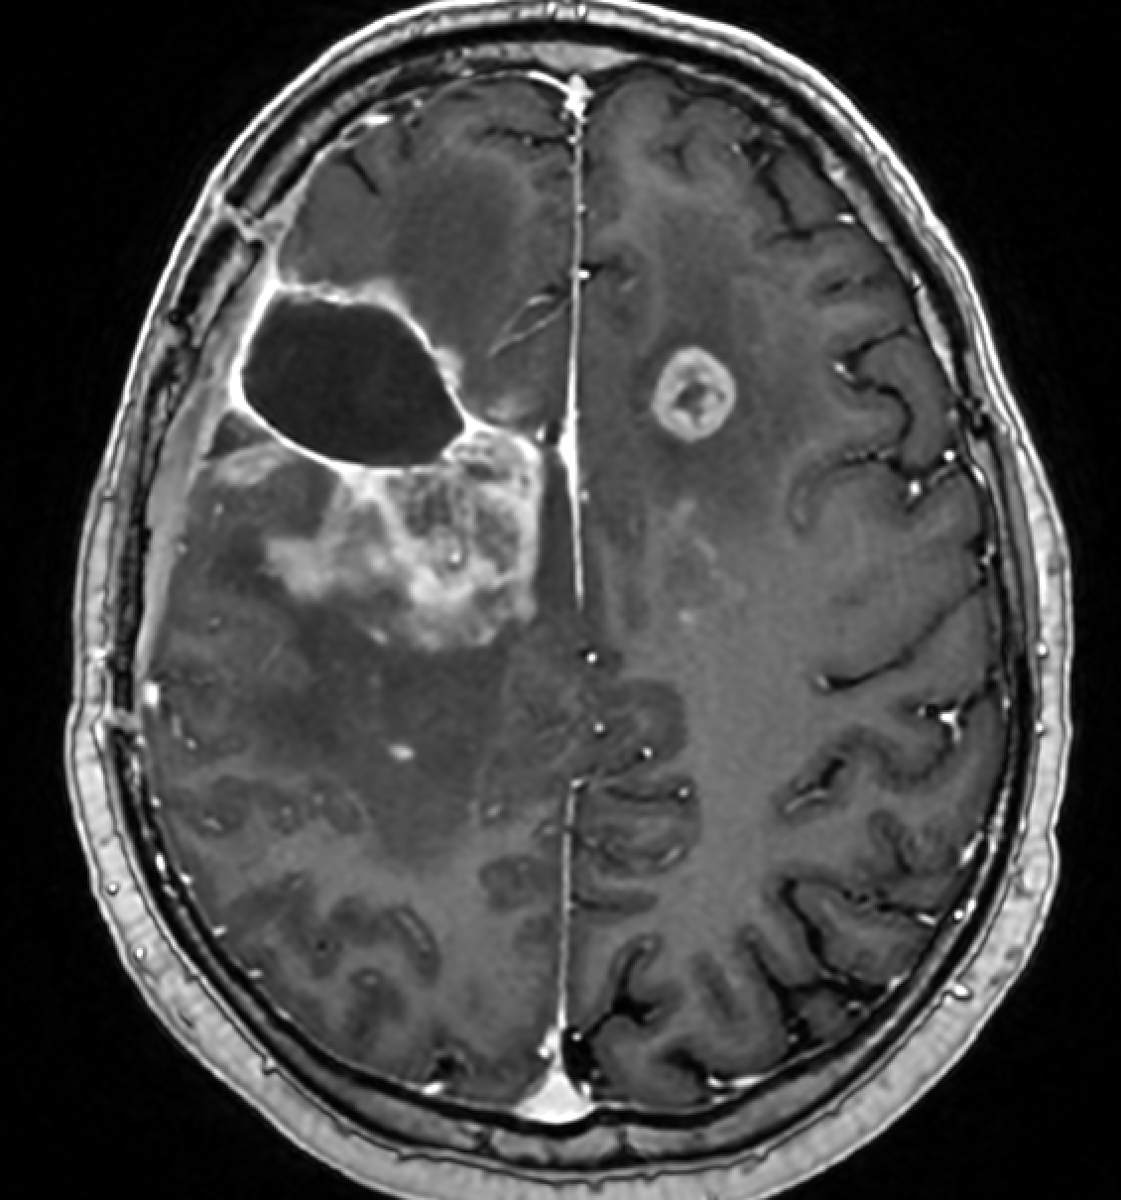
🩻This is a post‑debulking glioblastoma, IDH‑wildtype. After two doses of Avastin (bevacizumab), there appears to be dramatic regression of tumour on the post‑contrast images, but the ADC map tells a different story: it shows an expanding front of restricted diffusion, suggestive of hypercellular tumour. How do we explain this?
💡This is likely to be pseudoresponse. Avastin stabilises the blood–brain barrier, inducing a rapid reduction in contrast enhancement and vasogenic oedema. Although Avastin can improve progression‑free survival, it has not been shown to improve overall survival in glioblastoma.
💡Avastin‑related coagulative necrosis can also manifest as regions of low ADC, so while the expanding rim of restricted diffusion is concerning for tumour progression, follow‑up is needed to confirm whether it enlarges (supporting progression) or remains stable (more compatible with coagulative necrosis).
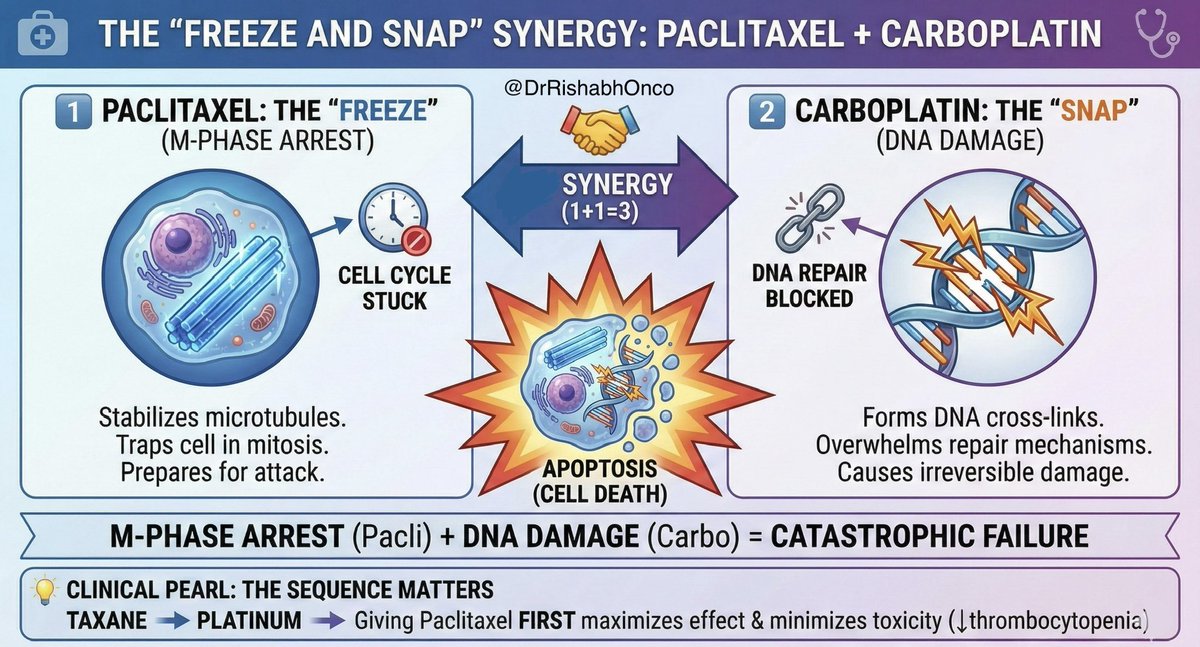
The Paclitaxel + Carboplatin "CarboTaxol" doublet is the bread and butter of oncology for a reason. 🍞🧈
But why does this specific combo work so well?
It’s all about the "Freeze and Snap" synergy. ❄️💥
1️⃣ The Freezer (Paclitaxel):
Paclitaxel stabilizes microtubules, preventing depolymerization.
It freezes the cell’s skeleton in the M-phase (Mitosis). The cell tries to divide but gets stuck. 🛑
2️⃣ The Snap (Carboplatin):
While the cell is arrested and stressed, Carboplatin slides in.
It acts as an alkylating agent, forming reactive platinum complexes that bind to DNA (cross-linking). 🧬🔗
🤝 The Synergy (Why 1+1 = 3):
The magic lies in the timing.
Paclitaxel arrests cells in the G2/M phase.
Cells in this phase are less efficient at repairing the DNA damage caused by Carboplatin.
The "Freeze" prevents the "Repair," leading to accumulation of DNA damage ➡️ Apoptosis (Cell Death). ☠️
💡 Clinical Pearl (The Sequence Matters):
This is why we often administer Taxane before Platinum.
Giving Paclitaxel first avoids the antagonistic effect where Carboplatin might inhibit the uptake or cytotoxicity of the taxane.
It also reduces thrombocytopenia! 📉🩸
#Oncology #MedTwitter #OncTwitter
@OncoAlert@myesmo@esmo_open@asco
SOFT study: 141 elderly (70+), chemo-ineligible pts w locally advanced rectal cancer.
Short-course RT → delayed surgery achieved 94% R0 resection & 5% local recurrence.
A v reasonable, low-burden strategy for older pts w competing risks. @OncoAlert
https://t.co/ZD1MYC6j5E
How is TARE the “only consistently reproducible option” when RTOG 1112 showed an overall survival benefit in a phase III trial, including a majority with MVI?
Where is the phase III RCT showing an OS benefit for TARE?
#HCC#OncTwitter 🧩
@nbn426@NiuSanford@KrishanJethwa
In the last decade, over 50+ telemedicine startups in India raised more than $2 billion and most have shut down. The pitch was- India has too few doctors, too many patients, and a broken healthcare system. Technology would fix it. But it didn’t.
Here’s a breakdown.
🥳New OncoScan (and my first!) in @IJROBP from the GU editorial board
"Precision Over Tradition: Transforming Prostate Cancer Treatment with SBRT"
2024 was the year of Prostate SBRT, or so it seems! 😇
FREE LINK👇🏽https://t.co/elEoWVH1cZ
@NicholasZaorsky@CDraulans
मिनी पाकिस्तान !!
क्या आपके आसपास कोई मुस्लिम बस्ती है? वही, जिसे आपके शहर का "म���नी पाकिस्तान" कहते हैं।
●●
शहर का पिछड़ा, तिरस्कृत इलाका, जिनके हालात Ghetto से बेहतर नही होते।
पहले Ghettoization समझिये।
मुम्बई की चाल आपने सुनी है। सामुदायिक अपार्टमेंट, जिसमे निम्न मध्यवर्गीय परिवार, जैसे तैसे जीते हैं।
लेकिन चाल में बहुरंगी कल्चर होता है। घेट्टो में एक जाति, समुदाय के लोग होते हैं।
●●
घेट्टो शब्द चला, नाजियों के राज में।
सत्ता पाते ही यहूदी दुकानें, व्यवसाय, नौकरी चौपट करने के बाद, नाजियों में उनसे आम कालोनियों में रहने का अ���िकार छीना।
विशेष रूप से बनाई चालों में भेज दिया गया, जिसके चारों ओर गार्ड्स होते। ये सेटलमेंट्स, घेट्टो कहलाये।
बेहद घटिया सिविक कन्डीशन में ये एक तरह की जेलें थी। यहां से लोगो को ट्रेनों में भरकर कंसन्ट्रेशन कैम्पो में पहुंचा दिया जाता।
●●
कंसेंट्रेशन का मतलब होता है- इकट्ठा करना।कैम्प पहुंचते ही स्त्री बच्चे बूढ़े तत्काल नहाने भेज दिए जाते। बाथरूम के शावर से “ज्य्क्लोन-बी” नामक गैस निकलती, सब मर जाते।
कार्यक्षम युवा कुछ माह,भूखे कमजोर होने के बाद गैस चेम्बर जाते।
●●
भारतीय मुस्लिम, खुद के बनाये घेट्टो में जा चुके हैं। वही,जिसे आप मिनी पा���िस्तान कहते हैं। इनका निर्माण अलग अलग कालक्रम में अलग ढंग से हुआ।
पुराने शहरों में सुलतानों-नवाबों के महल, किलों के गिर्द मुस्लिम बस्तियां मिलेंगी।
इसे मुस्लिम सत्ता के दौर की सिविल लाइन या ऑफिसर्स कालोनी समझिये। कभी राजसी इलाके थे, अब घेट्टो हैं।
●●
आजाद भारत मे विभाजन के घाव, दंगो की शक्ल में रिसते रहे। फिर भी मानवीय रिश्तों में बंधे हिन्दू इलाकों के मुसलमान,
और मुसलमान इलाको के हिन्दू एक दूसरे को स्वीकार करते। हजारों किस्से हैं, जब किसी हिन्दू ने मुसलमान, या मुस्लिम ने हिन्दू को बचाया।
पर नफरत की दुकान के सेल्समैन, मेहनत करते रहे। सेल में 1992 के बाद बम्पर वृद्धि हुई।
तो मुसलमान अच्छी कालोनियों से निकलकर वहाँ चले गए, जो मुस्लिम बहुल कहलाते। रिवर्स में उन इलाकों के हिन्दू भी निकलकर अन्यत्र चले गए।
नये घेट्टो बने। नफरत और भय का शिकार मुसलमान इस आत्म-घेट्टोकरण में सुरक्षा तलाश रहा था। वैसे ही, जैसे मौत की छाया में ज्यूस घेट्टो में दुबक कर रहते थे।
●●
घेट्टो के अंदर क्या होता है, इस पर सूचनाये कम..धारणाए ज्यादा हैं।
गोद मे बैठे मीडिया की खबर है, कि पाकिस्तान समर्थक नारे लगे।आतंकवादी पैदा हो रहे हैं।मस्जिद में हिन्दू विरोधी तकरीर हो रही,मदरसा जिहाद सिखा रहा है।
भ्रम और रहस्य का कुहासा, इसके गिर्द बुन दिया गया है।
●●
घेट्टो के भीतर का युवा भी भ्रमित हैं। किले के भीतर एकता का जोश है, कौम पे मर मिटने की ख्वाईश है।
लेकिन किले के बाहर अल्पसंख्यक होने की कमतरी भी है। ये नार्मल नही है।
तिस पर मौजूदा राजनीति ने इन्हें भयाक्रांत करने में कोई कसर नही छोड़ी। अब तो जनमानस के बड़े हिस्से ने, खुलकर यह धारा अपना ली है।
●●
विसर्जन, शोभायात्रा इस नंगी धमक का अवसर बन गए हैं। साल में 4-5 बार, देश भर में हिन्दू यह नग्नोत्सव झूमकर सेलिब्रेट करने लगा है।
घबराहट का मजा लेने लगा है।
पर यह घबराहट विस्फोटक है।
समाज के दो हिस्से जब एक दूसरे से दूर होत��� हैं, तो अविश्वास और कबीलाई आक्रामकता स्वतः जन्म लेती हैं।
याने घेट्टो की सीमाओं के दोनो ओर, युद्धोन्माद का पूरा समान मौजूद है। युद्धोन्माद लाशों के ढेर की ओर बढ़ता है। लाशें ही नफरत की सियासत को खाद पानी देती है।
और लाश चाहे जिस धर्म की हो, उसके तमाशबीनों की ताली से सत्ता, एक ही दल की निकलती हैं।
●●
ध्यान से देखिये। अब हम उसी नाजीज्म का सस्ता वर्जन है। नकली देशभक्ति है, झूठ का बोलबाला है।न���रत की सियासत, प्रोपगंडा चैनल हैं, निशाने पर लाया गया एक समाज है।
उसके आत्मनिर्मित घेट्टो भी हैं।
मगर आगे की राह में थोड़ा फर्क है।
नाजियों को शर्म थी, छुपाकर गैस चेम्बर्स में ले जाते थे। यहाँ शर्म की जरूरत नही। बस्तियों को ही एक्सटर्मिनेशन कैम्प में तब्दील करने का जतन है।
●●
फर्क यह भी, कि आम जर्मन इसके खिलाफ खड़े नही हुए थे।
हम खड़े हो गये हैं।
याद करके कि हम भारतीय हैं, और "हम भारत के लोग" किसी तानाशाह की आवाज पर, होलोकॉस्ट के समर्थन में खड़े होने वाली ब्रीड नही हैं।
●●
जर्मन नही हैं हम। हिंदू हैं।
सगर्व हिन्दू हैं..
वसुधैव कुटुम्बकम वाले।
पनाह छीनना, मार देना..
हिन्दू की तासीर नही।
इससे पहले कि दंगाई किसी घेट्टो को चुनें, आप अपनी पसंद का घेट्टो चुन लीजिये। बार्डर क्रास कीजिये, उनका हाथ पकड��� आश्वस्त कीजिए। एक मुस्कान बिखेरिये।
और तब, गर्व से मैं भी कहूँगा
आप हिन्दू हैं..
❤️
The greatest thinker of the 21st century:
Naval Ravikant.
He was an early investor in Uber, Twitter, and Notion.
And he famously said, “You’re not going to get rich renting out your time.”
Here are 10 of his teachings on wealth that changed my life:
Montelukast is widely prescribed in India, and sales appear to be rising. This is despite several reported adverse effects, including nightmares, depression, death by suicide. Sanjitha Muneeswaran and I make a case for stricter regulations @the_hindu 1/n
I was tasked with teaching @MDAndersonNews residents & med students about #rectalcancer.
The field has changed a lot since I started in 2012. You could say… there have been many “eras” of hot topics in the field of RT for rectal cancer!
(I had too much fun with this…)