>Nur Weiße können Rassisten sein, weil sie die Institutionen kontrollieren
Dann erklär mal, warum Schwarze in Afrika, Araber im Nahen Osten oder Chinesen in China ständig ethnische Hierarchien, Pogrome und Diskriminierung durchsetzen, ohne einen einzigen Weißen in Sicht.
Eure Definition ist reine Willkür: Rassismus = was Weiße tun. Alles andere ist „Widerstand“ oder zählt nicht. Das ist selbst rassistisch und marxistischer Klassenkampf-Bullshit auf Rasse umgemünzt.
I’m furious and heartbroken to see my country like this.
I could be prosecuted for this, but so be it. It needs to be said.
Our empathy is killing us. I stand with MY people, and they’re not my people.
Share this. We’ve had enough, and time is running out for France.
@Llywey@headsparks_ Explain to me how an immigrant becoming a welfare leech instead of building up his civilization or at least providing value in his guest country is "low-time preference"
@RockefellaK Noch ist auf der Seite gar nichts geleaked. Da sind nur KI Zusammenfassungen von Mails lel. Der Torrent Dump ist das interessanteste und der ist bis jetzt noch nicht geliefert. Ich denke das ist ein Bluff oder PsyOp.
Im Kern sprichst du aber trotzdem was wahres an
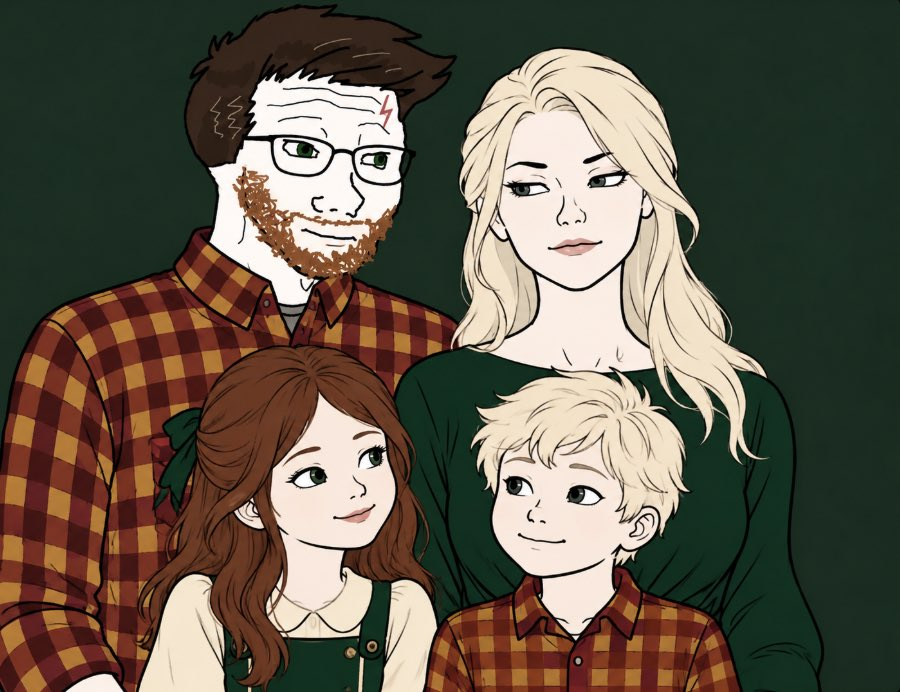
I've been rereading the Harry Potter books with my partner before bed and yeah, I have to give it to the chuds--Malfoid fixes two of the biggest problems with the book.
It's been discussed to death, but the characterization of House Slytherin really is the weakest part of the entire series.
Rowling clearly doesn't intend for the house to be pure evil, but all the named students are unpleasant or cruel, the most sympathetic adult Slytherins are portrayed as at best flawed anti-heroes, and by the seventh book literally every Slytherin student leaves before the battle of Hogwarts (either to join with Voldemort or stand aside).
At the same time, the Harry & Ginny pairing was never satisfying. Ginny's character growth is largely offscreen (offpage) and their romance is continually sidelined in favor of adventure. You get the sense that Rowling wasn't willing to take any more risks with Ginny after the Chamber of Secrets, so she feels flat even when compared to side characters like Neville or Luna.
By the end of the series Harry has had a bunch of different love interests and they've all been dismissed for one reason or another, so there's no time to add a new character or bring back an old one. It feels like Ginny just wins by process of elimination.
Making Malfoy the titular character's love interest is perfect.
Malfoy and Harry make good foils for one another because they are actually very similar characters. Both are prodigal sons grappling with family legacy and uncertain destiny. The books show a clear path to reconciliation, but never take it.
Their pairing would demonstrate how students needn't be defined by their house and creates a symbolic break between the previous generation of Slytherins and the next.
None of your (arguments) are implied by any steps, the first step alone is mainly a call for the FDA to stop mandatory licensing. Private insurance will still recommend only licensed doctors by other private licensing firms so that they don't have to pay you again for the damage caused by an doctor they recommended to you. I shouldn't have to explain this because you didn't watched it and the summary is insufficient.
Anyways I need to sleep and be productive tomorrow so I'm not gonna respond anymore, I already lost oversight because you screenshot all your text instead of just buying premium for $2. Stop being broke
Here you have a list of reasons why America is not a free market healthcare system which is not what I'm advocating for. My point was that still even with these shitty regulations the market is still better in some regards than other more heavily regulated european countries.
Illegality of Cross-State Insurance Purchases - Consumers are prohibited from reaching across state lines to purchase their health insurance. This narrows the selection available to consumers, encourages graft in each state and makes insurance pricing less competitive.
Licensure of Medicine - Doctors, clinics, hospitals and insurance providers must become licensed by local, state or federal government, depending on the scenario, in order to provide care. Doctors are licensed by the American Medical Association and granted "scope-of-practice" privileges by states,hospitals and clinics are licensed by municipalities, and insurance providers are licensed by state governments. The essential function of licensure in this case is to exclude would-be providers. Licensure has capital and credential requirements, which exclude providers which are lower-quality and lower-cost. For example, a would-be doctor may not have attended a prestigious medical academy but could diagnose common diseases. Hospitals require "certificates-of-need" in order to start construction, which are handed out by municipal or state planning boards. Hospitals can create local monopolies by influencing planning boards not to award "certificates-of-need". Thus, there is a restricted supply of medical facilities and professionals.
Insurance Alternatives Regulated - At the turn of the century, people belonging to fraternal societies were able to afford basic medical care for the entire year for just a day's wages. Fraternal societies were created as an alternative to insurance companies, where members could buy into the communal pool and then collectively hire a doctor to work on wages. Elitist doctor's were humiliated by this 'lodge-practice' and demanded the AMA be created, which then only granted licenses to those who did not do 'lodge-practice'. Mutual aid societies withered away in response to both the licensure and the capital and reserve requirements which were imposed on all 'insurance companies', which were too burdensome for the comparatively small mutual aid societies to comply with. Competition in insurance stagnated as alternatives were prohibited.
Unionism in Medicine - Medicine is a unionized industry. Nurses and other random hospital personnel, through their unions, demand that certain processes be made impossible unless under the supervision of a unionized worker. This means that jobs which require only the labor of one person become jobs that require the labor of six people. The hospital, and ultimately the taxpayer, then has to pay for said extra labor. This also raises the barrier to entry for possible competing clinics, if they can't provide certain services without hiring unnecessary workers.
Patents - Patenting is when a government gives an inventor a monopoly over an idea. Said inventor may then punish others should they try to use the same idea, using only their own private property. This limits the amount of providers-per-innovative-idea to one. Some might say that patents are a necessary carrot to the proverbial horse for spurring innovation. Patent lawyer Stefan Kinsella disagrees, saying that empirical evidence suggests that patenting actually has a depressing effect on innovation. Patenting in the medical industry leads to needlessly expensive medical goods, namely machinery and pharmaceuticals.
Food and Drug Administration - The FDA is an organization which screens products for safety and quality before giving them the 'green light' for sale and consumption. It has also been captured by agribusiness corporations since its very inception. It slows the release of new medicines, prohibits people from trying alternatives, and occasionally seizes property and privilege only to confer it to a state-blessed enterprise. This discretionary authority, especially when seized by monopolistic interest, leads to slowed innovation, fewer products available, and product markups as large as 37 times.
Medicare/Medicaid Price Fixing - The Medicaid and Medicare programs set the minimum reimbursement rates, which companies then use as a baseline. This system encourages you to go onto an insurance plan. Physicians offer lower prices to clients with insurance to try to attract business and then charge higher prices to make up for said insurance discount. This means then, that those without insurance and can probably least afford care, end up paying the most for it. Without price-fixing for procedures and treatments, there would be no general minimum charge and physicians wouldn't have to discount insurance companies to attract clients.
Paperwork - Paperwork in general is a restriction on business. It raises the costs of a business; as entrepreneurs are forced to comply with regulations, they must also employ lawyers and pencil pushers to sort through red tape. This disadvantages small businesses as they aren't politically connected enough to avoid regulation and also are more sensitive to high costs of businesses than are large businesses. Paperwork slants markets in favor of well-established businesses.
Institutional Tilt Towards Insurance - When everyone is encouraged to go on health insurance, everything is encouraged, and even employers are encouraged to provide health insurance, the consumer's function as a discriminator and cost-cutter is qualitatively altered. Instead of economizing and considering every purchase of medicine, the care-seeker will simply ask for help and sign the bill. Care-givers, acknowledging this, will sell high-cost options primarily and not suffer for it, seeing as the care-seeker's treatment is being covered by his insurance company. What happens over time when consumers do not seek the best bang for their buck is that both treatments and insurance rates will go up.
Mandatory Coverage of Specific Conditions - Insurance companies are compelled by law to offer coverage to certain treatments in all of their policies. This benefits the person with said medical condition to the disadvantage of all without said medical condition. All are forced to pay for the now higher rate, due to the increment of risk added by mandatory extra coverage, whether they want to be covered for said condition or not. If a person A has a certain condition, it is not the responsibility of the next person to subsidize the treatment of person A. Insurance plans become homogenized and unnecessarily expensive. This encourages people not to avoid certain conditions, such as obesity or heart disease.
Aid to Hospitals (Equipment) - Hospitals receive aid for having the latest and greatest hi-tech equipment. This encourages hospitals to spend too much money on expensive equipment, partly paid for by taxpayers. And since the hospitals aren't buying the equipment because of a legitimate need but because of a political incentive, they are not discriminating buyers. Thus, we can expect that suppliers of expensive medical equipment will raise prices comfortably without fearing that hospitals will stop buying.
Aid to Hospitals (Patients) - The government will pay for a share of a patient's hospital bill if it is sufficiently huge. Since hospitals are non- competitive they will respond by ratcheting up the hospital bill to get federal money. Citizens, in the aggregate of their tax forms and ER bills, end up paying twice as much.
Aid to Employers - The federal tax code encourages employers to provide their employees with health insurance. Some might say this is great, but it is not. Employers offer that health insurance out of your wages. Though the wage compensation you would get if employers were not encouraged to off you health insurance would probably not, at this moment, be as big as the total value of the health insurance he does provide you, at this moment, it causes some big problems. Firstly, it programs you to clutch your job like a life-line, whereas if you acquired insurance independently, you could go where you liked. If you value independence and self-respect, that's problematic. This also disables the consumer choice mechanism; no one will leave their job just to get a different healthcare plan. Secondly, it puts everyone on bloated insurance plans, which leads to the problems described above (insurance for things you don't need to be insured for, can pay for yourself, don't need to pay for, etc.)
Inflation - Since much of the deficit is financed out of Open Market Operations and Medicaid and Medicare are about half of the deficit, a sizable chunk of all printed money goes into government spending in healthcare. This means that the government's buying activity in healthcare drives the prices up and those not on the government healthcare teat will have to pay higher prices; not having had the privilege of paying yesterday's low prices with tomorrow's new money, they will have the pain of paying tomorrow's high prices with yesterday's old money. As the deficit gets worse, more debt will have to be monetized, and there will be more inflation in healthcare. Meaning, healthcare isn't getting any cheaper.
Claim: Healthcare is Inelastic and can’t Therefore be Left to the Free Market
https://t.co/6VHEpPG5Um
One of the 100 highest-spending diagnosis-related groups (i.e., categories of medical problems that determine payment for hospital stays) for inpatient care, 73 percent were shoppable; of the 300 highest-spending diagnosis-related groups for outpatient care, 90 percent were shoppable. In fact, “There is evidence—based on a study of three conditions and two common surgical procedures, that higher-quality hospitals attract a greater market share at a point in time and also grow more over time.” According to another article by Jason Shafrin, medical care and prices do have an elastic relationship. The results show that the price elasticity of expenditure on medical care is -2.3 across the .65 to .95 quantiles of the expenditure distribution, with a pointwise 95% confidence interval at the .80 quantile of -2.5 to -2.0. Although the price elasticity estimate varies with expenditure, there is a fairly stable elasticity across the estimated quantiles. A possible objection to this is that emergency medical services are completely unshoppable but I have already addressed this argument below:
Claim: Emergency Care is Unshoppable and can’t be Left to the Free Market
Response: This doesn’t take into account the fact that private health insurance would prevent hospitals from raising the prices of emergency services intentionally. For example, just as you get yourself car insurance, before you have a crash, you get yourself a year-subscription of medical service that would cover emergency services. Accordingly, a book by Christopher Rachels explains: for a risk to be insurable at all, one must be unable to predict with relative certainty those clients who will be "winners" or "losers" (“winners” and “losers” in this context simply refers to those clients who received more (winners) or less (losers) in reimbursements than he/she paid into the system. This should not be confused with someone who comes down with cancer which his/her insurance covers as being a winner in the general sense of the term. Thus, health risks which are largely in one's control are not "insurable" as they are neither unforeseeable nor random in occurrence. If the occurrence of a particular event may be systematically predicted, then any attempt to cover this would undermine the purpose of insurance. That is to say, insurance is intended to act as a sort of lottery in the sense that each of its individual clients are largely uncertain in advance regarding the degree to which they will have insurable damages to claim. However, they realize if such an insured event occurred, they may not have the funds available to pay for the resulting damage. Thus, they may choose to purchase coverage as a means to protect them from this risk. Since you obviously can’t predict when an individual needs an emergency service, insurance companies will indeed cover emergency services. These insurance companies usually pick which hospital is best for the consumers so that they can attract the most customers to maximize profits. To more effectively determine optimal pricing at any given point in time, insurance companies will be compelled to engage in continual in-depth research regarding the field covered. Naturally, those companies that attain more accurate data on such risks will be at a relative advantage to their competitors as such information will reveal more precisely the potential risk and frequency of its payouts to clients. Insurance companies will also negotiate with the hospital to get them to lower prices especially for emergency services. If one hospital starts intentionally raising the price of their emergency services, then that hospital would rarely make profit because no insurance company would pick an expensive hospital they have to cover the costs for. In other words, if a company uses poor data (or unverifiable prejudice) to determine prices, it will either overcharge for its services driving clients away to lower cost alternatives or undercharge relative to actual risks, resulting in losses, which will either cause the company to alter its practices or go broke, thereby freeing up the resources it once commanded to more efficient and profitable firms in the marketplace. In addition, even if you were uninsured, the truth is that emergency rooms account for only 2% of all healthcare spending. This is the smallest fraction of care, of which the hospitals would still compete on price. There isn't an "emergency surcharge” under free market healthcare. Everything the hospital would treat you for is something that they would treat on a non-emergency basis. An emergency heart bypass would be the same as a non-emergency one, the only real difference being in if they needed more supplies which you'd pay for if it were non-emergency and they used more supplies. The idea that emergency care is somehow some different thing completely detached from the rest of the care is ludicrous. It would be like you rushing into a grocery store last minute to buy supplies for a party versus buying them a week in advance. Hospitals essentially are not tacking on a surcharge for the urgency of your need. In addition, a hospital cannot exist by solely providing overpriced treatment for emergency services, because if it could exist, that would mean a demand for this kind of work would exist in the region and more hospitals would very quickly open. Especially by repealing all the government regulations (ie: CON laws) that have caused a decrease in the quantity of hospitals, a free market will spur more hospitals into the market than ever before. Then, there's the fact that such a hospital would have a horrible reputation and would quickly go bankrupt because people would prepare for such situations (ie: by purchasing insurance), if it were to exist. Not to mention the fact that private charity hospitals would also exist to assist those in need. Hence, emergency medical services would still be adequate under a free market.
And Like I already said, the healthcare system in America is not a free market, it's heavily regulated just as the insurance and their fucking IP
Letting your child starve without abandoning them is forestalling the guardianship and this would be an aggression. You can discriminate the parents in any way you want from your community btw and you should. I never made a moral claim that it is okay to not care for your child. Legality is not morality.
For the rest of the points, I'm still asking. Do you think markets or planning is more efficient? You didn't make a coherent argument why health care is more efficiently run by the state and not by private companies. If you look at canada, uk and germany for example their health systems are crumbling and are getting less service for more money. Germany is also a country with much more bureaucracy and regulation than the Nordic models, why is that?
1. You actually debate the strawman, read the argument again.
2. There are multiple races that are generally more low time preference? I count asians but not blacks lmao
3. The fact that you don't see that the regulations and IP laws are the exact reason why american healthcare is so expensive but you want to regulate exactly this market is actually priceless lmao https://t.co/w0ViSzNXha
4. They could even work less hours with less intervention lmao. The intervention is retarding their economic progress not advancing it
Denmark, Sweden, and Finland are not the stripped-intervention counterfactual. They are the same residual-market setup as Norway: high economic freedom rankings, private property that still prices most production, and high-trust low-time-preference populations (white people) that accumulated capital before the welfare expansion. The policies ride on that base, they do not generate it.
Denmark is not oil-free. North Sea extraction since 1972 has delivered hundreds of billions of DKK in state revenue. Sweden and Finland lack Norway-scale rents but share the same institutional and cultural package. Remove the market elements and the high trust, and the tax-and-transfer apparatus produces the ordinary calculation problems and capital consumption. There is no pure socialist version of the Nordics that works.
Drugs, firearms, and alcohol together explain roughly 1.6 years of the US life-expectancy gap; opioids alone account for about 0.5–0.9 years. The residual is dominated by obesity and behavior, not high deductibles blocking preventive care. US spending per capita is higher. Administrative costs exist under private insurance; single-payer systems simply ration and bureaucratize instead. Productivity per hour is comparable, yet Nordics work substantially fewer hours (lower GDP per capita) and have recorded slower productivity growth since 2000. Welfare is literally parasitic per definition.
Are you actually proposing that just because of the government the market works so well lol? If thats the case why aren't you socialist then?