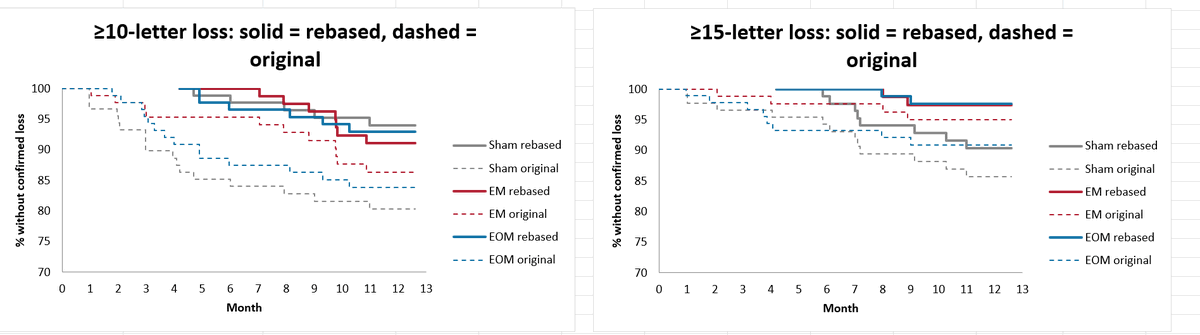
@BioLite_MD Mostly to make a point - I don't believe the drug would have an impact in early months. Placebo did worse in early months. Supposed effect only shifted patients from the 10-14 letters lost to 15 letters lost bucket. Be careful how you deal with the excluded patients.
In addition: Generic tafamidis is arriving in Europe, and France has published the first price.
France: the Journal officiel (28 Oct) set Tafamidis Zydus 61mg at €1,088 per box of 30 (€935.47 ex-factory), effective 1 Nov. That's ~83% lower than branded. More are lined up in France. Viatris, Zentiva, EG and Biogaran all have hospital/pharmacy codes registered, and patient groups say generics can be marketed from 19 Nov. Prices for those four haven't been published yet.
Generics are approved for hereditary ATTR-CM only. Vyndaqel keeps orphan exclusivity in wild-type, the large majority of patients, until Feb 2030. But expect European payers to push generic use as hard as the rules allow, and watch for leakage into wild-type.
Germany: no generic is listed in public pharmacy databases yet, but Accord's is approved EU-wide, and Adalvo and Welding hold European approvals that likely include Germany. Generics can price freely at launch.
The bigger lever is a Festbetrag (reference price). Once generics are on the market, the G-BA can form a Stufe 1 group for the same active ingredient. Orphan status doesn't block this: sapropterin got a Stufe 1 group in April 2026. Key precedent: the G-BA and the BSG (2018) treat Stufe 1 groups as active-ingredient-based and, as a rule, ignore approved indications. The G-BA has rejected "no alternatives in the group" arguments before (etanercept, zoledronic acid).
Pfizer has already moved: in August it launched a Vyndaqel 61mg film-coated tablet in Germany, approved for wild-type only, at the same €11,128 price. Pfizer says ~96% of German patients are wild-type.
Can the tablet be pulled into a reference price group? On precedent, likely yes. The G-BA routinely groups "oral dosage forms" together (abiraterone covers film-coated and plain tablets), and only therapy-relevant bioavailability differences count. Pfizer says tablet ≈ capsule.
G-BA consultation plus GKV-Spitzenverband price-setting typically takes months after generics launch, and a tablet script can't be swapped for a generic capsule in the meantime.
Obviously this impacts $PFE and Bayer more directly, but it's a headwind for $BBIO's European royalties too. $BBIO sold 60% of its European royalties on the first $500M of annual Beyonttra sales, so much of the near-term exposure sits with the royalty buyers. The bigger risk for BBIO is the tranche it fully keeps: if price erodes, Beyonttra may take much longer to get above $500M, or never get there.
Tail risk: BBIO signed an MFN deal with the administration in Aug 2026. If MFN expands and benchmarks against European acoramidis pricing, cheaper tafamidis dragging down Beyonttra's price could eventually pull down Attruby's US price.
I’m short a small amount of $BBIO. FDA flagged a new renal impairment signal for Attruby. FAERS shows a higher rate of AKI vs tafamidis, in line with the pivotal trial but now on a bigger sample. Could mean a Warnings & Precautions label change over time if signal is real.
@oncinvestor@BlaseBio@lcbnuoH I don’t bet on M&A because predicting it is hard. Year 1 launch numbers will likely look soft. Even with a path to profit, management should raise now. If a buyer calls after approval, you want leverage, not a cash clock. Market won’t like it near term, but it’s the right move.
Without stating the obvious that every sell side target is high. UBS's $60 PT = 3x peak sales (and there actually an erorr on their current model should be $56), a takeover multiple. Their own trading comps are 1.0x. It also needs ~$2B of GIST (60% share, 19 mo on therapy). On their inputs: ~$30 standalone, ~$38 with some M&A odds. $60 needs a near-term buyout I don’t see.
Your claim that acoramidis beats tafamidis isn’t supported: no head-to-head trial, and ATTRibute-CM all-cause mortality (compared to placebo + low double digit taf drop-in) was not significant. My view: head to head, little difference. You’re right that eGFR drops were known: EU already warns while FDA took a softer approach originally. With more real-world AKI reports and FDA now evaluating, I think a US Warnings & Precautions update is likely.
Lots of people on X call themselves dumpster divers. None of them are competition for me.
Small position in $KYNB. The biggest overhang (other than the pipeline) was the NovaQuest balloon payment, and they've paid it down.
Q4: hopefully they dump roxadustat on a partner for any amount upfront. Worst case, they get some funds (you know the usuals) to finance it and get a cash infusion. FG-3246 is a potentially interesting post-PSMA radiotherapy.