Consultant cardiac electrophysiologist, Golden Jubilee National Hospital and Glasgow Royal Infirmary. Honorary professor, @UofGlasgow. Amateur percussionist.
Presented at #ScientificSessions26:
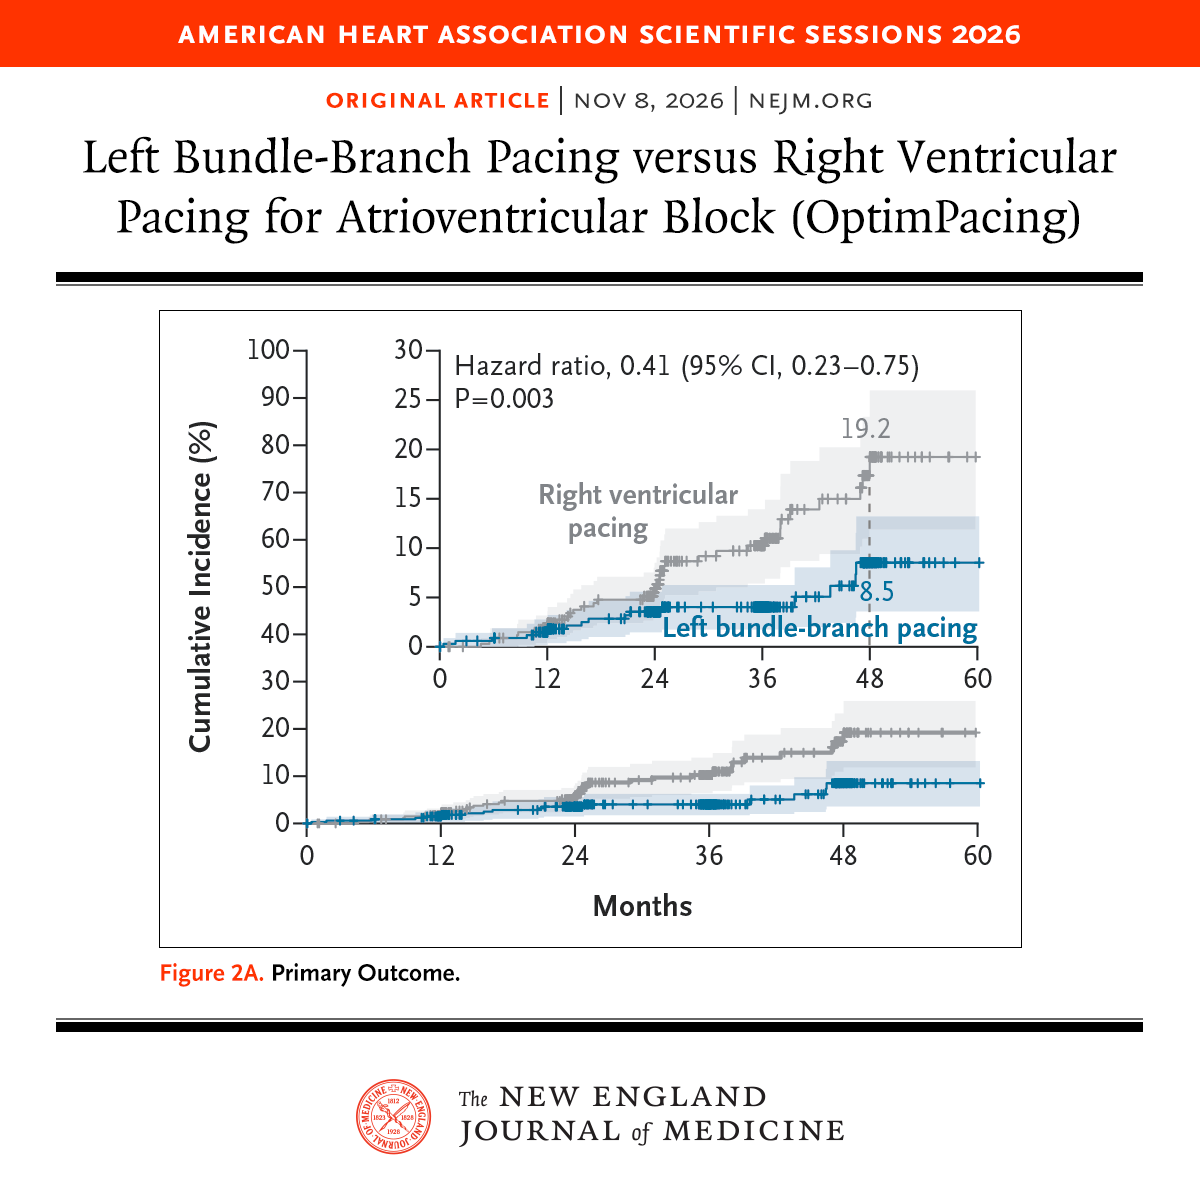
In patients with atrioventricular block, left bundle-branch pacing resulted in a lower incidence of a composite of death, hospitalization for heart failure, or pacing-induced cardiomyopathy than right ventricular pacing. Full OptimPacing trial results: https://t.co/Fg0lv9xcka
@AHAScience
Excellent presentation by @lsjMD at International Congress on Electrocardiology today:
Staccato v Legato patterns of parox AF
Different smart watches have different thresholds for picking up AF
40% of paroxysms of AF occur overnight (when people often take off their watches)!
@cpgale3 It strikes me that there is little or nothing about heart rhythm management (despite all the advances of the past 20 years) ... Rather like the National Service Framework from 2000, where they needed an extra "Arrhythmia" chapter 4 years later
Fantastic to see @theaspiredstudy has been picked up by @stemlyns - read @EMManchester thoughts on our @NEJM paper (accessible here: https://t.co/wc13bSsRqy) at https://t.co/5TjKb1PZA7
Returned home from #ESCCongress and now indulging my other passion! First rehearsal of the new term; Berlioz, Elgar and Tchaikovsky to look forward to over the coming weeks.
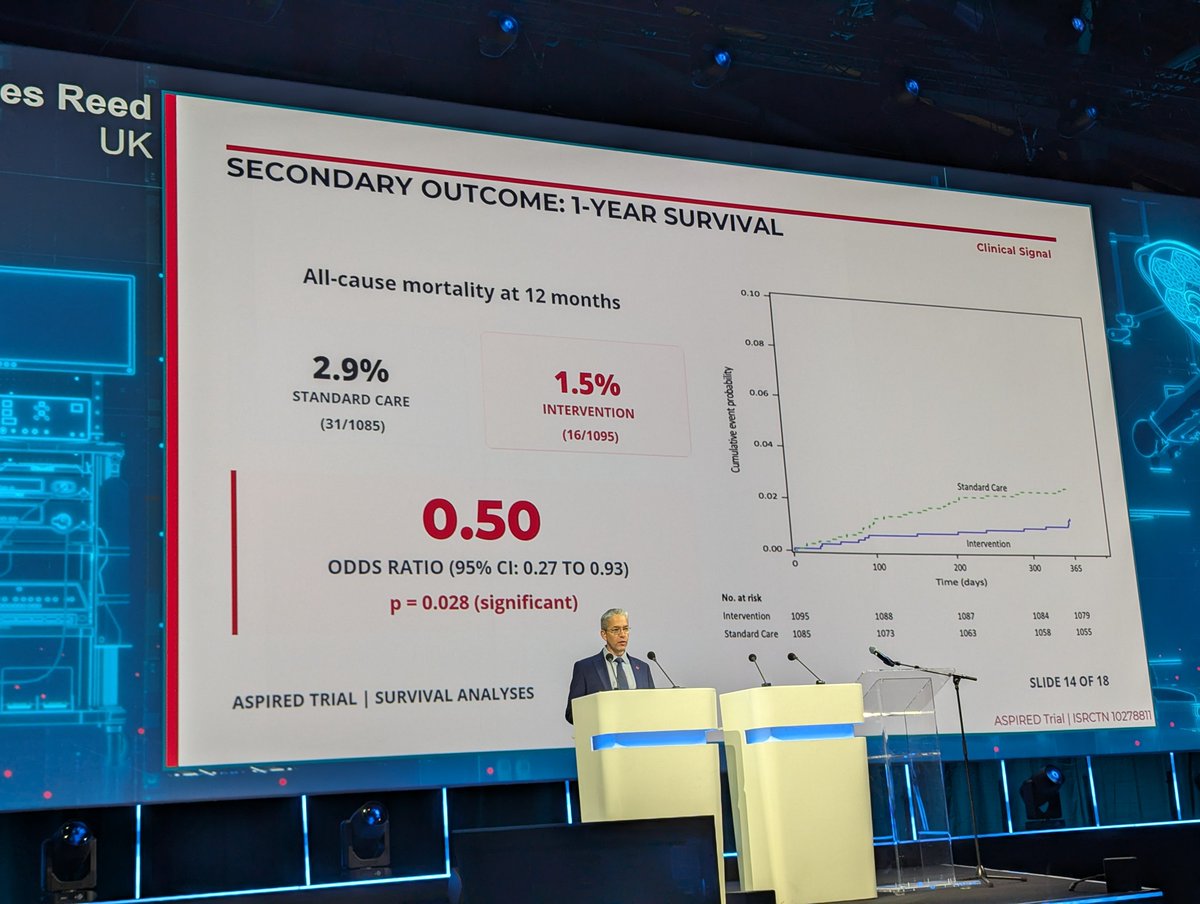
Congratulations to @mattreed73 and ASPIRED study team - presentation at #ESCCongress (and publication in @NEJM ). 14-day ECG monitor in pts with syncope did not reduce syncope burden - but did identify high risk patients and resulted in a 50% decrease in all cause mortality!
A major development in the 2026 ESC Heart Failure Guidelines is the move toward a simpler EF cutoff: HF with LVEF <50% versus HF with LVEF ≥50% — moving away from the traditional three-way separation of HFrEF, HFmrEF, and HFpEF.
And within this new framework, the guidelines send another clear message:
AF in heart failure is no longer just a rate-control problem.
➡️ When #AFib is driving LV dysfunction, restoring sinus rhythm is recommended, with catheter ablation playing a central role.
➡️ In selected patients with #AFib and HFrEF, catheter ablation should be considered to reduce heart failure hospitalization and improve survival.
➡️ In HFpEF, the evidence gap remains, and treatment decisions should be individualized.
The guidelines also highlight an old friend: digoxin. Once pushed to the sidelines, it again has a role in rate control for patients with AF and heart failure, particularly when other agents are ineffective, contraindicated, or poorly tolerated.
The key message for patients is simple: AF may be a driver of heart failure, not merely a consequence. Recognizing and treating it early could improve symptoms and outcomes.
The next frontier is clear: can eliminating AF change the natural history of HFpEF? #CASTLEHFpEF
#ESC2026 #ESCCongress #AtrialFibrillation #HeartFailure #HFrEF #HFpEF #Ablation @lamcardio@Phiso_de@chris_sohns@shivkumarmd@S_NarayanMD@drjohnm@TulaneTriad@TulaneHeart
With my great friend and namesake Derek ConnElly
nearly 30 years of organisations cancelling one of the two of us but we always take it with good humour
this time it's @escardio but they have all done it [some several times]
Sudden death is a poor end point for this reason. There is so much scope for bias. And remember that most sudden death is non cardiac anyway if you do rigorous autopsy.
It's a fantastic study and new icd trials are overdue
@DrMarthaGulati@escardio The reduction in SCD is not surprising. A patient who dies with an ICD in situ is less likely to have death classified as "sudden". Also think of the poor patient who gets a shock for VT/VF and dies of heart failure shortly afterwards - thats then a "non-sudden" death @drjohnm
@DrMarthaGulati Personal bias, but looking forward to CMR guide HF results (Sat 29th) addressing the question of 1y prevention ICDs in patients with LVEF 35-50% and high scar burden.
Also ASPIRED (Mon 31st) should be a game changer for syncope @mattreed73