𝗧𝘂𝗿𝗻𝗶𝗻𝗴 𝗣𝗮𝗴𝗲𝘀 𝗧𝘂𝗲𝘀𝗱𝗮𝘆 | #ASH2026 edition
𝟭𝟬 𝗺𝘆𝗲𝗹𝗼𝗺𝗮 𝗮𝗯𝘀𝘁𝗿𝗮𝗰𝘁𝘀 𝗜’𝗺 𝘄𝗮𝘁𝗰𝗵𝗶𝗻𝗴 𝗳𝗿𝗼𝗺 𝗜𝗻𝗱𝗶𝗮
With teclistamab (Tec), elranatamab (Elra), talquetamab (Tal) and SC Dara in our toolkit, my questions are about sequencing, duration, safety and access.
𝟭. 𝗠𝗼𝗻𝘂𝗺𝗲𝗻𝗧𝗔𝗟-𝟲 | #426
At 13.4 months’ median follow-up, Tec+Tal vs EPd/PVd: PFS HR 0.11; Tal+Pom also improved PFS/OS. ~80% were anti-CD38-refractory. Watch the planned 26-cycle bispecific cap and immunoglobulin replacement burden.
𝟮. 𝗠𝗮𝗴𝗻𝗲𝘁𝗶𝘀𝗠𝗠-𝟱 | #424
Elra vs DPd: PFS HR 0.56. Only 5.9% had prior anti-CD38 exposure: important when interpreting this for Dara-refractory relapse.
𝟯. 𝗪𝗵𝗶𝗰𝗵 𝗯𝗶𝘀𝗽𝗲𝗰𝗶𝗳𝗶𝗰 𝗻𝗲𝘅𝘁? | #2205
In a retrospective 187-patient series, 136 target-switchers had median PFS ~4 months with the second bispecific. Activity remains possible; the best order is unresolved.
𝟰. 𝗖𝗮𝗻 𝘄𝗲 𝘀𝘁𝗼𝗽 𝗯𝗶𝘀𝗽𝗲𝗰𝗶𝗳𝗶𝗰𝘀? | #845
43 selected responders stopped; 12-month treatment-free PFS was 85.4%. Relevant to financial and infectious toxicity; selection bias limits conclusions.
𝟱. 𝗜𝗻𝗳𝗲𝗰𝘁𝗶𝗼𝗻 𝗽𝗿𝗲𝘃𝗲𝗻𝘁𝗶𝗼𝗻 | #2275
Modelled 1-year grade ≥3 infection risk: 21.0% with continuous vs 38.3% with observed immunoglobulin replacement. Supportive care belongs in the budget; replacement was not randomized.
𝟲. 𝗪𝗵𝗼 𝘀𝗵𝗼𝘂𝗹𝗱 𝗿𝗲𝗰𝗲𝗶𝘃𝗲 𝗧𝗮𝗹? | #934
Among 43 IHC-evaluable Tal patients, none of 19 with low/negative GPRC5D responded. Could pretreatment IHC improve selection? Retrospective data need validation.
𝟳. 𝗣𝗘𝗥𝗦𝗘𝗨𝗦 | #111
After ASCT, 236 patients stopped Dara per protocol; lenalidomide continued. Eligibility required ≥24 months maintenance, ≥CR and ≥12 months sustained MRD negativity by serial NGS.
𝟴. 𝗔𝗤𝗨𝗜𝗟𝗔 | #112
In high-risk smoldering MM, 7-year OS: 87.8% vs 78.7% with 3 years of SC Dara vs monitoring. Risk definitions and reliable follow-up are central before treating asymptomatic patients.
𝟵. 𝗕𝗲𝗹𝗮𝗻𝘁𝗮𝗺𝗮𝗯 𝗲𝘆𝗲 𝗺𝗼𝗻𝗶𝘁𝗼𝗿𝗶𝗻𝗴 | #419
A 30-patient BelaRd study in newly diagnosed MM tests symptom-guided dosing. Both groups still had eye examinations. A practical implementation question for belantamab.
𝟭𝟬. 𝗘𝗫𝗖𝗔𝗟𝗜𝗕𝗘𝗥-𝗥𝗥𝗠𝗠: 𝗶𝗯𝗲𝗿𝗱𝗼𝗺𝗶𝗱𝗲 | #114
IberDd vs DVd: 10⁻⁵ flow MRD-negative CR, 41.1% vs 20.7%. PFS results await presentation. A CELMoD future-access watch: 84.3% grade 3/4 neutropenia; anti-CD38-refractory patients excluded.
For MRD, 10⁻⁵ is not 10⁻⁶; matching sensitivity also does not automatically make flow and NGS interchangeable for a trial’s treatment decisions.
These are abstracts to examine closely, with fuller data still to come.
#TurningPagesTuesday #MMsm
𝗛𝗼𝘄 𝗹𝗼𝗻𝗴 𝗰𝗮𝗻 𝗿𝗲𝗺𝗶𝘀𝘀𝗶𝗼𝗻 𝗹𝗮𝘀𝘁 𝗮𝗳𝘁𝗲𝗿 𝗯𝗶𝘀𝗽𝗲𝗰𝗶𝗳𝗶𝗰 𝘁𝗵𝗲𝗿𝗮𝗽𝘆 𝘀𝘁𝗼𝗽𝘀?
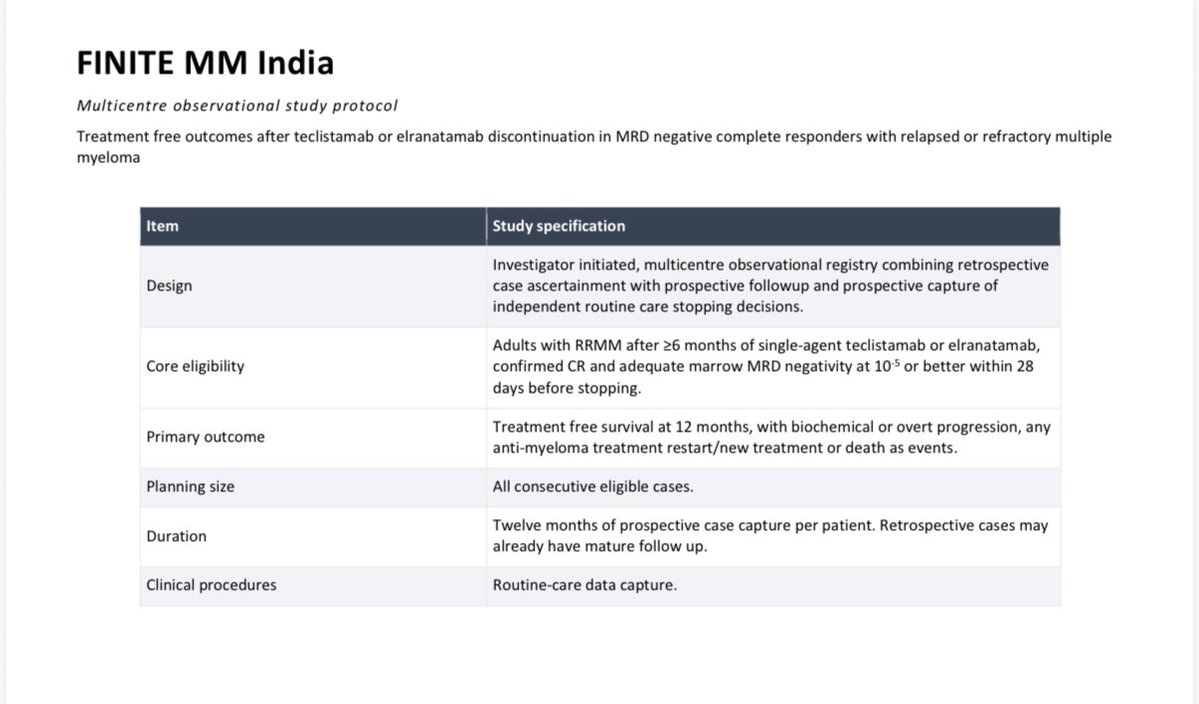
I’m inviting colleagues across India to collaborate on 𝗙𝗜𝗡𝗜𝗧𝗘-𝗠𝗠 𝗜𝗻𝗱𝗶𝗮, studying treatment-free outcomes after stopping #BiTes’ in #MutipleMyeloma.
We plan to include:
• 𝗥𝗲𝘁𝗿𝗼𝘀𝗽𝗲𝗰𝘁𝗶𝘃𝗲 𝗰𝗮𝘀𝗲𝘀: Treatment already stopped in CR because of infections, toxicity, financial constraints or a response-led decision.
• 𝗣𝗿𝗼𝘀𝗽𝗲𝗰𝘁𝗶𝘃𝗲 𝗰𝗮𝘀𝗲𝘀: Patients in whom discontinuation is planned, with systematic follow-up.
𝗣𝗿𝗼𝗽𝗼𝘀𝗲𝗱 𝗰𝗿𝗶𝘁𝗲𝗿𝗶𝗮:
• ≥6 months of BiTe monotherapy
• Confirmed CR or better within four weeks before stopping
We will assess treatment-free survival, relapse, infections, IVIG needs and retreatment outcomes-including early failures.
𝗘𝘃𝗲𝗻 𝗼𝗻𝗲 𝗲𝗹𝗶𝗴𝗶𝗯𝗹𝗲 𝗰𝗮𝘀𝗲 𝗶𝘀 𝘄𝗲𝗹𝗰𝗼𝗺𝗲. Please DM for details/any patients.
Synopsis attached. Prospective enrolment will follow protocol finalisation and required.
#mmsm
@Papa_Heme For us bmt is the easiest way to stay rich when one suffers from myeloma ! It gives us PFS which helps to see the sun rise of 2030 by which time we will have generic bites and car t cell at a fraction of the cost
Everspan is innovation - whole genome sequencing plus the preventive genomics with proteomics and whole body mri. @deepigoyal along with wearable device with a longitudinal follow up