FACS AHPBA/Board Certified HPB/General Surgeon with interests in: Liver, Pancreas, Biliary, GI Oncology, and Robotics. Proud husband, dad, and Christian.
EHL lithotripsy is extremely helpful to breakup stones which can then be easily pushed through to the duodenum. I like having a wire across ampulla and having dilated it first then flush/push through/pull back/flush to clear debris. Pushing Antegrade balloon might also work?
Surgical ligation of right hepatic artery for actively hemorrhaging massive ruptured HCC after ICG verifying adequate left sided arterial perfusion (IR not available anywhere inside a 100 mile radius). What would you have done?
@ziadtawad@DoctorBenChan Honestly, the Synchroseal I think is a better energy device than anything I've got open. Since he was hemodynamically stable, I think he'll make it through this episode. My biggest regret, though, is that with the artery formally ligated TACE/TARE is going to be very limited.
Microwave Ablation of 1.7cm CRLM during robo LAR. Joint cases (although a hassle for surgeons at times) save patients extra procedures, time, money. Safety is priority but wherever possible, with together! #teamsport
@JeyarajahRohan I agree. If I'm instrumenting the CBD I almost always either do sphinteroplasty (I've not found a safe way to do a true sphincterotomy from above) or I leave a stent and have GI come back in 6 weeks or so.
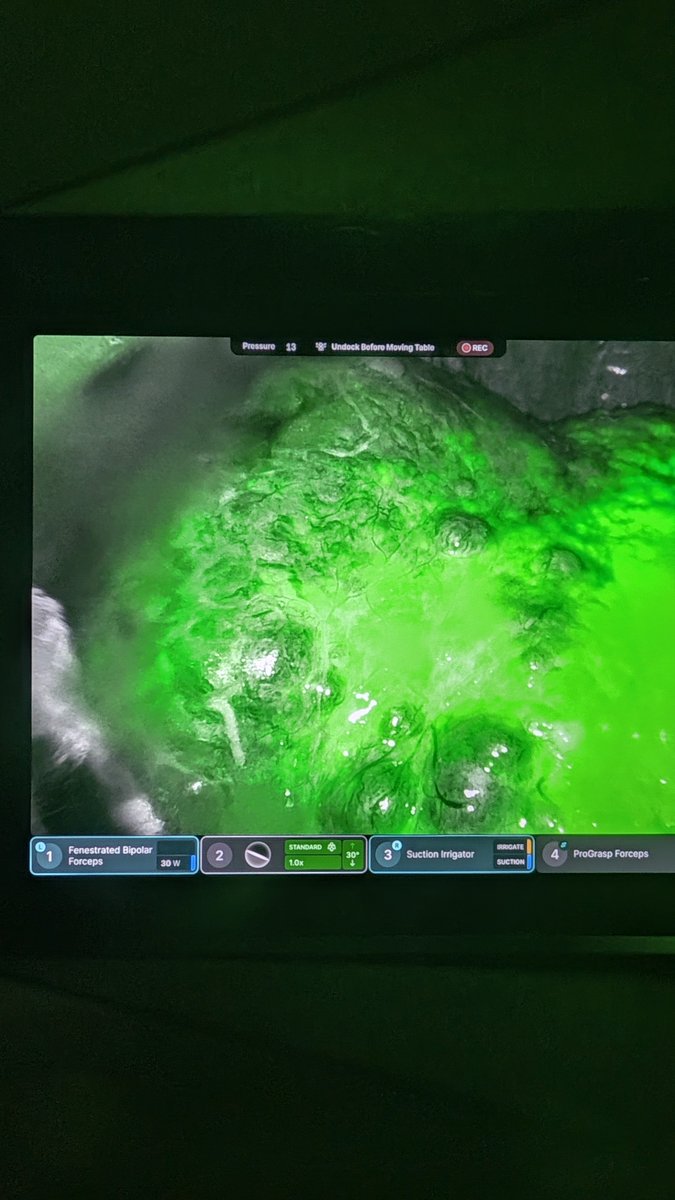
PGY1 - Spyglass CBDE during robot chole. Usually can just push these through but some times they float and spin, so snare is nice. I try to dilate the ampulla with 13Fr sheath first (just advance over wire all the way down through ampulla).
This National Grief Awareness Day, we want you to know that you're not alone. If you are grieving, CCF is here for you.
Our virtual support groups and CholangioConnect mentorship program are places to come together in community with those who truly understand.
To get connected, head to https://t.co/EkuuLniuHR 💚
@aabutaka Yeah my preferred method is to advance this through the ampulla (dilates to 13Fr) then fragment the stones up with EHL. Put wire through the scope through the ampulla then flush and push all the fragments into duo.
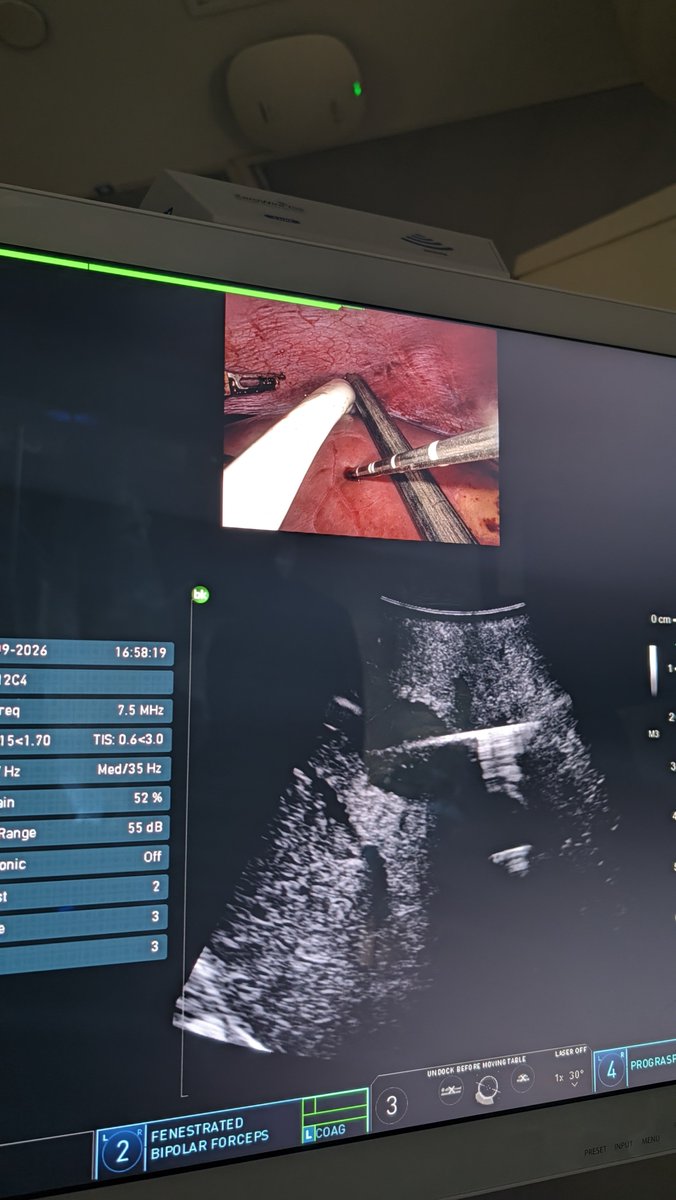
Robotic chole with common bile duct exploration with spyglass and intraop ultrasound (as sensitive as IOC and more specific). Single strange duct clearance with chole saves patients LOS and extra procedures.
@rajibaji1983 Transcystic 99% of the time (unless have other reason to go transductal). With glide wire and uropass sheath and EHL lithotripsy machine can almost always clear stones.