Sharing our latest publication on demographics table and central stage review of S1806/ INTACT trial https://t.co/2eNMXCAe9J
@PGrivasMDPhD@MonikaJoshimd@UroCancer
🚨 BREAKING: A cargo ship has SLAMMED into a river cruise ship in New Orleans, Louisiana, and passengers are reportedly IN THE WATER
Large scale rescue operation currently launching.
Pray for the souls on board 🙏🏻
A must read for trainees from Alvaro Morales on last 50 years of BCG and next frontier of molecular assays. Especially his rhetorical questions on whether mBCG should be given when utDNA converts to negative, or when utDNA stays positive. https://t.co/uTOO3KkCVb
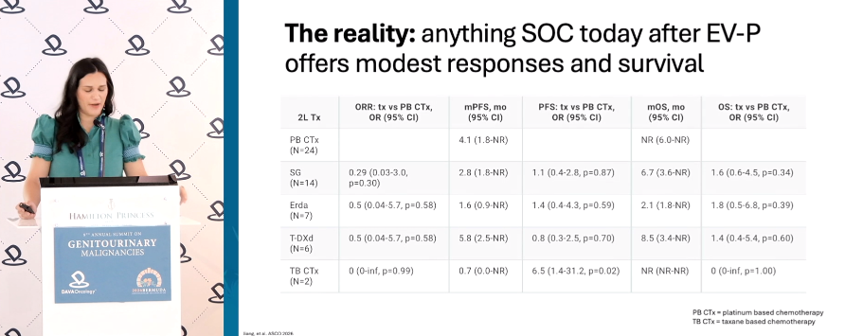
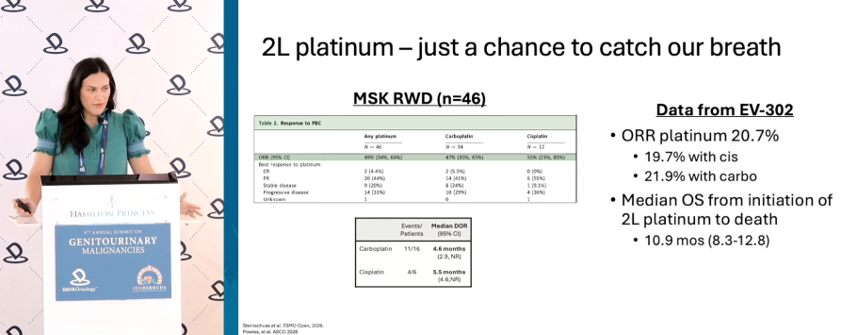
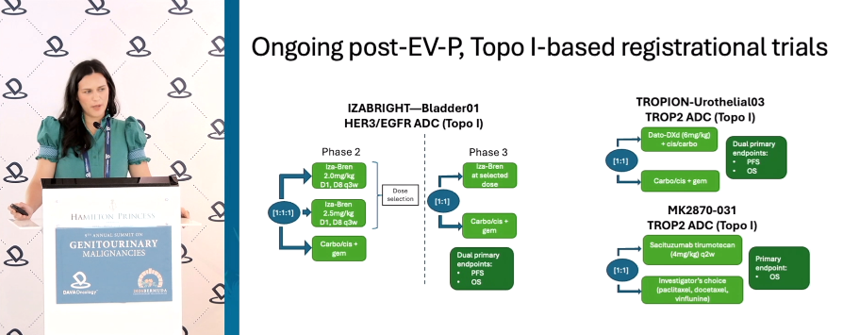
What comes after EV+P in advanced UC? @jackiebrown_MD (@WinshipAtEmory): 2L platinum yields ~20% ORR with modest PFS; erdafitinib (FGFR3) and T-DXd (HER2 2-3+) have minimal post-EV data. Trials preferred for fit pts, incl TROP2, HER3/EGFR and Nectin-4 Topo-I ADCs. #DAVAGU
Fodder for an adaptive trial on both sides of the equation (escalate/de-escalate). Add cfRNA @max_diehn for response characterization at baseline? Excited about future trials and an informed adaptive landscape in HRNMIBC beyond initial risk stratification and blunt Rx. Lots of opportunities to potentially advance our treatments. swog 1602 publication should benchmark outcomes for design.
https://t.co/8pvWgtkBbk
Data from INSITE Yair Lotan at al. effect modification of utDNA on mBCG for #bladdercancer. Argument for BCG being therapeutic and not preventative. Very informative
.@MonikaJoshimd and @PGrivasMDPhD are leading #ClinicalTrial EA8231, a phase 3 randomized trial comparing the effectiveness of pembrolizumab and sacituzumab govitecan to standard-of-care chemo in patients with advanced #UrothelialCancer. https://t.co/pAPr7iuYmR
Found what was once the repository of all my medical knowledge while cleaning out the garage!
“Dad, what was clinical decision-making like before OpenEvidence?”
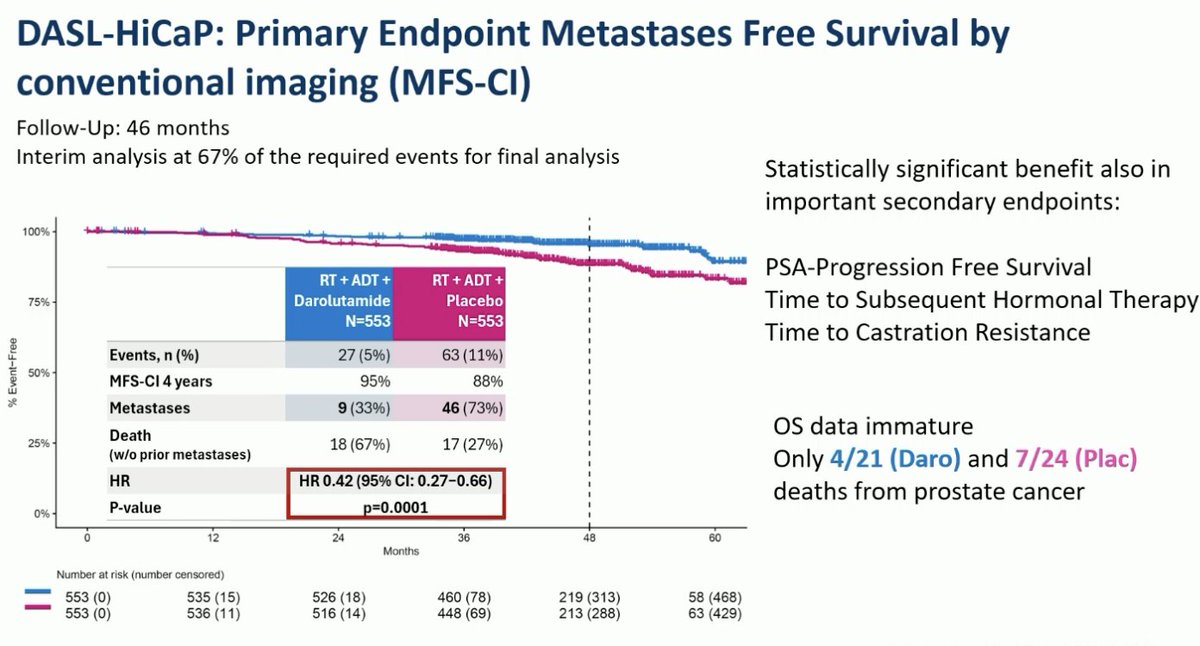
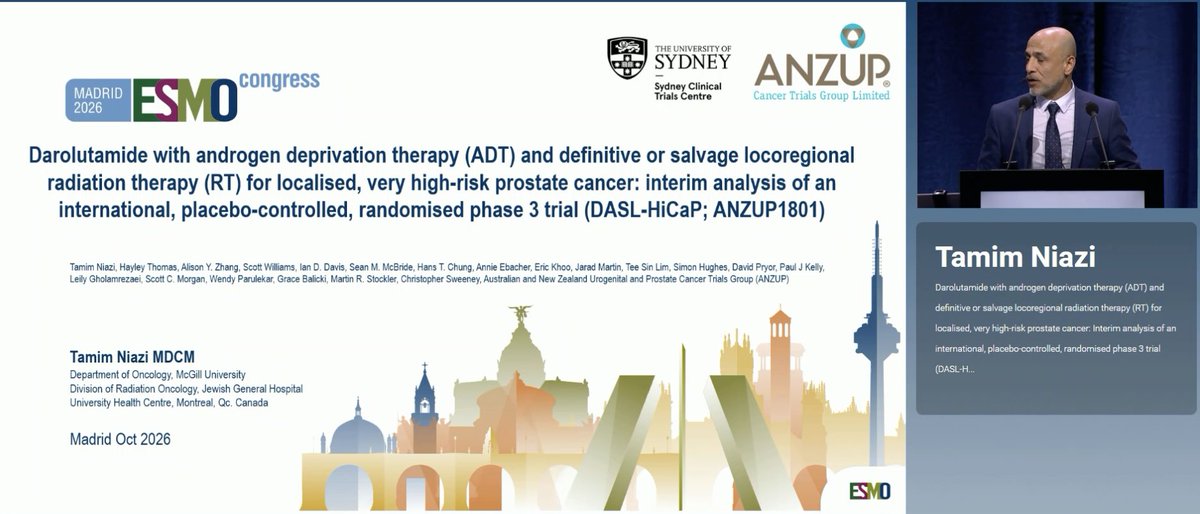
DASL-HiCaP: darolutamide on top of 96 weeks of ADT plus RT improved MFS in very high-risk localized prostate cancer, HR 0.42, 4-yr MFS 95% vs 88%.
📈 n=1,106, interim at 67% of events, 46 mo follow-up. OS immature
📝 Thanks to @Silke_Gillessen putting this into context STAMPEDE M0 (HR 0.53) and ENZARAD (HR 0.88): not contradictory, the ARPI benefit tracks metastatic risk
🎯 N1 is the clearest indication. N0 is less clear, and Gleason seems to matter
Every patient got pelvic RT, so who needs it in N0 not yet answered.
@Niazi_Dr7 #ProstateCancer #GUonc #ESMO26
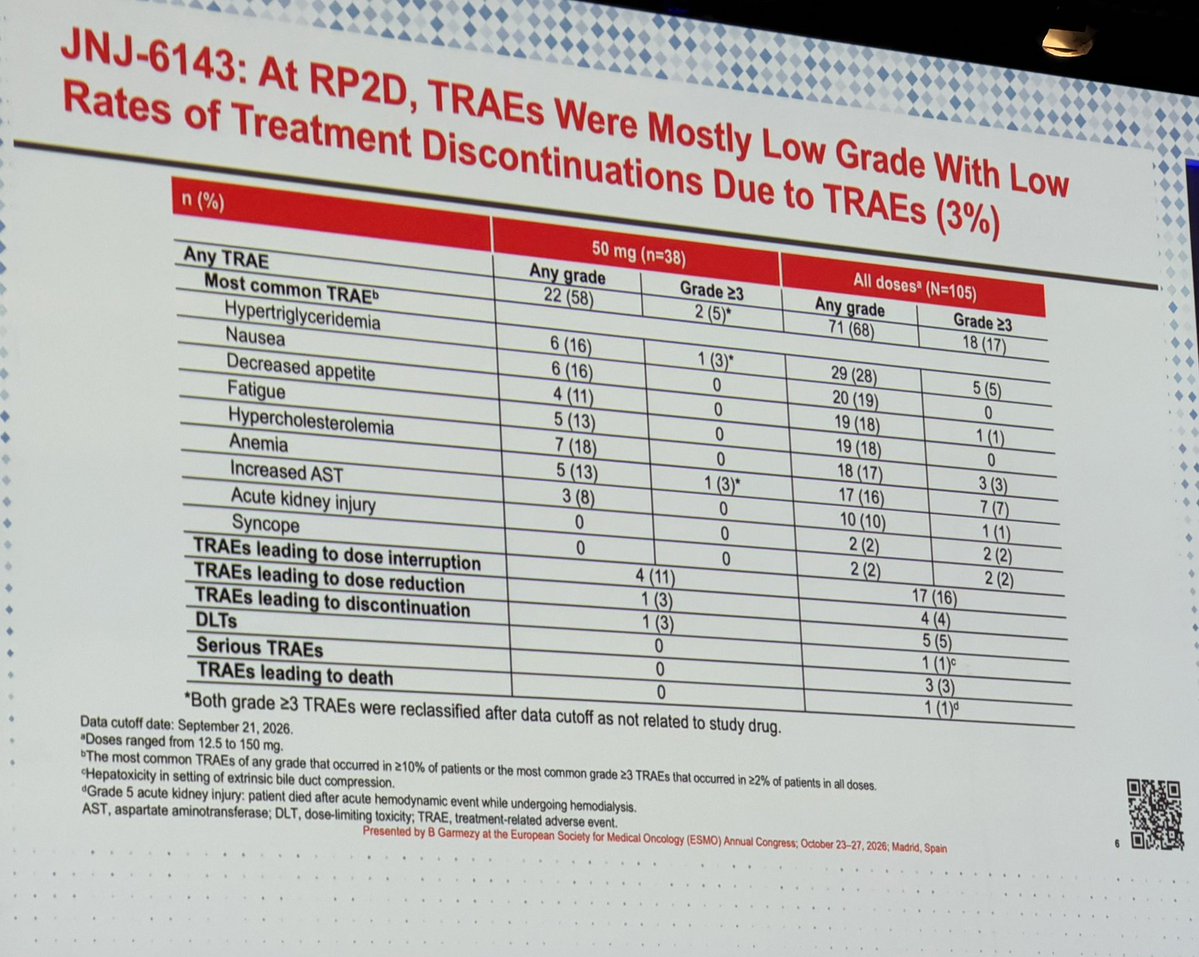
Thrilled to share updated results from JNJ-6143, the AR-BRD4 RIPTAC therapy, presented by @BGarmezy. Totally novel MOA was well tolerated, oral pill and produced significant benefit for pts (PSA90 50%, ORR 68%). P2 trial active now and more coming. Lots of potential!
JNJ-6143, first-in-class oral AR-BRD4 RIPTAC, phase 1 mCRPC: a wide window between efficacy and safety. n=105, doses 12.5 to 150 mg.
📈 50 mg daily: PSA50 77%, PSA90 48%, confirmed ORR 69%, after a median 4 prior lines
📊 PSA declines seen from 12.5 to 150 mg. 66% of all patients still on drug
🔍 At 50 mg: 58% any-grade TRAEs, no serious TRAEs. Median DOR 11.0 months, CI 5.9 to NE
Activity across a 12-fold dose range. Phase 2 is open at 50 mg.
Congrats to @BGarmezy on the presentation and all the investigators.
#ESMO26 #ProstateCancer #mCRPC #GUonc
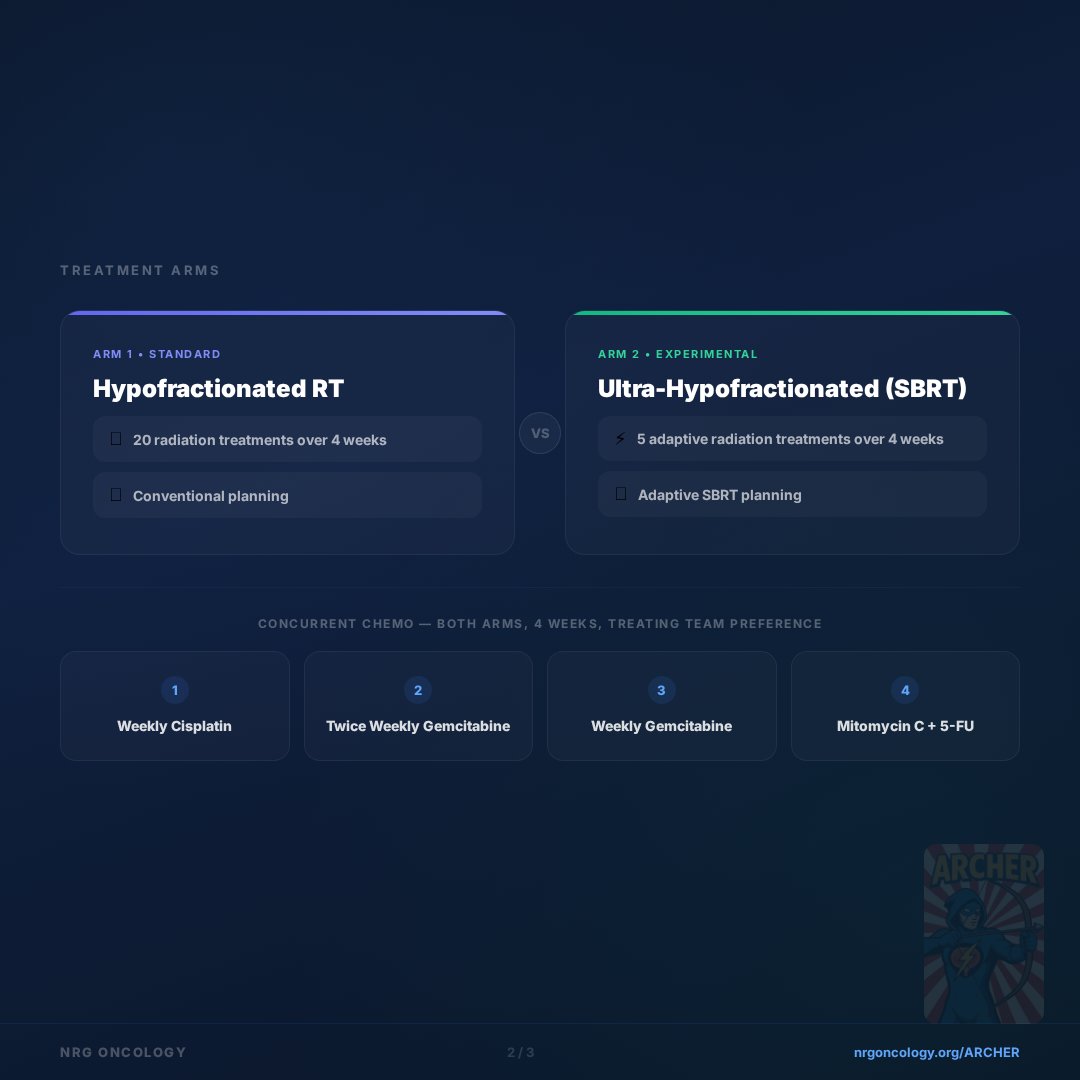
Huge milestone as the ARCHER study hits 100 patients! 🎉
It’s evaluating if 5 sessions of high-dose SBRT can shorten radiation and preserve the bladder in MIBC.
Proud to share the explainer video we created to help explain the trial below!
https://t.co/blXoe6pbXx
@eugene_pietzak So much nuance here and you are nicely pointing much of this out. If there was only a way to objectively quantify disease burden on day1 for a treatment that is given adjuvantly….(utDNA?). Does baseline burden between trials differ? @MarkTysonMD@UrogerliMD@JoshMeeks