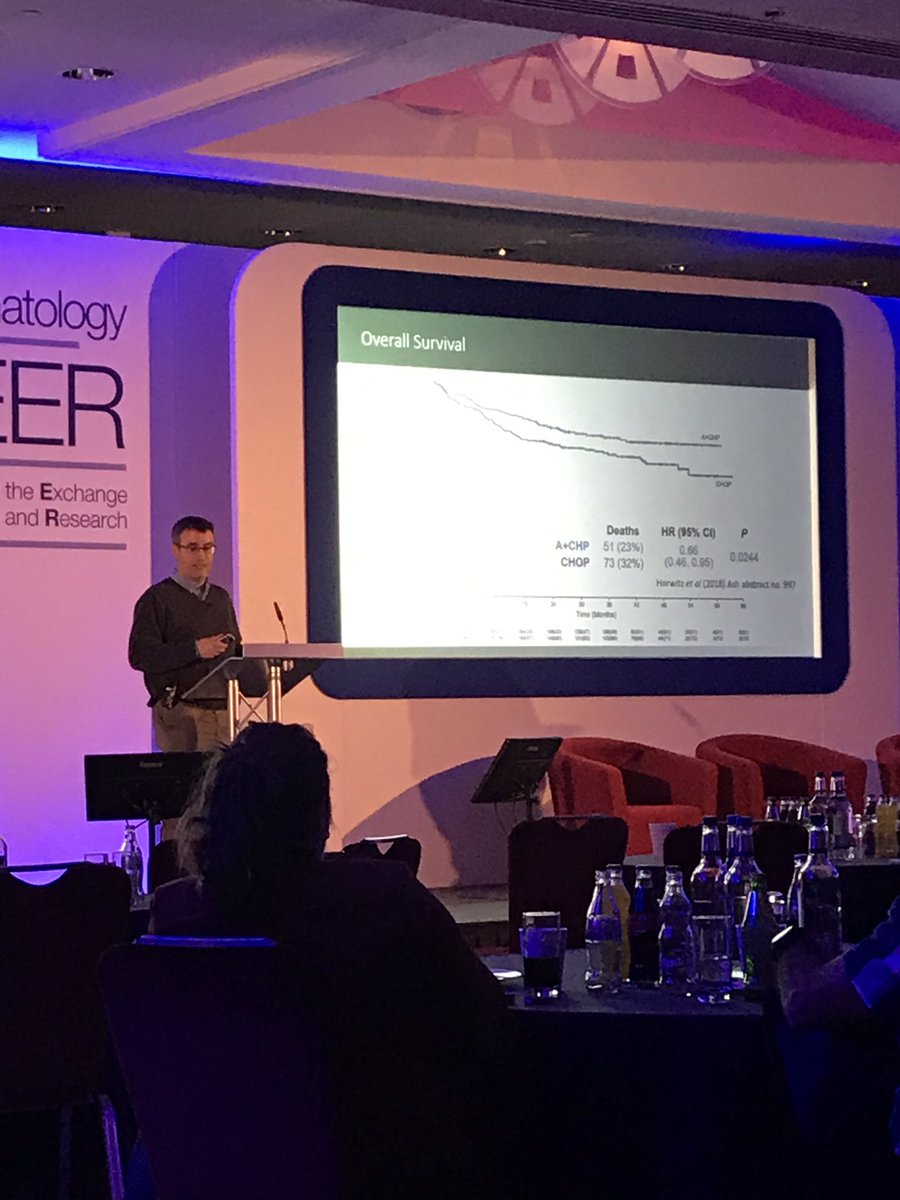
@chanyooncheah@graham74GC I don’t think POLA R CHP and AAVD are comparable though the numbers are similar. This is because in HD you can achieve similar ( better?) results with e BEACOPDac/ BEACOPP but there is no equivalent in DLBCL
@graham74GC@mike_dickinson1@NEJM@DocHutchings Yes , thanks for that , I think either bispecifics are better or a lot of people have got carried away with the hype -hopefully the former ! Though perhaps your conclusion can't be cemented in place till we see RWE for the bispecifics to compare with the POLA RWE ?
@graham74GC@SridharChaganti@BritSocHaem No bridging , no planned crossover and a primary endpoint of EFS means that the impact of SOC 3rd line CAR T is not accounted for. Interesting data but ‘paradigm shift’ perhaps not …
@graham74GC Modest advantage and possibly still not as good as eBEACOPP/ eBEACOPDac, though no direct comparative trial data to assess that. I still think BrECADD ( once HD21 is reported ) will be the way to go, unless the incorporation of checkpoint inh. into 1st line changes things again.
@chanyooncheah Rugby Union > Scores & Fixtures | Tables | Vir
SAT 13 NOV 2021 INTERNATIONALS
England
32
15
Australia
FT
HT 16-12
Steward, Blamire
TRIES
Farrell, Smith
CONS
Farrell (5), Smith
PENS
O'Connor (5)
@graham74GC@MaurerStats What about being well enough to receive CAR T infusion compared with those who were originally referred (‘pivotal’ trials presented data on patients who received CAR T infusion with re infusion as day 0).
@chanyooncheah@Dr_KatLewis Congratulations on a truly authoritative presentation, what should we do now ? We saw low levels of CNS relapse in our R CODOX M study & I think your Australian HyperCVAD experience was similar so add the French ACVBP/Ifos/MTX data & then maybe multi agent iv is the way to go ?
@hjg34095197@profghjackson Graham this is all very fine but what on earth do these percentages mean in the real world . 5% covers 60 places in the uk table - what does 5% mean . Is St Thomas’s the best hospital in the country ? Even though I trained there I am not sure ....
I recommend a superb and authoritative NEJM review by Lawrie Sehn and Gilles Salles on all aspects of DLBCL. I like the fig. linking GC/ABC and newer classifications. 1 question - they say there is now no role for IT therapy ? Evidence is poor for all CNS therapies but no role?
@tobyeyre82 @BloodJournal As you correctly state, Toby, a well defined series examined with characteristic rigour & accuracy by the BCCC team. However, it is not and should not be read as, a randomised , prospective trial which, though hard to achieve, should remain the gold standard for practice change.
@tobyeyre82 As you correctly state, Toby, a well defined series examined with characteristic rigour & accuracy by the BCCC team. However, it is not and must not be read as, a randomised prospective trial which, though hard to achieve, should remain the gold standard for practice change.
@gilles_salles I enjoyed your article but the problem with CAR T series is most report data from reinfusion and not from harvest.The UK data set you reference has this data. I think all series should try and do this. Without ‘intention to treat’ data, how will we compare to bi- specific data ?
I am just emerging from a nasty bout of probable COVID-19 , my best advice for people to look after themselves and family is to buy a portable pulse oximeter ( < £50 online ) . COVID hypoxia is insidious -to be safe every home should have one along with a thermometer !
@tobyeyre82@NCRI_partners In fairness , we should add in the R CHOEP14 data from the GLA and Nordic groups to this comparison, I do not have it to hand but perhaps somebody could add ?