$ABVX Scorpion called Abivax a fraud. To believe that requires the reader to completely dismiss the very large clinical dataset and/or believe this is the greatest conspiracy in the history of medicine by an order of magnitude. Show the falsified records. Show the cancer excess at the dose you’re attacking. Explain why blinded readers saw healthier colons on both scopes and biopsies. The evidence Scorpion made public falls well short of its headline, and they themselves tell you that they've already covered their short position by the time you read through the report. https://t.co/1v2442xxXd
Start with 50 mg dose.
In June, we estimated 0.59 cancers per 100 patient-years at 50 mg, excluding non-melanoma skin cancer. We kept the doses separate because 50 mg was the dose under scrutiny. Abivax’s July deck put the updated number at 0.64 across 944 patient-years at 50 mg, within its historical ulcerative colitis range of 0.30–0.70. Non-melanoma skin cancer also came in at 0.64, below the company’s 0.70–1.40 benchmark. Those are the 50 mg numbers. https://t.co/6OIuirQaVy · https://t.co/xepAr25GAg
Yes, the narrower Phase 3 maintenance analysis came in higher. Four cases over 438 patient-years gave you 0.91. The added Part 2 data had two cases over 288 patient-years, or 0.69. One patient had a platelet count over 900,000 at baseline and was later diagnosed with a blood-cell cancer. The other was diagnosed with prostate cancer after roughly three months on the drug. Investigators assessed both as unrelated. Then you get to the full 50 mg dataset and the rate is 0.64. If your case depends on the smaller slice, explain why the rest of the exposure should count for less rather than ignoring it because it's inconvenient to your short report credibility. https://t.co/zNf3b6Epa9
Scorpion’s UVA experiment is a lab measurement of light absorption. The public trial protocol already disclosed animal phototoxicity for obefazimod’s main breakdown product and required sun precautions and skin monitoring. The observed 50 mg skin cancer rate across Phase 2 and 3 still came in below the historical benchmark. That comparison leaves room for a rare or delayed risk, but again no evidence. It makes the sweeping cancer claim a lot harder to sell AND physicians are already screening for skin cancer risk due to OTHER STANDARD OF CARE DRUGS THAT CAUSE CANCER IN THESE PATIENTS AND CAN CONFOUND THE SKIN CANCER FINDINGS IN EXPERIMENTAL DRUG TRIALS. https://t.co/ExeBddasfX · https://t.co/f2aPtFmTKQ · https://t.co/H48oz618HP
Now explain the biopsies.
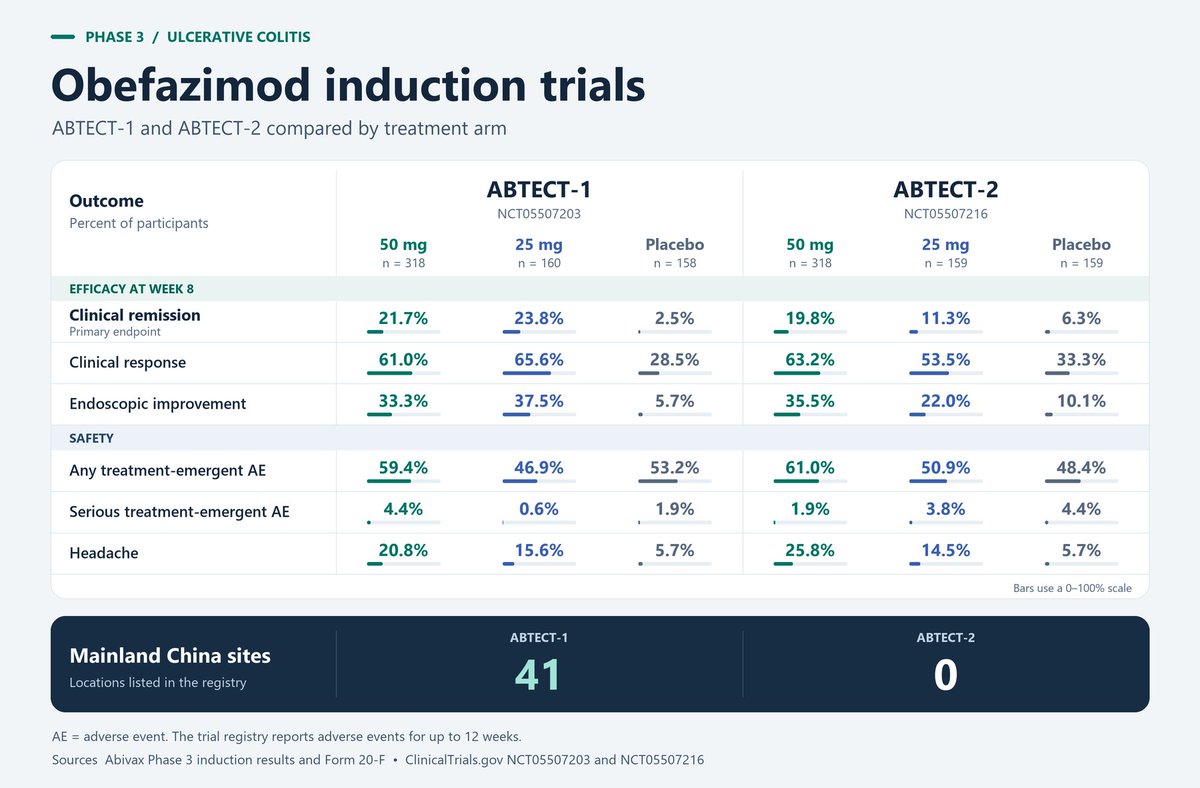
Two blinded Phase 3 trials randomized 1,275 patients. At 50 mg, eight-week remission was 21.7% vs 2.5% on placebo in one trial and 19.8% vs 6.3% in the other. The 25 mg dose missed the main endpoint in the second trial. The 50 mg dose hit it in both. https://t.co/kIH07dLP5U
Then 580 patients who had responded to obefazimod were randomized again. After 44 more weeks, 51% were in remission on either dose versus 10% after switching to placebo. A normal-looking colon on scope? 42% at 25 mg, 48% at 50 mg, 10% on placebo. Improvement confirmed by both scope and biopsy? 50%, 57%, 10%. If widespread gut-cell damage is your explanation for how this drug works, explain why the tissue looked healthier under the microscope. https://t.co/fAifEz9rzj
And the evidence goes back further. All three doses improved the main disease-activity score in the 254-patient Phase 2b trial. In the open-label follow-up, 114 of 217 were in remission at two years, with missing results counted as failures. In a separate, selected group that stepped down to 25 mg, 88 of 130 were in remission three years later. That’s a substantial record of follow-up on top of the three blinded Phase 3 trials. https://t.co/BQhLL9oKBT · https://t.co/eHSpdoGwCY · https://t.co/ItNwwpID4a
“Foreign trials” is doing a lot of work here.
The Phase 3 trials enrolled across 36 countries. Eastern Europe accounted for 38% of enrollment. In Western Europe, 50 mg remission was 19.0% vs 5.6% on placebo. In a smaller exploratory North American group, it was 8 of 62 vs 0 of 36, with scopes also favoring treatment. The protocol called for independent central readers who were blinded to treatment and visit order. If Scorpion has evidence of misconduct, show the sites, the records and what happens to the results when those sites are removed. https://t.co/o41Gr041SS · https://t.co/1Xw3hZbeFj · https://t.co/gk312wXG9J · https://t.co/Y5AbHVJ4kq
The “150-fold” experiment used zero cells. ZERO CELLS. Why are we relying on experiments that don't even include living cells when we have thousands of patient years worth of safety data?
Scorpion measured about one-fifth of the nominal drug concentration in a cell-free reconstruction, then applied that result to cell data from 2015 to get the 150-fold headline. That raises a question about an old assay. The DDT comparison is based on fat solubility. In people given 50 mg, the parent drug’s plasma half-life was about one hour and its main breakdown product’s was about four days. If the claim is dangerous accumulation in human tissue, show the tissue exposure. https://t.co/KsvAQXFjsx · https://t.co/QiX8CuY07S · https://t.co/Z2o9fNgv5x
And the supposedly fictitious biology was measured in patients. Both doses raised miR-124 in blood and colon tissue versus placebo in Phase 3, following the same finding in Phase 2. The Phase 3 analysis included 673 paired sigmoid biopsies, alongside paired rectal biopsies and blood samples. Scorpion can question the old binding assay. It still has to deal with the separate structural work and the biological change measured in actual patients. https://t.co/5Hn6GighhG · https://t.co/tDramY7NsK · https://t.co/Bco1bipbNy · https://t.co/TpPQofWk6T
The cancer cases deserved a serious look in June. We did the math then, and the expanded 50 mg data landed right within our estimates of background cancer rates in ulcerative colitis patients. Scorpion has a set of lab hypotheses and a fraud headline and completely ignores the fact the drug has show ZERO EVIDENCE OF ANYTHING THEY CLAIM IN THOUSANDS OF HUMAN BEINGS AND THEREFORE IS MOST LIKELY COMPLETELY WRONG.
Abivax has two positive 50 mg induction trials, a positive randomized maintenance trial at both doses, and biopsies that show the colon getting healthier. If you want to overturn that record, bring CLINICAL EVIDENCE that can explain it.
$ABVX As a follow-up to a few posts that I saw regarding the perceived elevated rates of NMSC and malignancies in the 50 mg arm specifically in the phase 3:
A few thoughts:
1) The phase 3 50 mg dose is actually a small minority of the patient years of safety data acquired -- the much larger dataset for that dose comes from the phase 2b long-term open label follow-up, which can be reasonably pooled with the phase 3 results given the same dose and detection protocols (Note, we have seen some analyses that pool 25 mg and 50 mg arms. We would NOT recommend doing this as it is not fair to claim that the risk of developing cancer in the 25 mg arm is known to be the same as the 50 mg arm). Pooling 50 mg phase 2b and 50 mg phase 3 data sets yields a much lower rate of events across the board. (I suspect it was just a bit of bad luck on the smaller phase 3 dataset for the 50 mg dose in isolation, see below chart for what we've been working off of after integrating these phase 2 data -- note there are some assumptions that go into this but the variability should be pretty de minimis);
2) Two ways things generally cause cancer: DNA damage from some oxidative/radiation/something else source that damages DNA or inhibits DNA repair mechanisms at their core OR substantial or highly targeted immunosuppression. Because both of these events are total exposure related, typically events accelerate over time. The phase 2 had the much longer follow-up with fewer patients whereas the phase 3 had more patients followed up for less time. The phase 2 had a very low number of events, and the phase 3 50mg dose was the only arm that had an elevated set. A priori, if the drug was a carcinogen, we would have expected the opposite: that the phase 2 would have a higher incidence/100 PY than the phase 3 given the individual patient exposures on a cumulative basis to such carcinogens are much higher in the phase 2 than the phase 3 in addition to the idea that there is a delay between when the carcinogen can cause the malignancy to when it can be detected (and T=0 is always the first instance in which that timer could start). Also, if the drug was as immunosuppressive as would be needed to cause cancer, you would expect to see a boatload of opportunistic infection before you'd see the cancer signal -- we see none.;
3) Pre-clinical testing confirmed that the drug is actually an anti-proliferative -- we would have expected the drug to be protective against tumor growth, not stimulating it;
4) No consistency or clustering for any cancer type at any time point;
5) NMSC carries a much different (lower) risk profile than other types of malignancies since they are caught very easily and have a low rate of metastases, and are seen at a massively disproportionately high case numbers relative to other types of malignancies (also included in the bottom table following pooling of the 50 mg arm), so FDA is less concerned about it than non-NMSC;
6) To warrant a black box, the FDA usually requires, at a minimum, consistency of preclinical and/or striking clinical datapoints such that careful consideration must be made to determine if the benefit/risk profile inverts in a subset of all patients that may receive the drug. In this case, we not only have completely disparate and conflicting datapoints, but we even have one data point relating to the MoA and pre-clinical data findings that suggest the drug should have the opposite effect. In addition, black box decisions are not made in isolation. They are heavily debated back and forth between the company, internally, require a lot of internal consensus on establishing causal link, and are not made in a vacuum to unmet need and efficacy;
7) UC patients have an elevated rate of inflammation (by definition) and, in turn, elevated rates of cancer compared to healthy individuals (~+.5 events/100PY vs non-UC). Obefazimod is now a proven highly effective therapy that leads to robust endoscopic remissions and attenuation of much of this inflammatory effect. I would hypothesize if you ran a large enough study and followed patients for long enough, you would find that there would be a cancer benefit from the drug secondary to the disease control that it would afford. The weight of this potential benefit (which makes sense given the pathophysiology) must be considered against the risk of the agent itself causing cancer (for which we have no reason to believe it actually should cause cancer).
@hannibalspeaks If those were the original dupi studies, completely different era of recruited patient populations.
Lebri probably functionally the same as Dupi, but Dupi has the cleanest signal because they recruited essentially all bio-naives.
I'm going to now take the other side of this: I think this report has been publicly ripped to shreds to a degree $ABVX doesn't actually need to issue a response at this point. BioX did it on their own.
The Scorpion report on $ABVX has an odd shape:
Lots of angles, none decisive —
lipophilic "carcinogen", UV phototoxicity, monkey tox, a retracted MoA paper, China sites, adjudication.
One by one, much of it is thin. High logP is a PK question, not proof of carcinogenicity. The ICH S10 UV threshold triggers more testing, not a verdict. Target organs in high-dose tox are routine. Approval rests on RCTs, not on a mechanism paper.
For the thesis to hold, the drug would have to be toxic, the trials manipulated and the effect weak, all at once, with the CRO, auditors, DSMB and regulators all missing it — That is very unlikely.
Compare the Madrigal whistleblower suit: one insider (ex-head of clinical development), one consistent story about one issue, liver safety data.
This reads like a thin core padded out to look heavier. Abivax still owes a detailed rebuttal.
Disclosure: long $ABVX
Abivax's short report from Scorpion Capital just hit a credibility problem over apparent AI drafting errors. Here's what you need to know.
On November 20, 2026, Scorpion Capital (@ScorpionFund, run by Kir Kahlon) published a short report on Abivax ($ABVX). It disclosed a short position and alleged that independent lab testing shows Abivax's drug obefazimod is toxic. Abivax stock fell about 9% to $73.20.
On November 22, biotech investor Adam Yusim posted a slide from the report. A footnote reads: "Source: logP values are calculated; standardize to one source (e.g., PubChem XLogP3) before publication." That is an instruction, not a citation. Critics say it looks like leftover note text from an AI-assisted draft that was never cleaned up before publishing.
Then Adam May posted that Scorpion and Kahlon had started deleting some of their posts on $ABVX. His post drew about 13.7K views. Others replied that screenshots already exist. May also said the work on the drug had circulated among institutional investors well before the first Phase 3 results over a year ago. He pointed out that the report claimed 11 months of diligence and called itself "our most intensive research to date." He added that the report contains many self-contradictions.
The report's substance is also being questioned. One trader noted its angles include a lipophilic "carcinogen" claim, UV phototoxicity, monkey toxicology, a retracted mechanism-of-action paper, China trial sites and adjudication. He said that, taken one by one, much of it is thin, and that a high logP is a pharmacokinetics question, not proof of carcinogenicity. A long-holder said he respects Kahlon's past shorts, such as $DNA, but finds this report less compelling.
Abivax says the report contains numerous factually inaccurate and misleading statements, assumptions and conclusions. It says some rest on studies Scorpion commissioned and funded. The company reaffirmed confidence in its Phase 3 ABTECT results and its planned year-end filing.
Another poster says a "part 2" of the Scorpion report is coming later today.
Key numbers:
- Report published: November 20, 2026
- ABVX share price: $73.20, down 9.24%
- Scorpion's claimed diligence: 11 months
- Phase 3 ABTECT 44-week maintenance results: positive, announced June 2026
- Planned filing: year-end
Abivax has disputed the report, and the short seller's own footnote is now the story.
$ABVX @ScorpionFund I'll just leave this last thought as I prepare to make dinner and open wine:
They claim ex-US sites, mainly China-derived data, is highly unreliable and can be manipulated, and that calls into question the efficacy of the drug.
So how do you explain why ABTECT-2 looked fantastic too? Zero China sites.
I'm pretty sure they pooled the efficacy data and forgot to look at the individual trials independently before making that claim. Whoops!
ABTECT-1 (NCT05507203) lists 41 mainland China sites, including Peking University First Hospital in Beijing and Ruijin Hospital in Shanghai. (https://t.co/8wFBx6gECP)
ABTECT-2 (NCT05507216) lists zero mainland China sites. (https://t.co/EqWxJZoMq3)
@JackMan716490@ScorpionFund From the $ABVX "flash crash" on 6/24/2026. One man's wise words are another man's observation on how the stock might react to even the mention of a short report, regardless of the merits within.
Recurring very right-tailed income is the hardest. We've been in a bull market for years, compounding by itself passively shifts you up the curve and very hard to lose wealth at a certain point unless you are reckless as the system starts to give you more and more optionality the more wealth you have.
To have high recurring income implies both high replacement cost and/or strong competitive moat.
Zero professional biotech investors I’ve talked to are worried about this (they’re all either pissed off at Scorpion, annoyed, buying more [and/or selling things to buy], or just brushing it off so far from my convos), so I’m not sure why a statement like management issued would move their needle. Because they can do the independent work to know who is right already. What specialist sells at $75 if you think the price has been artificially lowered by an article that is easily refutable, regardless of how management responds? I’d venture none should, fundamentally.
Retail generally relies more on ppl telling them what is right rather than doing the work themselves to validate it. If you don’t even know what PK is, or how to validate trial sites used for each study, or do risk adjustments for underlying cancer incidence rates in the IBD population they tested, then it’s harder to dismiss out of hand their claims. That’s why short sellers typically target retail-heavy stocks, as it gives them the perception of analytical advantage.
$ABVX investor base is a weird mix of a lot of specialist long-biased investors, a lot of retail, and pod shorts (not on fundamentals, but on “dead money” until CD if the perception is no near-term M&A). Also, we don’t know if Pharma would rather have a response or not, and only mngmt would know the answer to that.
If an investor base is mostly specialist investors, it makes sense not to respond. If it’s retail, it does. This investor base is both, so I think the decision to respond makes sense because the former group is unlikely to be meaningfully impacted since they’re already at the conclusion it’s BS and now idiosyncratically cheaper and the latter group may benefit from the formal refutation from $ABVX given they could interpret no response as admission of guilt.
Thats my take on this.
Also, legitimately WTF are you talking about with this "ex-North America" enrollment bear thesis for $ABVX? Did you even try a 30 second prompt in an LLM during your supposed 11 months of "research" here?
This point doesn't even stand to very basic scrutiny. your bear point is that "only" ~10% of $ABVX patients were enrolled in North America...So? Seriously about 2 minutes with an LLM could tell you this is NOT an outlier at all.
1⃣LUCENT-1 P3 study of mirikizumab in UC ➡️ ~13% North American enrollment
2⃣LUCENT-2 P3 study of mirikizumab in UC ➡️~13% North American Enrollment
3⃣ELEVATE-UC P3 study of etrasimod in UC ➡️~9% North American Enrollment
4⃣QUASAR IS-2 P3 study of guselkumab in UC ➡️5% North American Enrollment (after the P2b study IS-1 ALSO had 5% North American patient enrollment.
All of these are **FDA approved** therapies for UC today...This COMPLETELY debunks a hinge point of your entire bear case about there being something odd about $ABVX having 10% of patients enrolled from North America.
I am being completely serious here and I want your response. DID YOU EVEN CHECK WHAT THE "NORMAL" RATES OF NORTH AMERICAN TRIAL SITE ENROLLMENT WERE IN ULCERATIVE COLITIS BEFORE YOU MADE THIS A LITERAL HINGE POINT OF YOUR BEAR THESIS FOR $ABVX?
This is truly *laughably* poor work. Readily available PoC shows FDA approval in UC on datasets not only with NA enrollment rates ~around $ABVX's, but with even *lower* rates than $ABVX has! The Guselkumab (FDA approved as Tremfya) trial had literally HALF the percentage of North American patient enrollment has $ABVX! HALF!!!
So again, I ask you...did you even bother to check into this before basing a huge chunk of your thesis on this point? Because it doesn't stand up to 30 *seconds* of midwit LLM diligence.
Here's a source for you too so that you can do the numbers yourself if you want. https://t.co/uA9dCRJvmo
This Tremfya P3 (IS-2) had 17 patients on drug from US, and 5 from Canada. 11 patients on placebo from US and 2 from Canada. 17+5+11+2 = 35. 35/701 total patients = 4.99%. HALF the percentage of NA patient enrollment from this P3 study (that led to an FDA approved drug) as $ABVX's ~10% rate. Run the numbers on the P2b from IS1 in the same link - it's *also* 5% NA enrollment...Hello???
You're claiming that $ABVX is in trouble because of supposedly "low" NA enrollment rates...while the readily available proof of concept shows the rate can be HALF of what $ABVX has and *still* lead to approval. And this is supposedly one of your key findings you spent 11 months on? Debunking this didn't take me 11 minutes.
Awful dude - absolutely piss poor.