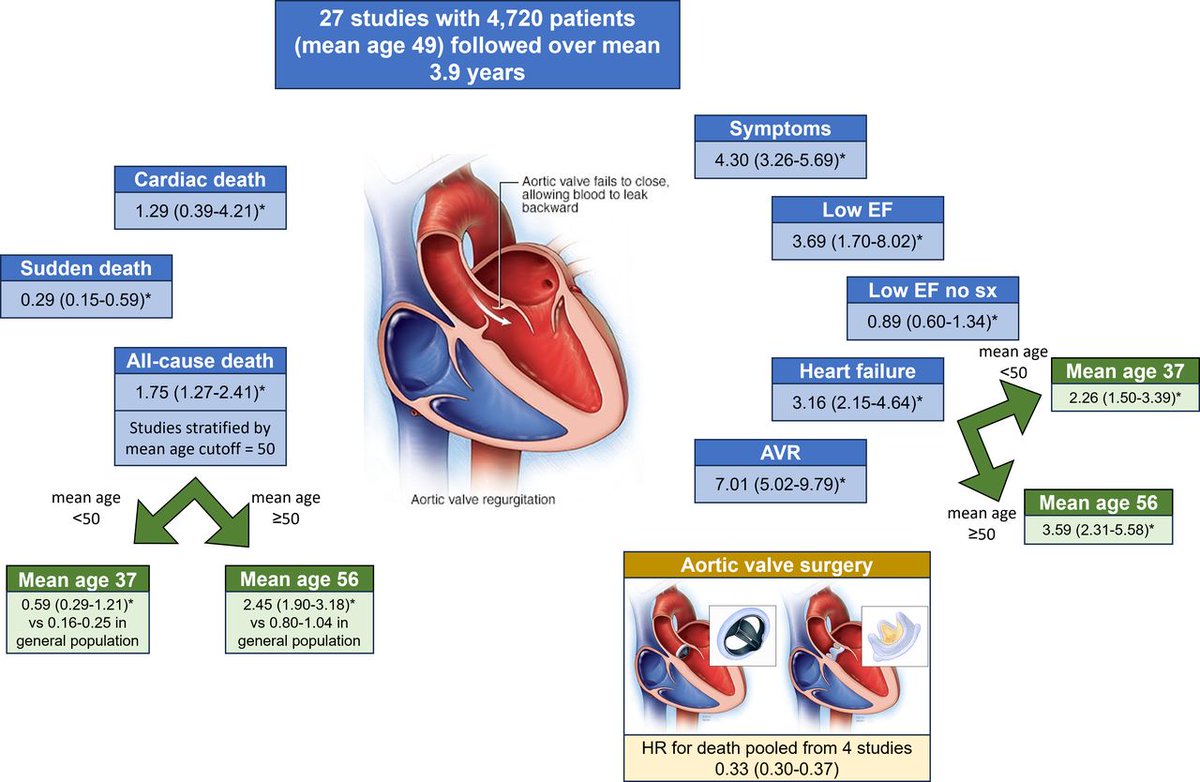
Natural history of asymptomatic moderate or severe aortic regurgitation: a systematic review and meta-analysis
Please read the article and enjoy an in-depth interview between @jhfrudd and the first author, Dr Jwan Naser from The Mayo Clinic in Rochester, Minnesota, USA
Paper: https://t.co/fxWs0bkEiv
Interview: https://t.co/ZGhyrExOAf
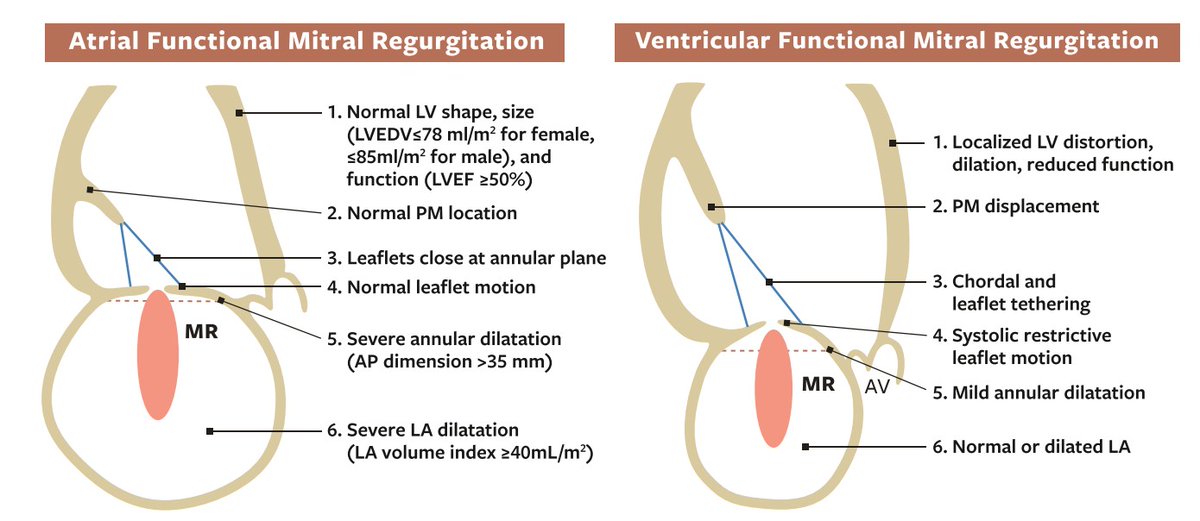
New open access meta-analysis: Sex differences in Primary MR https://t.co/6WEeTFVTs2 ⬆️mortality attributable to advanced disease (delayed referral), nonindexed cutoffs (including EROA?) may systematically disadvantage women. @JACCJournals@ACCinTouch@escardio@DrMarthaGulati@PPibarot
Presented at #ACC26:
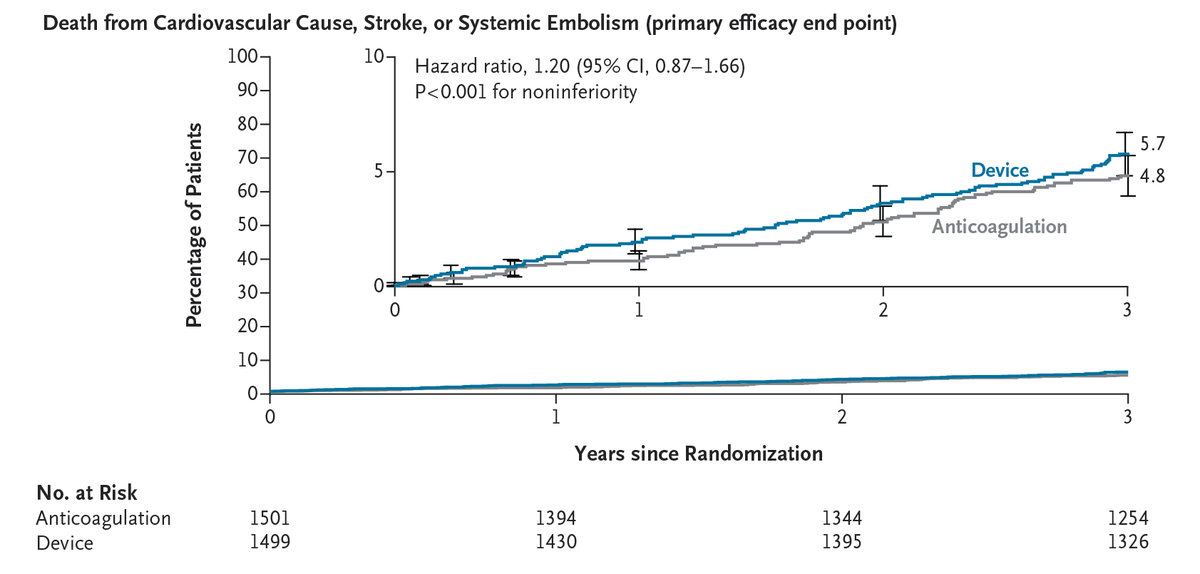
In patients with atrial fibrillation, left atrial appendage closure was noninferior to NOACs in an analysis of death from cardiovascular causes, stroke, or systemic embolism and was superior for non–procedure-related bleeding. Full CHAMPION-AF trial results: https://t.co/5Uv4N1HXXn
Editorial: Left Atrial Appendage Closure — Should Recommendations Be Expanded? https://t.co/afTN59ySIA
@ACCinTouch
#acc26 Six reasons why CHAMPION AF should not change oral anticoagulation for AF
I will have a formal post up on @theheartorg but here is a short summary
1) Stroke and Ischemic Stroke went the wrong way.
All S -> 33 vs 50 [HR 1.46 95% CI, 0.94-2.27)]
IS -> 27 vs 45; [HR = 1.61; 95% CI, 1.00-2.59)]
Look at those upper-bounds.
2) NI would not have been met for efficacy had they used a margin with both rate ratio and risk difference, which is standard practice.
The margin of 4.8% is based on event rates at 12%, which is 1.4 in relative terms (40% higher). But when event rates come in lower, as they did: 4.8% vs 5.7%, the 4.8% margin is too lenient.
The 0.9% higher rate of the primary endpoint has a 95% CI of (-0.8-2.6%), so 2.6% is less than the margin of 4.8%. Now do it with relative risk.
It's in table 2. The relative risk is 1.20. The 95% confidence intervals were 0.87-1.66. Note that 1.66> 1.40 so LAAC is not noninferior based on rate ratio margins
3) The primary safety endpoint is flawed because it excludes periprocedural bleeding and uses nonmajor bleeds, such as gum bleeds and bruising. It's open label trial so who which group will complain of more nonmajor bleeding?
4) When counting all events, Watchman barely reduced major bleeds. Also in the main results table is that major bleeds were 83 vs 87 (5.5% vs 5.8%; HR 0.92 95% CI 0.68-1.24)
5) Net Clinical Benefit was also flawed because they used nonprocedural bleeding and nonmajor bleeds.
A normal patient would simply say, there were 17 more strokes and only 4 less bleeds. Hardly a good trade.
6) Bayes: trials don't give answers, they update priors. For Watchman, you have PREVAIL failing against warfarin, CLOSURE AF clearly failing against best med Rx (mostly DOACs) so priors are pessimistic. To go from pessimistic priors to enthusiastic posteriors you'd need hugely positive data. CHAMPION is not that.
Don't believe the stories that CLOSURE failed due to them using other LAAC devices. In the AMULET IDE trial, Watchman and Amulet were similar. Also, if you believe that German operators are worse than US authors, you need to travel more.
Conclusion: Oral anticoagulation for AF is one of the most evidence-based practices in all of medicine. To upend that would take much stronger data.
Don't be bamboozled by this trial, which was designed to be positive before the first patient was enrolled.
#ACC2026
JACC just published 6yr outcomes from the Evolut Low Risk Trial w/additional 7yr follow-up.
1° endpoint (death or disabling stroke): no difference through 6 years.
Imp finding: A divergence in reintervention appears beyond year five.
@JACCJournals
https://t.co/OE0g4ar29f