Mistral Castellanos, MD
Hematology | Bone Marrow Transplantation 🇲🇽
Associate Professor of Bone Marrow Transplantation at @incanMX
@draMistralCM · @SNIIMX
4️⃣NIÑOS
📍9 meses-4 años: ferritina ≤20 ng/mL (en lugar de ≤12)
📍>4 años hasta adolescencia: ≤20
📍Adolescentes no menstruantes: ≤30
⚠️Aplica sin inflamación; con inflamación puede requerirse un umbral mayor
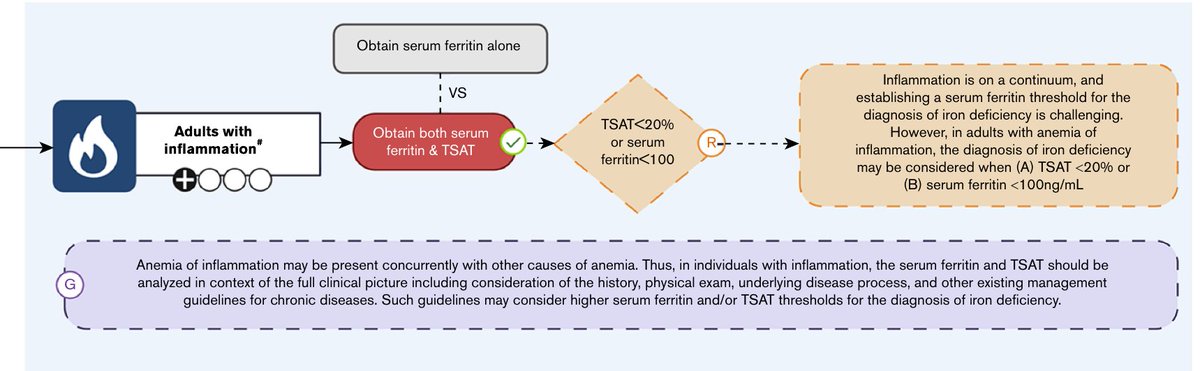
3️⃣INFLAMACIÓN (ERC, IC, cáncer, EII, reumatológicas)
✅Pedir ferritina + TSAT, no solo ferritina
💡Considerar deficiencia si TSAT <20% o ferritina <100 ng/mL
⚠️TSAT en ayuno de 5-9 h (sin hierro ni multivitamínicos)
5️⃣ Fecal Microbiota Transplantation to Prevent GVHD
Abstract 0569 | Phase II randomized trial
Fecal microbiota transplantation to prevent graft-versus-host disease: Results from a phase II randomized double-blind placebo-controlled trial.
📄 Abstract 0569
🔗https://t.co/JhNB5Vji5c
📅 Sun Dec 13 | 9:30 AM CT
Why watch: A novel microbiome-based strategy to prevent severe acute GVHD after allogeneic HCT. Randomized evaluation of fecal microbiota transplantation alongside standard GVHD prophylaxis.
🩸 #ASH26 | #BMT Abstracts to Watch
My current list of key allogeneic hematopoietic cell transplantation abstracts to watch at #ASH2026 👇
A mix of potentially practice-changing GVHD prevention strategies, donor selection, conditioning, MRD, and emerging transplant platforms.
4️⃣ Pre-transplant MRD in AML after HMA + venetoclax
Abstract 716
Pre-transplant flow cytometry in AML patients undergoing allogeneic HCT after hypomethylating agent and venetoclax therapy.
📄 Abstract 716
🔗https://t.co/EMcs0iNCwv
📅 Sun Dec 13 | 4:30 PM CT
Why watch: How should pre-HCT disease burden influence transplant decisions after lower-intensity therapy?
#ASH2026 #ASH26
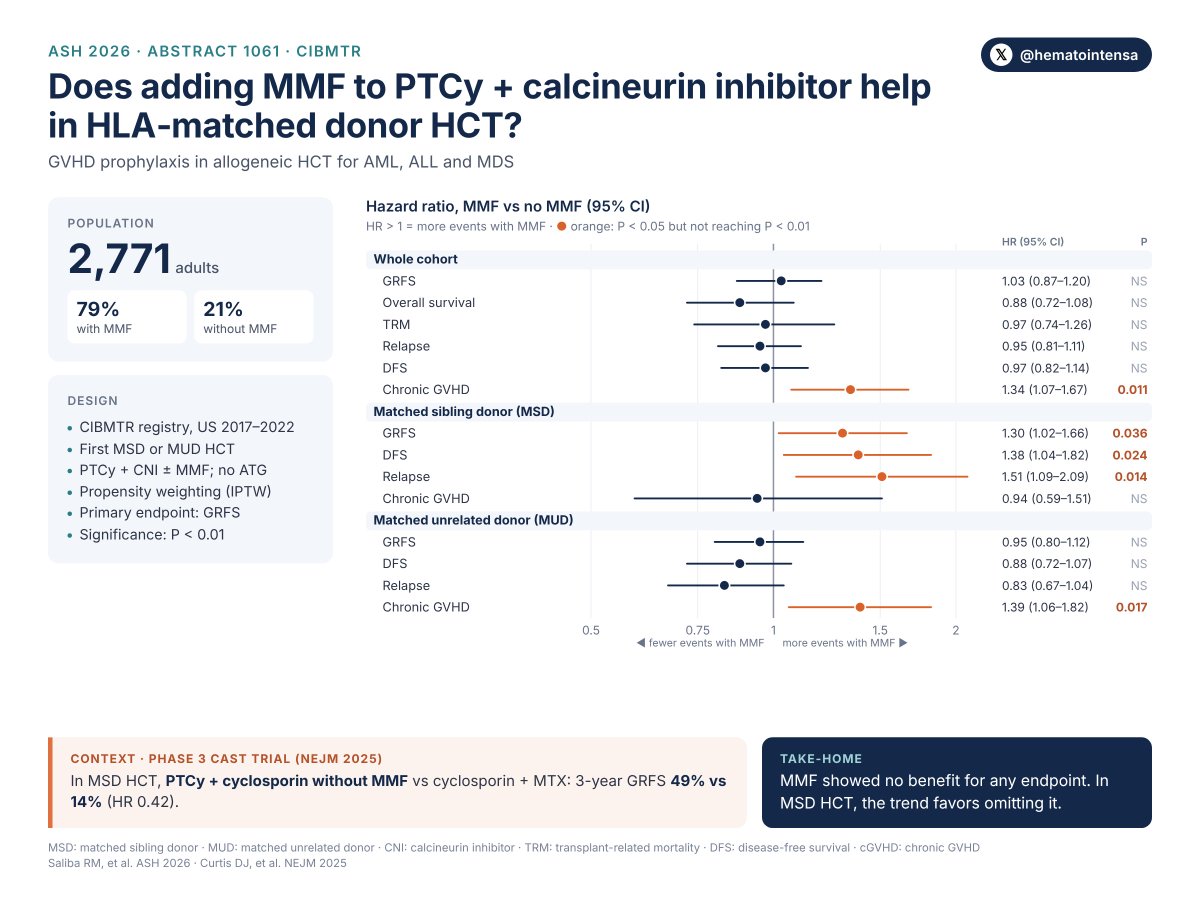
¿MMF CON PTCy + ICN EN DONADOR HLA IDÉNTICO?
➡️ASH 2026, Abstract 1061; CIBMTR n=2,771
📌Sin beneficio en GRFS, SG, MRT, recaída ni SLE
⚠️Tendencia a más EICHc con MMF
📍Donador relacionado: más recaída con MMF (NS)
💡De acuerdo c/ CAST (NEJM 2025): PTCy + CsA, sin MMF
#ASH26 #ASH2026
❓¿Qué NO cambió vs 2019?
📍Umbral para tratar: plaquetas <30 x10⁹/L
📍Esteroide corto (≤6 sem), NO prolongado
📍Prednisona o dexametasona como esteroide inicial
💡Lo nuevo: con qué se combina y el orden en segunda línea
GUÍAS ASH 2026: TROMBOCITOPENIA INMUNE EN ADULTOS 🧵
➡️Tratamiento inicial y de segunda línea
📌Ya NO se sugiere esteroide solo como 1ª línea
✅Esteroide + rituximab o + agente trombopoyético
📍Algoritmo de tratamiento
doi: 10.1182/bloodadvances.2026021269
2️⃣SEGUNDA LÍNEA (tras esteroide)
✅RECOMIENDA agente trombopoyético ➡️ única recomendación fuerte de la guía
💡Sugiere rituximab si se prefiere evitar tx crónico
📍Si no son opción: iBTK, MMF o iSYK (sin jerarquía)
⚠️Azatioprina: balance beneficio/daño menos favorable
✳️BUENAS PRÁCTICAS
📍Esplenectomía: diferir ≥1 año del dx por posible remisión; vacunas ≥2 sem antes
📍Cambiar de agente trombopoyético es válido si respuesta insuficiente, efectos adversos, mala adherencia o preferencia