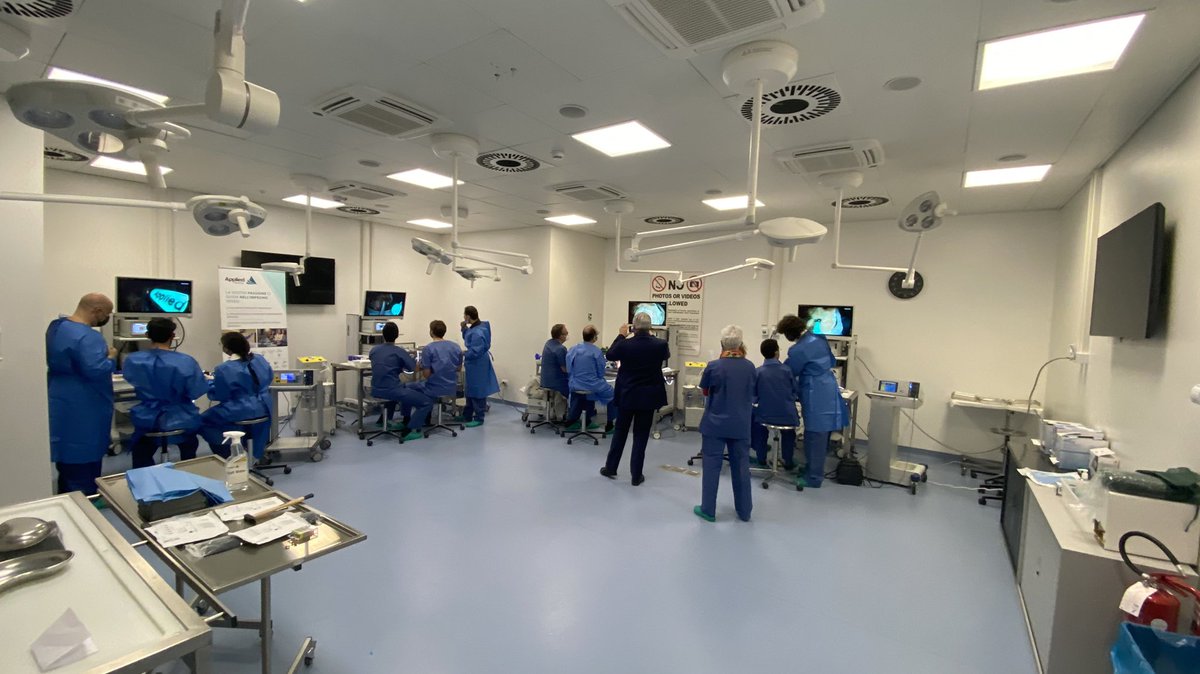
@escp_tweets is organising its first multicity (Amsterdam, London, Milano) hybrid hands-on TAMIS course at five different sites in Europe on Friday 19 November 2021.
https://t.co/ZOsNoKNZAM
Few places available in @HumanitasMilano@HumanitasCRS!!!
Deep dive into physiopathology, biomatkers, new Tx, alternative outcome measures, role of surgery, TDM, future treatment strategies in #IBD.
All of this and more will be discussed in Amsterdam Johan Cruijff ArenA in December!
@colorectaldis what an interesting subject ‼️
On #ESCP2021 we will have an entire session on difficult cases, inclusive:
💥Perianal Sepsis💥
👇Do not miss it👇
https://t.co/WHIqZj3Al3
#SoMe4Surgery#education
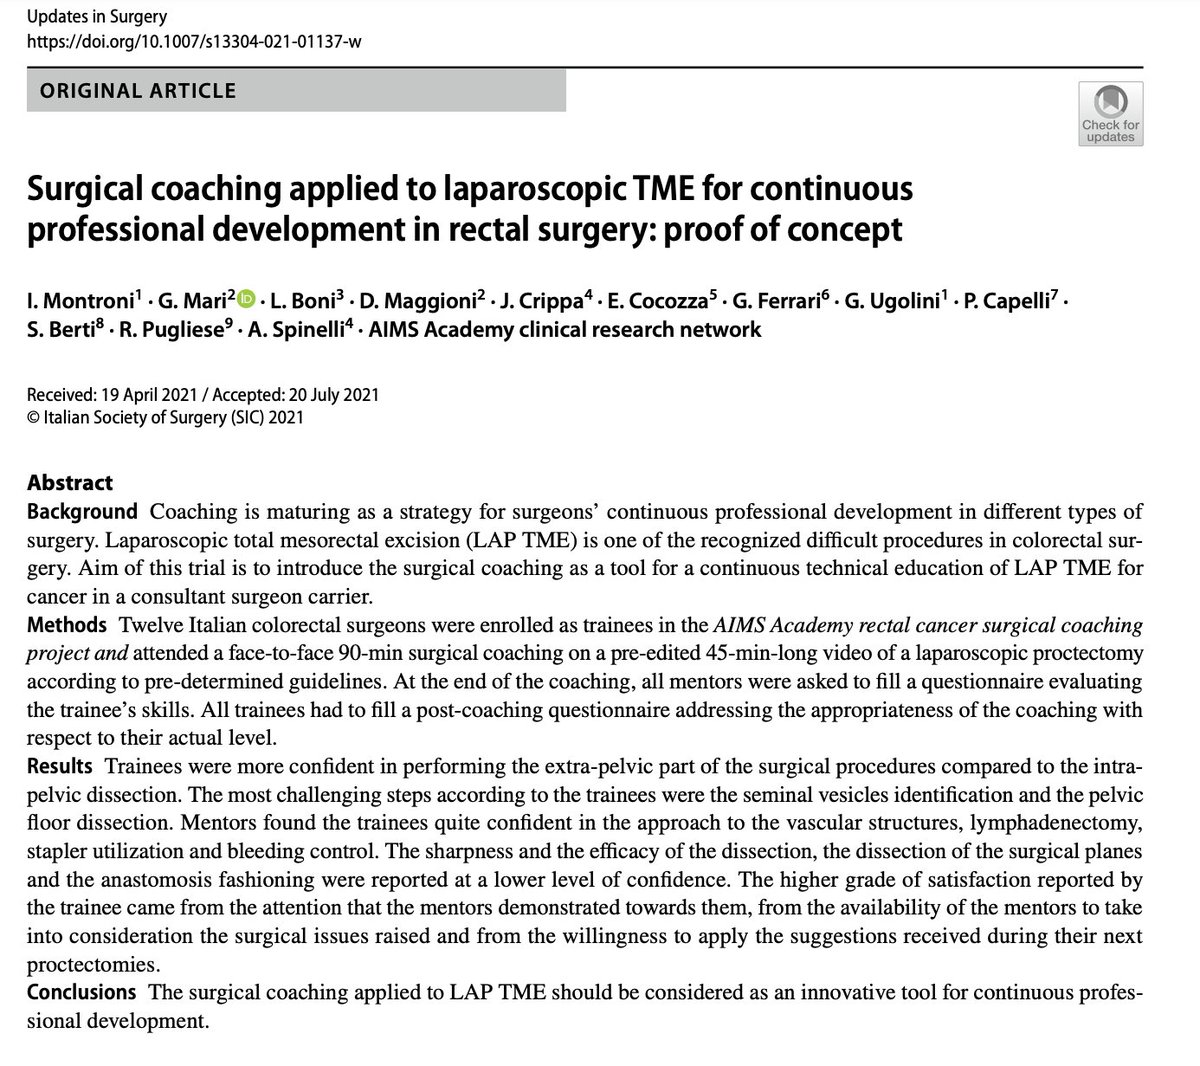
Now #available: Surgical coaching applied to laparoscopic TME for continuous
professional development in #rectal#surgery: proof of concept.
An intriguing paper by I. Montroni et al.
@3isac
https://t.co/W3TtECmX1U
Our most recent approach for rectal cancer, for those who asked:
If RESTORATIVE
-high Rectum ➡️PME ➡️DS
-mid & low R ➡️ full TME➡️TTSS
-ultra low R, too low for stapled anast. ➡️TME+partial ISR➡️Pull through
If NON RESTORATIVE bcs of
-onco ➡️APR/ELAPE
-fx ➡️TME +complete ISR
Sam, happy you like it!!
Roel and I first spoke about it 2.5 years ago in Leuven and then discussed the concept and refined the technique.
...and, yes, it’s definitely provocative, hopefully raising the discussion😜!
@RoelHompes@caterina_foppa@HumanitasCRS@CRSugergyAUMC
Differences in management and outcome for colon and rectal carcinoma with synchronous liver metastases: a population‐based cohort study https://t.co/lS8Sxm5XzN @ColorectalDis@ACPGBI
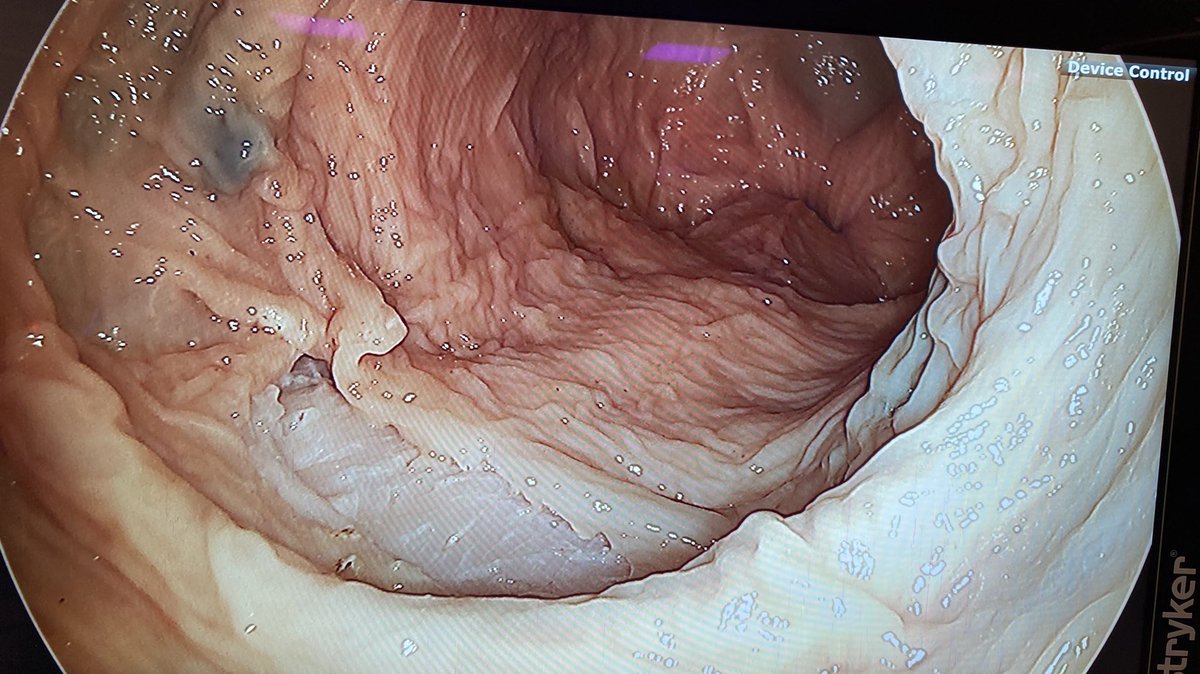
The advantages are
1-you give the pathologist the chance to assess the whole sm layer (differently from ESD)
2-even if unfavorable pathology, you have not compromised the mesorectal plane for dissection (differently from full thickness), especially important if anterior.