Liability is the foundation of a free people, without liability each individuals freedom is infinitley limited by the actions of others with no real recourse...meaning we are not free at all.
Liability is a keystone to protection for every person from others
Liability creates accountability through potentially devastating monetary damages
Liability creates proactive effort to avoid
Liability forces the ask what is reasonably knowable to ensure no harm
Liability protects against neglence
Liability protects against incompetence
Liability protects against ill intent...
Exclusion from liability removes the economic control that protects us
Exclusion trivializes real borne costs and negates accountability, is immoral, and serves to limit creation of proof, through lack of common law development
Liability exclusion should not be constitutional, but since it appears to be --
Bruesewitz v. Wyeth LLC (2011) affirming the 1986 creation of the no fault special federal court method and VICP, sidestepping normal legal processes
https://t.co/F4MwQVFin4
Sad part is, you get to look up your approved injury claims on tables and they decide to acknowledge you did or did not suffer the issue.
"Types of Compensation
The VICP provides compensation for past and future medical expenses, rehabilitation, therapies, special education expenses, equipment and placement. For pain and suffering, the VICP provides a maximum of $250,000. The VICP also provides compensation for 'lost earnings.' The VICP provides a $250,000 award for a vaccine-related death."
If it is covid and new 1 year only limit via CICP ...yet injury may build or not even be diagnosed until after the 1 year https://t.co/eDxPxdM8u9
I discovered this after 1 year myself
"On the rare chance you suffered a serious injury, or the death of a loved one, from the administration or use of a covered countermeasure, you may be eligible to file a claim for benefits.
You must file a Request for Benefits Package within one year of receiving or using the countermeasure that you believe caused the injury. You must also provide proof that a covered countermeasure was administered or used."
Being entered into VAERs with an injury should automatically create your entry and establish your claim. Even if VAERs did, CICP has acknowledged and paid almost nothing with only 26 people given an average of $4k. 1 trip to the ER for heart issues is about $10k, and that is just to stabilize you, it does nothing to solve for it...
https://t.co/yRd01p1D4p
S.3853 - A bill to amend the Public Health Service Act to end the liability shield for vaccinemanufacturers, and for other purposes
https://t.co/AhzsCcpKSx
First measure your levels.
Mine was 24 ng/Dl.
60 mg before bed made a big difference. Sleep better, feel better, etc...
More is not more with pregnenolone.
Things to consider:
1. Are you deficient or not -- range 30-250. If you levels are above 100 your not going to feel it like someone who is below 30. You mileage may vary...
2. Brand -- let's face it some brands are not delivering the best for each item. I am using Pure Encapsulations for this one. I use Swanson, Thorne, Life Extension, and others for different supps...
3. Delivery form. I hear sublingual and micronized are likely best. Im just using the regular gelatin capsules swallowed.
So does it do nothing?
Likely law of diminishing returns, the less you have before taking it, likely the more you will notice. Suggest retesting as well to see how far the needle has moved...
Note: if your pregnenolone levels are low, check you thyroid levels. You may not have enough pressure from T3 to convert cholesterol into pregnenolone.
T3 should be above 3.4 and rT3 should be below 12. My T3 was 2.8 and rT3 at 23.5.
@JuniorOmutsyba@babeotswejang No
C wastes too much of your mirror. Most 4 door cars I adjust to the rear door handle, then move the mirror out to make the handle disappear unless I move my head.
Today is my 14 year VACCINE INJURY anniversary. My vaccine injury led to eight years of illness and much loss.
Out of that darkness comes light.
I fought my way back to health with the help of allopathic, CAM, and nutritional ways. I am 95 percent better. I take no medications.
The light comes from the fact that
I researched the why of my vaccine injury. I researched adjuvants and excipients. I recognized vaccine injury in my own patients starting even before that in 2009 with an anthrax vaccine injured military man.
The light comes from speaking out against COVID mania tyranny from the beginning.
The light comes from being second author on the collaborative covid harms paper.
The light comes from starting the vaccine injury consortium last year and starting the work to get clinical trials here in US and our 8 draft clinical trials. Lots more work to actually doing them but it’s getting done.
The light comes from knowing the Covid shots are harmful from the beginning because of what they are which is a bioweapon.
The light comes from using my God given talents to fight for medical freedom, vaccine injury, truth in medicine and health, and separation of medicine and state.
The biggest LIGHT is that the darkness led me back to my lord and savior JESUS Christ.
Jesus is the way, the truth, and the life.
We live in a fallen world and Jesus did not promise ease of circumstance but he did promise to be with us.
If I can get better so can all the other vaccine injured people and I will work on this task with all my God given talents until I am called Home.
Is it methionine restriction the benefit or homocysteine conversion for FGF21?
TMG/betaine can be used to convert homocysteine back to methionine and TMG is known to increase FGF21.
Thougts on FGF21 supports via
TMG
K2
Butyrate
Etc.
@haidut calls out the cysteine issue (related to methionine/homocysteine) via b6/cbs transulfuration pathway.
The question becomes is keeping cysteine under control by converting homocysteine to methionine may be more important than pure avoidance?
@photobiogenesis@Mangan150 And that avoidance during growth fits @SamaHoole post describing our tastes buds and perhaps gives light to growth vs regulation and disease. Seems IP6 may be beneficial when unregulated growth such as cancer.
Your tongue has a receptor for meat. It detects glutamate and inosinate, the taste of a steak, a broth and an aged cheese, and it rewards you for finding them.
Your tongue has a receptor for fat. Found in 2015, named oleogustus, and it fires on dripping, marrow and cream.
Your tongue has one receptor for sweet. It was built for ripe fruit and honey, which arrived for a few weeks a year.
Your tongue has 25 receptors for bitter.
Twenty-five. One for every family of plant poison your ancestors learned to spit out, because bitter is the taste of a leaf defending itself.
Every child on earth rejects greens without being taught. That is the 25 receptors working exactly as built.
The adult learns to override them. It takes years, salt, oil and a sauce, and the child is told it is being difficult.
One receptor for meat, one for fat, 25 alarms for plants, and the whole nation has been trained to eat past the alarms and feel guilty about the two that say yes.
Your tongue filed broccoli under poison before you had a word for either.
@photobiogenesis IP6 is phtyic acid the "anti-nutrient" perhaps when you get we avoid these to allow growth and when we get older our tastes change to allow regulation--
@Mangan150 posted about IP6 and cancer:
"Complete remission of stage IV metastatic melanoma with IP6 and inositol."
You thought that Sunlight was just for vitamin D.
You are wondering, "what's all the fuss about sunlight?"
Here's a video where I step you through the data, and why you'll never see the sun the same again...
"You shall not give false testimony against your neighbor"
Cognitive dissonance
Mental gymnastics
Statistics / Per Capita
Your claimed point does not match the displayed scenario
I agree choosing to not work when able and to let others people pay your way is abhorent
Why are people on welfare?
Please list the drivers and how the program helps?
Daycare to income
Single parent vs dual parent/married family
Job availability
Wage to cost of living
Rent / housing costs
Disability
Unemployment
Worker displacement
Immigration legal and illegal
I doubt the scenario you posted is a significant proportion of the recipients
Care must be taken to not make welfare a subsidy for employers, a reward to act poorly, etc. trapping people in a damned if I do and damned if I don't scenario. Work requirement welfare may help, may also distort the system warping wages as well as costs for housing, etc. The market is imbalanced by interventions...
https://t.co/bQIaFtgpf8
@DuneC0L7D@RogerSeheult@DrJackKruse Yup listened to that this around noon and posted it to the below.
Seems there is a lot at play -- direct modulation as well as opsin sensor inputs and more...
The UV triggered nitric oxide pathway explains the latitude correlations in cardiovascular mortality that always seemed like a pure Vitamin D story. It's partly that. The rest is the nitric oxide. Two pathways, one sun. https://t.co/smyoLU1jKn
Medicare is on the verge of actuarial insolvency.
Right now, payroll taxes only cover 91% of annual Part A spending. The remaining 9% is funded from other sources, including a trust that will be out of money by 2033.
Once the trust is depleted in seven years, the federal government will have to cover these shortfalls on a “pay as you go” basis. The present value of these annual deficits—what we can think of as an unfunded liability—is a staggering $4.2 trillion.
Over the next 10 years, the number of Medicare recipients is going to increase by a million people every year, from 71.5M in 2027 to 80.5M in 2036. The program’s annual financing shortfall—which flows into the overall federal deficit—is projected to more than double, from around $600B in 2026 to $1.3T in 2035. It’s a major reason why the CBO expects the federal deficit to grow from $1.9T this year to $3.1T in a decade.
And these numbers are likely conservative. As AI creates innovative (and expensive) new therapies, it’s possible that many Medicare recipients will live meaningfully longer lives (glory to God). During each year of this actuarially-unplanned-for additional lifespan, they will consume more and more expensive care. These potential costs are largely not reflected in today’s actuarial tables, projections, or liability estimates.
To be blunt: We can’t afford any of this.
That $4.2T I mentioned above isn’t included in the national debt. It’s a liability on our country’s (metaphorical) balance sheet, but we haven’t yet borrowed the cash for it, so it’s not reflected in today’s $40T debt balance. The federal government is already incurring deficits of nearly $2T per year, with $3T per year staring at us in 10 years. The national debt at this point will be well over $60T.
All in an environment of rising interest rates and capital markets that are growing increasingly apprehensive about federal borrowing levels.
On a personal level, caring for the elderly in our lives is a blessing. On a macro-level, however, dedicating more than 5% of GDP to a federal healthcare program for the elderly and the disabled, with no trust remaining to fund costs, is a recipe for economic disaster.
So here’s why I bring all this up in regard to Democrats talking about Medicare for All:
Everything I talked about above—the unfunded liabilities, the growing annual deficits, the effect this will have on national debt, the fact that these numbers are likely understated—is based on Medicare NOT for all. All the numbers above assume Medicare will continue to cover only those above age 65 or living with a disability.
So imagine how much worse all these fiscal challenges will be when Medicare covers 100% of the population, not just 20%?
Every birth, every death, every trip to the hospital, every annual physical, every illness or ailment, every surgery, every emergency. Entirely covered by American taxpayers (and bondholders) on a pay-as-you-go basis, with zero reserves set aside to pay for it.
18% of GDP. 12% of the American workforce. All paid through the US Treasury.
People like AOC and Abdul El-Sayed will tell you this is incorrect, that the system will become more efficient once greedy capitalist insurance companies and hospital networks can no longer profiteer from the market failures of these oligopolistic industries.
At best, they are categorically wrong. At worst, they are outright lying to you.
The idea that the bureaucrats who ran USAID and the Department of Education will be able to operate one of the largest and most complex industries in our economy better than the private sector can is prima facie laughable. The notion that it would lead to superior patient outcomes is absurd.
What will happen is simple: Virtually the entire US healthcare industry will end up nationalized. Not just insurance, but every part of the value chain, from hospital networks to biotech companies to medical-device manufacturers. For all intents and purposes, there will no longer be a private-sector medical industry in America. Within a decade, nearly all of it will be owned by the government.
Here’s how it will happen (for anyone still reading, I promise, we’re almost done!):
To control costs, the government will cap increases to fee schedules, limiting what it reimburses hospitals and doctors for care. Because the market will at that point be single-payer, providers will have zero negotiating leverage—either you take what Medicare offers to pay, or you lose all your revenue.
As hospital networks lose the ability to operate profitably, they will have to divest assets. But no one is going to be willing to pay for them, since there is now only one buyer in the market (economists call this a “monopsony”), and that buyer is not incentivized to allow any profit to remain in the system. The only option will be to sell to an investment fund created and operated by the federal government.
The ripples will spread throughout every facet of the medical industry from there. The same single-payer dynamic that played out between Medicare and providers will occur with pharmaceutical companies, medical-device companies, and anyone else operating in a medical supply chain. The government becomes the sole purchaser, they squeeze margin out of their customers, their customers are no longer viable as independent going concerns, and they sell (“sell”) to the government.
Close to one-fifth of the American economy. One out of every eight jobs. All government-owned, operated, and controlled.
Every visit to the doctor starts feeling like a trip to the DMV. Any treatment deemed “non-essential” requires months, if not years, of waiting (ask your friends in Canada what that’s like next time they’re visiting the US to avoid a six-month wait for an MRI). America’s pharmaceutical companies have no profit to reinvest or sources of capital with which to fund the next generation of R&D. Only the wealthy and the politically connected are able to receive a level of care comparable to what any middle-class worker with a bronze-tier insurance plan receives today.
What does that sound like to you?
Ask yourself: Why would avowed socialists advocate so zealously for this?
Remember: The purpose of a system is what it does. And we know exactly what this system would do.
@AbdulElSayed Wow -- this is deep
Now explain how insurance works and where the money will come from
Easy to tell people I will give you "x"
Harder when you explain how much it will cost and who it will cost
🚨 It’s finally out!
The video that explains clearly what we believe is happening when infrared light hits the mitochondria.
It’s worth the whole watch!
How Infrared Light Actually Affects Your Mitochondria - Hypothesis
https://t.co/SozEskCzK0
Seemed pretty clear from 3:10-3:15 when you stated it modulates (...transferred more easily in some cases and sometimes less easily...it modulates..."
I appreciate both of your work. And I have been using a combination of natural sunlight, a red/nir panel, a party black light, a chicken red lamp, a Sperti vit D light, and blue blocking glasses.
While it hasn't managed to fix any of my problems, I at least feel like Im doing something ;)
In all seriousness, the body is modulated by external energy sources and work to uncover the how and why is important. From this we can learn what deficincy and excess causes. Since the sun is generally free, there may be some low cost habit and cultural changes that would improve everyone's health.
Please keep up the good work and I hope this gets us away from those impossible to focus under led lights we suffer from today.
I want you to think about white blood cells differently.
When you hear "plaque," most people picture cholesterol clogging a pipe. That is not what happens.
Here is what actually happens:
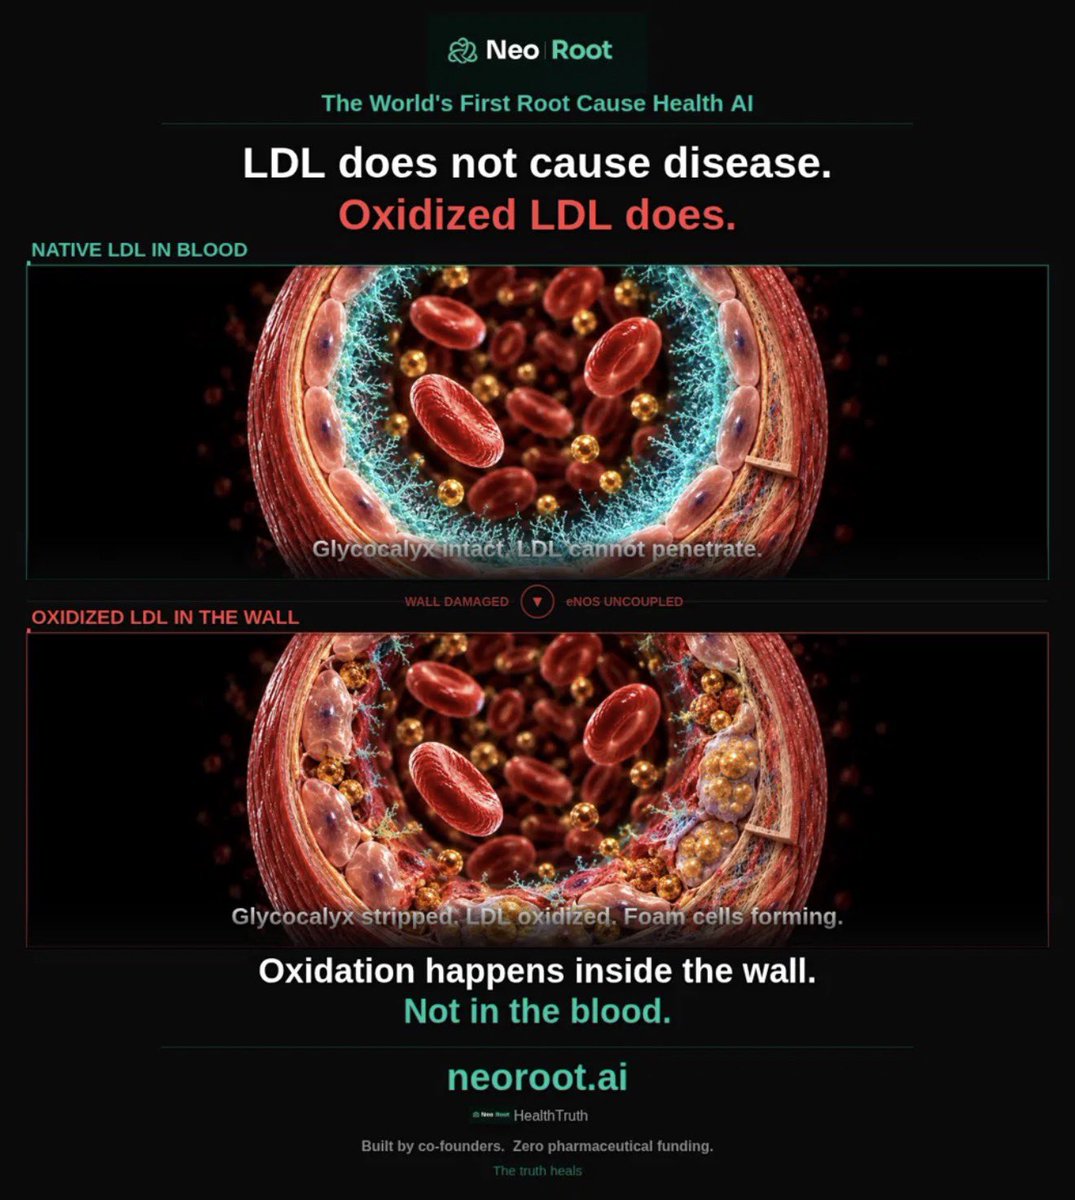
When your artery wall is damaged, LDL particles slip through and become oxidized. Your immune system detects the threat. It sends white blood cells. Monocytes cross into the wall and become macrophages. They do exactly what they are supposed to do. They engulf the oxidized LDL to clean it up.
But they cannot break it down. They swell. They become foam cells. And foam cells are the plaque.
Read that again. The immune response that is trying to save you is building the disease.
Blaming white blood cells for plaque is like blaming firefighters for fires. They are at the scene because there is a fire. The more firefighters you see, the bigger the fire. But the firefighters did not start it.
The fire is the damaged wall. Insulin resistance. Chronic inflammation. Uncoupled eNOS. A stripped glycocalyx. That is what let the LDL in. That is what oxidized it. That is what called the immune system.
Nobody asks why the fire started. They just count the trucks.
That is modern cardiology. Count the particles. Ignore the wall.
The truth heals
@Marion436842126 Tired of firetucks and emergency vehicles blocking the road?
Get ride of them!
Don't worry why they show up
Don't solve the problem they are addressing
Just know you did your part by getting rid of them so they cannot block the road....
@stringerbell99@FatEmperor
I want you to think about white blood cells differently.
When you hear "plaque," most people picture cholesterol clogging a pipe. That is not what happens.
Here is what actually happens:
When your artery wall is damaged, LDL particles slip through and become oxidized. Your immune system detects the threat. It sends white blood cells. Monocytes cross into the wall and become macrophages. They do exactly what they are supposed to do. They engulf the oxidized LDL to clean it up.
But they cannot break it down. They swell. They become foam cells. And foam cells are the plaque.
Read that again. The immune response that is trying to save you is building the disease.
Blaming white blood cells for plaque is like blaming firefighters for fires. They are at the scene because there is a fire. The more firefighters you see, the bigger the fire. But the firefighters did not start it.
The fire is the damaged wall. Insulin resistance. Chronic inflammation. Uncoupled eNOS. A stripped glycocalyx. That is what let the LDL in. That is what oxidized it. That is what called the immune system.
Nobody asks why the fire started. They just count the trucks.
That is modern cardiology. Count the particles. Ignore the wall.
The truth heals
@ketontrack Why the fear of LDL?
If we have fires do we fear the firetruck?
Seeing lots of firetrucks in a location means something.
Why LDL is collecting in plaques?
LDL is critical to life -- nerves, hormones, fat soluable vitamins and energy transport.
Interesting war -- professions vs self directed research tools, what is AI and the proper role?
Good and Bad
Professions will lock AI down to preserve a captured category of work, claiming safety and your protection, but is it or are they gatekeeping access under the guise of protection because AI is dangerous?
Advanced professions are battening down the hatches via legal battles protecting thier livelihood.
How? Both directly and by allowing liability claims to insulate from.
Meanwhile almost every other work type is being told to train AI at work daily, letting AI watch and then replicate what you do... let that sink in...your are training it to make you redundant...
What is AI?
AI is like the combination of advanced search with predicted values. Each model approximates a result based on observed data. That data and that model are not truth (correct facts) they are data points right or wrong...(I'm not going to get into correlation, causation, p values, and process understanding...)
Ask:
How can AI be any more liable than a series of internet queries and human extrapolation?
Liability then must fall on the packaging and implied use.
If the tool is sold as a replacement or implied to do the same, then they liability must follow. If it is sold as tool to help explore with the caveat it is simply a research tool like a library or internet and the end user must synthesize their understanding, then it gets murky.
Ask:
1. Would I hold the library liable for a book that has errors?
2. Would I hold the internet web page liable for an opinion?
3. Would I hold an advanced summarization software liable for taking the above and summarizing it and the predicting a likely correct answer?
Vs.
4. Would I hold a doctor liable for error?
At what point is there a reasonable expectation?
And then -- Is there a reasonable expectation of AI?
I absolutely want AI to tell me what research shows regarding medical or anything else. But I also want the links and I want to read the details. AI is a companion, not the answer. But we may see medical AI also become the answer much like selfdriving cars...
Critical distinction-- what AI was used, what was the implied use, what was stated use?
So who is as fault?
Is it the AI creator, who sold you AI as a tool to do things that you may have no background or understanding in? Did it come with certification to provide medical guidance in lieu of a medical professional?
Is it the user who accepts non-usame case certified AI summary as fact and has no background to question or understand?
Then ask -- Why would a group say they are protecting you by attempting to ban access to information?
Fear any attempt to limit access to information
But also fear AI telling us something that is not true...
Winters v. OpenAI: Pastor Sues OpenAI and Sam Altman for Medical Malpractice, Alleging ChatGPT-4o's Advice Contributed to a Near-Fatal Pulmonary Embolism
Landmark case could shape how AI is used in medicine. URL TheFocalPoints @McCulloughFund@sama@OpenAI@ChatGPT
Interesting war -- professions vs self directed research tools, what is AI and the proper role?
Good and Bad
Professions will lock AI down to preserve a captured category of work, claiming safety and your protection, but is it or are they gatekeeping access under the guise of protection because AI is dangerous?
Advanced professions are battening down the hatches via legal battles protecting thier livelihood.
How? Both directly and by allowing liability claims to insulate from.
Meanwhile almost every other work type is being told to train AI at work daily, letting AI watch and then replicate what you do... let that sink in...your are training it to make you redundant...
What is AI?
AI is like the combination of advanced search with predicted values. Each model approximates a result based on observed data. That data and that model are not truth (correct facts) they are data points right or wrong...(I'm not going to get into correlation, causation, p values, and process understanding...)
Ask:
How can AI be any more liable than a series of internet queries and human extrapolation?
Liability then must fall on the packaging and implied use.
If the tool is sold as a replacement or implied to do the same, then they liability must follow. If it is sold as tool to help explore with the caveat it is simply a research tool like a library or internet and the end user must synthesize their understanding, then it gets murky.
Ask:
1. Would I hold the library liable for a book that has errors?
2. Would I hold the internet web page liable for an opinion?
3. Would I hold an advanced summarization software liable for taking the above and summarizing it and the predicting a likely correct answer?
Vs.
4. Would I hold a doctor liable for error?
At what point is there a reasonable expectation?
And then -- Is there a reasonable expectation of AI?
I absolutely want AI to tell me what research shows regarding medical or anything else. But I also want the links and I want to read the details. AI is a companion, not the answer. But we may see medical AI also become the answer much like selfdriving cars...
Critical distinction-- what AI was used, what was the implied use, what was stated use?
So who is as fault?
Is it the AI creator, who sold you AI as a tool to do things that you may have no background or understanding in? Did it come with certification to provide medical guidance in lieu of a medical professional?
Is it the user who accepts non-usame case certified AI summary as fact and has no background to question or understand?
Then ask -- Why would a group say they are protecting you by attempting to ban access to information?
Fear any attempt to limit access to information
But also fear AI telling us something that is not true...