We find that stopping antipsychotic depots abruptly in @SchizBulletin Open is likely to produce too rapid a shift in drug levels to avoid withdrawal effects (which might provoke relapse), despite being much slower than stopping oral medication.
This is contrary to the general wisdom that depots are 'self-tapering' on stopping. 6-monthly paliperidone might be an exception.
Instead it makes more sense to taper depots to lowest dose and then switch to oral medications for a more careful taper.
Led by industrious @jamieroneill.
Link below.
Very privileged to have been nominated by @LypftResearch as their Research Hero for October 2025 for our work on the MIDILIA pilot! Thanks ever so much to all the team who helped make the project happen, both at @LeedsandYorkPFT and elsewhere in the UK!
https://t.co/T7LSLnirej
A huge thanks to everyone involved in conducting this work, including @LypftResearch, Chris Wilson, George Crowther, @markhoro, @DrSamMcLean, Michael Dixon, Muhammad Faisal, and all the staff from @ASI_lab! Apologies if there’s anyone I’ve missed!
Delighted to be able to finally share our write-up of the MIDILIA pilot in @TheBJPsych Open. Greater fluctuations in plasma concs of psychosis medication between LAI doses correlated with greater symptom changes. Read the full paper open-access here: https://t.co/neNuPsG9cp
Great to work with @markhoro@_AndersSorensen & @DavidTa23968240 on this in silico analysis of antidepressants. Dosing in smaller amounts but more often reduces fluctuations in the body and the risk of withdrawal effects. Thanks to JAD and @ElsevierConnect for publishing!
Good to see the final version of this paper in print from @jamieroneill Tapering drugs by dosing every second day risks severe withdrawal effects and is generally not wise. Better to use smaller doses e.g. liquids or compounded versions each day https://t.co/VnXO5DYB8D
Neat piece of work by @jamieroneill on why dosing antidepressants every second or third day risks severe withdrawal effects as plasma/SERT occupancy levels vary wildly. Better to give same small dose each day using liquids or other options
https://t.co/CL39blq5bZ
Clinically useful paper led by @jamieroneill looking at how to hyperbolically taper decanoate antipsychotic depots. Abrupt stopping likely not sufficiently slow enough taper for many patients, requires switching to orals https://t.co/Kdmz6A982w with @
@DavidTa23968240
Thanks to @PsychTimes for writing about our recent paper in Journal of Psychopharmacology on what clinicians should consider when increasing the dose of antipsychotics @adamjameson96 @DrSamMcLean@ChrisL8888
https://t.co/UwtXzoFsTx
Glad to have had the opportunity to talk at the conference about deprescribing to a packed room (a friend of mine was turned away at the door!) and many thoughtful and engaged questions. Thanks to @DavidTa23968240 and Robin Murray for chairing
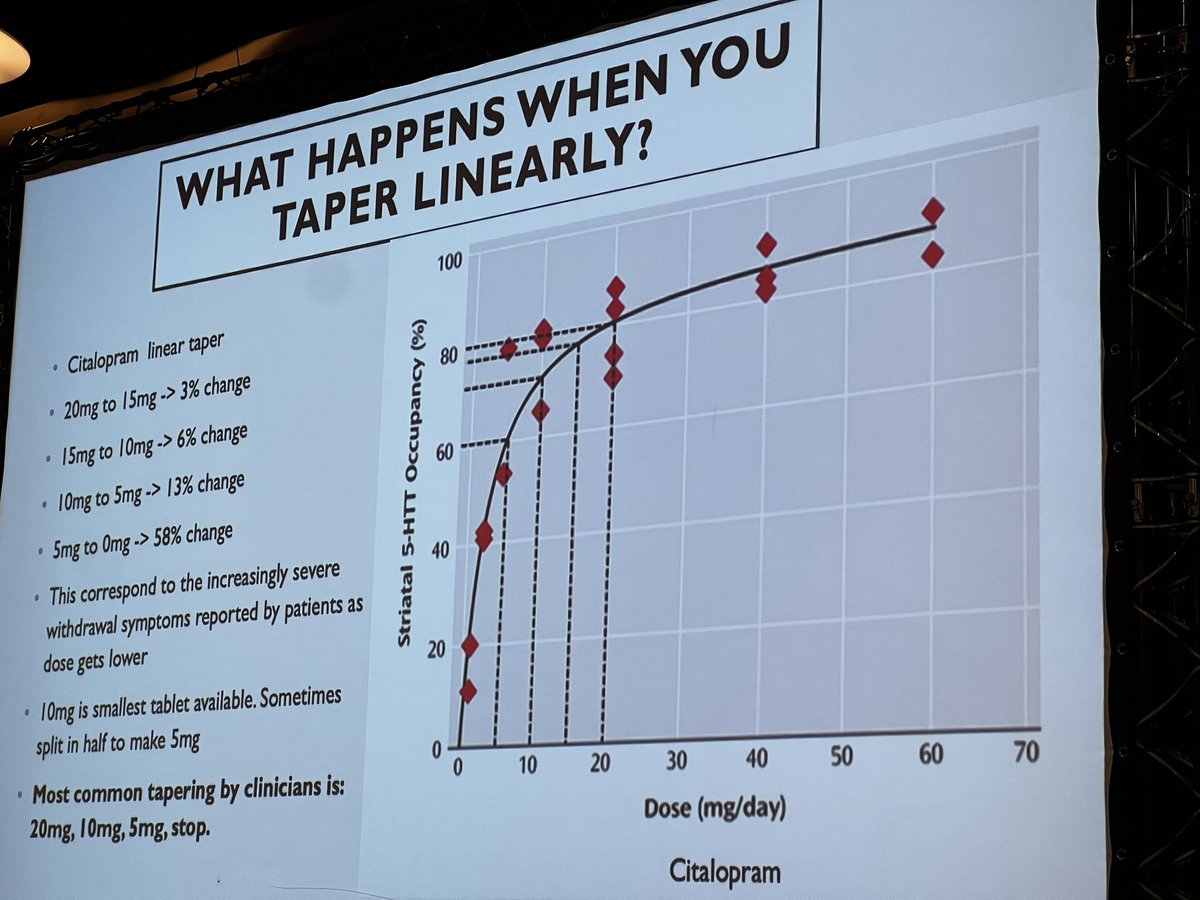
Prof Taylor from King's College London recommends that antidepressants are regularly reviewed and, if no longer necessary, tapered in a manner proportional to their current dose (so that reductions get smaller and smaller in size as the total dose gets smaller).
#RCPSychIC 2024
How to make small doses for antidepressant tapering by @markhoro. Important not to skip doses. He doesn’t think it is worth switching to fluoxetine. #RCPsychIC
New paper out in Journal of Psychopharmacology
BNF maximum doses for psychosis drugs based on safety, not efficacy. Not for use as guideline / target to achieve clinical response. Point of futility often much lower @DrSamMcLean @adamjameson96 @ChrisL8888
https://t.co/HecyriWfpT
Dosing to individual response vital, and drug monitoring / pharmacogenetics plays key role in personalising dosing. This should be used if clinical response not achieved by our recommended targets to see if either increase or switch needed @DrSamMcLean @adamjameson96 @ChrisL8888
Dear @NHSKFH, any chance the new Maudsley Deprescribing Guidelines could be added to your excellent eBook collection alongside the Maudsley Prescribing Guidelines? Lots of HCPs would be delighted to have access to this new resource.
@jamieroneill Agree. There's a brilliant paper on this that explains with crystal clarity that abruptly stopping antipsychotics produces much faster changes than you would think https://t.co/6u0qEqyIT8
@markhoro Agreed, but important to stress that recurrence rates of 40% in abrupt LAI discontinuation group at 6 months suggests that depots may not be as effective at self-tapering as they may seem…