🚨🔴⚪️ BREAKING: Arsenal agree deal to sign Ezri Konsa from Aston Villa, here we go!
Fee agreed at £50m plus add-ons and long term deal in place with English defender.
Konsa will undergo his medical in next 48h then signing in at #AFC — follows @TheAthleticFC.
PCAB achieves full, maximum acid suppression within 2 to 4 hours of the very first dose, a traditional PPI takes 3 to 5 days of continuous dosing to reach the same clinical effect.
Notes and illustration from Simplify Rx 📱
🏥🩺 Our patient had hepatitis B and was taking alcohol regularly.
🔥 A diagnosis of decompensated liver cirrhosis was made because she had facial wasting with no peripheral oedema ( Potato-on- stick appearance). No features of heart failure ( ruling out EMF).
🔥 We tapped 2 L
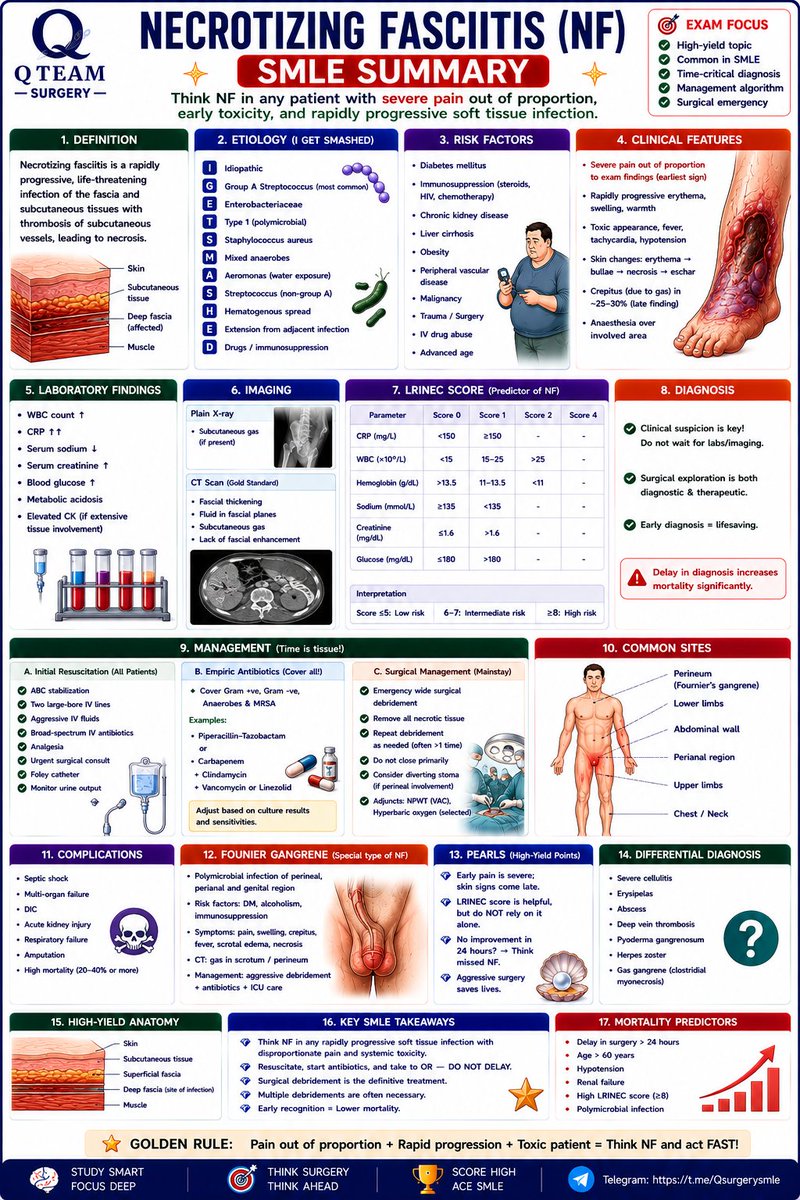
🚨 NECROTIZING FASCIITIS — SMLE SUMMARY
A life-threatening surgical emergency that requires immediate recognition and intervention 🩺
This visual summary covers:
▫️Definition and pathophysiology
▫️Common organisms and risk factors
▫️Clinical features and red flags
▫️Pain out of proportion to examination
▫️LRINEC score interpretation
▫️CT findings and diagnosis
▫️Broad-spectrum antibiotic coverage
▫️Emergency surgical debridement
▫️Complications and mortality predictors
▫️High-yield SMLE pearls and exam tips
Remember the golden rule 🔥
Severe pain + rapidly progressive soft tissue infection + systemic toxicity = Think Necrotizing Fasciitis until proven otherwise.
Early diagnosis and urgent surgical debridement save lives. Delay kills tissue and increases mortality.
Telegram: https://t.co/EPqChBhGHt
💊 DRUG CALCULATION MADE EASY 💊
Master essential drug calculation formulas with simple examples for Pharmacy, Nursing, and Medical students.
✅ Tablet Calculation
✅ Liquid Calculation
✅ Injection Calculation
✅ IV Flow Rate
✅ Drops per Minute
✅ Weight-Based Dosing
10 LAB VALUES A RHEUMATOLOGIST NEVER IGNORES
Laboratory results are not diagnoses—but some should immediately change your differential diagnosis.
Key laboratory red flags include:
🔴 Ferritin >1000 ng/mL
🔴 Low C3 + Low C4
🔴 CK >1000 IU/L
🔴 Persistent eosinophilia
🔴 Active nephritic urine sediment
🔴 Platelets <50,000/µL
🔴 Positive PR3-ANCA or MPO-ANCA
🔴 Ferritin + cytopenias
🔴 Monoclonal protein
🔴 ESR >100 mm/hr
The most important abnormal laboratory result is often the one that prompts you to ask the right question.
Remember:
✅ Laboratory values are clues, not diagnoses.
✅ Always interpret results in the clinical context.
✅ A single abnormality may be the first clue to a life-threatening rheumatologic disease.
Which laboratory abnormality has most often changed your diagnosis?
Infographic by Dr. Aravind Palraj
#Rheumatology #MedicalEducation #MedEd #ClinicalReasoning #InternalMedicine #Nephrology #Hematology #AutoimmuneDisease #FOAMed #RheumTwitter #MedTwitter #LaboratoryMedicine #Medicine #DMRheumatology #ClinicalPearls @IhabFathiSulima@docakx
💧 Edema is not a diagnosis — it’s a clinical clue.
From heart failure ❤️ to kidney disease 🩺, liver cirrhosis 🫀, and hypothyroidism 🦋, understanding why fluid accumulates is the key to finding the cause.
Master the mechanisms.
Recognize the patterns.
Treat the patient, not just the swelling.
#MedTwitter #FOAMed #MedicalEducation #InternalMedicine #Nephrology #Cardiology #ClinicalMedicine
Inflammation is not one signal.
It is a biological conversation, and each marker lets us listen to a different voice.
By the way, this infographic is the perfect companion to my previous one on CRP, ESR and procalcitonin.