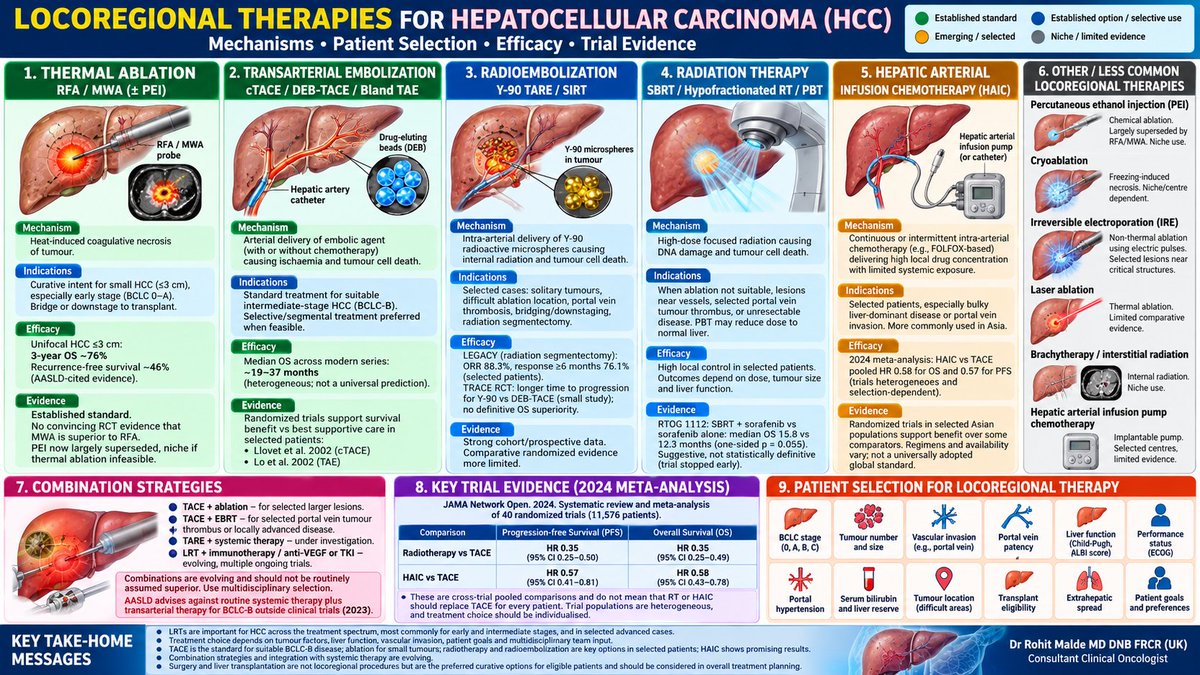
Locoregional Therapies in HCC
How to choose ?
Which Shop to go to ?
Know thy weapons and its use
Individualise
MDT
Patient and Tumour factors
Mutually narrow down
🚨 ESMO 2026 | TOP 10 GYNAE ONCOLOGY TRIALS TO WATCH!
From chemotherapy-free immunotherapy to next-generation ADCs, #ESMO26 could reshape gynaecological oncology!
🔥 My Top 10, by cancer subtype:
🔴 ENDOMETRIAL CANCER
TroFuse-005 (LBA11) | Sacituzumab tirumotecan vs physician’s choice in recurrent/advanced disease.
KEYNOTE-C93 (LBA12) | Pembrolizumab alone vs chemotherapy in 1L dMMR disease. Can we omit chemotherapy?
NRG-GY020 (1239O) | Adjuvant radiotherapy ± pembrolizumab in early-stage dMMR disease.
Sacituzumab tirumotecan + pembrolizumab (1259P) | ADC + immunotherapy in post-platinum pMMR disease.
🔵 OVARIAN CANCER
BEHOLD-1 (LBA41) | Mocertatug rezetecan, a B7-H4 ADC, in platinum-resistant disease.
REJOICE-Ovarian02 (1247RO) | Raludotatug deruxtecan + bevacizumab in platinum-resistant disease.
REJOICE-Ovarian01 (1331P) | Updated efficacy and safety of raludotatug deruxtecan.
BEHOLD-1 biomarker analysis (1248RO) | Which biomarkers predict response to B7-H4 ADC therapy?
🟣 CERVICAL CANCER
CALLA (LBA45) | Tisotumab vedotin + pembrolizumab vs chemotherapy in recurrent/metastatic disease.
EMPOWER-Cervical 1 (1250O) | Cemiplimab-based strategies and long-term outcomes.
⭐ My top 3 to watch:
KEYNOTE-C93 | TroFuse-005 | BEHOLD-1
Which trial has the greatest potential to change your practice?
@ESMO_open@myesmo@ASCO@oncoalert
#ESMO26 #GynOnc #Oncology
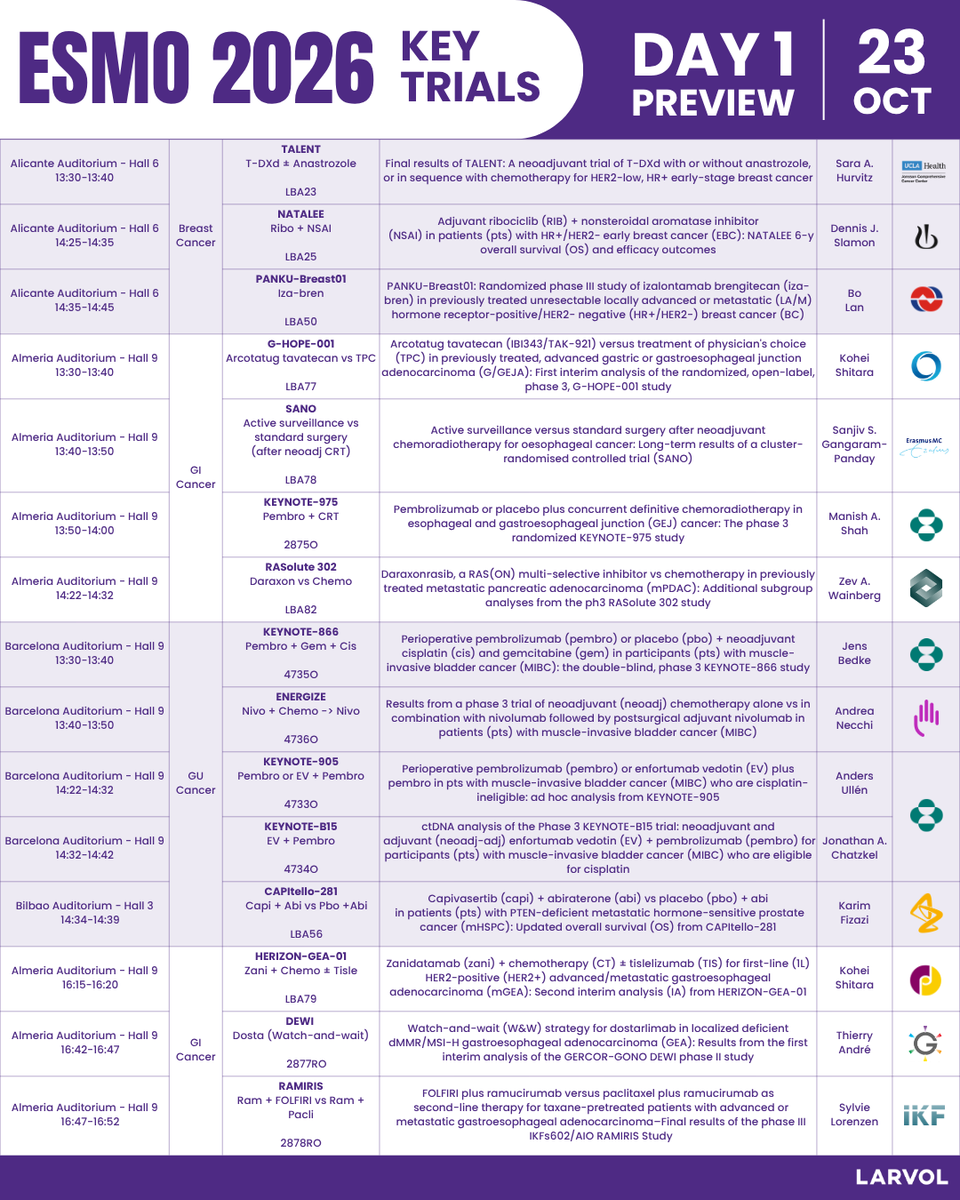
🚨 ESMO 2026 | TOP 10 GI CANCER TRIALS TO WATCH!
From CLDN18.2 ADCs and PD-1/VEGF bispecifics to chemotherapy-free strategies, major GI oncology data are coming at #ESMO26!
🔥 My Top 10 Trials
🔴 GASTRIC / GEJ CANCER
CLARITY-Gastric 01 (LBA7) | CLDN18.2 ADC vs investigator’s choice
G-HOPE-001 (LBA77) | Novel CLDN18.2 ADC
HERIZON-GEA-01 (LBA79) | Zanidatamab + chemotherapy ± tislelizumab
GERCOR-GONO DEWI | Dostarlimab and nonoperative management in dMMR disease
LOMAC (LBA81) | 4 vs 6 months of adjuvant CAPOX
KC-WISE (LBA80) | Anbenitamab + chemotherapy
RAMIRIS | FOLFIRI + ramucirumab vs paclitaxel + ramucirumab
FORTITUDE-101/102 | FGFR2-targeted therapy and biomarker analysis
🟠 BILIARY TRACT CANCER
HARMONi-GI1 (LBA8) | Ivonescimab + chemotherapy vs durvalumab + chemotherapy
🟣 ESOPHAGEAL / GEJ CANCER
KEYNOTE-975 (2875O) | Pembrolizumab + definitive chemoradiotherapy
⭐ Two Presidential trials to watch closely: CLARITY-Gastric 01 and HARMONi-GI1.
Which GI trial will have the greatest clinical impact?
@myesmo@ESMO_open@ASCO@oncoalert
#ESMO26 #GICancer #Oncology
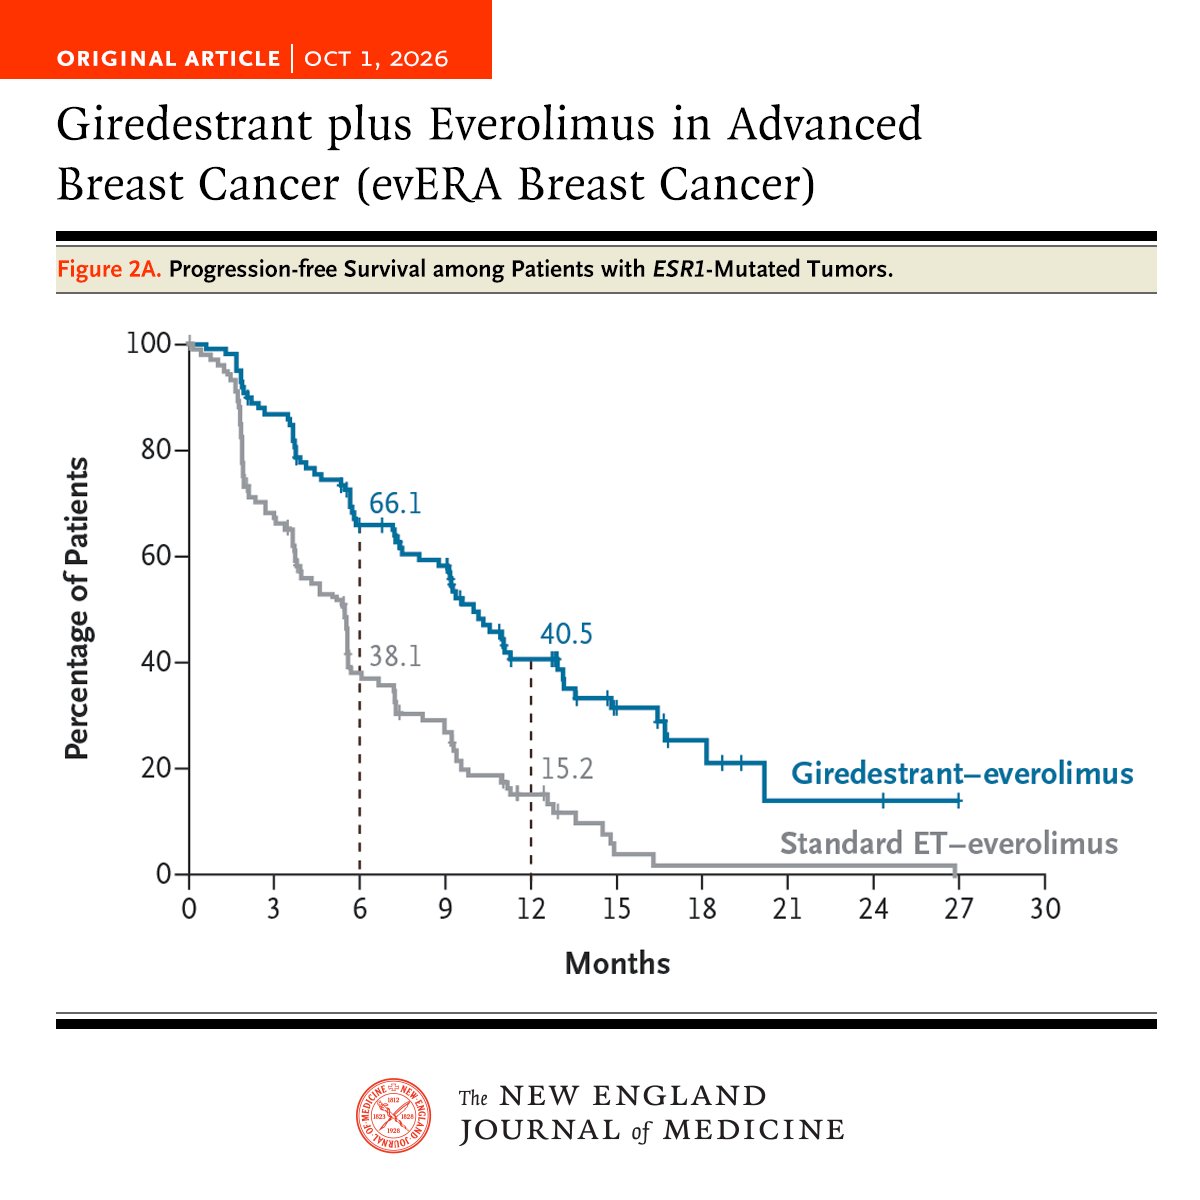
In ER-positive, HER2-negative advanced breast cancer, giredestrant, an ER degrader and full ER antagonist, plus everolimus led to longer progression-free survival than standard endocrine therapy–everolimus; safety was similar. Full phase 3 evERA Breast Cancer trial results: https://t.co/7vIwGQHatY
55yo patient with de-novo metastatic (bone) HR+/HER2- MBC. Received letrozole + ribociclib for 2 years, at which point she develops liver progression of disease. ctDNA shows an ESR1 mutation, all the rest wild type.
What next treatment would you choose, assuming all available?
Now published in Lung Cancer: Therapeutic Evolution in Resected Stage IB-IIIA NSCLC.
Click below to access the publication and explore real-world treatment patterns, biomarker testing gaps, and outcomes among US patients with early-stage and locally advanced NSCLC.
ORAL SERDs — WHERE DO I FIT? 🤔
The post-progression ER-degrader meeting:
💊 Elacestrant: “I was the first.”
💊 Giredestrant: “I tried everywhere!”
💊 Vepdegestrant: “I’m a PROTAC.”
💊 Imlunestrant + abemaciclib: “Together, we don’t need ESR1m.”
Then SERENA-6 / camizestrant walks in:
💬 “I found the sweet spot — BETWEEN THE LINES.”
🧬 ESR1m emerges during 1L AI + CDK4/6i
→ AI → camizestrant
→ continue the same CDK4/6i
→ before radiological progression.
So the question becomes:
If CAMI moves before progression… where do the post-progression agents fit?
Not head-to-head. Not obsolete.
Just a fascinating new sequencing question created by molecular interception.
#BreastCancer #OralSERD #ESR1 #SERENA6 #Camizestrant #PrecisionOncology #MedicalOncology #MVOnco
Perioperative IO in resectable NSCLC — the landscape at a glance. 🫁
6 Phase III trials → one simple question:
EFS benefit is common. Has OS followed?
✅ EFS positive in 5/6 trials
OS so far:
• KEYNOTE-671 (pembro): HR 0.74 ✅
• RATIONALE-315 (tisle): HR 0.65 ✅
• CheckMate 77T: HR 0.85 — interim, NS
• AEGEAN: HR 0.89 — interim, NS
• NEOTORCH: HR 0.62 — interim, NS
• IMpower030: HR 0.77 — not formally tested after the primary EFS endpoint was not met
The perioperative story is increasingly about moving from EFS → mature OS evidence.
#LungCancer #NSCLC #Immunotherapy #PerioperativeIO #ThoracicOncology #Oncology #MVOnco
What’s the difference between #cTMA and #aHUS? TMA describes the blood vessel injury and microclots - the effect. cTMA points to #complement as the drive - the cause. https://t.co/N674L8MNg7
That distinction matters- naming can help clarify diagnosis and treatment. #nomenclature
🩸 Facts about Smoldering Multiple Myeloma:
The PANGEA risk model, biomarkers linked to shorter time-to-progression, limitations of static risk models, progression risk in low- and intermediate-risk SMM, and high-risk SMM defined by a ≥50% 2-year progression rate.
#SMM #SmolderingMultipleMyeloma #MultipleMyeloma #Hematology #HemeOnc #Oncology #MedicalEducation #MedEd #ClinicalHematology #HemeHub
🫁 EGFR at #WCLC26: 5 trials to watch 👇
1️⃣ ADAURA | PL03.01
8-year update of adjuvant osimertinib in resected EGFR-mutant NSCLC.
🔥 How durable is the survival benefit at 8 years?
2️⃣ PAPILLON | PL03.03
Amivantamab + chemotherapy vs chemotherapy in 1L EGFR exon 20 insertion NSCLC.
🔥 Does the PFS advantage translate into an OS benefit?
3️⃣ REZILIENT 3 | PL03.04
Zipalertinib + chemotherapy vs chemotherapy in 1L EGFR exon 20 insertion NSCLC.
🔥 Could this establish another frontline standard for exon 20 disease?
4️⃣ ORIC-114
Next-generation, brain-penetrant EGFR/HER2 exon 20 inhibitor.
🔥 Can an oral TKI improve CNS control and reshape sequencing?
5️⃣ BLU-945 combinations
Next-generation EGFR inhibition after progression on osimertinib.
🔥 Can we target resistant EGFR clones while sparing wild-type EGFR?
Which one are you watching most closely?
#LungCancer #EGFR #NSCLC #WCLC26 @IASLC@OncoAlert
How do you individualize treatment for patients with high-risk #HCC?
Explore the new CME activity by @mlieducation on evolving frontline immune checkpoint inhibitor-based therapies, with a focus on #liver reserve, tumor burden, mortality risk, and patient-specific factors.
🔗 https://t.co/koNRl1niQh
Prostate RT in de novo mCSPC: the endpoint depends on volume.
🟢 Low volume → think SURVIVAL
STAMPEDE: OS HR 0.68 → prostate RT [II,A]
🟠 High volume → think GU PROTECTION
PEACE-1: delays serious GU events + improves CRPC-free survival → prostate RT can be recommended [II,B]
No proven OS benefit.
On triplet? Finish docetaxel → then prostate RT [III,A].
Same RT. Different reason. Volume matters.
📖 Fizazi K, et al. Ann Oncol. 2026;37:590–604.
ESMO Clinical Practice Guideline.
🚨 ONCO EMERGENCY: How to Manage EXTRAVASATION in 30 Seconds 🩺💉
Extravasation of chemotherapy = oncology emergency.
Early recognition + immediate action = tissue saved.
Here’s the crisp, protocol-ready approach 👇
1️⃣ STOP Immediately
❌ Stop infusion
❌ Do not flush
✔️ Leave cannula in situ
✔️ Aspirate as much drug as possible
✔️ Mark the area + click a photo
2️⃣ Identify the Agent
Classify the drug:
🔥 Vesicant (DNA-binding / Non-DNA)
😣 Irritant
🙂 Non-vesicant
(Anthracyclines, Vinca alkaloids, Taxanes, Platinum, Mitomycin etc.)
3️⃣ Two Key Pathways
A) “Localise & Neutralise” – DNA-Binding Vesicants
(Anthracyclines, Mitomycin, Dactinomycin)
❄️ COLD compress 20 min × 4/day × 1–2 days
💊 Antidotes:
<3 ml anthracycline → Topical DMSO
3 ml anthracycline → Dexrazoxane (Savene) within 6 hrs
Mitomycin → DMSO
B) “Disperse & Dilute” – Non-DNA Binding Vesicants
(Vinca alkaloids, Taxanes, Trabectedin)
🔥 WARM compress 20 min × 4/day × 1–2 days
💉 Hyaluronidase 150–1500 IU SC around site (5 injections)
4️⃣ Elevate, Analgesia, Plastics Referral
✋ Elevate limb
💊 Analgesics if required
🏥 Early plastics/flush-out team for large-volume or CVAD extravasa
tion
5️⃣ Follow-Up
Mandatory review within 1 week
Patient counselling: monitor for redness, blistering, worsening pain
Document EVERYTHING (site, size, drug, photo, interventions)
💡 TAKE-HOME
Extravasation is rare but high-stakes.
Most injuries are preventable with:
Good venous access
Trained staff
Fast action
Correct antidote pathway
Oncology teams save tissue before they save time. ⏱️🩺
🔖 Save this. Share with your residents and healthcare staff.
#OncoTwitter #MedTwitter #ChemoSafety #Nursing #Oncology @myESMO@OncoAlert@ESMO_Open@asco