NEET-PG Reforms: Is Reservation Compatible with Merit-Based Postgraduate Medical Education?
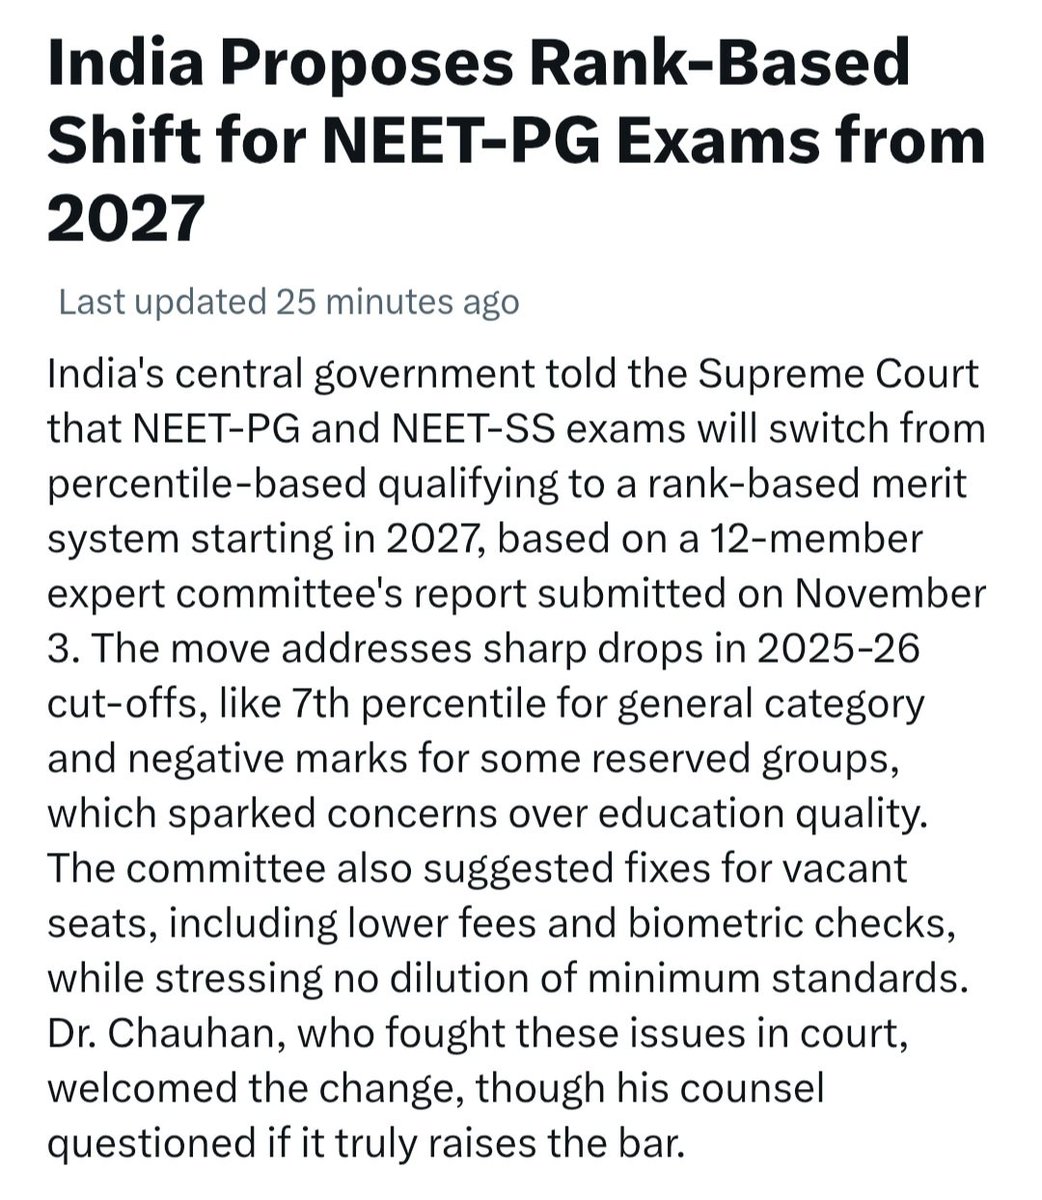
An expert panel appointed by the Union Health Ministry has proposed significant reforms in NEET-PG and NEET-SS admissions, including replacing percentile-based eligibility with a rank-based merit system, biometric verification, fee rationalisation and improvements in residency conditions.
However, the most fundamental issue remains unaddressed: why should reservation continue to determine admissions to postgraduate medical specialities, where academic competence and clinical proficiency are essential?
Replacing percentile with rank is unlikely to resolve the underlying problem. Both are measures of relative academic performance. As long as category-based seat allocation and differential qualifying thresholds continue, the overall rank list does not translate into a uniform standard of admission. Candidates with substantially different academic performance can secure admission to the same speciality under different allocation criteria.
The argument for reservation becomes particularly contentious at the postgraduate level. Medical graduates have already completed a professional degree and are competing for advanced specialist training. At this stage, selection should arguably prioritise demonstrated academic ability, clinical aptitude and preparedness for specialised responsibilities. Introducing category-based differences in qualifying standards risks subordinating these considerations to criteria unrelated to individual academic performance.
Medical education is not merely an avenue for obtaining a qualification; it is preparation for independent clinical responsibility. Ultimately, patients depend on the competence of their treating specialists, not the category through which they secured admission.
The panel has also recommended reducing fees for pre-clinical and para-clinical courses, addressing stipend disparities, reviewing service bonds, incentivising rural postings and improving employment opportunities.
These are relevant reforms, but they do not address the fundamental question of whether postgraduate medical admissions should be based on a common, transparent academic standard.
The real reform should be a merit-based postgraduate admission system with uniform minimum competency requirements, irrespective of category. Changing percentile to rank while retaining the existing reservation framework risks changing the mechanics of selection without addressing the underlying question of academic standards and professional competence.
Our doctor has written it so accurately!
In this country, a doctor is treated as a free service provider.
Why is only the doctor called a looter?
A doctor charges ₹500 as a fee:
“He’s looting everyone! ₹500 just for looking at you for 5 minutes? He didn’t even give medicine!”
A lawyer takes ₹5,000 for one hearing — “That’s the fee.”
An architect takes a 10% cut — “Those are professional charges.”
A tuition teacher takes ₹1 lakh in advance -“Education is expensive.”
A policeman openly takes money — “It happens.”
Leaders, clerks, engineers, contractors -they swallow crores -“That’s the system.”
But the doctor = looter. Wow!
Only doctors are expected to hold free camps.
Why?
Has anyone ever seen:
• A sweet-maker running a free samosa camp?
• A lawyer running a free bail camp?
• A teacher running a free admission camp?
• A Chartered Accountant running a free income-tax return camp?
• A politician running a free honesty camp?
• A police station running a free FIR camp without bribes?
No. Only the doctor is supposed to do free camps, free service, free check-ups. Otherwise, he’s not a good doctor. He’s just a businessman.
And who’s asking for this?
The same person who comes and says:
“Doctor sahab, give me a fake 2-day medical certificate, I need leave.”
“Doctor sahab, make the insurance bill a little bigger.”
“Doctor sahab, make a small change in the MLC (medico-legal case).”
You yourself are not honest, but you want charity from the doctor?
Let me tell you —
You’re not paying for my 5 minutes. You’re paying for my 38 years.
12 years of MBBS and MS studies, nights spent without sleep, festivals missed, my own children’s birthdays missed, standing for 4 hours in the OT (operation theatre) at 2 a.m., putting my hands inside your abdomen, stopping the bleeding, and saving your life while you sleep.
My advice itself is my medicine. That advice can save you from death. One wrong piece of advice can take a life. Behind these 5 minutes of advice lies the experience of 50,000 patients.
Yes, some doctors are commercial — I admit that.
But
Some teachers sell papers,
Some lawyers sell justice,
Some clerks sell files,
Some leaders sell the country.
The entire system is corrupt — yet only the doctor gets abused? Because the doctor won’t kill you, won’t abuse you back, and will stay silent.
Don’t come for charity. Come for treatment.
If you want charity, make it compulsory for every profession.
Otherwise — pay the fee with respect.
₹500 is not looting. Your thinking is the loot.
— Dr. Ajeet Singh, MD (Physician)
(Copied from Facebook)
3,426 MBBS seats are still empty, and private colleges are now offering 40% off.
This in a country where about 24 lakh students write NEET for roughly 1.4 lakh seats.
So has the new generation stopped seeing the ROI in becoming a doctor?
I don't think the dream has died. Every government seat is filled, so the demand is clearly there. What has stopped working is the math.
A private MBBS seat now costs around ₹1.25 crore all in. Every aspirant also knows that MBBS isn't the end. You need a PG, which means another entrance exam, a few more years and often another big cheque. You start earning properly close to 30, on a loan that started growing when you were 18.
Today's students and parents work this out openly at the dining table. A generation ago the white coat was reason enough to sign up.
75% of new MBBS seats in the last three years went to private colleges. We added seats, but we didn't make them any easier to afford. Lowering NEET cut offs won't fix this. Students are qualifying. They just can't pay.
Medicine is still one of the most meaningful careers there is. But you can't sell a ₹1 crore degree on passion alone. Fee regulation, more government seats and a clearer path from MBBS to a real income are what will fill these empty chairs.
So which is it, an ROI problem or an affordability problem? I'd like to hear your view.
#NEET #MBBS #NEETPG #MedicalEducation #DoctorsOfIndia
I'm a doctor. My community is Jeevan-data. You don't exist if we don't exist. If you lived today, thank a doctor. And here are our demands to the govt:
1. MCP (Minimum Consultation Price) to be legalised at Rs 1000 per patient by law. If a patient is not able to pay that much, govt should pay.
2. Right to proxy block the highways: Since doctors are too lazy to leave their OPDs and hospitals to physically block the highways, they should be allowed to hire people to protest on their behalf and govt should reimburse that amount.
3. Rs 1 lakh pension to every doctor after they turn 30, even if they are practicing.
4. Govt to pay for doctors insurance: Since physical violence against doctors is not uncommon, Govt should provide full insurance charges for all doctors.
5. Minimum 10 crores interest free loan to every doctor for setting up their hospitals, which we'll not pay back and should be waived off at the end of financial year.
Which "data" are you and what your demands?
I’m Mumbai, all bars are open but temples are not. You can travel 2 hrs in an elbow-to-elbow plane/local train but can’t see a movie in a safe theatre. You can eat in a jam packed 150% full restaurant but can’t eat at a food court. Why do we have such irrational governments?
@SonuSood Sir my mother is admitted in Venkateshwar Hospital, and she us suffering from sever sepsis and multi organ damage.. I have done watever i can do, but as per docs there is comming estimate of 12lacs..I am running a fundraiser with ketto. Please help in any way u can.
The protocol on airlines website do not mention anything regarding vaccinated individuals and Icmr has asked not to do rt pcr for traveling purpose hence the question
@mybmc@CSMIA_Official@MumbaiPolice i am a doctor at k.b. bhabha hospital bandra, i am traveling from Gorakhpur(u. p.) to mumbai, i am completely vaccinated and asymptomatic, do i still need to do the Rt Pcr?
India has its shortcomings.
But it would be absolutely unfair if we didn’t take a brief pause to recognise our milestones.
Today, we’re the fastest nation in the world to administer 100-million vaccines:
🇮🇳India took 85 days
🇨🇳China, 102 days
🇺🇸USA, 89 days
#MaskUpIndia
With Rtpcr -ve cases, only hrct showing changes & no symptoms in intial days, With so many colleagues infected and inavailability of beds how are we going to break the chain? It is spreading like wildfire. #maharashtralockdown#newcovid#COVIDー19@mybmc@OfficeofUT@PMOIndia
Kinesins are motor proteins that move molecules around the cell. They are powered by ATP and transport molecules along microtube filaments at a rate of 2000 nm/s, meaning they take 250 tiny steps a second.
A stunning example of cellular nanotechnology! 🧐
What did @narendramodi do, what did India do to achieve this remarkable result? Preexisting immunity? Wholistic healthcare & Ayurveda? The many limbs of Yoga? Bhakti?
New SARS_CoV_2 virus strain update. TL;DR - there is something to understand more, and it looks like the virus has tweaked its biology at least on transmissibility; Public health, scientists + surveillance systems are on it.