A very nice AI-based tool from #MASCC for supportive care information.
I guess the AI wave has swept over the #oncology landscape as well.
There were so many presentations on the use of AI in prevention, screening, diagnosis and treatment. Some hype, some truly promising.
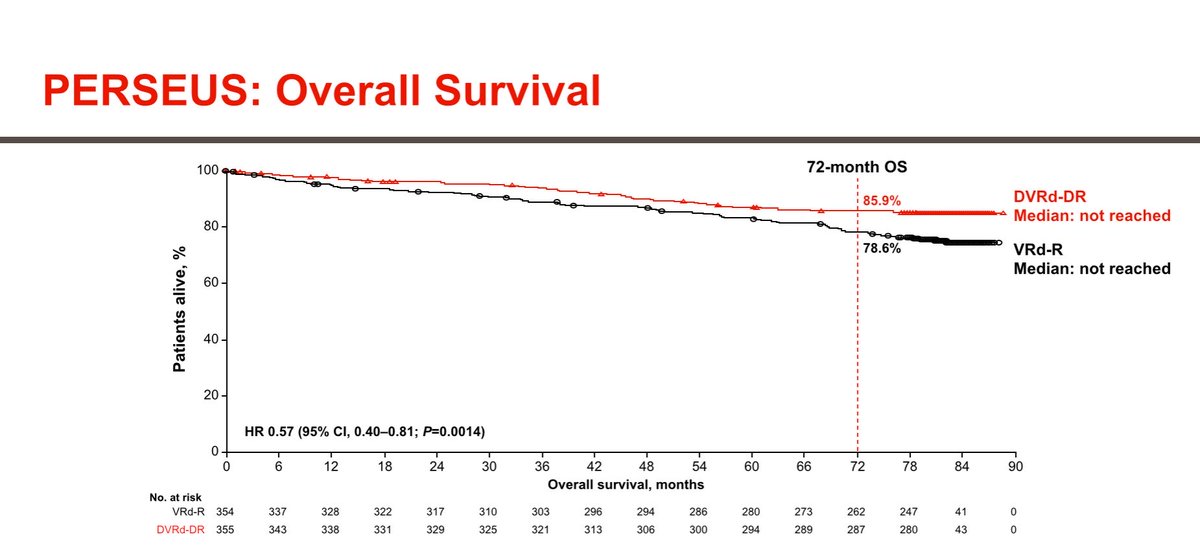
PERSEUS is the gold standard benchmark outcome for Newly Diagnosed Myeloma
6 year overall survival: 86%
6 year PFS 81%
with quad induction and Dara-Len maintenance.
As we test bispecifics, ADCs, CARTs etc, any new approach should be better. A new therapy CANNOT have even 5% all cause mortality in first 4 years.
There is no room for error with infection related mortality. No early drop off. No learning curve. As a field we have to establish preventive measures to prevent infection related deaths. #IMS26
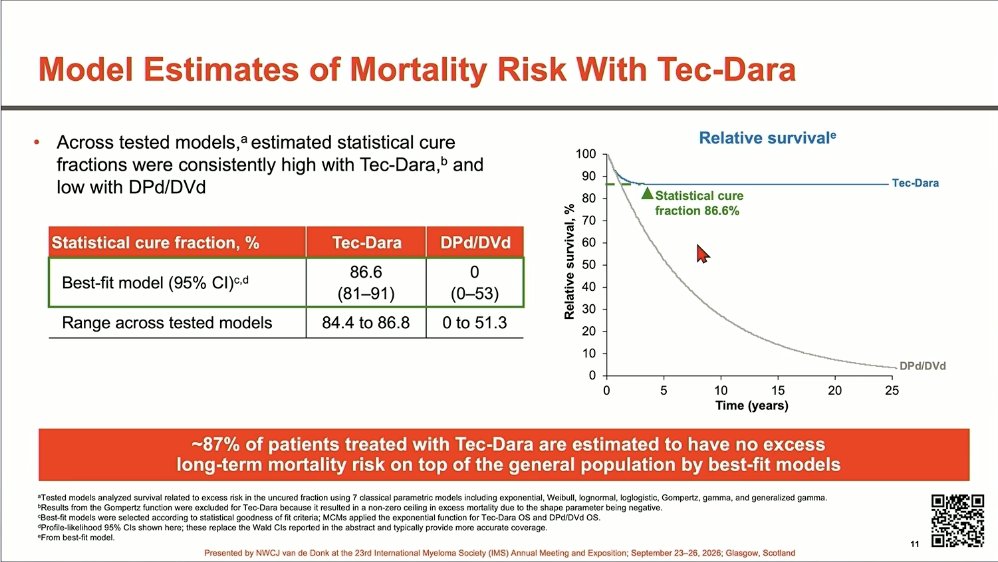
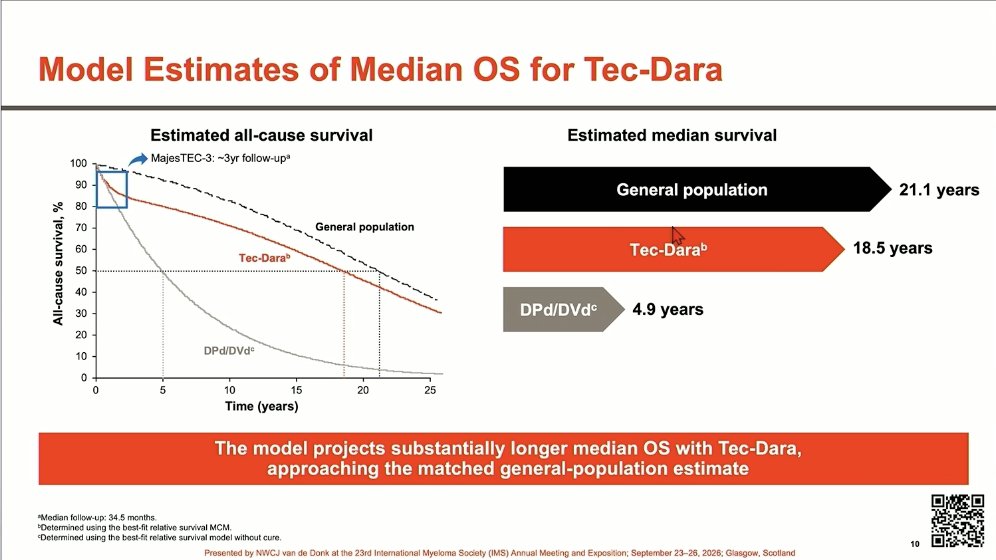
#IMS26#mmsm Oral- % of functional cure with the use of Tec-Dara @Myeloma_Society
Estimated functional cure of 87% with Tec-Dara showing excellent promise of such therapy.
➡️Future will need time limited therapy (Stop and see what will happen)
➡️Assess cumulative toxicity with longer use of this therapy (infections most imp)- Non relapse mortality will be imp
Future is bright in myeloma
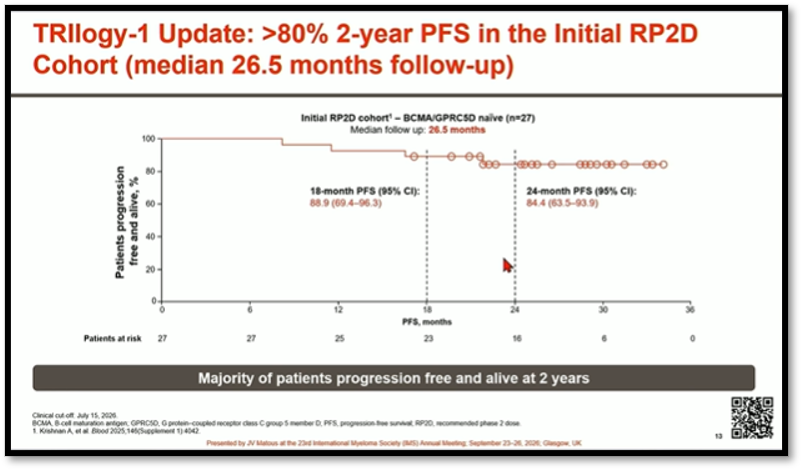
Incredible 2-year PFS with Ramantamig in a ~95% CD38-refractory and 100% triple-class exposed population! These results are substantially superior compared to single-agent BCMA BsAbs and BCMA or GPRC5D CAR Ts in similar population. Based on these results, its plausible that we will see a near-flat PFS curve with Ram in Trilogy-5!
#IMS26
@AlGarfall@MileHighMyeloma
🧬 Daratumumab: beyond a myeloma antibody.
For two decades, Revlimid has been the backbone and immune amplifier of myeloma therapy.
But is the backbone changing? 👑
Dara does more than kill CD38+ myeloma cells. It remodels the immune ecosystem, depleting CD38+ Tregs, Bregs and MDSCs while expanding and diversifying T-cell populations.
Then partner the platform with an immune amplifier:
Lenalidomide → Iberdomide
Or with T-cell redirection:
Teclistamab → Talquetamab
MAIA → AURIGA → Iber-Dara → MajesTEC-3 → MonumenTAL-3
Different partners. Different mechanisms. One evolving strategy.
Revlimid may have ruled the myeloma kingdom for two decades. Is Dara ready for the crown? 👑
Perhaps Dara is no longer simply another drug in the combination.
It is becoming the immune platform upon which we build the next generation of myeloma therapy.
#MultipleMyeloma #MMSM #MedTwitter
My 2026 Update on Diagnosis, Risk Stratification, and Treatment of Myeloma is out! #OpenAccess
It’s current including all recent advances in immunotherapy. Managed to squeeze in iberdomide approval from 6 days ago! Bookmark!
https://t.co/VUheu7xlMr
Actualizaciones 2026 de Mieloma Múltiple (MM) de American Journal of Hematology. Cambian algunas cosas:
🔴 La terapia inicial ya no es triple. Sino cuádruple: Dara-VRd o Isa-VRd para todos, sean o no candidatos a trasplante.
🔴 El trasplante dejó de ser "el primer paso". Va después de 3–4 ciclos, y en riesgo estándar se puede diferir hasta la primera recaída.
🔴 Nueva definición de alto riesgo (IMS/IMWG): t(4;14) sola ya NO es alto riesgo. Necesita gain(1q) o del(1p) concomitante. Igual gain(1q) aislado.
🔴 El mantenimiento sí mejora la mortalidad. Estándar: lenalidomida + anti-CD38. 2 años en riesgo estándar, hasta progresión en alto riesgo.
🔴 Mieloma latente de alto riesgo: daratumumab 3 años (AQUILA Trial). Antes era solo observar.
🔴 Primera recaída: cilta-cel o Tec-Dara desplazan al triple clásico.
🔴 Ya no: trasplante en tándem, consolidación post-trasplante y alogénico.
Es un tema complejo pero muy interesante. Completo en (https://t.co/3O93s10lns).
Who should receive FLAG-IDA-VEN as induction for newly diagnosed AML?
The results are impressive: CRc ~95%, MRD negativity ~90%.
But perhaps we are asking the wrong question.
The question is not whether FLAG-IDA-VEN is active. It clearly is. The question is whether its deeper early response translates into enough durable benefit to justify substantially greater treatment intensity.
Once TP53-mutated AML is separated out, the differences among contemporary approaches may be considerably smaller than the early response rates suggest. Importantly, less-intensive VEN-based therapy can still successfully bridge a substantial proportion of patients to allo-HCT.
So what are we buying with FLAG-IDA-VEN?
More early MRD negativity? Probably.
But do we get more sustained MRD negativity?
More patients to allo-HCT?
Better EFS?
Better OS?
We don’t know.
What we do know is the price of greater intensity: more cytopenias, transfusions, infections, antibiotics/antifungals, hospitalization, supportive care and resource utilization.
NCCN lists FLAG-IDA-VEN as a Category 2B option for selected patients, not a preferred induction regimen.
And the future may increasingly be VEN + biology rather than VEN + more chemotherapy: FLT3 inhibitors, menin inhibitors, IDH inhibitors and other targeted approaches.
A randomized trial could define the true incremental benefit of FLAG-IDA-VEN.
It will probably never happen.
Until then, the added benefit appears marginal at best, while the added treatment burden is very real.
DEEPEST RESPONSE ≠ BEST OUTCOME.
SAME BRIDGE TO ALLO. DIFFERENT TREATMENT BURDEN.
WHERE IS THE ADDED VALUE?
🧬 In Biology We Trust.
#AML #Medtwitter
1/7 Lenalidomide maintenance: what have two decades of trials actually taught us?
The PFS benefit is remarkably consistent—but population, duration, exposure, biology, and trial design all matter.
A visual mini-series on what the evidence proves—and what it does not.
#MultipleMyeloma #MedTwitter
Eltrombopag Added to Standard Immunosuppressive Treatment as Front-Line Therapy for Severe Aplastic Anemia: Long-Term Outcomes of the Phase-3 Randomized Superiority EBMT-SAAWP RACE Study
https://t.co/jhwym4tBjC
https://t.co/URmEGy3xvU
One-stop free-to-use website to risk stratify myeloma, MGUS, smoldering myeloma, Waldenstroms Macroglobulinemia, Amyloidosis.
Also links to iStopMM calculator to determine when a bone marrow is needed in MGUS.
Will be regularly updated. More calculators and links to key articles will be added soon!
Landmark Paper in Hematology: results of the seminal trial published by Bacigalupo et al. in 1991 highlighted the power of immune-mediated leukemia control after allogeneic transplantation.
Read more in Haematologica
https://t.co/8knZFfLmjI
MAXILUS trial (#EHA26, S173 | Della Porta et al.): luspatercept at the max-approved 1.75 mg/kg SC Q3W from cycle 1 in transfusion-dependent LR-MDS.
Phase 3b, open-label, non-randomized, 2-cohort (ESA-naïve & ESA-R/R/I) — both arms get luspatercept, no active comparator.
Signal (ESA-naïve, n=54):
• 81.5% met primary endpoint (RBC-TI ≥8wk + concurrent Hb ↑≥1 g/dL, Wks 1–24)
• RBC-TI ≥8wk 83.3%, ≥12wk 75.9%; median peak Hb 11.3 (Δ +3.2 from baseline 8.1)
• Held up in RS− (73.9%) & sEPO ≤200 (86%); DOR not reached
• ESA-R/R/I more modest but real: 61.5% primary endpoint, median ≥12wk TI DOR 59.6wk
caveats:
• Non-randomized, no comparator → can’t be benchmarked head-to-head. COMMANDS-comparable endpoint here (RBC-TI ≥12wk + Hb ↑≥1.5) is 72.2%, numerically above the COMMANDS luspatercept arm — but cross-trial + enriched population, NOT a fair comparison.
• Max dose front-loaded (vs standard 1.0→1.75 titration); design can’t isolate how much benefit is the ceiling dose vs the population.
• Selected for response (sEPO ≤200, Hb ≤10).
• Safety isn’t free: Gr3/4 TEAE 68.5%; EOIs incl fractures 13%, HTN, kidney toxicity, malignancies. 4 Gr5 TEAEs (7.7%) in ESA-R/R/I. Early HR-MDS progression ~4%.
• Median f/u ~11 mo → OS, QoL, durability, late toxicity all pending.
Based on the latest data at #ASCO26 awe can consider bispecifics especially teclistamab (has the most data) alone or in combination with daratumumab in first relapse of myeloma.
Here is our latest https://t.co/x9KJzoJyXJ approach to first relapse.
#ASCO26#mmsm
High-Risk Multiple Myeloma: Redefining Risk and Rethinking Therapy
@DrGarethMorgan1
Summary of Phase 3 Randomized Trials in Early Line Relapse, Outcomes in Selected Populations
The triplet combination of quizartinib, decitabine and venetoclax improved overall survival in older patients with newly diagnosed FLT3-ITD AML, Dr. Musa Yilmaz shared at #ASCO26. Learn more: https://t.co/pxHZDcxXXx @MusaYilmazMD#EndCancer
In the GALE CRUSTED trial, higher-dose ivermectin plus permethrin was no better than standard-dose ivermectin plus permethrin, but both regimens were effective, leading to cure in 75% and 82% of the patients, respectively. Full trial results: https://t.co/tCKUAG1RWU