What if a small molecule could activate a transcription factor program in one cell type and destroy the same pathway in another? In our new preprint, we describe one such story on bifunctional molecules that toggle between transactivation and repression.
Great thread. Most seminal scientific theories and ideas came from small data + serendipity, not Big Data. Correlations can be very useful, but massive correlations don’t by themselves a theory make.
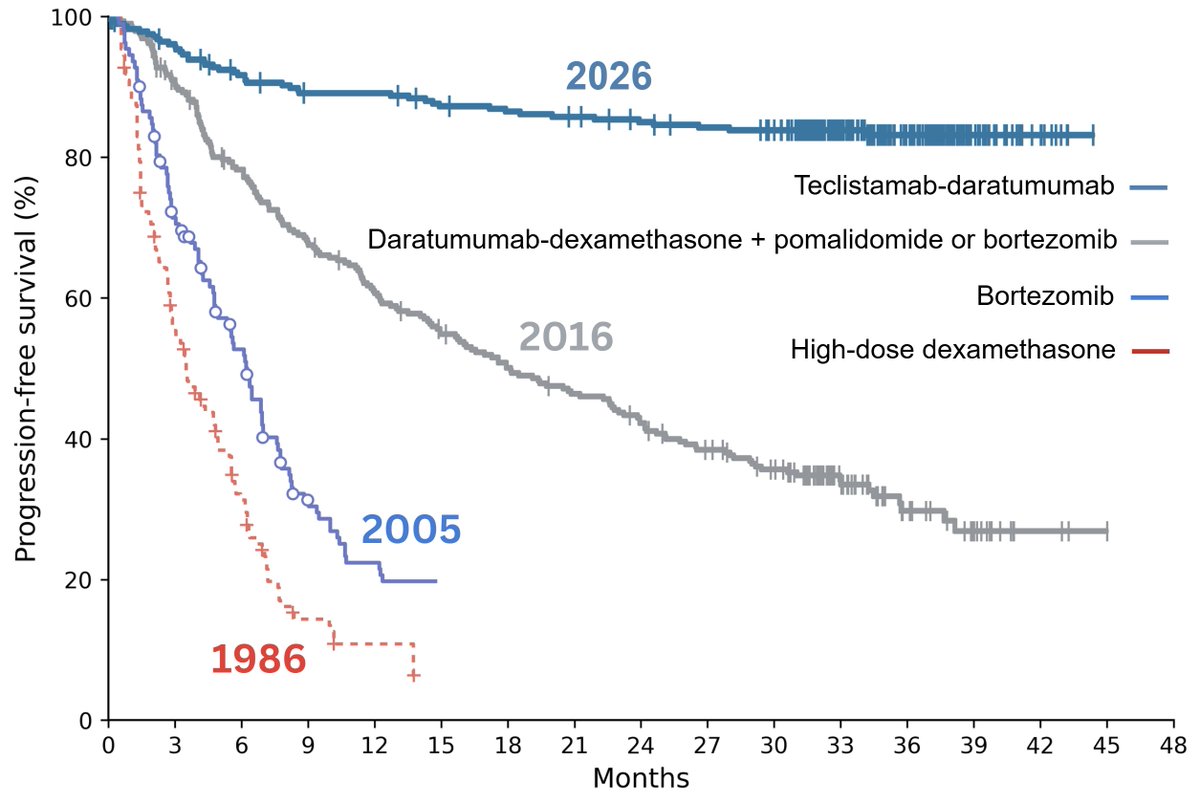
"In medical research, there’s a practice of ending a study early when the results are too striking to ignore. ... When an intervention works this clearly, you change what you do."
While not publicly traded, Halda presented one of the most exciting data during the AACR triple meeting, ultra novel RIPTAC modality
Steep and durable responses with this new modality! Cheers!
https://t.co/5wd8svxmpc
(5/6) Most exciting part is this novel MOA has very encouraging prelim activity against mCRPC. In pts with ≥ 6 wks tx, PSA50 was 59%, PSA90 was 32%, PR in 5/5 pts with RECIST-evaluable, and activity regardless prior tx or genomic alterations
(1/6) Introducing an AR RIPTAC therapy, HLD-0915, for men with mCRPC by @HaldaTx We presented data from the FIH, phase 1 trial at the @AACR#Targets25 meeting. Here’s the Tweetorial for this active, tolerable, oral med and link to the slides https://t.co/mKbro4l0Or
Remember all those BET/bromodomain inhibitors/degraders that went by the wayside due to severe toxicities and a poor TI?
It turns out there's a cool and better way to drug the key BRD4 target if you choose wisely...
https://t.co/gBdDD4JINV
In Himachal Pradesh in the northern part of India, a nurse named Kamla Devi bravely crosses a raging river to tend to and vaccinate a newborn.
https://t.co/AGhrrEx5I0
Ever since the Lady Gaga migraine ads, I've wondered what the ODT meant in Nurtec ODT.
It means Orally Disintegrating Tablet.
Okay, so what? Lots of drugs are oral. Why does Nurtec have ODT in the brand name while most drugs don't?
I ended up in a drug branding rabbit hole.
This is a major story from #ASCO25. Randomized phase 3 trial of time of day of immunotherapy infusion. Randomized to infusion before or after 3pm. Early infusion far superior: PFS 11.3 vs 5.7 HR 0.42, OS HR 0.45! Impactful, pragmatic, not costly. This should be a bigger story.
2/N
Take Home Points in Metastatic Hormone Sensitive Prostate Cancer (mHSPC):
· ADT + ARPI is the clear minimum standard across disease volume and synchronous/metachronous
· Docetaxel addition is generally not favored in low-volume disease, should be avoided in low-volume, metachronous disease and generally favored in high-volume disease
· ADT monotherapy should be avoided
· XRT to the primary is highly favored in synchronous low-volume disease and has only a limited role in synchronous high-volume disease.