@ResearchPulse1@bioinvestor24 But at the same time how much money have tirzepatide and semaglutide made at this point? Still multi billions to be made TBH ALas the TAM is enormous
🔔Elora+Tzp Phase 2 T2D was presented at Obesity Week today. This was presented at EASD 2026 earlier this fall, but they gave us more background today.
INTRO
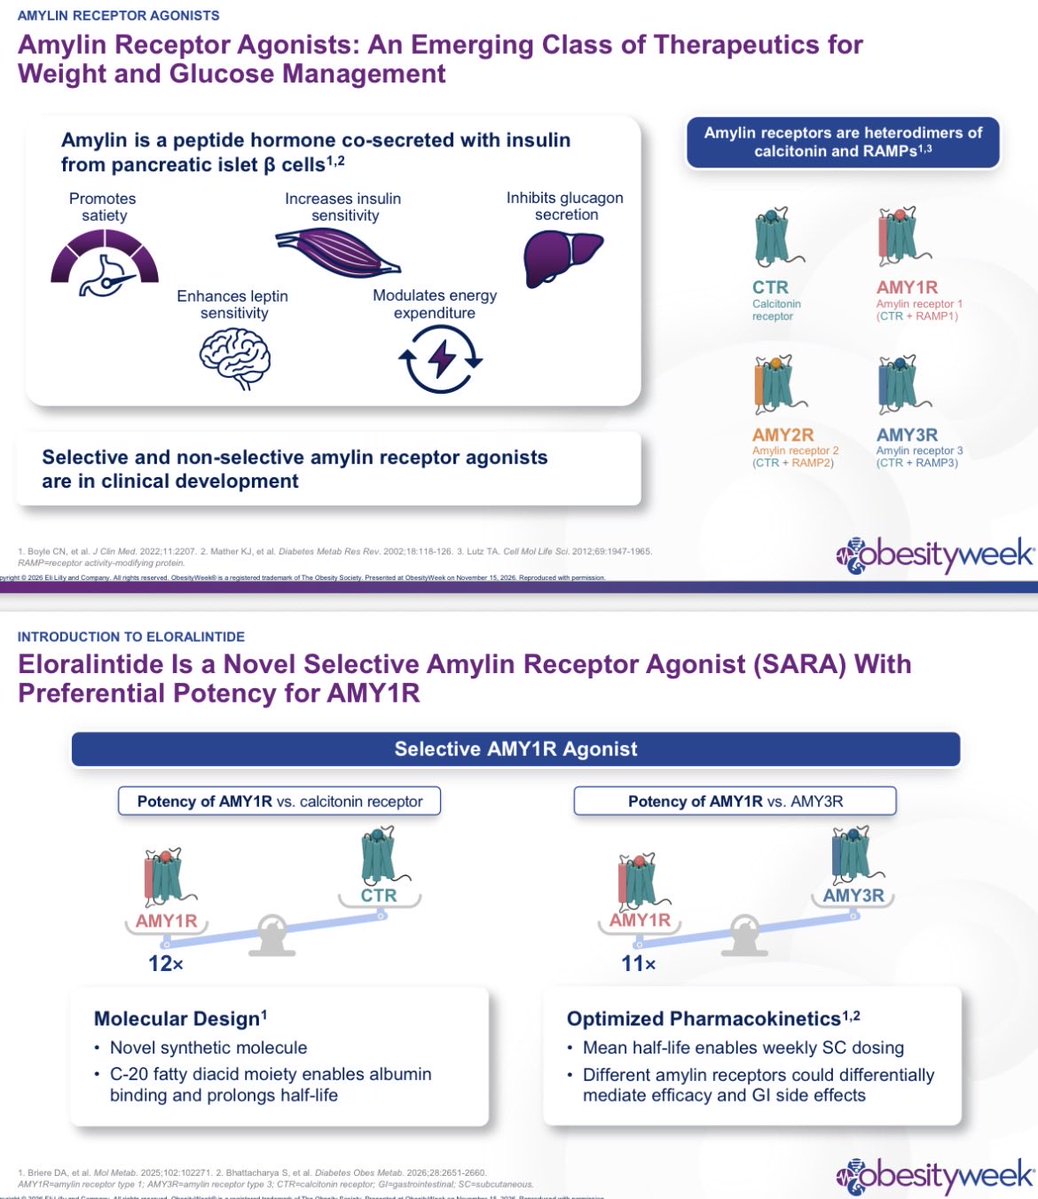
▪️Set the stage by reviewing the Eloralintide’s potency at the AMY1R receptor vs both CTR and AMY3R, establishing it as a selective amylin agonist
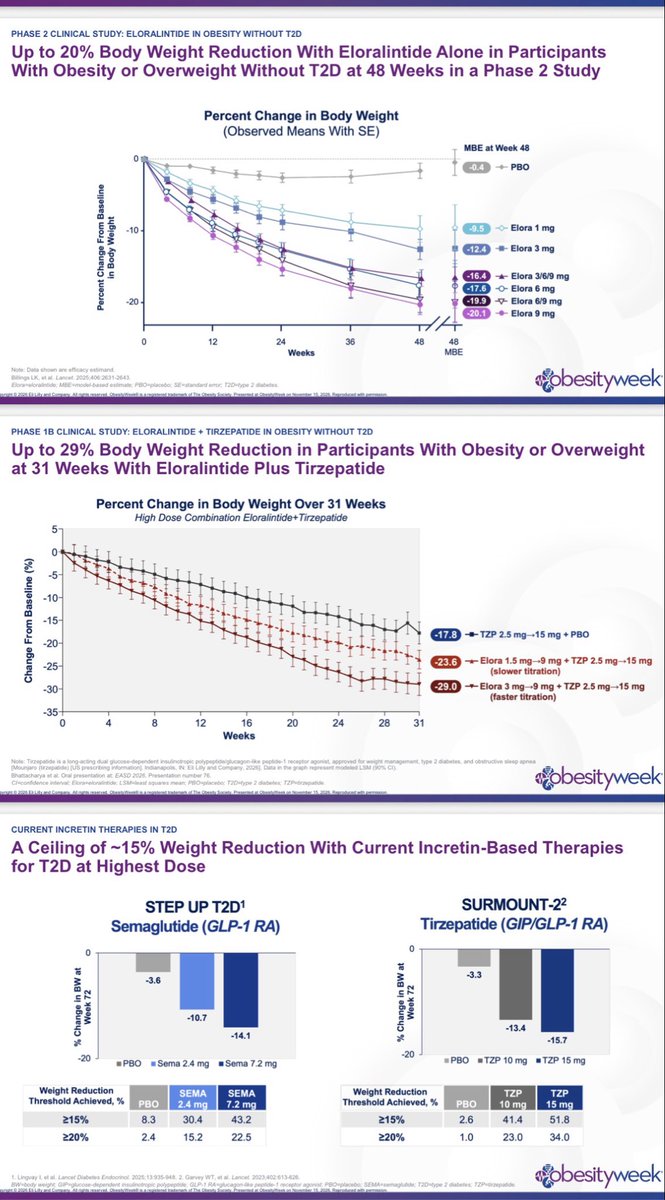
▪️Reviewed Elora’s 48 week Phase 2 performance on its own (up to 20% WL) and the recent P1 Elora + Tirz data (up to 29% WL at 31 weeks) - both in obesity without T2D
▪️Prior best performance in T2D for weight-loss was 16% at 72 weeks (using tirzepatide)
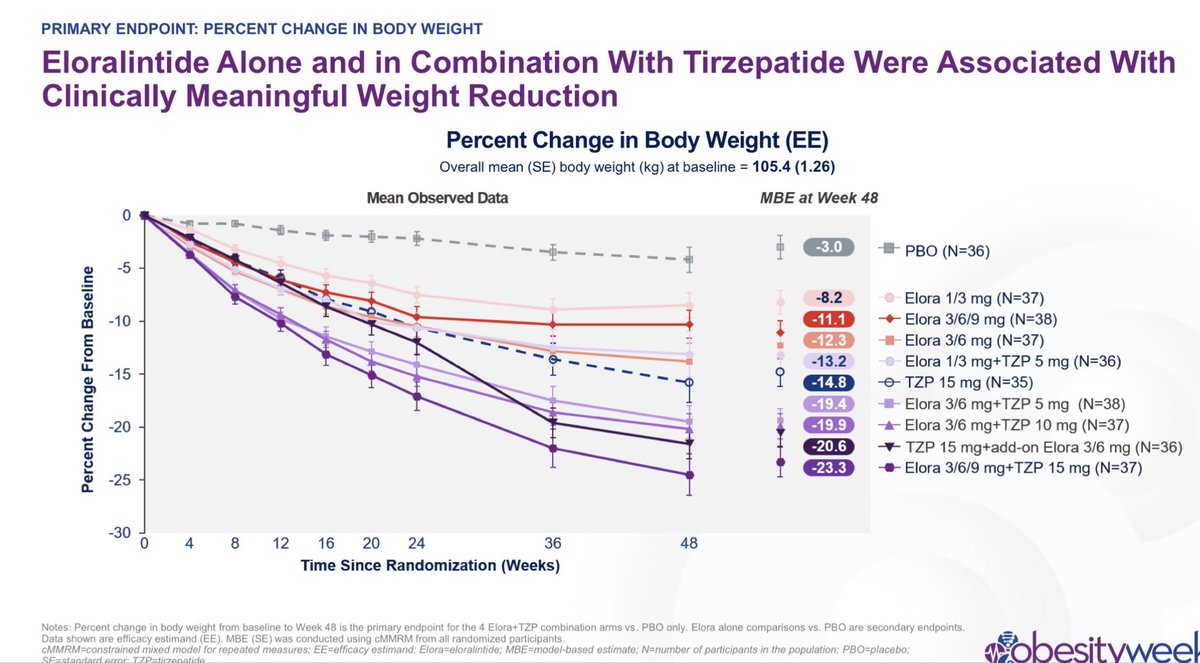
RESULTS (48 weeks) - Efficacy estimand
▪️Elora alone - 8-12% WL, 1.1-1.4% A1C reduction
▪️EloraTZP (3/6mg Elora) - 19-23% WL, 2.6-2.9% A1C reductio
💥NEW INFO💥
▪️BMI targets: On highest EloraTzp dose, 46% reached BMI <= 25 (Baseline BMI of 40) 😲
▪️AE DC reasons🙌: 1 EloraTzp + 1 Tzp for weight reduction, 4 EloraTzp for decreased appetite, 5 EloraTzp for nausea, 2 EloraTzp vomiting
▪️Pulse rates dropped on Elora alone, rose on TZP, and were in the middle for EloraTzp
▪️Body composition changes: Fat loss index (% of WL from fat): Elora alone - 60-66%, EloraTzp (3/6mg) - ~70%, Tzp + Add on Elora 60%
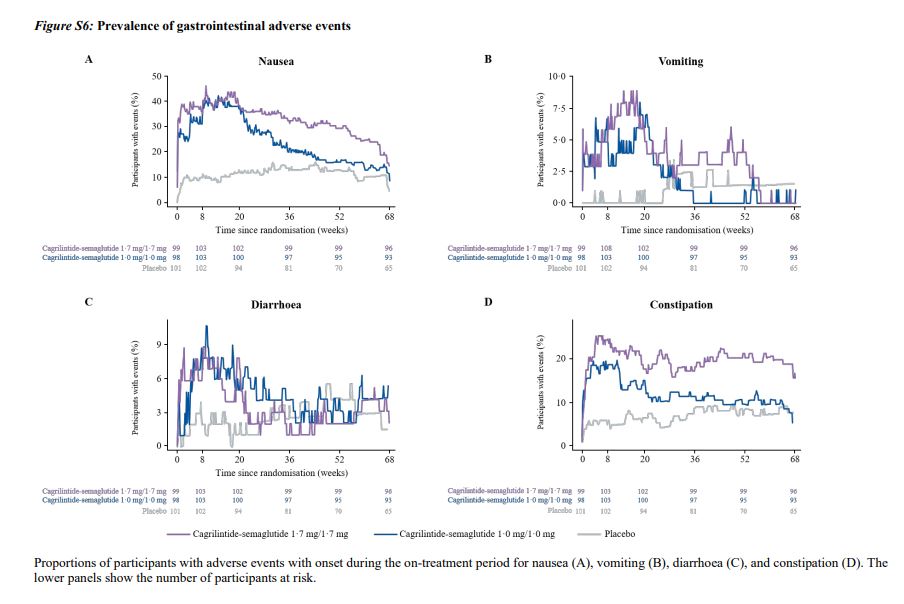
▪️Prevalence of side effects
▪️Prevalence and severity of fatigue
@bioinvestor24 First trial I've ever seen with decreased appetite as a reason to stop the trial.
Also the these two slides. Elora alone is a modest diabetes drug. Together it's super effective. And the % with normal BMI in just 48 weeks is 🤯
@ZdenekStepanek7 Just look at the percentages of side effects. Take literally 1 minute of critical thinking to examine these results to see incredibly high rates of N/V/D and constipation
Cagrisema in Redefine 9...worse tolerability at lower doses than Survodutide and that's with more flexible titration. It's not as good for A1c as tirzepatide, and even the lower doses have over double the rate of SE/AE as tirzepatide. I can't see myself prescribing this often.
@jdgs28 Not like plain Sema fits the definition. I mean enicepatide hits this mark too. So does VK2735. It's just marketing stuff that I'd expect from a sales rep not a major obesity conference announcement 🙈
Pick Tirz, Elora or Reta and look at week 8! All of them are about ~7% average weight loss! Just meaningless marketing talk here from Novo. Most people respond quickly to these newer generation meds!
#PRESS Novo’s CagriSema analyses show 67.8% of people studied are early responders, achieving ≥5% weight loss by week 8. Adults with overweight or obesity also reported meaningful quality of life improvements in physical function. Learn more in the press release here: https://t.co/4mis5Gapwj
@Aktieland I'm pointing out the absurd nature of this claim. It's pure marketing by Novo. It's utterly meaningless. Its cherry picking a data point. Using their own data average weight loss for all CS patients at week 8 was 5.6% so what's the point?!
@ResearchPulse1@ObsvRetardation DC is confounded in these trials because people are getting paid money to stay in the trial, they have a principal investigator encouraging them to stay, being in a trial is a self-selection bias on its own. These people are motivated to stay in. That's why it's a confounder
@JCanNuSH@ObsvRetardation I know it's imperfect but you get the idea I'm trying to show. Many of the Survo DC rates were because they were forced to stop by trial protocols vs dose reduction or skipping in the CS trials..flip those around and CS is in the same place as Survo is right now IMHO.
@JCanNuSH@ObsvRetardation To be clear Survo has it's issues, but it's probably a more tolerable drug than folks *think* just because of how the trial was designed. I think both CS and Survo have an uphill battle ahead of them. But at least with Survo I see a similar AE profile over time like tirz or sema
@JCanNuSH@ObsvRetardation I know we're on the same wavelength about this. Check out Survo. Huge DC rate due to rigid trial protocols. Nausea rate never gets above 10%!! Give Survo the same trial flexibility as CS & I bet the DC rate plummets. Having 30% nausea + 20% constipation a year into trial is wild
@ResearchPulse1@ObsvRetardation I'm not worried about trial DC rates. That's confounded always.
But as a prescriber I get to tell patients your risk of nausea, constipation and fatigue is quite high compared to tirz, plain Sema or Reta. That's the crux of the issue
@ResearchPulse1@ObsvRetardation But then I worry about generalizability with such strict inclusion criteria. And still the SE rate remains high in R1(55% nausea) Can it hit that 25%?? Probably? But there's also a seemingly flat dose response curve in post hoc analysis. I dunno. We'll see.
@ResearchPulse1@ObsvRetardation But the rub with R11 is we now have 2 different trials showing it's hard for people to sustain dosing on Cagrisema. R1 was only 57% on the 2.4 at the end of trial. And yesterday was 67% and 75% for 1.7 & 1.0 respectively. Not sure forcing titration back up is the solution.