🧬 ESMO 2026 | 12 PRESIDENTIAL ABSTRACTS
12 trials. 12 take-home messages. One glance.
From personalised mRNA vaccines and ADCs to targeted therapy, immunotherapy combinations and treatment de-escalation.
✅ What improved: RFS, PFS, EFS, MFS or OS?
⚠️ MOIO reminds us: Less frequent treatment is not automatically equivalent.
The evidence in one line. The implications for practice.
@myESMO@OncoAlert@larvol
#ESMO26 #Oncology #ClinicalTrials #MVOnco
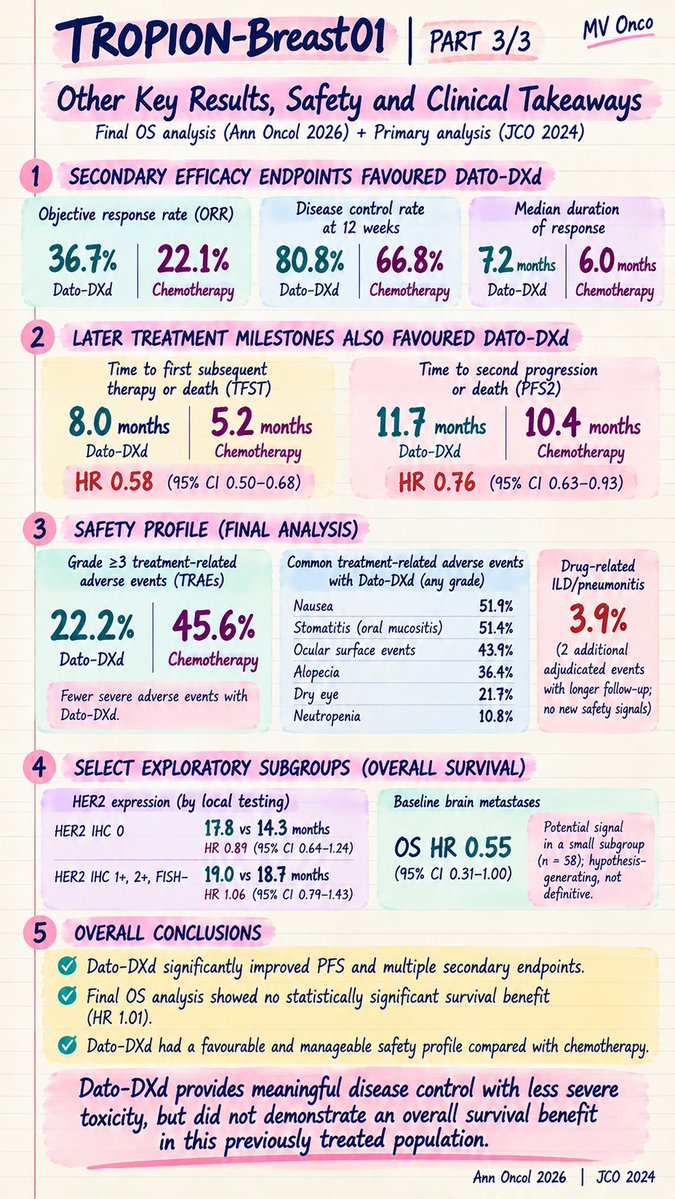
🧬 TROPION-Breast01: PFS WON. OS DID NOT!
✅ Dato-DXd vs chemotherapy in previously treated HR+/HER2− metastatic breast cancer (n=732).
📈 PFS: 6.9 vs 4.9 months (HR 0.63).
❌ Final OS: 18.6 vs 18.3 months (HR 1.01) — no survival benefit demonstrated.
🔄 Subsequent ADC use: 12.3% vs 24.0%, favouring the chemotherapy arm. Could this have diluted the OS difference?
🔍 Post hoc adjusted OS: HR 0.86 — exploratory, not statistically significant.
✅ Better response rates and fewer grade ≥3 TRAEs (22.2% vs 45.6%). ⚠️ Stomatitis, ocular toxicity and ILD remain important.
🎯 Take-home: Better disease control ≠ longer survival. Subsequent ADC therapy may matter, but does not establish an OS benefit.
Bardia et al., JCO 2024; Pistilli et al., Ann Oncol 2026.
@myESMO@OncoAlert@larvol #MVOnco #TROPIONBreast01 #DatoDXd
PD-L1-high NSCLC: adding chemo to pembrolizumab delays progression, but adds toxicity without a proven survival gain.
Thanks to Decroisette & the GFPC team
Who really needs the chemo in first line?
#ESMO26#NSCLC
💊 ADC SEQUENCING: TARGET OR PAYLOAD?
Does changing the ADC really change the weapon?
✅ Same target + different payload: T-DM1 → T-DXd
✅ Different target + different payload: EV → SG
⚠️ Different target + same payload class: T-DXd → SG
⚠️ Same target + same payload class: Dato-DXd → SG
🔬 DXd and SN-38 are different drugs, but both are TOP1 inhibitors.
🎯 Changing the TARGET ≠ changing the WEAPON!
SWITCH + SATEEN highlight potential payload cross-resistance. Sequencing remains context-dependent, not an absolute YES/NO rule.
📚 Refs: Liu X et al., SWITCH, ESMO 2026 (4RO); Tarantino P et al., SATEEN, ESMO Breast 2026 (LBA4).
@myESMO@OncoAlert@larvol #ADC #ESMO26 #MVOnco
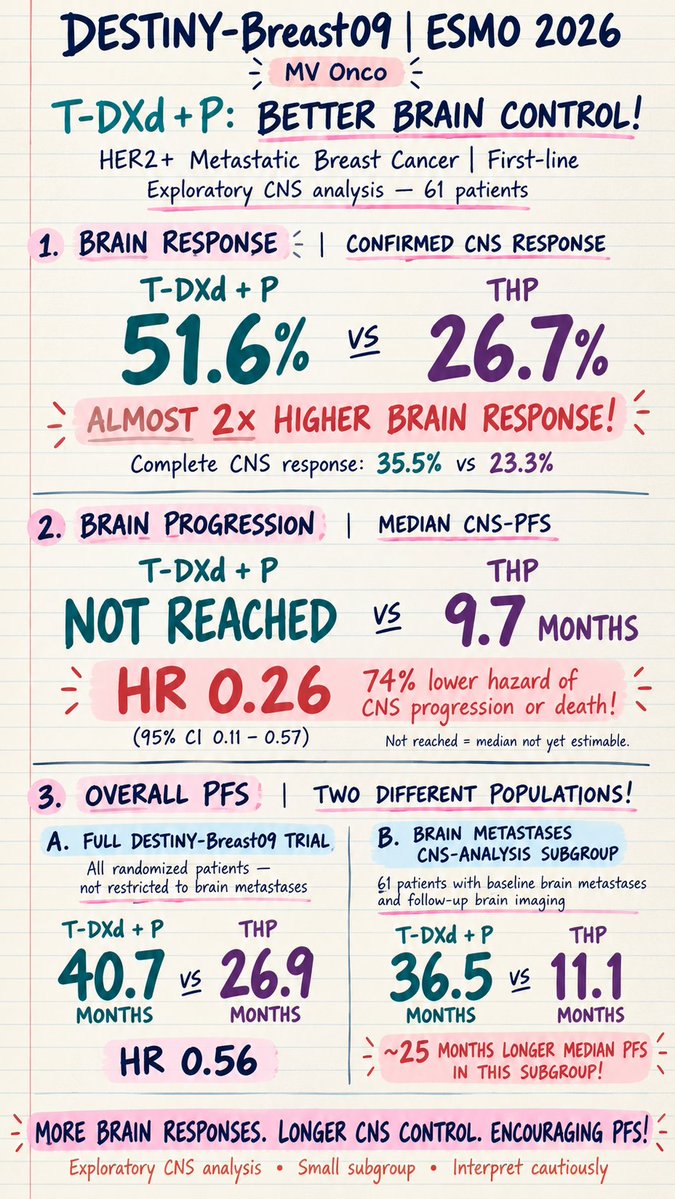
🧠 HER2+ Breast Cancer: What If Only the Brain Progresses?
BRIDGET | ESMO 2026 — Does Adding Tucatinib After Brain Radiation Help?
In patients with controlled extracranial disease, BRIDGET explored:
SRS → Continue HP + Add Tucatinib
📌 Phase II | 47 evaluable patients
• Historical median brain PFS benchmark: 5 months
• BRIDGET median brain PFS: Not reached (p<0.0001)
• 18-month brain PFS: 59%
• 18-month extracranial PFS: 98%
⚠️ Primary endpoint met, but no randomized HP-alone comparison.
Take-home: When only the brain progresses, treat locally, preserve effective HER2 therapy and consider adding tucatinib in selected TKI-naive patients.
Sammons et al. ESMO Open. 2026.
https://t.co/nsFWHkvtMS
@myESMO@OncoAlert@larvol #MVOnco #ESMO2026 #BreastCancer
#ESMO26 Management of mCRPC: Personalized treatment selection and sequencing @dmukherji@urotoday
Spectrum of PARPi sensitivity in mCRPC by HRR gene alteration
Evidence from PROfound, MAGNITUDE, TALAPRO-2, PROpel, and FDA pooled analysis
📈 Update on tarlatamab in 2L ES-SCLC from DeLLphi-305.
🧀 Small fraction of patients obtained long-term benefit as shown by 16% of patients w/o disease progression at 16 months.
✅ Better OS and tolerance compared to chemo, though. #ESMO26#LCSM
🚨 ASCO 2026: PARP inhibitors in ovarian cancer. What has changed?
The new ASCO Living Guideline, published in @JCO_ASCO, reviewed 31 pivotal trials and 13 HRD assays.
1️⃣ First-line maintenance: The preferred window for PARPi
🔹 SOLO-1: Olaparib established durable benefit in BRCA-mutated disease.
🔹 PRIMA / PRIME: Niraparib improved PFS, with the greatest benefit in HRD-positive disease.
🔹 ATHENA-MONO: Rucaparib demonstrated PFS benefit, particularly in HRD-positive tumors.
🔹 PAOLA-1: Olaparib + bevacizumab benefits patients with HRD-positive disease following platinum + bevacizumab.
2️⃣ Biomarker selection is critical
✅ BRCA-mutated or HRD-positive: Offer first-line PARPi maintenance after platinum response.
❌ BRCA-wild-type / HRD-negative: Not routinely recommended, despite modest PFS signals in PRIMA and ATHENA-MONO.
3️⃣ Recurrent ovarian cancer: A major restriction
🔹 SOLO-2 / NOVA / ARIEL3: PFS benefits established, but mature OS findings raised concerns in some subgroups.
➡️ Recurrent maintenance is now primarily reserved for PARPi-naïve, BRCA-mutated patients responding to platinum.
4️⃣ PARPi as treatment, not maintenance?
🔹 SOLO-3 / ARIEL4: Concerning OS findings altered the risk-benefit assessment.
❌ PARPi monotherapy is NOT recommended for treatment of recurrent ovarian cancer outside clinical trials.
5️⃣ What about PARPi rechallenge?
🔹 OReO / ENGOT-ov38: Modest PFS benefit, but insufficient evidence for routine PARPi rechallenge.
The clinical takeaway:
PARPi treatment is moving from broad use across multiple lines toward earlier, biomarker-selected maintenance.
The question is no longer simply “Is the patient platinum-sensitive?”
It is “BRCA? HRD? Prior PARPi exposure? Which line of therapy?”
@ASCO@myesmo@ESMO_open
#OvarianCancer #PARPi #ESMO26
Full paper link in comment below ⬇️
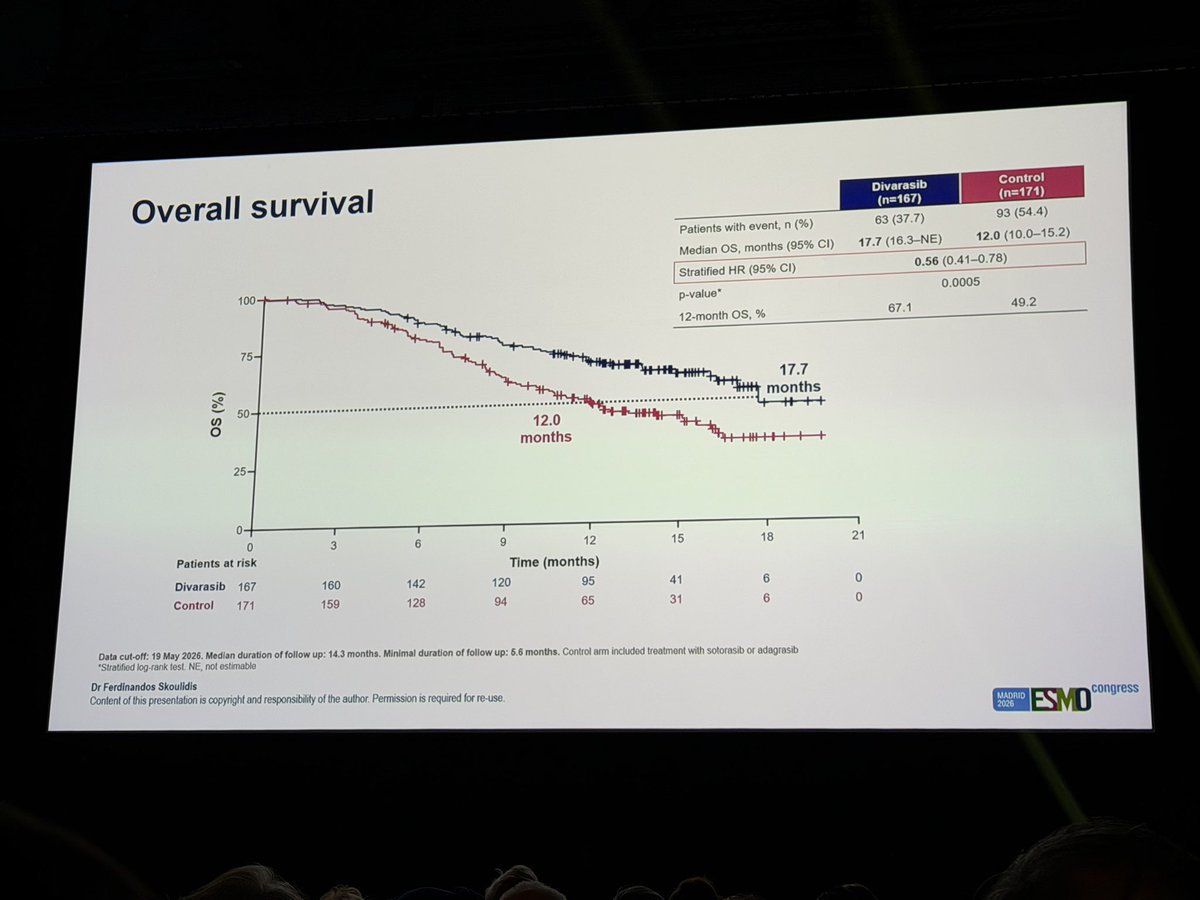
#ESMO26 | KRASCENDO-1
Divarasib delivering both PFS and OS benefits over existing KRAS G12C inhibitors is impressive. OS HR: 0.56!
A practice-changing trial.
One question: can divarasib work after sotorasib/adagrasib?
#ESMO26 | CLARITY-Gastric01
Doubling OS from 5 to 10 months with the CLDN18.2-targeted ADC sonesitatug vedotin in ≥3L is impressive (HR 0.47). Benefit even in patients with lower CLDN18.2 expression is encouraging.
However, the primary PFS endpoint was not met in the ITT population. Its role in 2L and efficacy after zolbetuximab remain unclear.
one question: Given that CLDN18.2 expression can change after treatment, should a fresh biopsy have been mandatory at study enrollment? Or does lowering the positivity cutoff to ≥25% reduce the clinical relevance of this discordance, making archival tissue sufficient?
#ESMO26 | BRIDGET
A clinically valuable study addressing a real treatment dilemma in HER2+ breast cancer. Adding tucatinib after local therapy for isolated brain progression achieved 18-month intracranial PFS of 59% and extracranial PFS of 98%.
Durable CNS control while maintaining an effective systemic regimen—a thoughtful strategy with compelling results. Congratulations to the investigators! @drsarahsam 👏
💊 Sotorasib and adagrasib were fundamental proof of concept drugs approved for a clear unmet need even none of them never demonstrated overall survival benefit.
🤯 Today those drugs are part of the past in oncology history.
Divarasib improve ORR, PFS and OS in previously treated KRAS G12C mutant NSCLC with a better safety profile in Krascendo1 Ph3 randomized clinical trial.
Kudos to @Roche to conduct a F2F trial.
#ESMO26 #LCSM
Impressive activity across MBC subtypes with the TOPO1, B7H3-targeted ADC SYS6043, with reasonable safety. Hard to interpret these results, though, given no prior TOPO1 ADCs receipt by any of the patients on trial. #ESMO26#ESMOAmbassadors
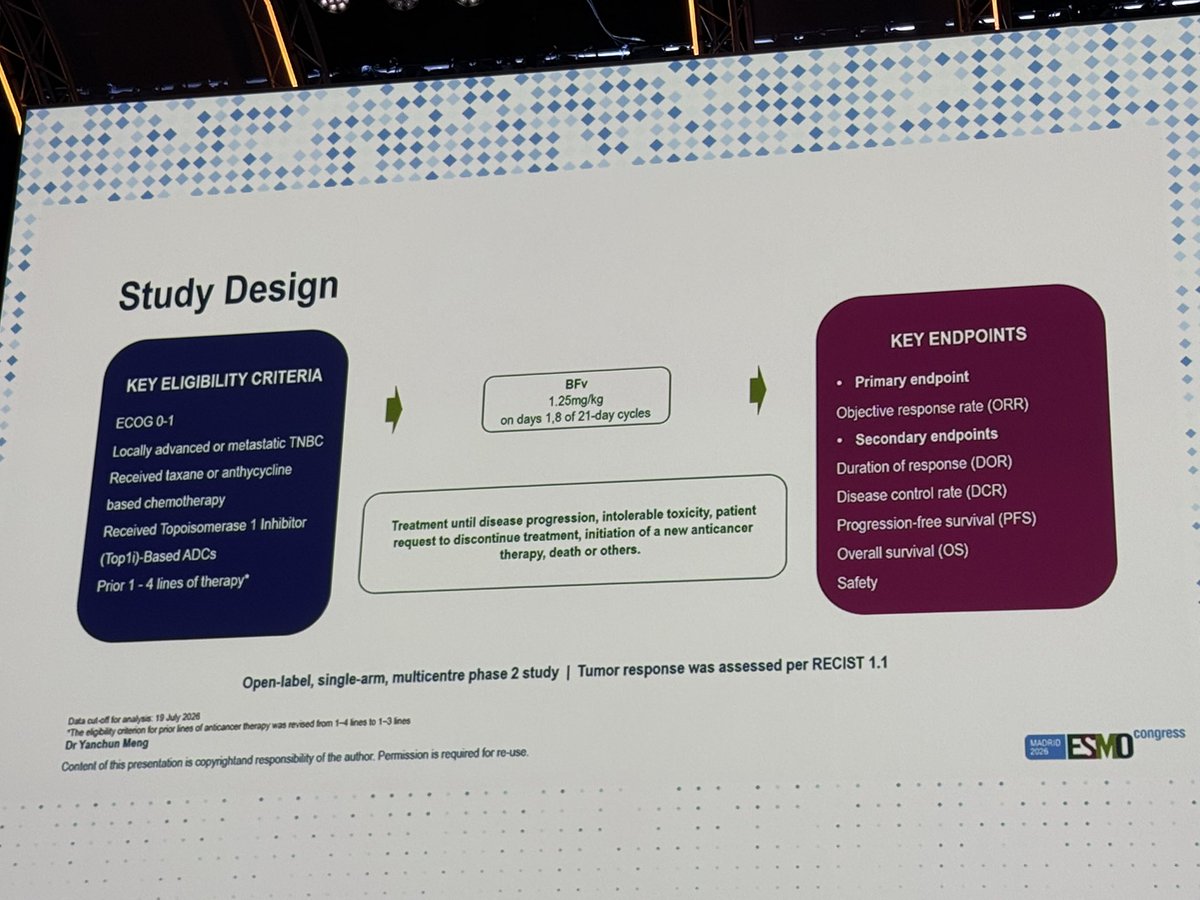
Switching ADC target does not work. Switching payload does.
Among 60 TOPO1-ADC-pretreated patients with MBC, using a microtubule (MMAE) ADC led to 30% ORR and DoR of 8.8 mo. #ESMO26#ESMOAmbassadors