How far should we pursue curative-intent treatment in de novo metastatic #NPC?
Delighted to have contributed to this newly published international consensus guideline @TheLancetOncol.
🧵1/5
📍Evidence gaps remain. Curative intent is not a promise of cure. Dedicated prospective trials are needed to refine patient selection and treatment choices.
Beyond “metastatic or not?”, we should ask: "could we offer this patient a realistic chance of long-term survival?"
🧵4/5
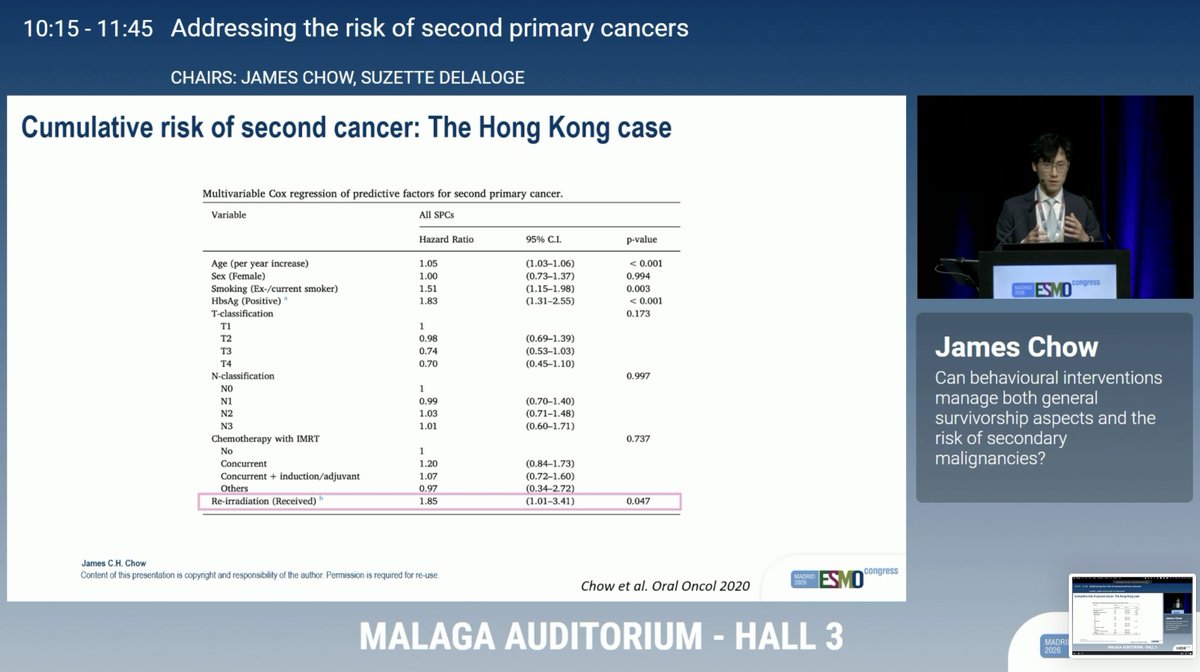
What a wonderful #ESMO26! Grateful to co-chair the Second Primary Cancer symposium with Dr. Suzette Delaloge.
As we celebrate remarkable breakthroughs in cancer treatment, we must also bring together evidence-based strategies to support survivors’ long-term health.
These are modeled benefits, not clinical outcomes—but they highlight a compelling theme: small refinements in contouring today could make a difference to patients' lives for years to come.
And that's what makes our work as #HNC radiation oncologists so rewarding!
🧵(3/3)
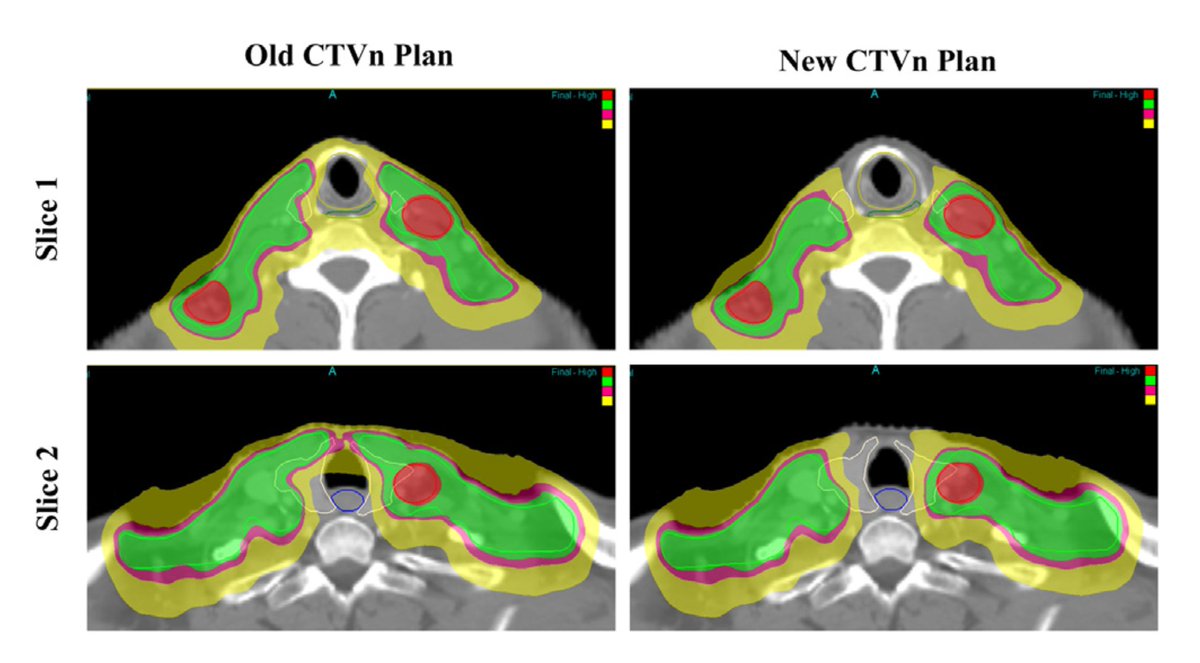
Recent international consensus efforts harmonized CTV delineation for #nasopharyngeal cancer.
One seemingly small refinement shifts the anterior border of level IVa to spare the space between #strap and #SCM.
But how much difference can one contour change make? ✏️
🧵(1/3)
We evaluated the dosimetric impact on the #thyroid in 30 patients with varying lower-neck LN patterns.
On average, this small CTV change resulted in a 9% absolute reduction in NTCP-predicted #hypothyroidism risk (20% RRR), while maintaining comparable PTV coverage.
🧵(2/3)
Just published: our review on pulmonary LCNEC - a rare but aggressive & heterogeneous entity.
We review current evidence across all disease stages and emerging strategies including molecular profiling and DLL3-targeted therapy. @jameschowch#LCNEC#LungCancer#Oncology
@ProtonStorey Thank you for this very nice article. It’s a pity to see how the primary endpoint/ design of phase III had to compromise. Concurrent chemo gives 5-6% gain in 5yEFS and has become SOC for advanced HNC. A 9% 3yPFS margin is simply too wide and clearly clinically inferior.
The 5-year follow-up results of phase 2 trial Xevinapant + CRT in LA-HNSCC in press: The risk of death halved in xevinapant vs placebo with HR 0.47. Phase 3 trial ongoing. @PBlanchardMD@GustaveRoussy@FAndreMD https://t.co/paYqZSpf2K
IT'S OUT:Our paper on elective nodal irradiation mitigates local and systemic immunity generated by combination radiation + immunotherapy in head and neck tumors. Link: https://t.co/ssDN5N5fyc
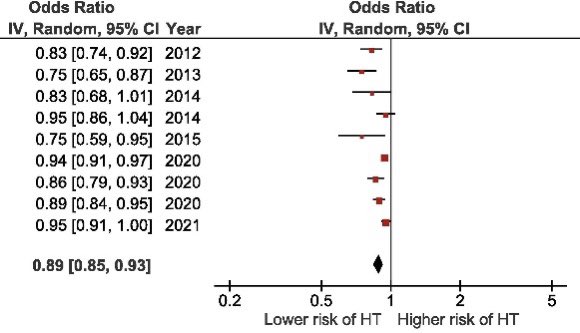
@StephenRameyMD @cd_fuller For every cc reduction in thyroid volume, the risk of post-RT hypothyroidism is estimated to increase by ~12%, such effect is independent of radiation dosimetry. These small glands tend to overlap significantly with nodal PTV in radical HNC plans esp with bil irradiation
Happy to share our external validation work on radiation DV constraints of the thyroid gland for #HNC out in the #greenjournal ☢️
While keeping VS60 above 10cc should limit 5-year primary hypothyroidism risk to <15%, ALARA remains the golden rule.🏅
#radonc#savethethyroid
@StephenRameyMD @cd_fuller We have reviewed all published thyroid constraints in the literature and most studies have shown that thyroid volume per se is a predictor for post-RT hypothyroidism independent of radiation dosimetry. Patients with small glands are inherently high-risk👇🏻
https://t.co/RkTWWCswpo