Hypokalemia + metabolic alkalosis + normal/low BP? 🧂
Think Bartter vs Gitelman syndrome.
Same biochemical pattern, but different nephron sites—and urinary Ca²⁺ + serum Mg²⁺ can quickly point you in the right direction.
A nephron-based comparison 👇
#NephTwitter#FOAMed
🔬 Precision dosing. Better decisions. Better transplant care.
An insightful session on using AUC to unravel pharmacological mysteries post-transplant at ISOT 2026, Hyderabad.#ISOT2026HYD
🔬 Unmasking the complexities of C4d-negative ABMR and MVI at ISOT 2026, Hyderabad. Looking forward to an engaging scientific session by Dr GEETIKA SINGH #ISOT2026HYD
Hello NephJC community,
NephJC is now over a dozen years old.
When we started, the idea was pretty simple: get a bunch of nephrologists together on Twitter, pick an important paper, and argue about it in public.
Somehow, that turned into something much bigger.
NephJC became a place where nephrologists, fellows, residents, students, researchers, and patients could come together to understand the research and manuscripts moving nephrology forward. We built detailed article summaries, visual abstracts, podcasts, book clubs, tweetorials, and an internship designed to train the next generation of medical educators.
And through all of it, we have tried to hold onto one basic principle:
The education should be free.
No subscriptions.
No passwords.
No paywalls.
And no pharmaceutical sponsorship.
Every year, big (and small) pharma offers to sponsor NephJC, or advertise at https://t.co/Dx1xhx0rd8, or place an ad in @FreelyFiltered. It would make running NephJC much easier.
We say no.
In fact, our bylaws prevent us from accepting pharmaceutical support. Why? Because NephJC exists to critically evaluate the medical literature, including papers studying drugs made by those same companies. We believe accepting any support would at the very least create the perception of a conflict even if our hearts stayed true (which of course they would).
That’s the hill we will die on.
But independence isn’t free.
Web hosting costs money. Podcasting costs money. Software costs money. Visual abstracts cost money. Running the NephJC Editorial Internship costs money. Keeping this entire unique experiment in post-publication peer review alive costs money.
Over the years, we have funded NephJC in a lot of different ways. In the beginning, we passed the hat among the NephJC workgroup. Satellite Healthcare (RIP😢) was an early supporter. @ArkanaLabs gave us a generous three-year unrestricted grant. The Flozinator Pin (https://t.co/OVKbdsAIEh) helped carry us through the pandemic.
But for the last five years we have a simple model: NephJC is supported by the people who use NephJC.
Wikipedia.
Public radio.
NephJC.
You don’t need to donate to read a NephJC summary. You don’t need to donate to download a visual abstract. You don’t need to donate to listen to Freely Filtered or Channel Your Enthusiasm. And we are never going to put those things behind a paywall.
But if NephJC has taught you something…
If one of our summaries helped you understand a paper…
If you’ve borrowed one of our visual abstracts for a lecture…
If you’ve listened to the Filtrate argue about a trial while driving to work…
If you’ve used NephJC to teach your fellows, residents, or students…
Then we’re asking you to help pay for it.
Not because you have to.
Because that’s how we keep it independent.
The alternative is easy. There is plenty of industry money available in nephrology.
We choose the harder path because we think independent, critical, open medical education is worth protecting.
If you agree, please support the 2026 NephJC Pledge Drive.
Open your wallet. Open your purse. Skip one fancy coffee. Or give enough to buy us the whole coffee shop.
Whatever makes sense for you.
Thousands of people use NephJC. We don’t need every one of them to give a lot.
We just need enough of them to give something.
Keep the FOAMed flowing. Support NephJC.
DONATE HERE: https://t.co/Tcn5vuV9ZK
Joel Topf
President, NephJC
#TheWeeklyNephron
Quality-oriented diet therapy for CKD
🥗 What if the kidney diet isn’t really about saying “no” to more foods?
This review makes a strong case for moving from nutrient-by-nutrient restriction to better overall diet quality
https://t.co/xPvzRNPdPW
🧵@DrAkshayaJ
Burnout is a pressing challenge in the high-stakes field of transplant medicine. Join Dr. Manish Malik at HITEX, Hyderabad as he shares strategies for sustaining long-term Work Life Balance in our demanding specialty. 🔗 https://t.co/5SNPggeAJL @IndiaSoTx
Therapeutic drug monitoring and AUC-guided dosing are crucial for individualizing immunosuppressant therapy and optimizing post-transplant outcomes. Join Dr. Pattanaik at HITEX, Hyderabad to explore these clinical tools. 🔗 https://t.co/5SNPggeAJL @IndiaSoTx#isot26hyd
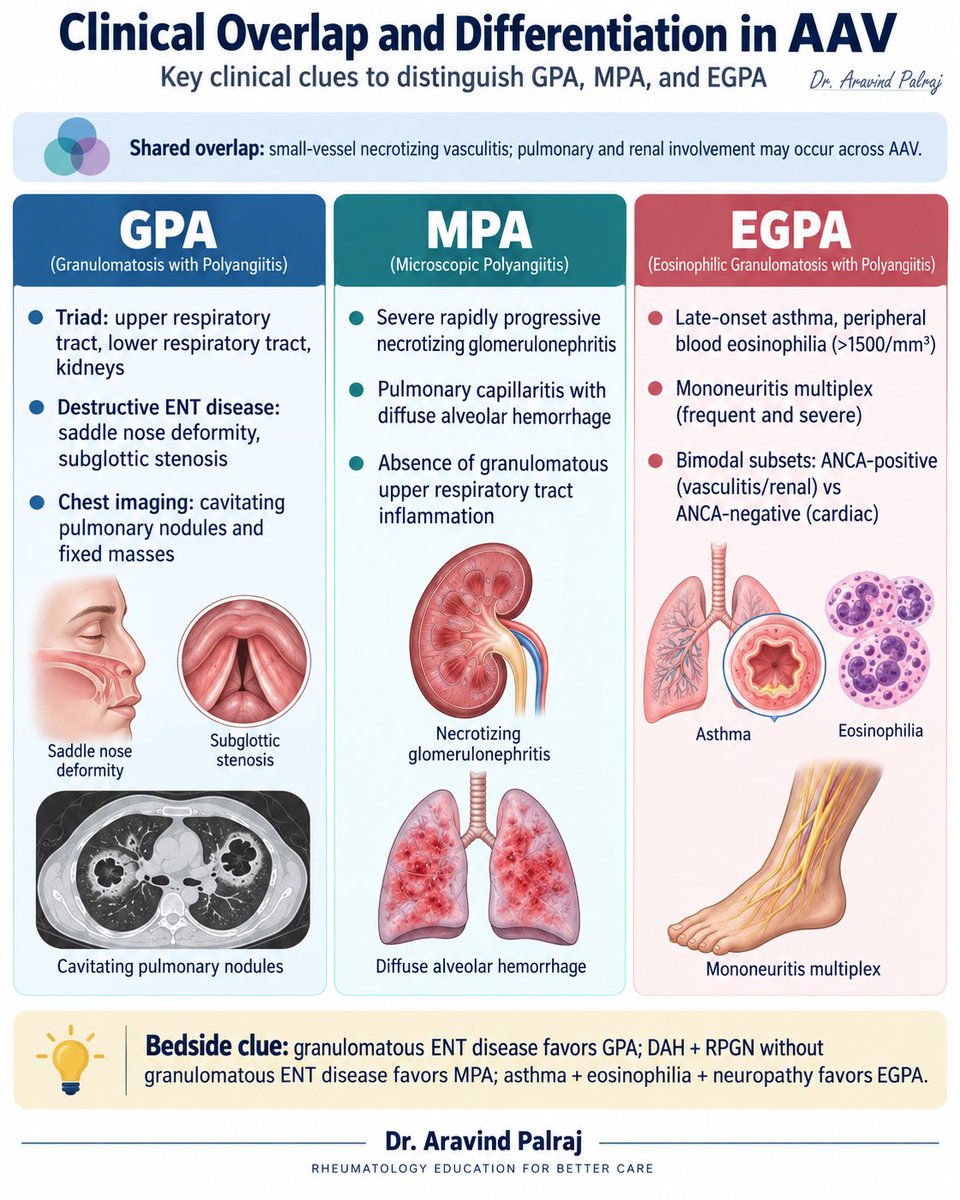
GPA, MPA, and EGPA can all present as ANCA-associated vasculitis—but the clinical phenotype often tells you where to look.
GPA → destructive ENT disease + pulmonary nodules/cavitation + GN
MPA → RPGN + pulmonary capillaritis/DAH, without granulomatous ENT disease
EGPA → asthma + eosinophilia + neuropathy; ANCA status often tracks phenotype
The overlap is real. The pattern is the clue.
#Vasculitis #Rheumatology #AAV #ANCA #MedEd @IhabFathiSulima@docakx
A Donor With Sepsis. A Life Waiting. Would You Say YES?
Explore the challenges, evidence and ethics of accepting organs from septic donors at ISOT 2026.
#ISOT2026 hyd
@ISNeducation Considering the patient has systemic evidence of TMA and serology is negative for lupus, do we still need a biopsy or should we start Plex immediately rather than delaying therapy for biopsy?
Which autoimmune disease will show systemic evidence of TMA other than lupus?
@ISNeducation In India, we do get CFHR1/CFHR3 mutation a doing genetics in TMA cases, how do you interpret it? Because theres some literature saying it can seen in normal population also.