Cardiologist @MidAmericaHeart, building programs to implement therapies, advance discovery, and foster innovation for patients suffering from heart disease.
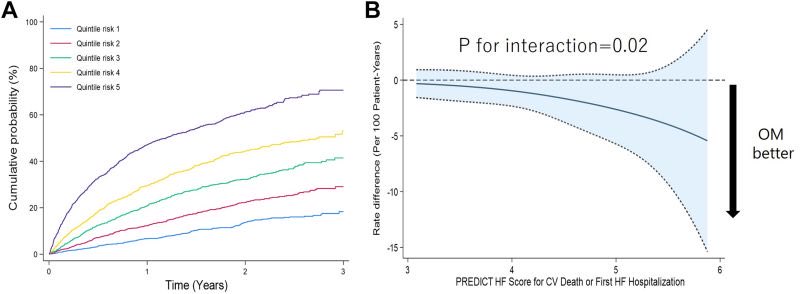
Now in @JACCJournals from #HFC members @DukeHFDoc@scottdsolomon, et al.
This analysis from GALACTIC-HF examines whether the treatment effect of omecamtiv mecarbil varies across baseline risk, defined by the PREDICT-HF score, in outpatients with HFrEF. https://t.co/MIJZwMAidn
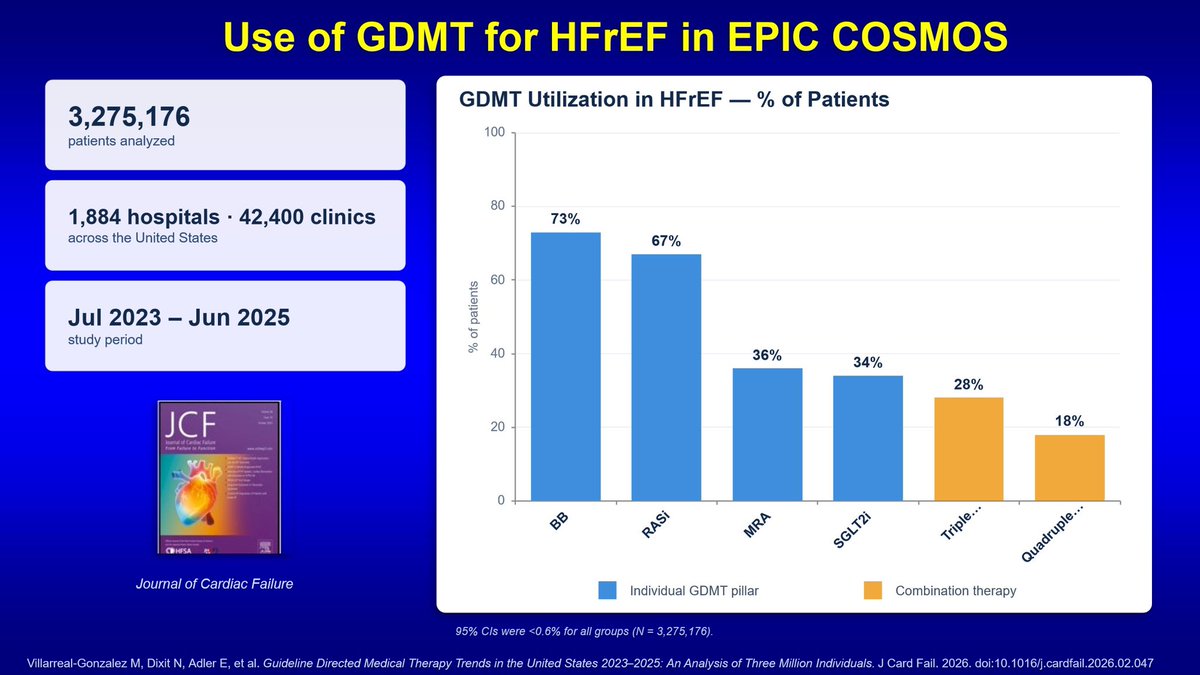
Patrick Mahomes turns 31 today.
• 3x Super Bowl Champ
• 3x Super Bowl MVP
• 2x MVP
• Offensive Player of the Year
• 2x 1st Team All-Pro
• 6x Pro Bowler
• Most Passing Yards in Chiefs History
• Most Passing TD in Chiefs History
This is absolutely insane.
Its like saying 1990s era chemotherapy / radiation for cancer is "good care" in 2026 --
We need to do better for patients suffering from heart failure.
@gcfmd@NMHheartdoc@SJGreene_md@DrMarthaGulati
Welles Crowther was a former Boston College lacrosse player who had a trademark red bandanna.
He was also working in New York on Sept. 11, 2001 when terrorists struck the World Trade Center.
This is the story of how he led people to safety on that fateful day 25 years ago.
Now in JACC: Heart Failure by #HFC member Javed Butler and colleagues.
This study evaluates hs-CRP and IL-6 as predictors of ASCVD and incident HF in adults with type 2 diabetes and overweight/obesity. https://t.co/KnH28iHFwV
Why do people with type 2 diabetes often lose less weight with GLP-1–based therapies?
My first paper as an @AstraZeneca employee uses mathematical modeling to suggest that GLP-1 induced glycemic improvements may reduce urinary glucose excretion and energy expenditure, partially offsetting negative energy balance—particularly with background SGLT2 inhibitor therapy.
Preprint: https://t.co/MwcAaeiwt0
Big news today…
@RyanJTedfordMD is officially back !!! Some are saying this is bigger than the NFL season being back in action. #FreeRyanTedford
What’s more important?
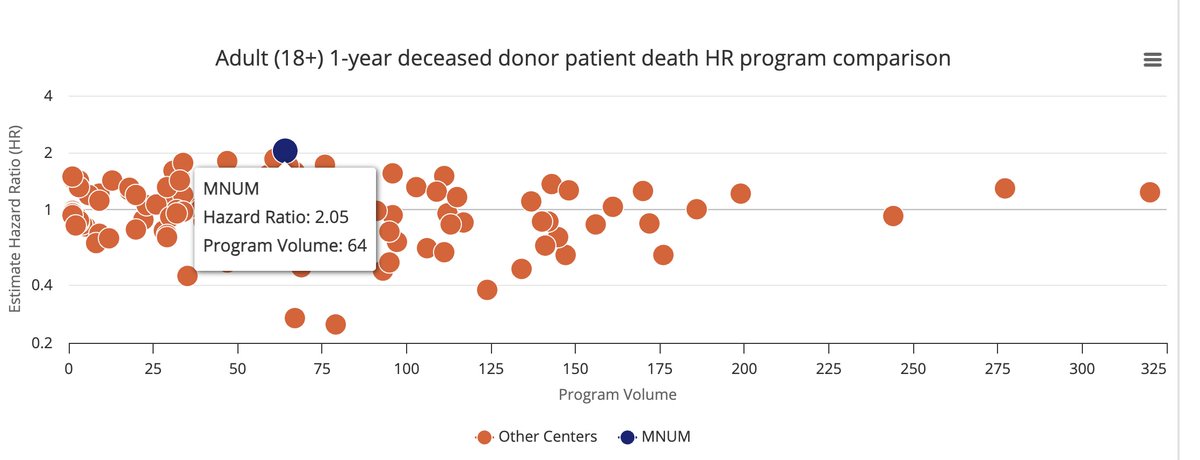
We are proud to have such great survival outcomes at @MidAmericaHeart and we also realize the opportunity to provide more care for more patients to increase access to transplant in Kansas City. @BrettSperryMD@MichaelNassifMD
July 2026 SRTR Heart Transplant Data:
Highest volume: Vanderbilt, Duke, Cedar's Sinai
Best 1-year survival? St Luke's Kansas City
Worst 1-year survival? Univ of Minnesota
🆕 New in OpenSource: Cardiology
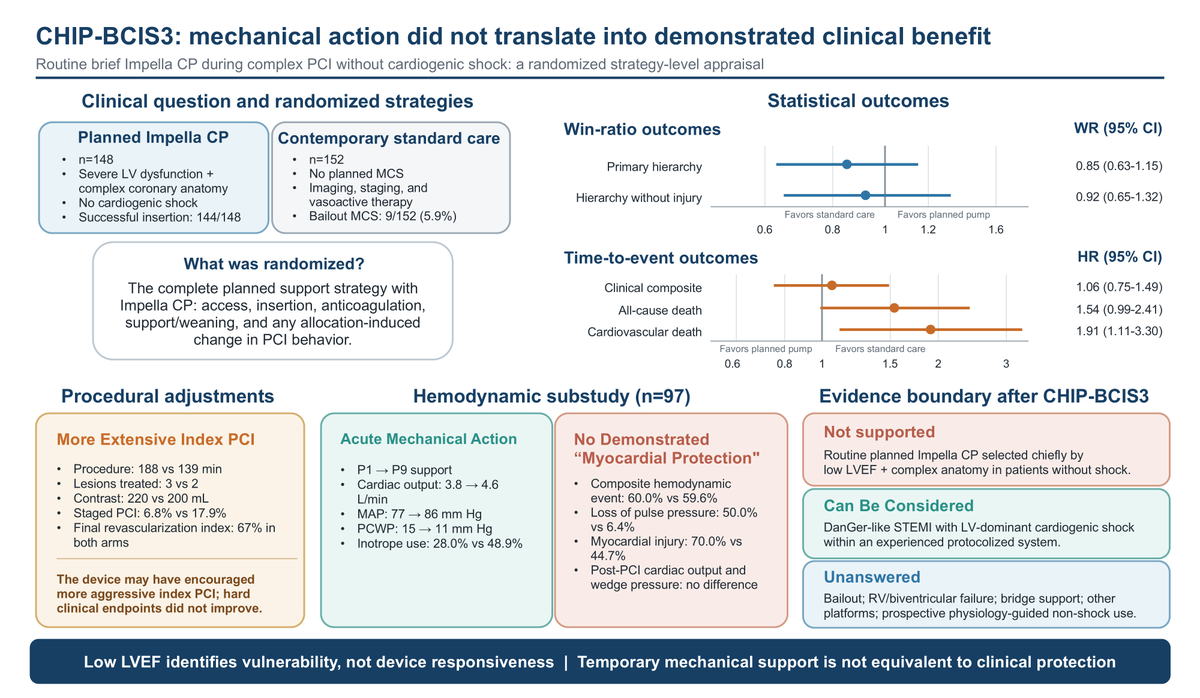
"Routine Microaxial-Flow-Pump Support During High-Risk PCI: A Critical Appraisal of CHIP-BCIS3"
@ihtanboga on the trial testing whether planned Impella CP protects patients during complex PCI without shock.
Mechanical action ≠ protection. 🧵
Read it free @opensourcecards - link below
Key ? in ongoing CKM development: how do you define a class?
Will all NuSH Rx be considered similarly? What about MR/aldo Rx?
Chemically spiro looks more like progesterone than it does finerenone
How can new molecules be tested in '26 on background of untested/unproven priors?
Well the answer is always “it depends” but the main lesson of the study I cited is you need to give enough to hit the threshold. So my general rule of thumb is I take the patients oral equivalent dose, convert to IV and double it. But it’s probably still too conservative. Checking urine sodium is another way to prove you’ve given enough but there are real practical barriers to doing that.
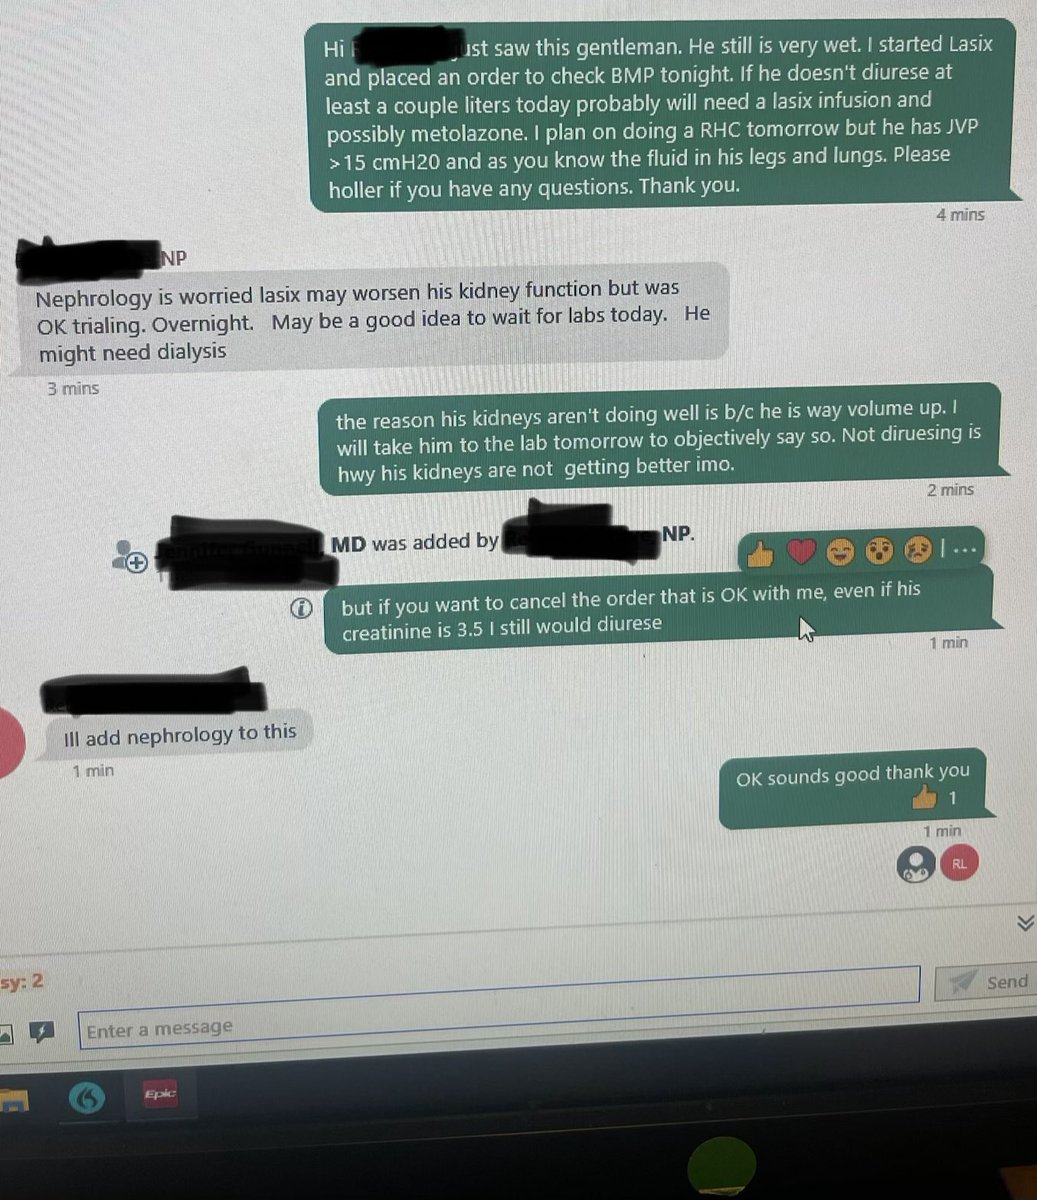
Loop diuretics are threshold drugs, not direct nephrotoxins. In congested HF, underdosing can be worse than aggressively getting above the natriuretic threshold. Testani and colleagues have prospectively tested 1,000 mg/day furosemide-equivalent loop dosing, producing substantially more diuresis and decongestion without a significant renal-function penalty.
https://t.co/BnVao4rTRY
You can load the kidneys with a gram of Lasix and still not hurt the kidneys directly. What hurts the kidneys is hemodynamic derangements like congestion or prerenal state plus other real nephrotoxins not loop diuretics
Loop diuretics are threshold drugs, not direct nephrotoxins. In congested HF, underdosing can be worse than aggressively getting above the natriuretic threshold. Testani and colleagues have prospectively tested 1,000 mg/day furosemide-equivalent loop dosing, producing substantially more diuresis and decongestion without a significant renal-function penalty.
https://t.co/BnVao4rTRY
You can load the kidneys with a gram of Lasix and still not hurt the kidneys directly. What hurts the kidneys is hemodynamic derangements like congestion or prerenal state plus other real nephrotoxins not loop diuretics
Tale as old as time. Lasix nephrotoxicity: the Bigfoot of inpatient medicine. Too many fear it. Nobody’s actually seen it.
Meanwhile the kidneys are drowning in venous congestion wondering why nobody will just give the F* Lasix. LASIX IS NOT NEPHROTOXIC. CIN doesn’t exist. @ASNKidney we need your help to say “Bigfoot” is just AI.
Loop diuretics are threshold drugs, not direct nephrotoxins. In congested HF, underdosing can be worse than aggressively getting above the natriuretic threshold. Testani and colleagues have prospectively tested 1,000 mg/day furosemide-equivalent loop dosing, producing substantially more diuresis and decongestion without a significant renal-function penalty.
https://t.co/BnVao4rTRY