@drbennisahmed 💊🫀 HFrEF GDMT saves lives, yet most patients never get all 4 pillars
Three recent studies point the same way: a polypill boosts adherence, gets more patients on full therapy and may improve outcomes
Time for bigger trials & real-world rollout
#HFrEF#CardioTwitter 🚀
Delivering Quadruple Therapy for Heart Failure With Reduced Ejection Fraction in a Customizable Polypill: The COMBO-HF-X Pilot Randomized Trial
4 pillars of HFrEF therapy in a single pill: a game changer?
The COMBO-HF-X pilot randomized trial, published in JACC: Heart Failure, explores a customizable polypill combining the 4 pillars of guideline-directed therapy.
🎯 A promising strategy to simplify treatment and improve adherence, but larger trials are needed.
#HeartFailure #HFrEF #Cardiology
@hfcollaboratory@gcfmd@SJGreene_md@BiykemB@mvaduganathan
https://t.co/YOBeRW0Bs8
🩺 Intensive vs standard BP:
9 RCTs, 65K patients
📉 Every HR <1 (0.73–0.90); pooled HR 0.82, 95% CI 0.78-0.87
🧮 Heterogeneity of treatment effect? None: I²=0%
🎯 Lower SBP ➡️ better outcomes in HTN, T2D and stroke
Implement!
@JCardFail@HFSA@dranulala@robmentz Needs a full-force response
Implement quadruple GDMT (ARNI/ACEi/ARB, BB, MRA, SGLT2i) for EVERY eligible patient in EVERY setting, whether inpatient, clinic or telehealth
🚀 Start early, titrate fast, close the gap
❤️ #GDMT#HeartFailure#Cardiology
@orion7710 File a formulary exception request with a supporting indication statement
Denied again? Appeal
Alternative:
Bayer US Patient Assistance Foundation: it provides free Bayer prescription medicines, including Finerenone, to eligible patients who cannot afford their medication
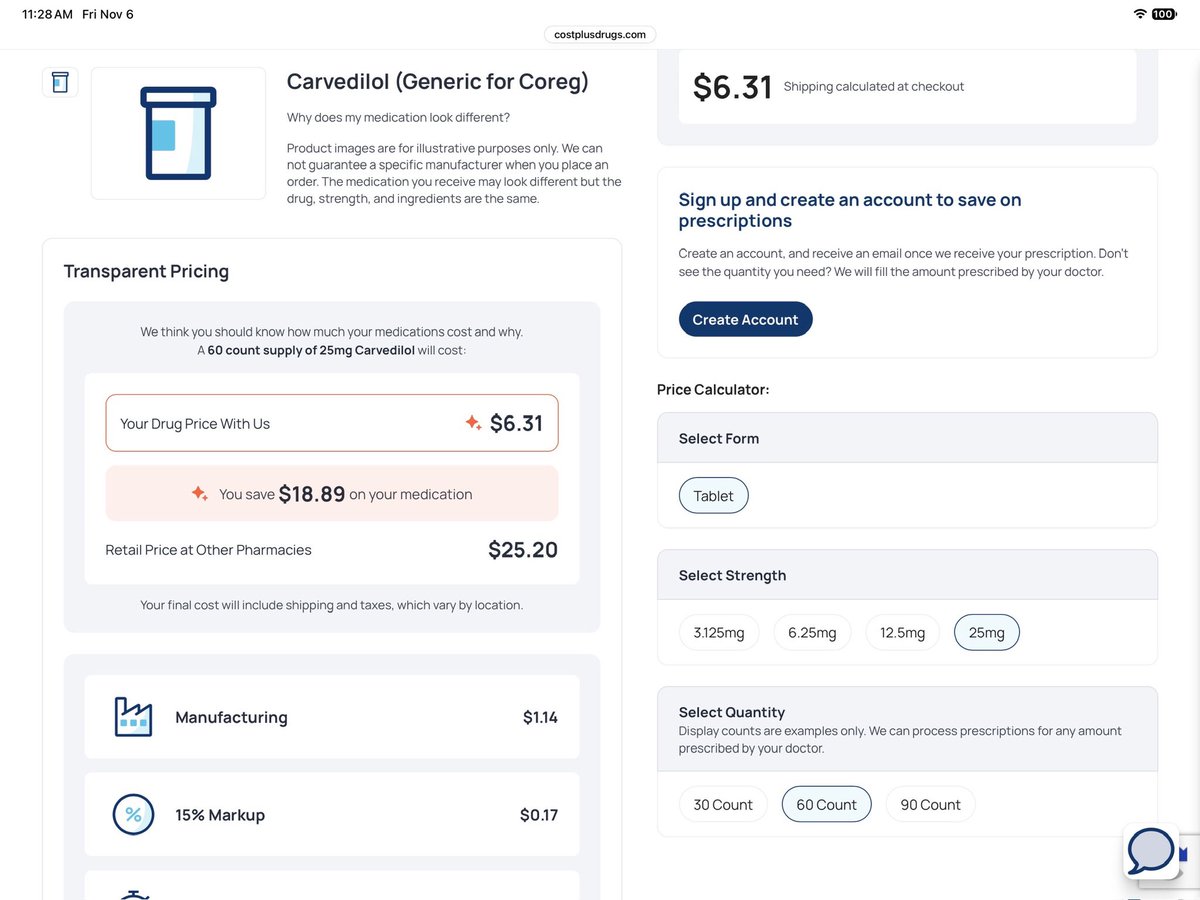
@AdityaMandawat@costplusdrugs@HFSA Incredibly easy steps to follow and very low total cost to get these spectacular clinical benefits for your eligible patients with HFrEF
Vaccination Is Heart Failure Care: Closing the Team-Based Delivery Gap
The ACC guidance establishes vaccination as part of cardiovascular care. Reliable delivery, however, depends on shared accountability across clinicians and settings. Heart failure specialty teams need not replace primary care; they are well positioned to complement it by recognizing vaccination gaps, serving as trusted messengers who connect immunization to cardiovascular risk, and ensuring that recommendations lead to on-site administration or a closed-loop referral.
@gcfmd@SJGreene_md@hfcollaboratory@DrMarthaGulati@Hragy
https://t.co/9QI4LO888Z
Vaccination Is Heart Failure Care: Closing the Team-Based Delivery Gap
“…interdisciplinary teams can turn evidence-based recommendations into documented completion and more reliable patient protection.”
https://t.co/GMg37CQBHb
@JCardFail@ACCinTouch@American_Heart@HFSA
@Heart_BMJ “These findings suggest that publication of updated clinical guidelines alone may be insufficient to ensure timely implementation for patients with established disease and highlight the need for systematic approaches to review treatment following major guideline changes.”
Dr. Karol Watson (@kewatson) highlights the results of the highly-anticipated Lp(a)HORIZON trial published in @NEJM and presented at #AHA26. Watch the full discussion with Dr. André Sofair and Dr. David Cohen (@djc795) for more key study results: https://t.co/O4nQaaWkTp
@drpablocorral The presence of nonoptimal levels of ≥1 traditional risk factor is nearly universal before CVD
These results challenge claims that CVD events frequently occur without antecedent major risk factors
https://t.co/LHcLcZV4Du
@drbennisahmed A model predicted the Lp(a)HORIZON results before topline:
pelacarsen HR 0.88 for MACE (95% PPI 0.86–0.90)
Actual trial results: HR 1.02 (0.90–1.15). 12.3% vs 12.1%
Narrow model intervals ≠ real uncertainty
Genetics ≠ 4.7 yrs of Lp(a) lowering after ASCVD
Cardiovascular-Kidney-Metabolic Overlap in Patients Hospitalized for Heart Failure
In this nationwide cohort of US patients with HF, HF in the absence of other CKM conditions was uncommon, and increasing CKM multimorbidity was associated with increasing clinical risk, especially in HF with reduced EF.
@gcfmd@SJGreene_md@DrMarthaGulati@ehj_ed@hfcollaboratory@mvaduganathan
https://t.co/gSLhtBdLMw
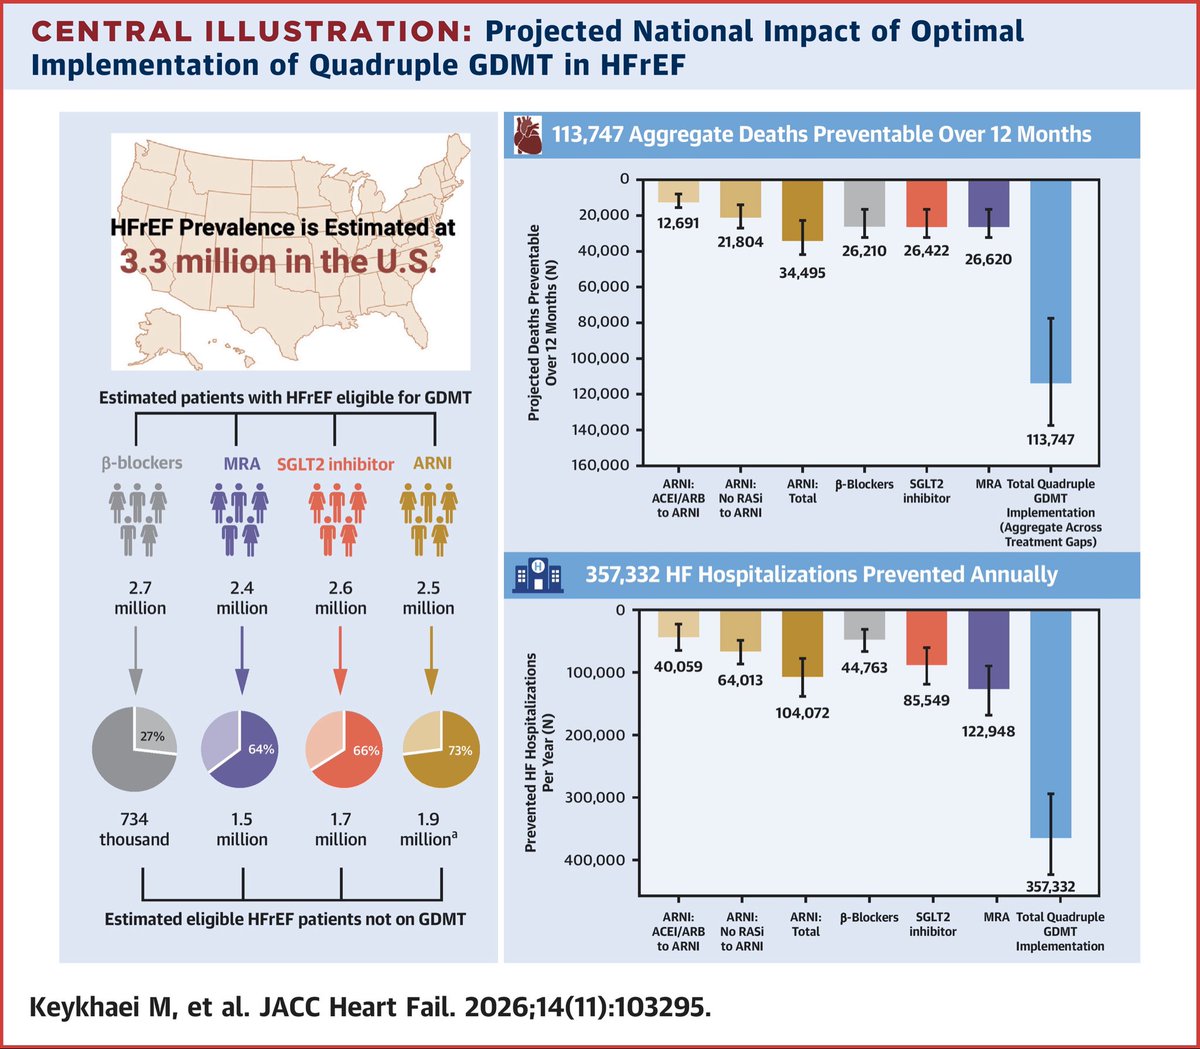
Only 18.2% of eligible US patients with #HFrEF receive all four foundational therapies (ARNI, beta-blocker, MRA and SGLT2 inhibitor).
A national study estimates that closing this gap could prevent 114,000 deaths and 357,000 #HeartFailure hospitalizations each year.
National Impact of Optimal Implementation of Guideline-Directed Medical Therapy in Heart Failure With Reduced Ejection Fraction
Incomplete implementation of quadruple GDMT in HFrEF remains a major modifiable opportunity to reduce preventable deaths and HF hospitalizations in the United States.
@JACCJournals@ACCinTouch@gcfmd@SJGreene_md@AndrewJSauer@HFSA
https://t.co/4nlD1fWXS2
✅ 4 drug classes cut HFrEF deaths: ARNI, BB, MRA, SGLT2i
❌ 30 others with great rationale failed in Phase 3 RCTs
🇺🇸 Only 18% get all 4 → ~114K US deaths preventable/yr
🎯 Implement GDMT with the same intensity we test new drugs
#HFrEF#CardioTwitter@HFSA@ACCinTouch