#AVCT
Morning guys
Please find in the below download link an AI generated podcast created by Google's new NotebookLM service wrt @avacta 's recent results & AVA6000 drug testing.
Worth a listen
@VOXmarkets@MylesMcNulty
https://t.co/eTTAHt36XW
#AVCT
Imagine a 60 year old male.
It could be you. Your husband. Your dad. The fun uncle you always loved seeing as a child.
In early 2021, he felt a lump behind his right knee. An ice pack didn’t help. Ibuprofen and physio exercises didn’t help. Finally he went to the doctor.
Biopsy.
Grade 3 undifferentiated pleomorphic sarcoma, a rare type of cancer.
Three months of radiotherapy followed by surgery. Viable tumour cells in under 10% of tumour volume - all seems well by September 2021.
By March 2022, he’s diagnosed with severe Stage 4 cancer which has spread to the membrane around his lungs.
By June 2022 options are running out, and he’s put on an early trial for a new combination therapy (Etigilimab + Nivolumab) for 6 months.
He has a 41% chance of grade 3+ treatment-emergent adverse effects which could be life threatening in themselves.
The disease continues to progress.
He then enrolls in the @avacta AVA6000 trial at the beginning of 2023.
Over the course of 11 months between February 2023 and January 2024, he has a near complete resolution of multiple metastatic lesions in the pleura (a -74% in the diameter of the lesions). See scans below.
During his time on AVA6000 (and last we heard he was still on drug 14 months later), his chances of developing neutropenia dropped by two-thirds compared to naked doxorubicin, and chances of febrile neutropenia dropped to 0%.
Importantly, quality of life has been greatly improved. AVA6000 boasts a 50% reduction in patients experiencing nausea, an over 50% reduction in patients experiencing decreased appetite, and the chances of experiencing pain or constipation decreasing 7 fold.
Bear in mind we are seeing this efficacy during a phase 1a safety and tolerability study.
Bear in mind this is only one patient - there are many others.
The data can only continue to get better.
In the near term, I suspect the precision platform will be linked to other drugs which are designed to have greater efficacy against other types of cancers for which doxorubicin is not the gold standard. This pipeline is due to be revealed by the end of the year.
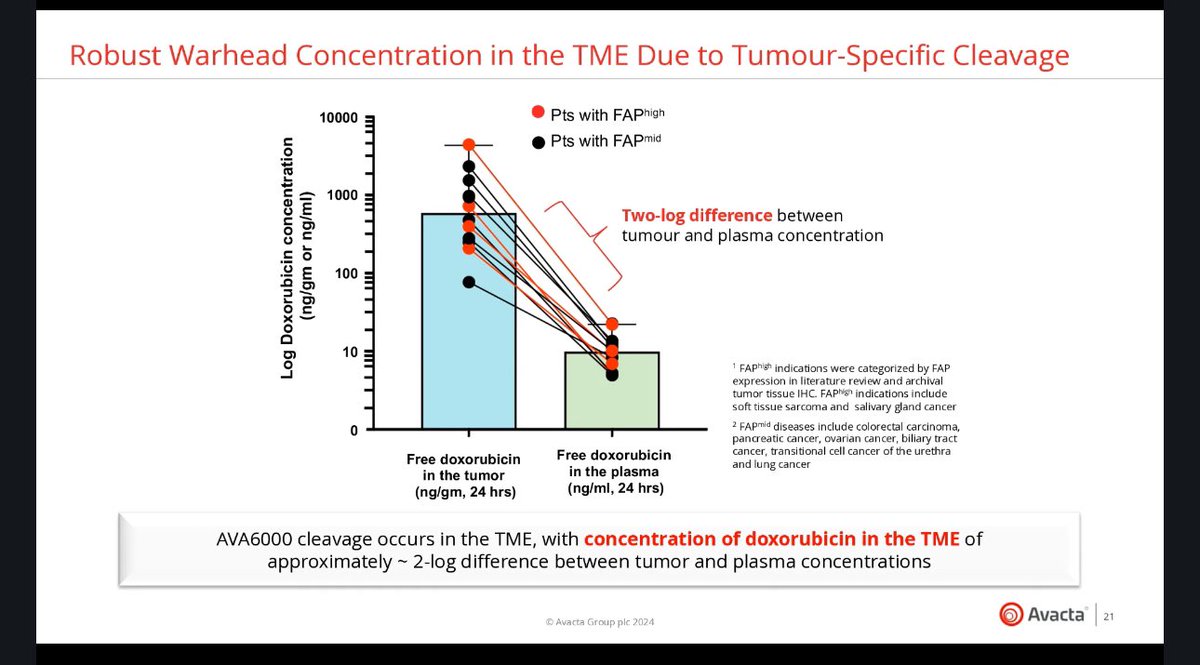
Are Avacta worried cancers such as pancreatic, colorectal and biliary tract are only FAPmid not FAPhigh? No chance. The attached graph shows the platform works just as well in both circumstances.
This is real world stuff affecting real people just like me and you - already making a huge difference to treatment outcomes as well as quality of life during treatment.
Would you want yourself or your loved one on AVA6000 as opposed to standard doxorubicin? I would.
I eagerly await the data from the 2-weekly dosing schedule which are to be presented at @myESMO before we move into the phase 1b expansion cohorts later in the year.
Thoughts welcome, let’s continue to strive for progress.
@annals_Oncology@OncoAlert@ACSNews@EORTC@brunolarvol@MakisMD@CD_AACR@DrChoueiri@vivekSubbiah@Liz_ORiordan@JTrentMDPhD@Alegronchi@herbloong@MBCadvocate@Winette_vdGraaf@pawel_sobczuk@theNCI@CR_UK@VriesElisabeth
@TimGreten @jsoriamd@PTarantinoMD
@ElenaGarralda @NCIEytanRuppin @NEJM@Cancer_cell@NatureCancer@RonDePinho@Simocristea@DCalleMD@breelynwilkyMD@DrLaraDavis@sarcomapatients@t0mclark3@barneycalman@rebeccasmt@andrewgregory@eleanorhayward@richardhorton1@BBCHughPym@HSJEditor@ShaunLintern@Nicktriggle@dennis_campbell@Kamranabbasi
SOFIE’s May 2024 presentation has a whole slide dedicated to their partnership with #AVCT@avacta
preCISON ‘can significantly benefit from FAP targeting diagnostics’.
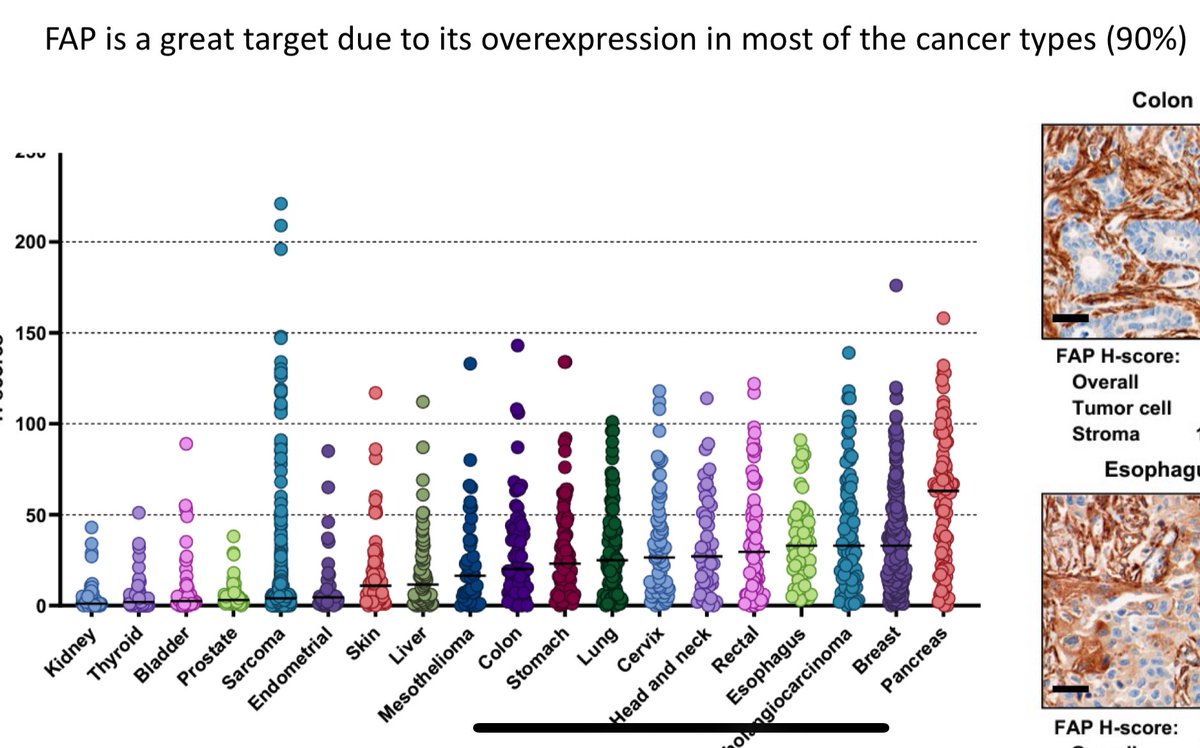
FAP is a great target due to its over expression in *most of the cancer types (90%)*
https://t.co/np9v9IuMqN
@sofiebio posted about their partnership with @avacta on their website. The news sits on their homepage.
https://t.co/lPEcQ6H0cy
https://t.co/9yyQiJgmp5
#AVCT
@Ophidian18 What would please me immensely would be if the board announced a trading halt today and reopened it in a couple of weeks time at a price of £1.75.
Wouldn’t it be a right laugh watching all the FUDders shitting themselves for a few days knowing that they’re gonna be toast!! 😃👍
Yesterday marked the day #AVCT started moves that will change the company. Today was just another couple pieces of a very big puzzle. The train has started and there is plenty more to come.
This morning’s #AVCT RNS was Andy Dufresne out of the sewer pipe and basking in the rain.
No shortage of information to unpack, which should not be a surprise given AVCT is sat on 25 months of detailed data.
Firstly, safety:
An “excellent safety profile continues to be observed in the sixth dose escalation cohort”
At 310mg of Dox, 209mg of AVA6000 equivalent (but targeted and therefore super charged) AVA6000 continues to be received safely.
That statement alone changes the landscape of Doxorubicin.
It can be dosed for longer, drastically expanding the number of people who can receive it, thereby enabling the efficacy of Doxorubicin to be utilised. It becomes the standard of care overnight.
Worth remembering Lartruvo hit sales of $562m per quarter (per quarter) before it was found to be no better than Doxorubicin alone.
We do not have that problem, AVA6000 is doxorubicin. The market continues to misunderstand this simple fact. This is the ‘small’ market we will initially target: $2Bn+ per year.
Next up, efficacy, a “significant reduction in tumour volume confirmed in a patient with soft tissue sarcoma”
A significant reduction in tumour volume. It is working. Let’s put to bed this absurd concept that AVCT may not have a working delivery platform. It works. And it’s unbelievably safe.
It’s also worth bearing in mind the criteria for inclusion in P1a. These are very sick (selfless) patients. To observe a halting of disease profession is one thing, to observe a significant reduction is something else.
I note AVCT explicitly did not choose to define the reaction in RECIST terms. Does a significant response equate to complete response? I suspect not, but I’m assuming they’re very close and patients in Cohort 6 are only 2-4 doses into trial. What will dose 5 and 6 deliver? We will know soon enough with detailed data being released in Q4. Again, I thought they would hold this back to AACR 2024 so a win.
Specifics aside, AVCT now has what pharma have been craving: efficacy. Partnerships will follow.
It’s also worth observing AVCT had authority to go to C7 (at 400mg). The fact they are not (and have selected 385mg) demonstrates they’ve finally found the sweet spot on the response Vs safety curve.
Next, the most significant statement to date (given we knew it was efficacious):
A “revised regulatory strategy aims to achieve earlier commencement of pivotal Phase 2 study in soft tissue sarcoma in 2024”
Avacta have turned their plan on its head.
The FDA - not the MHRA is now in the driving seat - which is fabulous news. They are remarkably quick. They know Tap. They know Lartruvo. They know Dox. An accelerate approval application is almost certainly coming. They want to expedite safe drugs. Side note: pulling that LFT a master stroke in the grand scheme of relationship with the FDA.
Crucially, this trial is no longer late. It’s ahead of schedule. Find me a Phase 2 clinical drug which is efficacious and shown zero reaction in share price over a 25 month period.
The muted reaction is of course the elephant in the room: funding. However, AVCT will have zero problem achieving funding. They will now have a plethora of options too: from licensing the pipeline to an exclusive placement with a serious II.
The SP is suggestive the open market will be invited to this funding event. It won’t be.
We’re therefore in a perverse position where I suspect a funding RNS will move the dial more than succeeding where pharma have failed for 50 years.
Even without funding, an SP sub ATHs is demonstrative the market still doesn’t get it. An SP below where it was before the trial began is quite frankly laughable.
AVCT will shortly be a phase 2 clinical trial company where the sums of its parts is lower than before this trail began.
Andy will be on the beach soon, mending boats with Red.
Well done to all SHs who kept the faith: an unwavering little community here. Most think we’re mad.
Then again, most would have sold keytruda for $1,000.
@tom_the_bomb__@Blueberrymgmnt Your patent cliffs expire
I have a platform
You want versatility
I provide wide utility
You want efficacy
I have 157 days of data from receptive STS patients at x2 mammoth doses plus 757 days of PK, biopsies and CT scans
Deal time
#AVCT
Tap is key.
Lartruvo (Olaratumab) was the first approved STS medicine in four decades.
That provides us with a pretty good insight into:
(1) how hard it has been to replace Dox as the SoC;
(2) how keen the FDA is to find a solution.
As we all know, Lartruvo was eventually withdrawn in 2019 (following P3 demonstrating no benefit in overall survival vs standard Dox).
As you allude, it was run by Tap. There is still debate over why and how it failed, making trial structure absolutely critical (and why AVCT want to ensure trial design for P1b is sound).
Having Tap on side is as good as it gets for AVCT from an experience perspective.
He has lived the regulatory process with Lartruvo. The FDA know him well. Any trial run by Tap is going to generate attention.
He’s the guy who stands up at ASCO/AACR and people listen to. The one the community look at when it comes to ‘teasing out efficacy signals’. That phrase alone (see below from ASCO) tells you how difficult it is to beat straight doxorubicin in STS; how difficult it is to demonstrate improved efficacy in STS. Not to mention safety.
What I think most don’t appreciate is the sheer scale of sales Lartruvo was demonstrating before it was withdrawn.
Following receipt of Accelerated Approval from the FDA, sales of Lartruvo totalled $562m in just 3 months.
$562m in three months.
What were the FDA signing off on?
A P2 study which dosed 64 patients with Olaratumab.
42 of the 64 saw disease progression. See flow chart below. This drug (and these results) was considered a breakthrough in STS.
Therefore, when we hear anecdotally from AVCT that a clinician such as Tap, regard AVA6000 and Dox as ‘night and day’ - take notice. He knows where the standard sits.
Our P1b (which may indeed grow beyond 48 patients, but let’s call it 48) is dosing 75% of the amount of patients which received Olaratumab in their P2 study. That was sufficient for the FDA to permit sales of the drug and indeed led to sales of $500m+ in one quarter.
The FDA took just 5.5 months from granting priority review to awarding the accelerated approval which enabled those sales.
If that’s the territory for just AVA6000, @avacta’s platform in preCISION is near impossible to value.
@AlbertMay59 Hi Albert, I couldn’t find how to DM you but could you add me to the new TA group pls? If you need anything from me just ask. Thanks I’m advance.
Picked up For Blood and Money by @nathanvardi on Saturday and have already finished it!
An incredible read, and highly recommended for biotech investors - particularly so for fellow shareholders in @avacta.
In its its pre | CISION platform, a drug delivery vehicle targeting the tumour micro-environment, #AVCT is sat on something truly special.
Safety and tolerability in the #AVA6000 Phase 1a trial have already obliterated expectations, owing to the exquisite specificity to FAP of the pre | CISION linker. The first indication of positive efficacy data could potentially now be mere weeks away. This is what the investment community (and to a lesser extent, Big Pharma) is waiting on.
Read For Blood and Money. It's amazingly helpful for the lay investor to understand what Avacta is up against, in developing its portfolio of oncology drugs.
It also helps one to appreciate just how large Avacta could become, in not only revolutionizing the chemotherapy market, but in successfully challenging the antibody-drug conjugate class.
Personal view? @avacta's share price sits in the foothills of the foothills of where it is ultimately going.
I assume a very conservative peak sales target (2030) for #AVA6000 of $4.5bn. That's a trebling of most existing forecasts for conventional dox, by that point in time, and assumes a 75% market share.
[One could quite easily argue for a quintupling of the $2bn conventional dox forecast market, and a 100% displacement of the old drug by 6K.]
I also assume a 75% CoS from now (in fact, as I wrote in my last note, six months ago - I think getting 6K to market now is procedural for #AVCT. A jumping-through-hoops exercise).
That's just one drug of possibly many dozens of anti-cancer drugs that #AVCT could develop with its pre CISION linker.
It is a direct, very real threat to the rapidly growing ADC class (which Morgan Stanley forecasts to reach $140bn+ per annum, within ten years).
......
The usual pond life are desperately trying to drag the SP down with their standard attack of, "Placing coming!"
My view is that @avacta will never approach the UK markets again to tap it for cash. The insider dealing is just too shocking, and the FCA too weak to do anything about it.
AVCT will instead seek out (and I believe, is already in the process of doing so) individual instos - or possibly players from Big Pharma (the obvious names being Novartis and/or Takeda) - to take an entire placing to themselves.
Shorts thinking they can close out by taking shares in an impending placing, or else using big volumes in the panic - will be delightfully screwed in such an instance. Truly looking forward to it!
......
There should be zero panic about @avacta right now. The share price is acting in the exact opposite way to how interest in preCISION is building across the pharma world.
The company has cash to last it over year if need be.
The risk / reward on offer now at 92p is just absurd. We could be seeing astonishing efficacy data in a handful of months, possibly sooner.
Yesterday, we touched the recent HCI bond conversion price. I suspect that was the bottom.