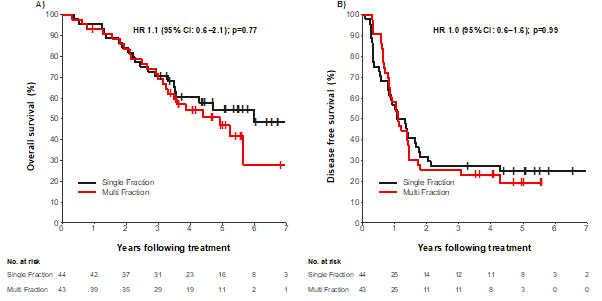
An optimal dose‐fractionation for stereotactic body radiotherapy in peripherally, centrally and ultracentrally located early‐stage non‐small lung cancer - Zarębska - Thoracic Cancer - Wiley Online Library https://t.co/NUB6jTs3yt
Neoadjuvant chemoRT with radiation dose escalation with contact x-ray #brachytherapy boost or external beam RT boost for organ preservation in early cT2-cT3 rectal adenocarcinoma (OPERA) published in @LancetGastroHep
👉Abstract in the #ESTROnewsletter https://t.co/G4qQRdr7Va
With new FIGO staging what it is the stage given for carcinosarcoma with cervical involvement and negative LVI ? @FIGOHQ@ESGO_society@IJGConline Could not find it in the new staging system 🤷♀️
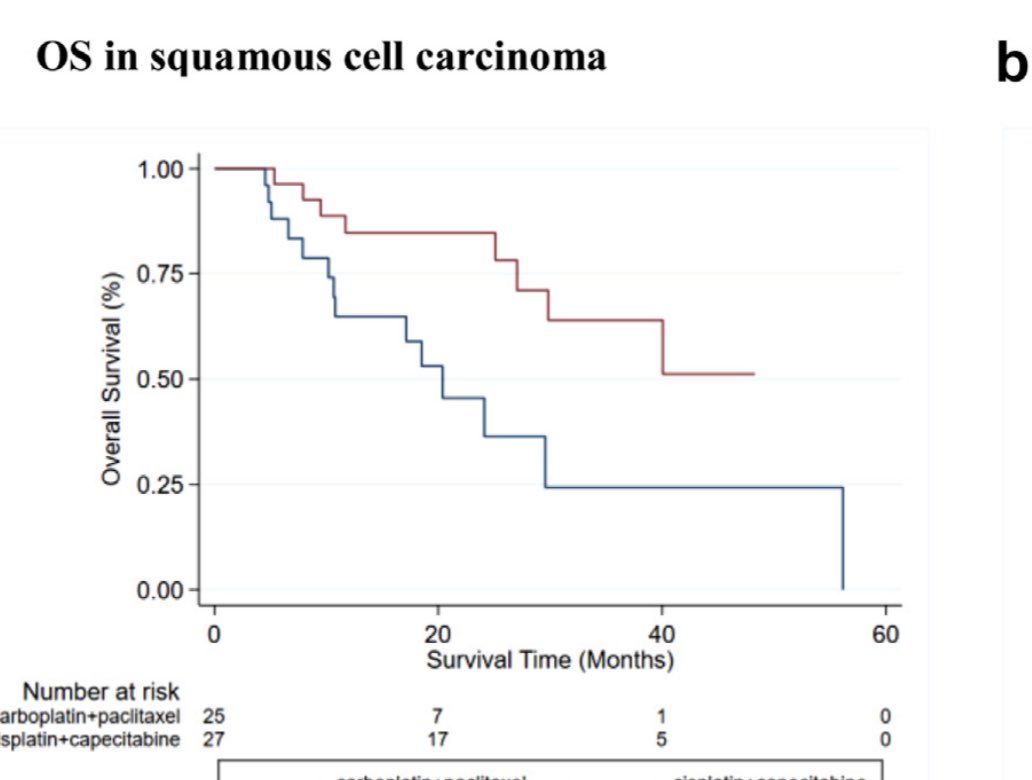
🔹randomized study on PET response based choice of Cis/Cap vs Carbo/Tax for ChemoRad in Esophageal Cancer
👉 Cis/Cap induction
👉 if SUV max ⬇️ less 35% rand. between Cis/Cap vs Carbo/Tax
❌ closed early for futility and potential harm
https://t.co/qghOkrnmW4
#radonc
Learn about localised, advanced, and metastatic #prostatecancer management, latest scientific evidence & future advancements. Engage in interactive case studies, journal clubs, & open discussions.
Early fee until 12 July, register for our course now!
ℹ https://t.co/OGy5cbZyND
🙏 Dr. Ik Jae Lee, Professor & Chair #radonc at #Yonsei University, for giving me the opportunity to visit the Heavy Ion Therapy Center in Seoull!! Seeing the synchrotron and 200 ton gantry were truly impressive! Looking forward to the outcomes from Yonsei using carbons 🇰🇷
Shifting to local control, @JoeChangMD shares data suggesting that SABR is equivalent to surgery with better toxicity in some early stage NSCLC patients. I-SABR may also reduce EFS as killed cancer cells may serve as in situ cancer vaccine. #DAVAHawaiiLung
Excellent reference. Mets <5cm 100 Gy BED advised, but for ultracentral metastases, or >5cm or with anti-cancer therapy, it may be lowered to >=75 Gy BED. Small, peripheral metastases consider 1 Fx SBRT. Lots more in this paper.
PRO: Do We Still Need Whole-Brain Irradiation for #BrainMetastases?
Prospectiv. trials comparing multiple SRSs with the modified HA-WBRT +/
SIB , are on the way and should help further define the optimal therapy for
this patients.
https://t.co/dbgoPqoi7h
#SRS#WBRT#radonc
@DrewMoghanaki@DoctorJSpicer@FordePatrick@NEJM SABR-COMET study @drdavidpalma was ph II RCT with highly sig OS benefit for SBRT to oligomets, more pts (99), same HR (0.47)
https://t.co/ojPjvgyRHc
@danielrgomez Ph II RCT of SBRT for oligomet NSCLC w/ HR of 0.46 for OS
https://t.co/Ub23CXhlEu
Both undoubtedly @nejm rejects=bias
Updated results from SAFRON-II will be presented this Sunday at #ESTRO23, once again demonstrating the value of single-fraction SBRT for oligomets (28 Gy x 1 versus 12 Gy x 4). #radonc@_ShankarSiva https://t.co/9Co5DTQwds
The @ASTRO_org -ESTRO guideline on oligometastatic #NSCLC will be presented at #ESTRO23 on Tuesday 16 May, at 10:15 (interdisciplinary track): https://t.co/R2fR4VLTAy
@IyengarPuneeth@Mat_Guc
TACE vs. SBRT for HCC: randomized phase II TRENDY trial
- stoped early due to poor a accrual
- all endpoints significantly or numerically better after SBRT
👉 time to progression 19 vs 12 mo
👉 median OS 44 vs 37 mo
👉2a local control 100% vs 44%
CONGRATS
https://t.co/XQt9uNqiIs