#EMUC26 wrapped up yesterday! In the closing session, Prof Thomas Zilli shared key takeaways on #RadOnc as a core pillar of #GUcancer care. 🎥
Watch below & stay tuned as we share more interviews this week! 👇@ZilliThomas
Renal GPA update in RCC with brain metastases (n=1,049; 21 institutions): median OS 20.0 months in patients treated 2016–2022, vs 9.6 and 12.0 months in legacy cohorts.
The updated Renal GPA stratifies median survival from 4.8 to 51.2 months. Retrospective data.
#KidneyCancer #RCC #GUOncology
Annals of Oncology - past and present: Editor-in-Chief @tompowles1 talks to the journal's founding Editor, Prof. Franco Cavalli, during the #ESMO2026 Congress
Now out in #JCO! 👇
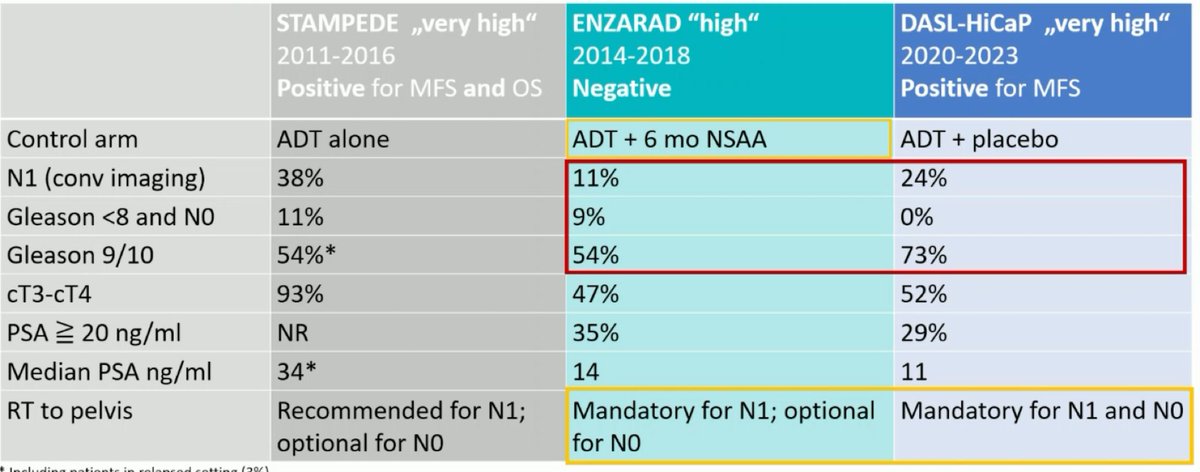
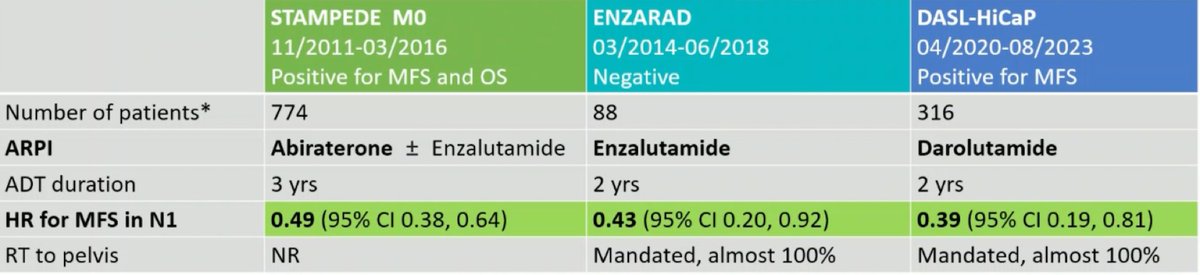
ENZARAD (ANZUP 1303): Phase 3 Trial of Enzalutamide with Androgen Deprivation Therapy and Radiation Therapy in High-Risk Localized or Locally Advanced Prostate Cancer.
Read the article. https://t.co/uLcI1sIUgp
#ProstateCancer#pcsm
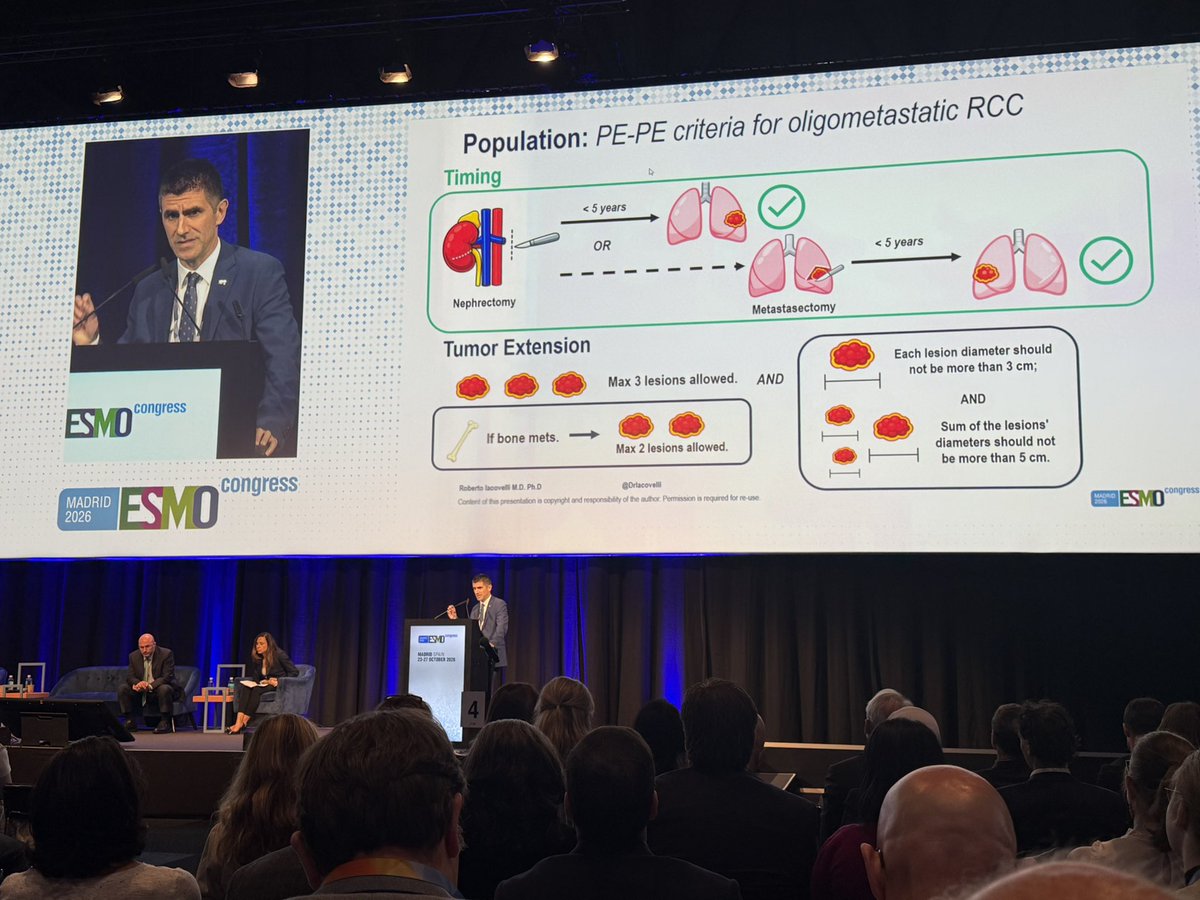
PE-PE population: a new concept for oligonetastatic definition in RCC. Thanks @DrIacovelli for bringing up!!! Something that we were assuming and using in the clinic is now confirmed. Pembrolizumab should be offer as “adjuvant” treatment for oligometastatic PE-PE+ ccRCC patients. My question is; : what is the value/contribution of giving 1 cicle before SBRT/surgery? @myESMO@OncoAlert
One year of APA+ADT comes with toxicity, and outcomes after control-arm salvage aren't shown. His view: follow-up too short; would not yet support perioperative APA+ADT with RP in high-risk disease, needing mature survival and post-salvage data first.
🚨 #ESMO26 | SARON: Better PFS, but NO overall survival benefit! @fifimcdrmh
presents the randomized phase II SAFRON trial in synchronous oligometastatic, driver-negative NSCLC.
📊 Median OS:
🔹 SACT alone: 28.0 months
🔹 SACT + consolidative RT: 31.0 months
🔹 HR 0.99 (95% CI 0.63–1.55), p=0.95
✅ Better disease control and longer PFS with RT.
❌ But NO OS benefit demonstrated!
An important reminder: improving PFS does not necessarily translate into longer survival.
Thought-provoking data challenging the routine use of consolidative RT in this setting!
#ESMOAmbassadors #ESMO26 #LungCancer #NSCLC
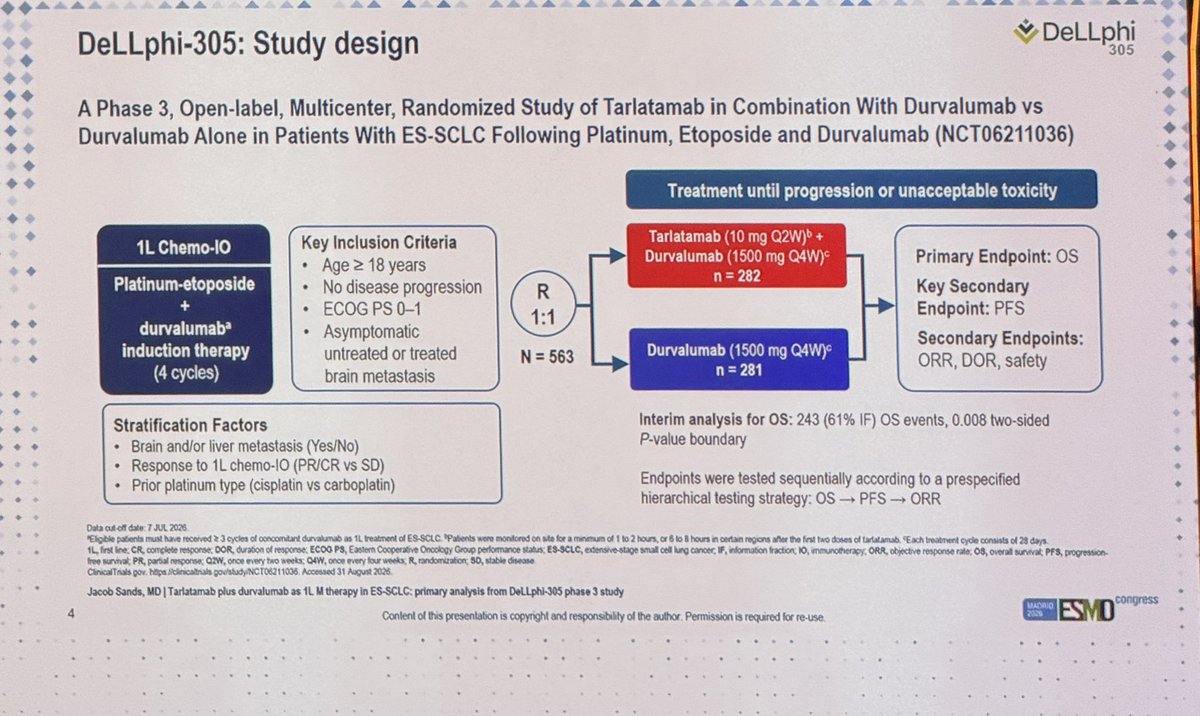
💥Game-changer in small cell #lungcancer! #ESMO26 LBA3 DeLLphi-305: Tarlatamab + durvalumab vs durvalumab 1L maintenance in ES-SCLC (n=563) after chemo-IO. Median OS ⬆️ 21.1 vs 12.7 mo (HR 0.42), PFS ⬆️7.4 vs 1.9 mo (HR 0.34), ORR 26% vs 4%. ☢️44% of pts still on T+D due to #radiotherapy of oligoprogressive sites? #SCLC #LCSM @NEJM ➡️ https://t.co/nhVH10CQZG
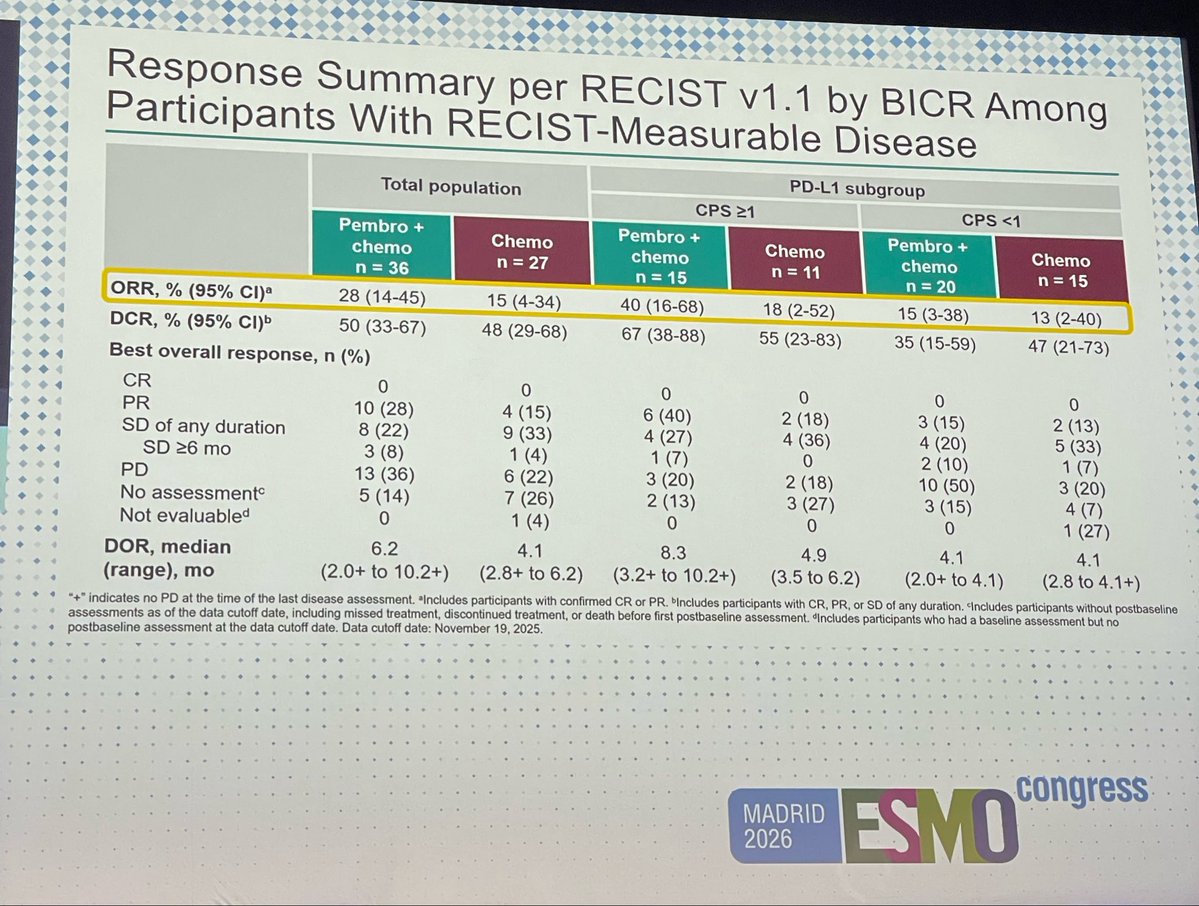
Encouraging OS results in neuroendocrine prostate cancer at #ESMO26!
#KEYNOTE-365 evaluated pembrolizumab + carboplatin/etoposide vs chemotherapy alone.
• mOS: 10.2 vs 7.1 months (HR 0.33)
• rPFS: 5.1 vs 4.0 months (HR 0.66)
• PD-L1 CPS ≥1: mOS 11.0 vs 4.8 months (HR 0.16)
No new safety signals observed.
@myESMO@oncoalert
With VOLGA results coming at #ESMO26, a summary of contemporary phase III perioperative trials in muscle-invasive bladder cancer.
⚠️ Different populations and designs—avoid cross-trial comparisons. VOLGA and EV-303 importantly include surgery-alone control arms without neoadjuvant therapy.
🔑 The next challenge: identifying who truly needs adjuvant ADC therapy—and who can safely avoid it.
#BladderCancer #GUOnc @OncoAlert@BladderCancerUS
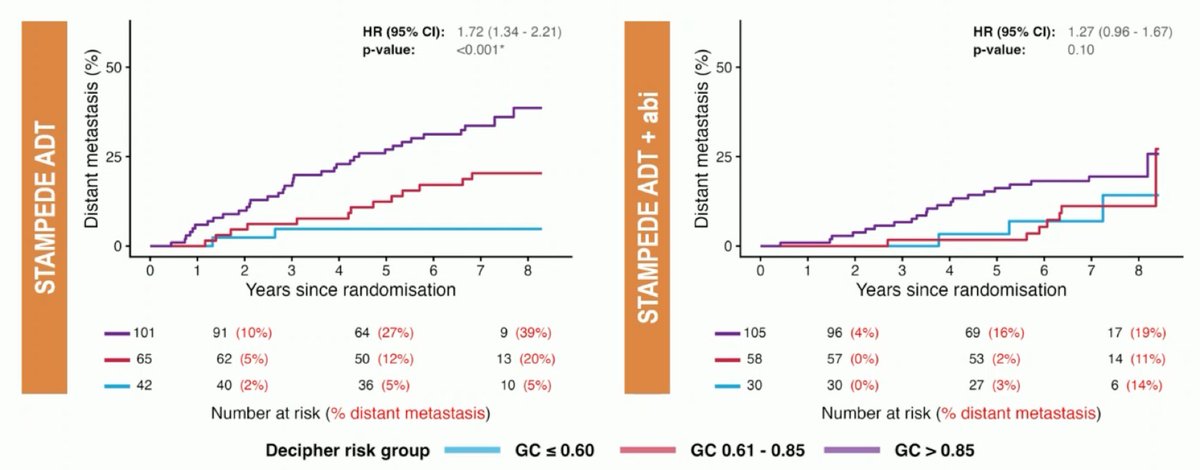
Transcriptome classifier risk strat and intensification with ARPIs for clinically VHR PCa @urotoday#ESMO26
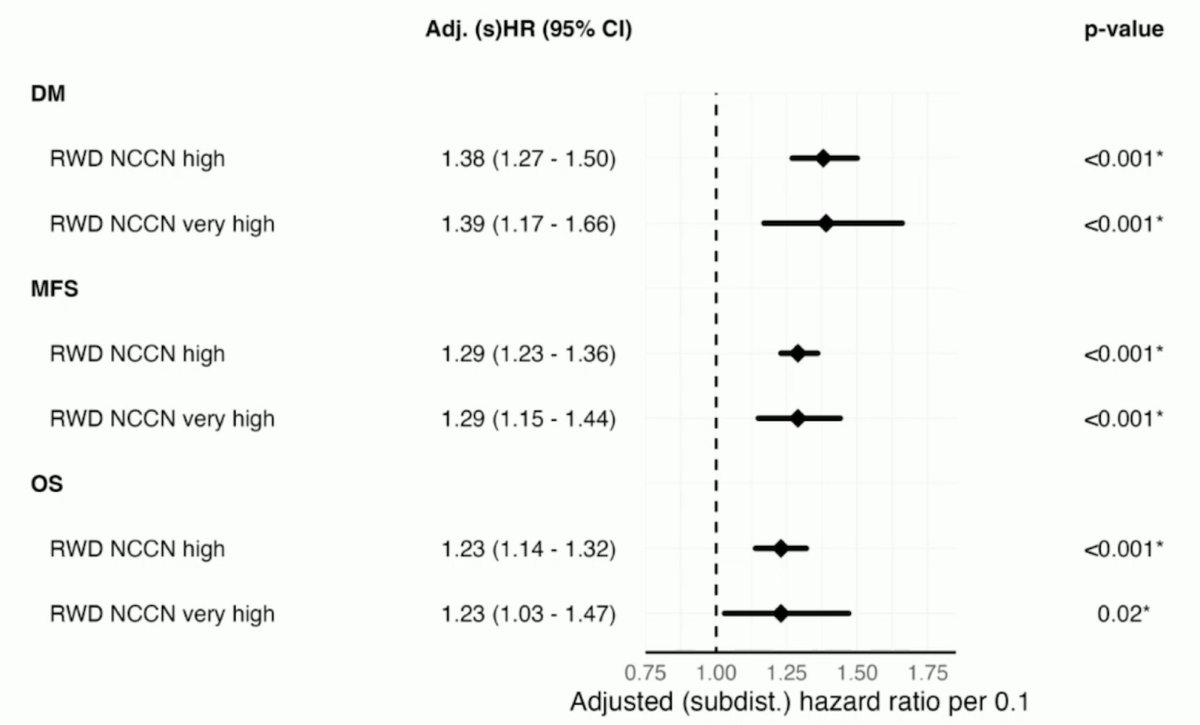
🚨STAMPEDE Abi trial (n=401); RWD cohort of NCCN high/very high risk PCa (n = 27,607)
🚨STAMPEDE - Decipher HR: ⏫DM, ⏬PCSS
🚨Decipher HR: Predictive of Abi benefit in STAMPEDE N0 pts (p-int: 0.01)
🚨Decipher: prognostic in RWD for DM, MFS, OS
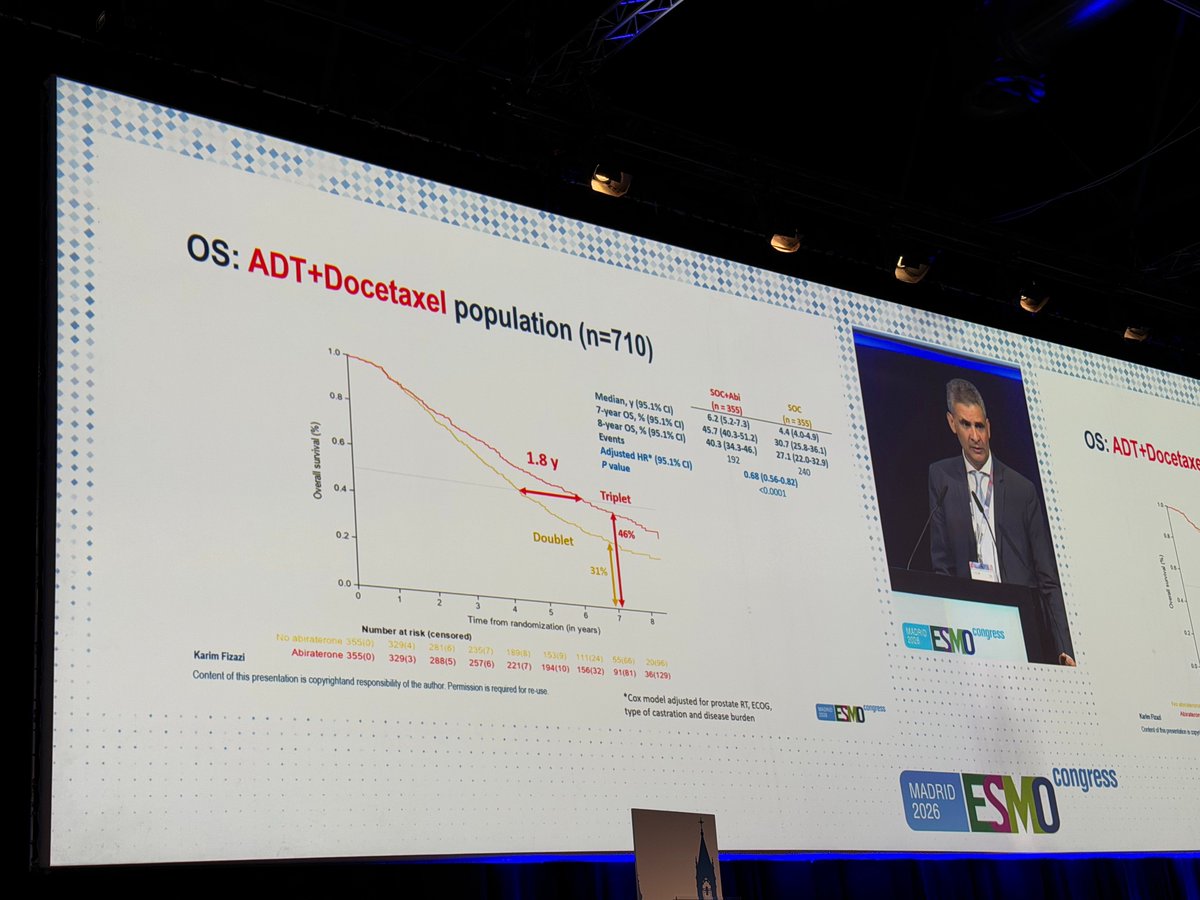
Fantastic presentation by Karim Fizazi! PEACE-1 at 7.7 years: adding abiraterone to ADT + docetaxel improved median OS to 6.2 vs 4.4 years (HR 0.68) in de novo mCSPC. Durable benefit from upfront intensification! @myESMO#ESMO26@oncoalert
ESMO 2026 - presidential LBA | VOLGA Phase III –
Perioperative Durvalumab + Enfortumab Vedotin (EV) in cisplatin-ineligible/refusing patients:
📊 EV + Durva vs Control
• 2-year EFS: 64% vs 45% (HR 0.51; p<0.0001)
• 2-year OS: 78% vs 69% (HR 0.58; p=0.0027)
• pCR: 45% vs 10%
Adding tremelimumab improved EFS (HR 0.61) but no significant OS benefit yet, with higher grade 3/4 toxicity (42% vs 30%).
🔥can this stop the need of post op EV ? Probably yes . New SOC 🙂👍
Looking forward the full datasets @OncBrothers@OncoAlert@myESMO
#ESMO26 #VOLGA #BladderCancer
🚨📣 big news at #ESMO26: 🧵1/MASTERPLAN RCT shows adding SABR to perioperative chemotherapy for high-risk localized #pancreatic cancer ⬆️⬆️ median overall survival to 22.0 months vs 14.0 months (HR 0.45). #PancreaticCancer#RadOnc@TROGfightcancer in press @TheLancetOncol - https://t.co/KhPO4dgZd4
It hard to explain why 1 trial with gem/cis +/-PD(L)1 (NIAGARA) is +ve for EFS/OS and 2 very similar trials (presented today) are negative in MIBC. Potentially NIAGARA has the highest risk population, not all respond to IO and the maintenance phase the most effect- but the OS of gem/cis pembro HR of 1 is concerning. This reflects what we saw in metastatic disease with contradictory results for the big combination trials. Overall EVP looks better and more consistent #ESMO26 @myESMO@Annals_Oncology@OncoAlert
⚡️ Phase 2 trial in RCC with inferior vena cava tumor thrombus: neoadjuvant stereotactic ablative radiotherapy (SAbR) followed by surgery (n=23).
1-year recurrence-free survival: 71.4% — above the 55.7% historical benchmark. Thrombus downstaging in 22%.
A promising approach for one of the most challenging complications in kidney cancer.
#KidneyCancer #RCC @JAMAOnc
https://t.co/hxqFmaqXGe