💬 Editorial by Kai-Uwe Eckardt, MD, and Mark Koury, MD: #SGLT2 inhibitors were developed for glycemic control but also consistently increase hemoglobin and hematocrit across patients with cardiovascular disease, heart failure, or chronic kidney disease, with or without diabetes. This additional effect may contribute to multimodal anemia management while accompanying the established cardiovascular and kidney benefits of this drug class.
https://t.co/QQ39GpMHsb
#KidneyWk @ASNKidney
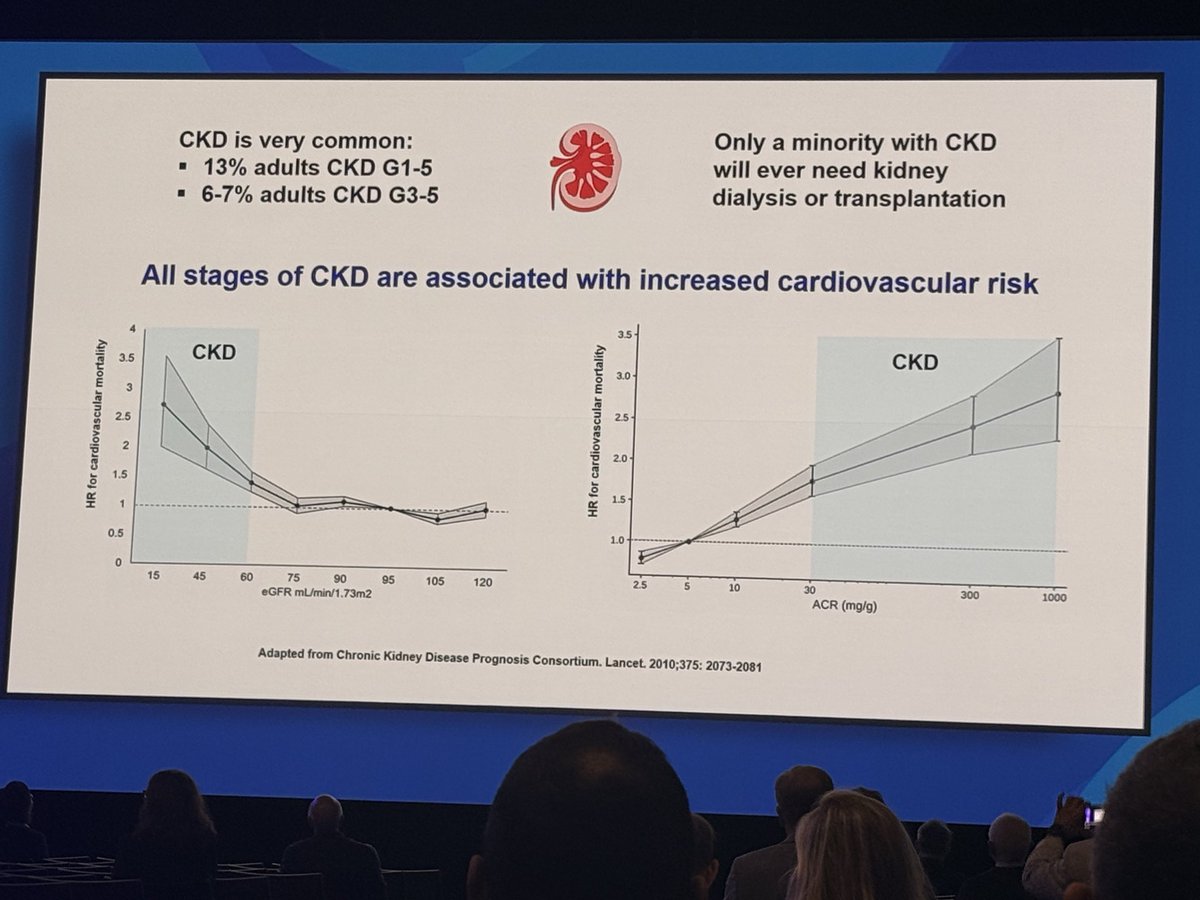
Yes. Competing outcome of death is monumentally higher than ESRD. This is why gfr slope reduction or other kidney enpoints for HTN/diabetes ckd misses the boat. Honestly, if you are a nephrologist, doing primary and secondary prevention for CVD through risk factor modification is way higher value than worrying about Hgb, product, or Vit D
Apparent resistant hypertension affected about 40% of people with CKD and type 2 dm in CONFIDENCE. Finerenone plus empagliflozin lowered BP more than either drug alone, on par with spironolactone but without its hyperkalemia burden. Now in JACC: Advances: https://t.co/0Ubo3xpu8m
💙 An inspiring start to #KidneyWk 2026!
Dr. Samir Parikh @samirparikhmd, ASN President, opens his Presidential Address with a powerful message about COURAGE.
A reminder of the courage it takes to lead, innovate, and advance kidney care. 🫘
#UTSWNephroly@UTSWInternalMed
Presented at #KidneyWk:
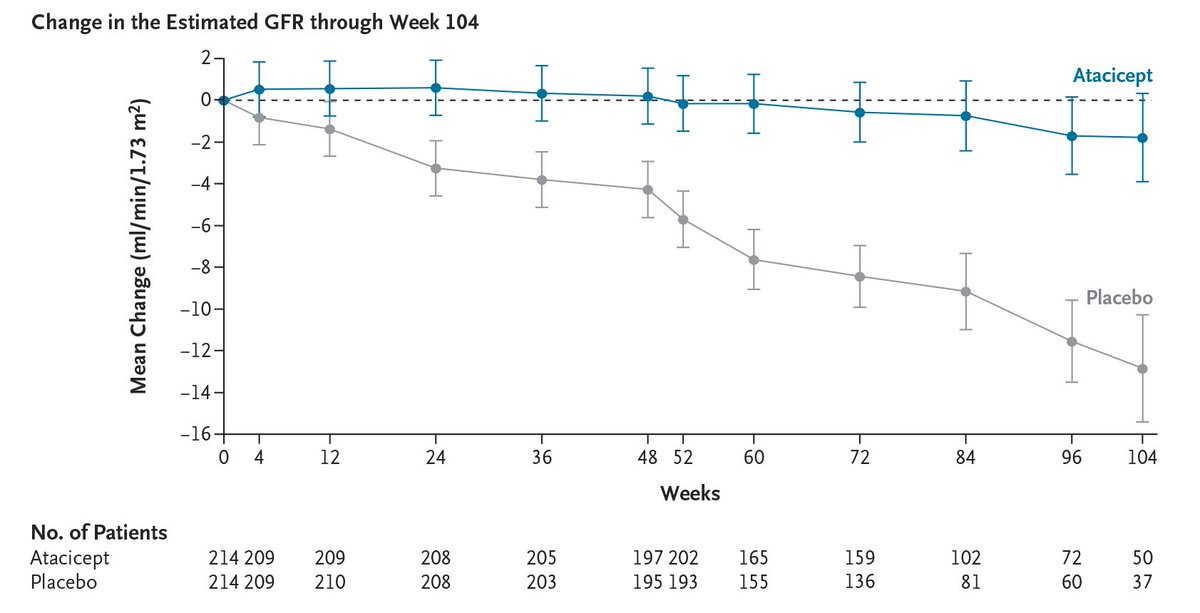
In patients with IgA nephropathy, atacicept, a human TACI–Fc fusion protein that modulates B-cell activity, slowed and stabilized the decline in the eGFR as compared with placebo. Full phase 3 ORIGIN 3 trial results: https://t.co/vNEvYf4Ao1
@ASNKidney
Presented at #KidneyWk:
In a phase 3, double-blind, randomized trial involving patients with IgA nephropathy, sibeprenlimab stabilized the eGFR slope over 24 months, consistent with a reduced risk of kidney-function decline. Full VISIONARY trial results: https://t.co/T8euA518cz
@ASNKidney
💙 An inspiring start to #KidneyWk 2026!
Dr. Samir Parikh @samirparikhmd, ASN President, opens his Presidential Address with a powerful message about COURAGE.
A reminder of the courage it takes to lead, innovate, and advance kidney care. 🫘
#UTSWNephroly@UTSWInternalMed
More data is good. And I appreciate intent of the article. Nelson Leung whos my friend and colleague (and writers the light chain cast nephropathy management section on UpToDate) is on the paper. My problem is the conclusion. Thats way behind and too confident for what a retrospective study can reveal and if physicians or patients actually take that to heart and implement or if insurance rejects approval can and will cause harm. The tweet that I saw promoted the conclusion. Thats what people see. Not the previous sentence that there was benefit in newly diagnosed.
I don’t remember the last time we plexed a patient with relapsed MM with cast nephropathy. It’s really uncommon to have that presentation in today’s Myeloma practice. I’m mainly concerned about newly diagnosed MM presenting with acute light chain cast nephropathy and there my message is crystal clear: plex first and ask questions later. Start dara VCd asap. In patient. Advocate for patients to have access even if hospital loses money.
Matthias Kretzler, MD, will receive the Homer W. Smith Award at #KidneyWk. Read more about contributions advancing precision medicine and kidney disease research in #ASNKidneyNews: https://t.co/TizVP0NEYe
Join us at #KidneyWk as physician, comedian, and health care advocate William Flanary, MD, receives the ASN President's Medal.
Read more in #ASNKidneyNews: https://t.co/JGTiIAtRSt
@@DGlaucomflecken
@VincentRK Thanks for your comments. However, I would like to highlight that there are very few patients in practice that receive both Dara and plex - mayo is unique that way.
The target trials were separate and were intended to look at each treatment individually, not together.