

Top Tweets for #PdPh

Dural puncture → EBP. 11 days later, labor DPE = rapid, effective, no PDPH return. Bottom line: Epidural/CSE/DPE remain options soon after EBP. https://t.co/DUTLrHH4oE #Anesthesia #MedTwitter #PDPH #Epidural #OBAnes #FOAMed #ObGyn

After accidental dural puncture and EBP, a laboring patient received DPE 11 days later—rapid, effective analgesia, no return of PDPH. What this means for neuraxial choices in labor: https://t.co/DUTLrHH4oE #Anesthesia #Epidural #DPE #PDPH #MedTwitter #ObGyn


Images in #Anesthesiology - Air Entrainment and Subsequent Pneumocephalus Associated with Epidural Blood Patch 📷 https://t.co/hUYKes0EDs
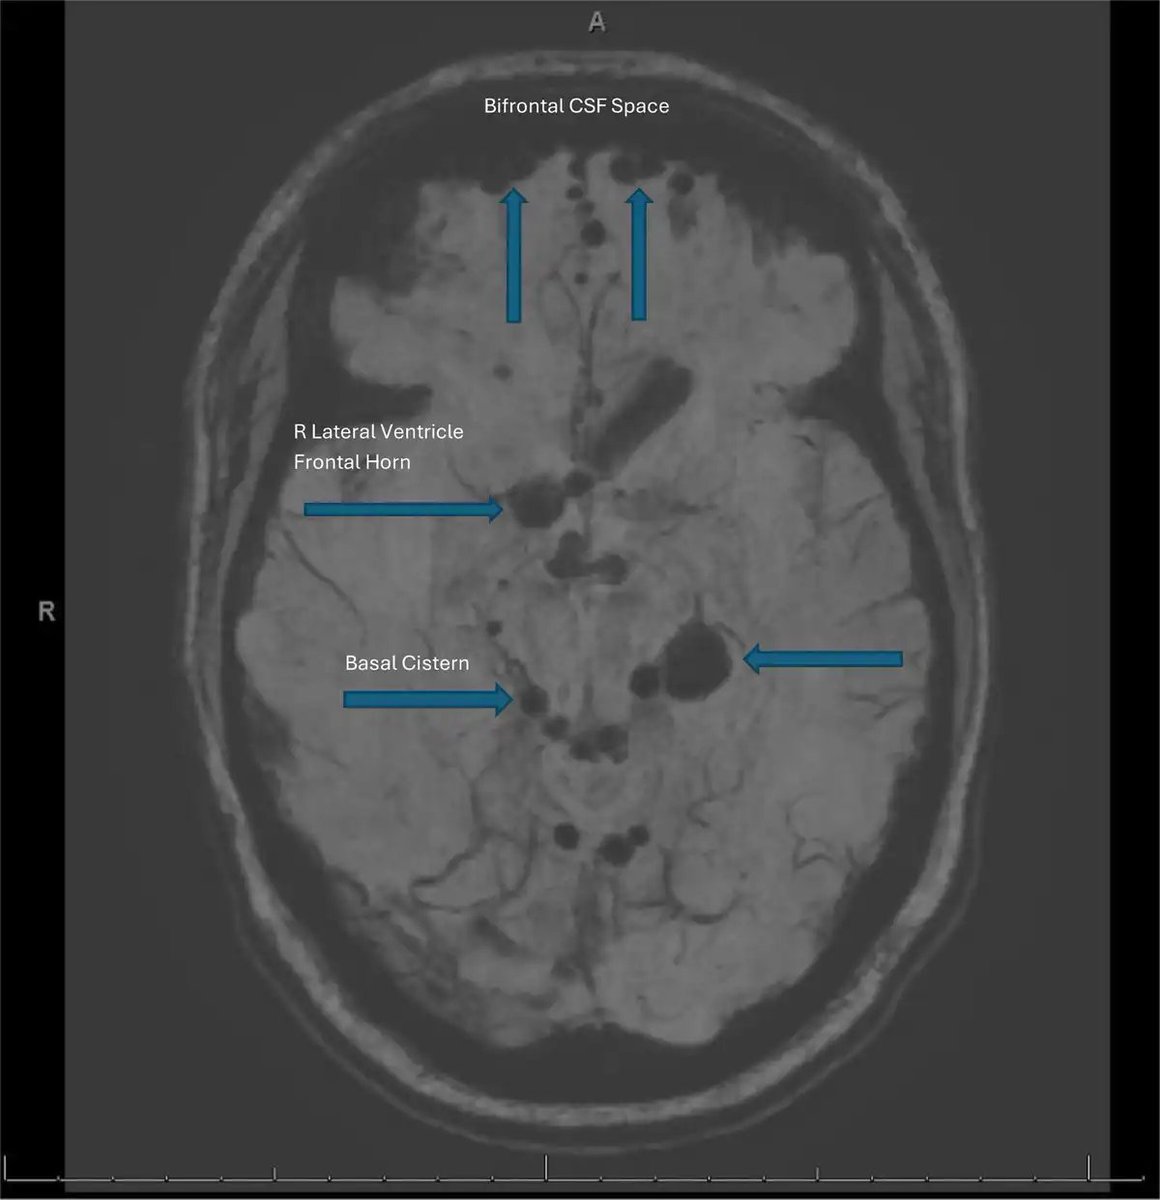
Dural puncture → EBP. 11 days later, labor DPE = rapid, effective, no PDPH return. Bottom line: Epidural/CSE/DPE remain options soon after EBP. https://t.co/DUTLrHH4oE #Anesthesia #MedTwitter #PDPH #Epidural #OBAnes #FOAMed #ObGyn


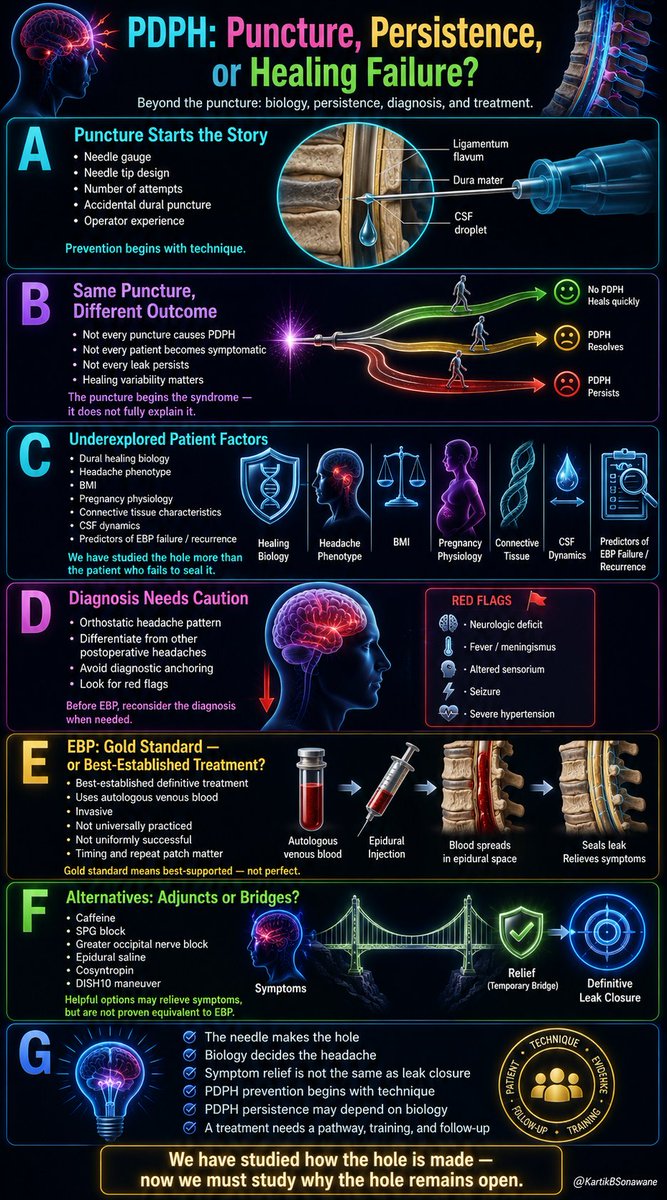
🧠 PDPH: PUNCTURE, PERSISTENCE, or HEALING FAILURE?
#PDPH #PostDuralPunctureHeadache #DuralPuncture #CSFLeak #EpiduralBloodPatch #HealingBiology #PatientSusceptibility #RegionalAnaesthesia
#RegionalAnesthesia #GrayZonesInRA #GrayAreasInRA
GRAY ZONES in RA:
🔸PDPH is familiar to every anesthesiologist.
🔸But it may not be only a puncture problem.
🔸It may also be a story of persistent CSF leak, delayed dural sealing, patient biology, diagnosis, and pathway-based care.
🟥 A. PUNCTURE STARTS THE STORY
🔸 Needle gauge matters
🔸 Needle tip design matters
🔸 Number of attempts matters
🔸 Accidental dural puncture matters
🔸 Operator experience matters
🔸 Technique remains important
PDPH prevention begins with technique, but technique does not explain everything.
🟧 B. SAME PUNCTURE, DIFFERENT PATIENT
🔸 Some remain asymptomatic
🔸 Some develop mild headache
🔸 Some develop severe disability
🔸 Some recover quickly
🔸 Some have persistent symptoms
🔸 Some need EBP
The puncture begins the syndrome, but patient response shapes the outcome.
🟨 C. PERSISTENCE DECIDES THE BURDEN
🔸 Dural rent may seal early
🔸 CSF leak may continue
🔸 Symptoms may persist
🔸 Disability may increase
🔸 Conservative treatment may fail
🔸 Escalation may be needed
PDPH burden depends not only on the hole, but on why the hole remains open.
🟩 D. PATIENT BIOLOGY IS UNDEREXPLORED
🔸 Dural healing biology
🔸 Connective tissue characteristics
🔸 Headache phenotype
🔸 Pregnancy physiology
🔸 BMI
🔸 CSF pressure dynamics
🔸 Predictors of EBP failure
🔸 Risk of recurrence
The patient may be as important as the puncture.
🟦 E. DIAGNOSIS NEEDS CAUTION
🔸 Orthostatic pattern matters
🔸 Timing matters
🔸 Severity matters
🔸 Associated symptoms matter
🔸 Differential diagnosis matters
🔸 Diagnostic anchoring should be avoided
Diagnose PDPH early, but do not label every post-neuraxial headache as PDPH.
🟪 F. RED FLAGS MUST REOPEN THE DIAGNOSIS
🔸 Neurological deficit
🔸 Fever or meningism
🔸 Altered sensorium
🔸 Seizure
🔸 Severe hypertension
🔸 Non-postural headache
🔸 Worsening headache pattern
🔸 Poor response to usual care
Red flags should never be hidden under the label of routine PDPH.
🟫 G. EBP REMAINS BEST ESTABLISHED
🔸 Uses autologous venous blood
🔸 Provides epidural tamponade
🔸 May seal the CSF leak
🔸 Often gives rapid relief
🔸 Timing matters
🔸 Repeat patch may be needed
🔸 Effective, but not perfect
EBP is best-established, but not universally successful.
⬛ H. GOLD STANDARD DOES NOT MEAN PERFECT
🔸 Invasive procedure
🔸 Needs trained hands
🔸 Not universally practiced
🔸 May fail
🔸 Symptoms may recur
🔸 Long-term outcomes need clarity
Gold standard means best-supported, not flawless.
🟥 I. ALTERNATIVES ARE BRIDGES, NOT EQUALS
🔸 Caffeine
🔸 Hydration
🔸 Analgesics
🔸 Sphenopalatine ganglion block
🔸 Greater occipital nerve block
🔸 Epidural saline
🔸 Cosyntropin
🔸 DISH10 maneuver
Symptom relief is not always leak closure.
🟧 J. PATHWAY IS AS IMP AS PATCH
🔸 Early recognition
🔸 Patient counseling
🔸 Disability assessment
🔸 Red flag screening
🔸 Clear EBP criteria
🔸 Trained performer
🔸 Follow-up plan
🔸 Documentation and audit
A gold-standard treatment needs a gold-standard pathway.
🎯 KEY TAKEAWAYS
🔹 The needle makes the hole
🔹 Patient biology decides the headache
🔹 Persistence decides the burden
🔹 Diagnosis needs caution
🔹 Red flags must be respected
🔹 EBP is best-established, not perfect
🔹 Alternatives are bridges, not equals
🔹 Pathway improves safety and consistency
🔥 PDPH PREVENTION begins with technique, PERSISTENCE may depend on biology, and TREATMENT needs evidence, training, and pathway.
🔥We have studied how the hole is made.
Now we must study why the hole remains open.
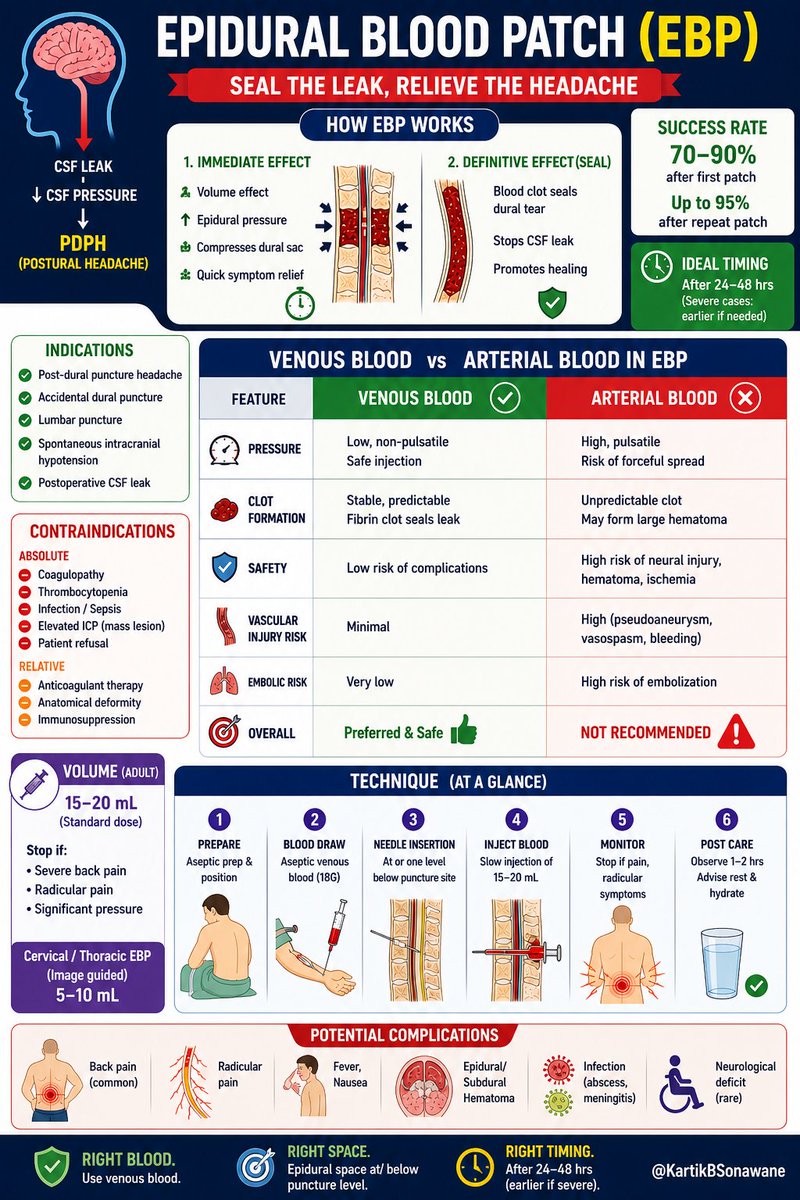
🩸 𝐄𝐏𝐈𝐃𝐔𝐑𝐀𝐋 𝐁𝐋𝐎𝐎𝐃 𝐏𝐀𝐓𝐂𝐇 (𝐄𝐁𝐏): 𝐏𝐫𝐞𝐜𝐢𝐬𝐢𝐨𝐧 𝐢𝐧 𝐍𝐞𝐮𝐫𝐚𝐱𝐢𝐚𝐥 𝐂𝐨𝐦𝐩𝐥𝐢𝐜𝐚𝐭𝐢𝐨𝐧 𝐌𝐚𝐧𝐚𝐠𝐞𝐦𝐞𝐧𝐭
#EpiduralBloodPatch #RegionalAnesthesia #NeuraxialAnesthesia #PDPH #PatientSafety #AnesthesiaEducation #PainMedicine #EpiduralSafety
#GrayZonesInRA #GrayAreasInRA
𝐆𝐑𝐀𝐘 𝐙𝐎𝐍𝐄𝐒 𝐢𝐧 𝐑𝐀:
1️⃣ ⚖️ 𝐓𝐑𝐀𝐍𝐒𝐅𝐎𝐑𝐌𝐈𝐍𝐆 𝐂𝐎𝐌𝐏𝐋𝐈𝐂𝐀𝐓𝐈𝐎𝐍 𝐈𝐍𝐓𝐎 𝐂𝐔𝐑𝐄
🔹 The EBP is far more than a simple treatment for PDPH.
🔹 It is one of the most critical interventions in RA, requiring meticulous attention to:
• Timing
• Blood source
• Patient selection
• Contraindications
• Procedural expertise
• Complication prevention
🔹 EBP acts as a highly effective biologic sealant that:
• Restores CSF homeostasis
• Seals dural defects
• Rapidly reverses debilitating symptoms
🔹 Anatomy + physiology + vascular safety + timing + judgment = outcome
2️⃣ ⚠️ 𝐂𝐑𝐈𝐓𝐈𝐂𝐀𝐋 𝐂𝐋𝐈𝐍𝐈𝐂𝐀𝐋 𝐂𝐎𝐍𝐒𝐈𝐃𝐄𝐑𝐀𝐓𝐈𝐎𝐍𝐒
🔸 Optimal timing of intervention
🔸 Appropriate blood volume selection
🔸 Therapeutic vs prophylactic application
🔸 Management in anticoagulated patients
🔸 Infection and coagulopathy risks
🔸 Repeat patch decisions
🔸 Anatomical precision
🔸 Strict vascular source safety
3️⃣ 💉 𝐃𝐔𝐀𝐋 𝐌𝐄𝐂𝐇𝐀𝐍𝐈𝐒𝐌𝐒 𝐎𝐅 𝐄𝐁𝐏
🚀 𝐈𝐦𝐦𝐞𝐝𝐢𝐚𝐭𝐞 𝐄𝐟𝐟𝐞𝐜𝐭 (𝐏𝐫𝐞𝐬𝐬𝐮𝐫𝐞 𝐑𝐞𝐬𝐭𝐨𝐫𝐚𝐭𝐢𝐨𝐧)
🔹 Raises epidural pressure
🔹 Compresses thecal sac
🔹 Restores CSF equilibrium
🔹 Reduces meningeal traction
🔹 Relieves orthostatic headache rapidly
🛡️ 𝐃𝐞𝐟𝐢𝐧𝐢𝐭𝐢𝐯𝐞 𝐄𝐟𝐟𝐞𝐜𝐭 (𝐁𝐢𝐨𝐥𝐨𝐠𝐢𝐜 𝐒𝐞𝐚𝐥 𝐅𝐨𝐫𝐦𝐚𝐭𝐢𝐨𝐧)
🔹 Forms fibrin clot over dural rent
🔹 Seals CSF leak
🔹 Prevents ongoing fluid loss
🔹 Promotes fibroblastic tissue healing
4️⃣ 🩸 𝐕𝐀𝐒𝐂𝐔𝐋𝐀𝐑 𝐒𝐎𝐔𝐑𝐂𝐄𝐒
𝐀. 🔵 𝐕𝐄𝐍𝐎𝐔𝐒 𝐁𝐋𝐎𝐎𝐃 (𝐆𝐎𝐋𝐃 𝐒𝐓𝐀𝐍𝐃𝐀𝐑𝐃)
🔸 𝐇𝐞𝐦𝐨𝐝𝐲𝐧𝐚𝐦𝐢𝐜 𝐀𝐝𝐯𝐚𝐧𝐭𝐚𝐠𝐞𝐬
🔹 Low pressure
🔹 Non-pulsatile flow
🔹 Controlled epidural spread
🔹 Predictable clot formation
🔸 𝐁𝐢𝐨𝐥𝐨𝐠𝐢𝐜𝐚𝐥 𝐀𝐝𝐯𝐚𝐧𝐭𝐚𝐠𝐞𝐬
🔹 Stable fibrin seal
🔹 Physiologic clotting behavior
🔹 Reduced endothelial trauma
🔹 Lower embolic potential
🔸 𝐏𝐫𝐚𝐜𝐭𝐢𝐜𝐚𝐥 𝐀𝐝𝐯𝐚𝐧𝐭𝐚𝐠𝐞𝐬
🔹 Easily accessible
🔹 Rapid bedside collection
🔹 Safer procedural profile
𝐁.🔴 𝐀𝐑𝐓𝐄𝐑𝐈𝐀𝐋 𝐁𝐋𝐎𝐎𝐃 (𝐀𝐕𝐎𝐈𝐃𝐄𝐃)
🫀 𝐇𝐞𝐦𝐨𝐝𝐲𝐧𝐚𝐦𝐢𝐜 𝐃𝐚𝐧𝐠𝐞𝐫𝐬
🔺 High-pressure system
🔺 Pulsatile flow
🔺 Forceful epidural spread
🔺 Tissue dissection risk
🔺 Sudden spinal cord compression potential
⚠️ 𝐌𝐚𝐣𝐨𝐫 𝐑𝐢𝐬𝐤𝐬
🔴 Epidural hematoma
🔴 Cord ischemia
🔴 Vasospasm
🔴 Nerve root injury
🔴 Pseudoaneurysm
🔴 Neurological deficit
🔴 Paralysis
🧬 𝐖𝐡𝐲 𝐀𝐫𝐭𝐞𝐫𝐢𝐚𝐥 𝐁𝐥𝐨𝐨𝐝 𝐈𝐬 𝐃𝐚𝐧𝐠𝐞𝐫𝐨𝐮𝐬
🔺 Unpredictable clot dynamics
🔺 Greater pressure-related trauma
🔺 Increased vascular injury
🔺 Higher catastrophic complication potential
5️⃣ 🕒 𝐓𝐈𝐌𝐈𝐍𝐆: 𝐀 𝐌𝐀𝐉𝐎𝐑 𝐃𝐄𝐓𝐄𝐑𝐌𝐈𝐍𝐀𝐍𝐓 𝐎𝐅 𝐒𝐔𝐂𝐂𝐄𝐒𝐒
𝐄𝐚𝐫𝐥𝐲 𝐄𝐁𝐏 (<𝟐𝟒 𝐡𝐨𝐮𝐫𝐬)
🔹 Faster relief in severe cases
🔸 Higher failure rates
🔸 Active CSF leakage may disrupt clot
𝐃𝐞𝐥𝐚𝐲𝐞𝐝 𝐄𝐁𝐏 (𝟐𝟒–𝟒𝟖 𝐡𝐨𝐮𝐫𝐬)
🔹 Better clot stabilization
🔹 Higher long-term efficacy
🔹 Reduced repeat procedure need
6️⃣ 📚 𝐄𝐁𝐏 - 𝐀𝐧 𝐀𝐃𝐕𝐀𝐍𝐂𝐄𝐃 𝐍𝐄𝐔𝐑𝐀𝐗𝐈𝐀𝐋 𝐏𝐑𝐀𝐂𝐓𝐈𝐂𝐄
𝐄𝐁𝐏 𝐢𝐧𝐭𝐞𝐠𝐫𝐚𝐭𝐞𝐬:
🔹 Detailed neuraxial anatomy
🔹 CSF physiology
🔹 Hemodynamic principles
🔹 Clot biology
🔹 Infection prevention
🔹 Procedural precision
🔹 Risk-benefit judgment
🎯 𝐅𝐈𝐍𝐀𝐋 𝐓𝐀𝐊𝐄𝐀𝐖𝐀𝐘𝐒 🏆
🩸 Right Blood (Venous)
📍 Right Space (Epidural)
⏱️ Right Timing (Clinical Judgment)
🔥 EBP represents one of regional anesthesia’s true 𝐆𝐑𝐀𝐘 𝐙𝐎𝐍𝐄𝐒, where science, skill, & clinical judgment must align to safely transform 𝐂𝐎𝐌𝐏𝐋𝐈𝐂𝐀𝐓𝐈𝐎𝐍 𝐢𝐧𝐭𝐨 𝐂𝐔𝐑𝐄.

How should #PDPH be managed after accidental dural puncture (#ADP)? Dziadzko et al. respond to recent correspondence, exploring new evidence and the challenges of heterogeneity in practice. Read their insights: https://t.co/fUgRB0fJ14 #Anaesthesia #PeriOpMed


🧠 Brain MRI in PDPH 🧠
118 PDPH patients, and 92% had NO intracranial hypotension findings on brain MRI. Not the paper's main focus, but a really important detail.
#PDPH #spinalCSFleak #Anes #Anaes #CSFleak

🚨New Paper Alert! 🚨
When should myelography play a role in PDPH evaluation? How do we avoid repeat dural punctures? How often does it help?
@issclsociety @TheAJNR @The_ASSR @spinalCSFleak @SpinalCSFCanada
https://t.co/QCs2zhWFgX

ラリージャパン 2025 Day2終了!
走行距離417.9km
いろいろあってもうDay3始まっとるやん笑
勝田貴元選手の優勝もあり得る!
頑張ってください!
寝ます!
#ラリージャパン2025 #WRC #勝田貴元 #Ford #GRヤリスrally2 #ラリー2 #rally2 #PdPh #TGR




@DebeshBhoi @aiims_newdelhi @KalagaraHari @ESRA_Society @ASRA_Society Thank you @DebeshBhoi 🙏 It was a privilege to be at @aiims_newdelhi, an institution with an outstanding reputation.
Truly impressed by the warm hospitality of Prof. Gangaprasad, Anjolie, & the enthusiastic team. I thoroughly enjoyed the interactive discussions on #PDPH


Nice to have the talk on #PDPH.. at AIIMS,New Delhi Thanks Prof Vishal Uppal..a great interactive talk..@aiims_newdelhi @Ropivacaine @KalagaraHari @ESRA_Society @ASRA_Society


Chronic post-dural puncture headache exists! However, MRI in these patients is mostly negative, contrary to the tremendous symptom burden. Read the full article here ⬇️
Big thanks to @Niklas_Luetzen and the whole #CSF Team at Universitätsklinikum Freiburg!
#PDPH @issclsociety

Open Access:
An MRI study using the Bern score finds that patients with chronic post-dural puncture #headache do not have typical imaging features of #intracranial #hypotension
https://t.co/BHghPObrt4
@ZanderCharlotte et al


Open Access:
An MRI study using the Bern score finds that patients with chronic post-dural puncture #headache do not have typical imaging features of #intracranial #hypotension
https://t.co/BHghPObrt4
@ZanderCharlotte et al

Continuing Professional Development
Postdural puncture headache in obstetrics - Canadian Journal of Anesthesia #CJA #CJA2025 #Anesthesia #Anesthesiology https://t.co/KkTWywot4w
#ProfessionalDevelopment #OBAnes #PDPH

Continuing Professional Development
Postdural puncture headache in obstetrics - Canadian Journal of Anesthesia #Anesthesia #Anesthesiology https://t.co/238Gv065QR
#CPD #ProfessionalDevelopment #OBAnes #PDPH


Continuing Professional Development
Postdural puncture headache in obstetrics - Canadian Journal of Anesthesia #CJA2025 #Anesthesia #Anesthesiology https://t.co/bRUZdWGClR
#CPD #ProfessionalDevelopment #OBAnes #PDPH


This week’s SPIN-POV: Post-LP CSF leaks are not uncommon in children. This child presented with a severe headache and MRI features of intracranial hypotension and was treated with targeted epidural blood patching. Using atraumatic pencil-point needles can reduce the risk.

Last Seen Hashtags on Sotwe
granny incest
Seen from Switzerland
femboy #anal #video
Seen from Egypt
zootwitter
Seen from Turkey
freeuse gabbie carter
Seen from Thailand
brawlstarscosmo
Seen from United States
teenageee
Seen from Portugal
นัดเยสหนองบัวลำภู
Seen from Malaysia
transgender
Seen from Latvia
monkeyapp
Seen from United Kingdom
แอบถ่ายเมีย
Trends for you
Most Popular Users

Elon Musk 
@elonmusk
241.7M followers

Barack Obama
@barackobama
119M followers

Cristiano Ronaldo
@cristiano
114.4M followers

Donald J. Trump
@realdonaldtrump
111.9M followers

Narendra Modi
@narendramodi
107.2M followers

Rihanna
@rihanna
98.7M followers

NASA
@nasa
92.4M followers

Justin Bieber
@justinbieber
91.8M followers

KATY PERRY
@katyperry
90M followers

Taylor Swift
@taylorswift13
83.9M followers

Lady Gaga
@ladygaga
75.4M followers

Virat Kohli
@imvkohli
73.3M followers

Kim Kardashian
@kimkardashian
70.9M followers

YouTube
@youtube
68.8M followers

Neymar Jr
@neymarjr
66.3M followers

Bill Gates
@billgates
65.1M followers

Selena Gomez
@selenagomez
63M followers

The Ellen Show
@theellenshow
62.3M followers

CNN
@cnn
61.8M followers

X
@x
60.7M followers