

Top Tweets for #pdph

Dural puncture → EBP. 11 days later, labor DPE = rapid, effective, no PDPH return. Bottom line: Epidural/CSE/DPE remain options soon after EBP. https://t.co/DUTLrHH4oE #Anesthesia #MedTwitter #PDPH #Epidural #OBAnes #FOAMed #ObGyn

After accidental dural puncture and EBP, a laboring patient received DPE 11 days later—rapid, effective analgesia, no return of PDPH. What this means for neuraxial choices in labor: https://t.co/DUTLrHH4oE #Anesthesia #Epidural #DPE #PDPH #MedTwitter #ObGyn


Images in #Anesthesiology - Air Entrainment and Subsequent Pneumocephalus Associated with Epidural Blood Patch 📷 https://t.co/hUYKes0EDs
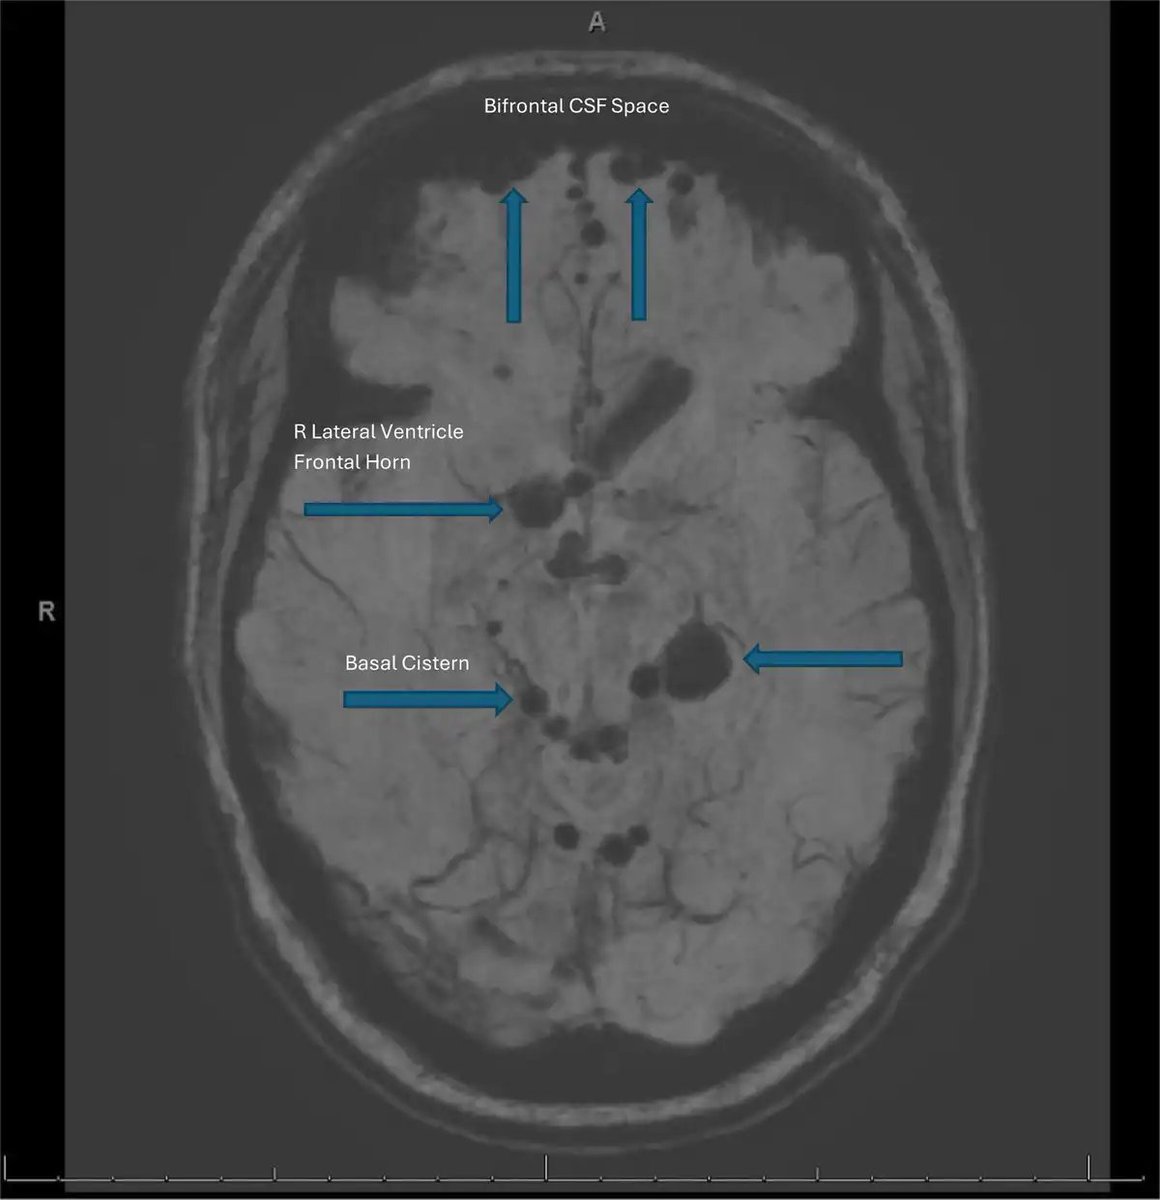
Dural puncture → EBP. 11 days later, labor DPE = rapid, effective, no PDPH return. Bottom line: Epidural/CSE/DPE remain options soon after EBP. https://t.co/DUTLrHH4oE #Anesthesia #MedTwitter #PDPH #Epidural #OBAnes #FOAMed #ObGyn


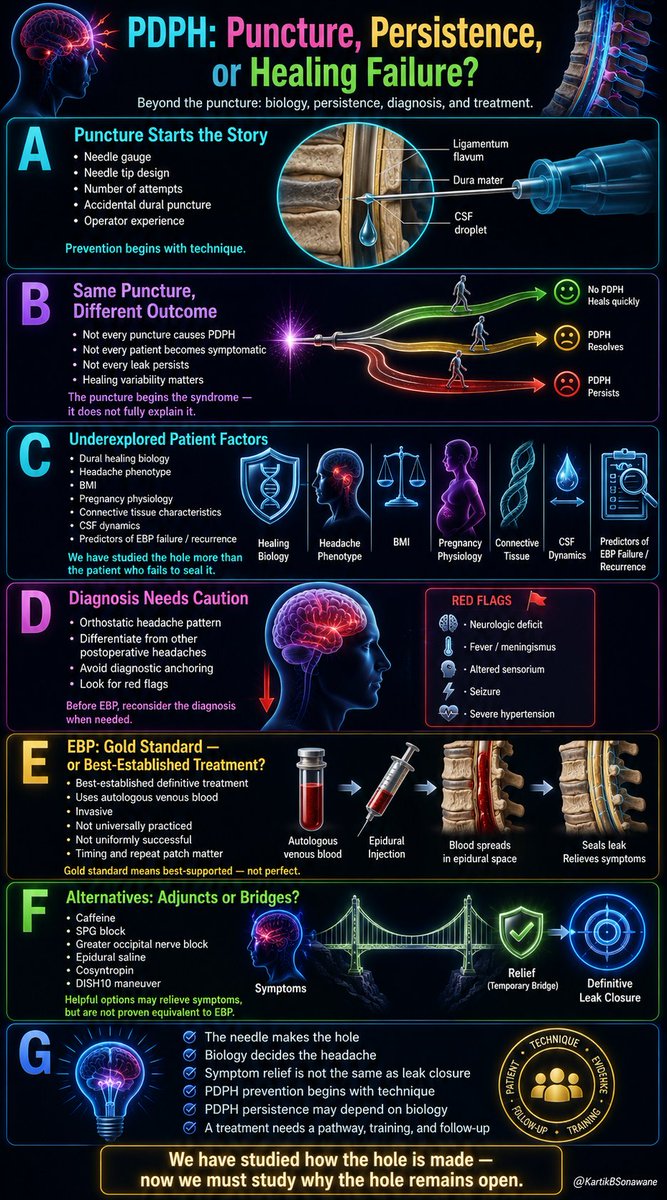
🧠 PDPH: PUNCTURE, PERSISTENCE, or HEALING FAILURE?
#PDPH #PostDuralPunctureHeadache #DuralPuncture #CSFLeak #EpiduralBloodPatch #HealingBiology #PatientSusceptibility #RegionalAnaesthesia
#RegionalAnesthesia #GrayZonesInRA #GrayAreasInRA
GRAY ZONES in RA:
🔸PDPH is familiar to every anesthesiologist.
🔸But it may not be only a puncture problem.
🔸It may also be a story of persistent CSF leak, delayed dural sealing, patient biology, diagnosis, and pathway-based care.
🟥 A. PUNCTURE STARTS THE STORY
🔸 Needle gauge matters
🔸 Needle tip design matters
🔸 Number of attempts matters
🔸 Accidental dural puncture matters
🔸 Operator experience matters
🔸 Technique remains important
PDPH prevention begins with technique, but technique does not explain everything.
🟧 B. SAME PUNCTURE, DIFFERENT PATIENT
🔸 Some remain asymptomatic
🔸 Some develop mild headache
🔸 Some develop severe disability
🔸 Some recover quickly
🔸 Some have persistent symptoms
🔸 Some need EBP
The puncture begins the syndrome, but patient response shapes the outcome.
🟨 C. PERSISTENCE DECIDES THE BURDEN
🔸 Dural rent may seal early
🔸 CSF leak may continue
🔸 Symptoms may persist
🔸 Disability may increase
🔸 Conservative treatment may fail
🔸 Escalation may be needed
PDPH burden depends not only on the hole, but on why the hole remains open.
🟩 D. PATIENT BIOLOGY IS UNDEREXPLORED
🔸 Dural healing biology
🔸 Connective tissue characteristics
🔸 Headache phenotype
🔸 Pregnancy physiology
🔸 BMI
🔸 CSF pressure dynamics
🔸 Predictors of EBP failure
🔸 Risk of recurrence
The patient may be as important as the puncture.
🟦 E. DIAGNOSIS NEEDS CAUTION
🔸 Orthostatic pattern matters
🔸 Timing matters
🔸 Severity matters
🔸 Associated symptoms matter
🔸 Differential diagnosis matters
🔸 Diagnostic anchoring should be avoided
Diagnose PDPH early, but do not label every post-neuraxial headache as PDPH.
🟪 F. RED FLAGS MUST REOPEN THE DIAGNOSIS
🔸 Neurological deficit
🔸 Fever or meningism
🔸 Altered sensorium
🔸 Seizure
🔸 Severe hypertension
🔸 Non-postural headache
🔸 Worsening headache pattern
🔸 Poor response to usual care
Red flags should never be hidden under the label of routine PDPH.
🟫 G. EBP REMAINS BEST ESTABLISHED
🔸 Uses autologous venous blood
🔸 Provides epidural tamponade
🔸 May seal the CSF leak
🔸 Often gives rapid relief
🔸 Timing matters
🔸 Repeat patch may be needed
🔸 Effective, but not perfect
EBP is best-established, but not universally successful.
⬛ H. GOLD STANDARD DOES NOT MEAN PERFECT
🔸 Invasive procedure
🔸 Needs trained hands
🔸 Not universally practiced
🔸 May fail
🔸 Symptoms may recur
🔸 Long-term outcomes need clarity
Gold standard means best-supported, not flawless.
🟥 I. ALTERNATIVES ARE BRIDGES, NOT EQUALS
🔸 Caffeine
🔸 Hydration
🔸 Analgesics
🔸 Sphenopalatine ganglion block
🔸 Greater occipital nerve block
🔸 Epidural saline
🔸 Cosyntropin
🔸 DISH10 maneuver
Symptom relief is not always leak closure.
🟧 J. PATHWAY IS AS IMP AS PATCH
🔸 Early recognition
🔸 Patient counseling
🔸 Disability assessment
🔸 Red flag screening
🔸 Clear EBP criteria
🔸 Trained performer
🔸 Follow-up plan
🔸 Documentation and audit
A gold-standard treatment needs a gold-standard pathway.
🎯 KEY TAKEAWAYS
🔹 The needle makes the hole
🔹 Patient biology decides the headache
🔹 Persistence decides the burden
🔹 Diagnosis needs caution
🔹 Red flags must be respected
🔹 EBP is best-established, not perfect
🔹 Alternatives are bridges, not equals
🔹 Pathway improves safety and consistency
🔥 PDPH PREVENTION begins with technique, PERSISTENCE may depend on biology, and TREATMENT needs evidence, training, and pathway.
🔥We have studied how the hole is made.
Now we must study why the hole remains open.
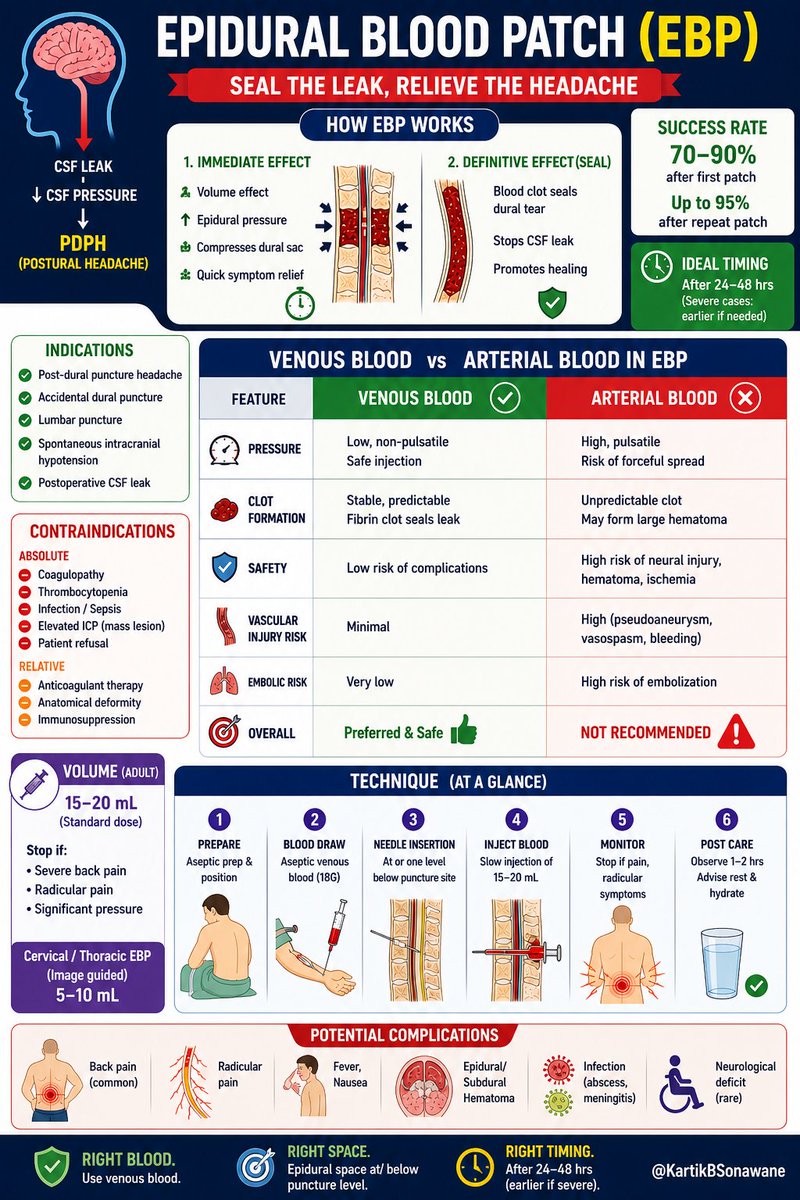
🩸 𝐄𝐏𝐈𝐃𝐔𝐑𝐀𝐋 𝐁𝐋𝐎𝐎𝐃 𝐏𝐀𝐓𝐂𝐇 (𝐄𝐁𝐏): 𝐏𝐫𝐞𝐜𝐢𝐬𝐢𝐨𝐧 𝐢𝐧 𝐍𝐞𝐮𝐫𝐚𝐱𝐢𝐚𝐥 𝐂𝐨𝐦𝐩𝐥𝐢𝐜𝐚𝐭𝐢𝐨𝐧 𝐌𝐚𝐧𝐚𝐠𝐞𝐦𝐞𝐧𝐭
#EpiduralBloodPatch #RegionalAnesthesia #NeuraxialAnesthesia #PDPH #PatientSafety #AnesthesiaEducation #PainMedicine #EpiduralSafety
#GrayZonesInRA #GrayAreasInRA
𝐆𝐑𝐀𝐘 𝐙𝐎𝐍𝐄𝐒 𝐢𝐧 𝐑𝐀:
1️⃣ ⚖️ 𝐓𝐑𝐀𝐍𝐒𝐅𝐎𝐑𝐌𝐈𝐍𝐆 𝐂𝐎𝐌𝐏𝐋𝐈𝐂𝐀𝐓𝐈𝐎𝐍 𝐈𝐍𝐓𝐎 𝐂𝐔𝐑𝐄
🔹 The EBP is far more than a simple treatment for PDPH.
🔹 It is one of the most critical interventions in RA, requiring meticulous attention to:
• Timing
• Blood source
• Patient selection
• Contraindications
• Procedural expertise
• Complication prevention
🔹 EBP acts as a highly effective biologic sealant that:
• Restores CSF homeostasis
• Seals dural defects
• Rapidly reverses debilitating symptoms
🔹 Anatomy + physiology + vascular safety + timing + judgment = outcome
2️⃣ ⚠️ 𝐂𝐑𝐈𝐓𝐈𝐂𝐀𝐋 𝐂𝐋𝐈𝐍𝐈𝐂𝐀𝐋 𝐂𝐎𝐍𝐒𝐈𝐃𝐄𝐑𝐀𝐓𝐈𝐎𝐍𝐒
🔸 Optimal timing of intervention
🔸 Appropriate blood volume selection
🔸 Therapeutic vs prophylactic application
🔸 Management in anticoagulated patients
🔸 Infection and coagulopathy risks
🔸 Repeat patch decisions
🔸 Anatomical precision
🔸 Strict vascular source safety
3️⃣ 💉 𝐃𝐔𝐀𝐋 𝐌𝐄𝐂𝐇𝐀𝐍𝐈𝐒𝐌𝐒 𝐎𝐅 𝐄𝐁𝐏
🚀 𝐈𝐦𝐦𝐞𝐝𝐢𝐚𝐭𝐞 𝐄𝐟𝐟𝐞𝐜𝐭 (𝐏𝐫𝐞𝐬𝐬𝐮𝐫𝐞 𝐑𝐞𝐬𝐭𝐨𝐫𝐚𝐭𝐢𝐨𝐧)
🔹 Raises epidural pressure
🔹 Compresses thecal sac
🔹 Restores CSF equilibrium
🔹 Reduces meningeal traction
🔹 Relieves orthostatic headache rapidly
🛡️ 𝐃𝐞𝐟𝐢𝐧𝐢𝐭𝐢𝐯𝐞 𝐄𝐟𝐟𝐞𝐜𝐭 (𝐁𝐢𝐨𝐥𝐨𝐠𝐢𝐜 𝐒𝐞𝐚𝐥 𝐅𝐨𝐫𝐦𝐚𝐭𝐢𝐨𝐧)
🔹 Forms fibrin clot over dural rent
🔹 Seals CSF leak
🔹 Prevents ongoing fluid loss
🔹 Promotes fibroblastic tissue healing
4️⃣ 🩸 𝐕𝐀𝐒𝐂𝐔𝐋𝐀𝐑 𝐒𝐎𝐔𝐑𝐂𝐄𝐒
𝐀. 🔵 𝐕𝐄𝐍𝐎𝐔𝐒 𝐁𝐋𝐎𝐎𝐃 (𝐆𝐎𝐋𝐃 𝐒𝐓𝐀𝐍𝐃𝐀𝐑𝐃)
🔸 𝐇𝐞𝐦𝐨𝐝𝐲𝐧𝐚𝐦𝐢𝐜 𝐀𝐝𝐯𝐚𝐧𝐭𝐚𝐠𝐞𝐬
🔹 Low pressure
🔹 Non-pulsatile flow
🔹 Controlled epidural spread
🔹 Predictable clot formation
🔸 𝐁𝐢𝐨𝐥𝐨𝐠𝐢𝐜𝐚𝐥 𝐀𝐝𝐯𝐚𝐧𝐭𝐚𝐠𝐞𝐬
🔹 Stable fibrin seal
🔹 Physiologic clotting behavior
🔹 Reduced endothelial trauma
🔹 Lower embolic potential
🔸 𝐏𝐫𝐚𝐜𝐭𝐢𝐜𝐚𝐥 𝐀𝐝𝐯𝐚𝐧𝐭𝐚𝐠𝐞𝐬
🔹 Easily accessible
🔹 Rapid bedside collection
🔹 Safer procedural profile
𝐁.🔴 𝐀𝐑𝐓𝐄𝐑𝐈𝐀𝐋 𝐁𝐋𝐎𝐎𝐃 (𝐀𝐕𝐎𝐈𝐃𝐄𝐃)
🫀 𝐇𝐞𝐦𝐨𝐝𝐲𝐧𝐚𝐦𝐢𝐜 𝐃𝐚𝐧𝐠𝐞𝐫𝐬
🔺 High-pressure system
🔺 Pulsatile flow
🔺 Forceful epidural spread
🔺 Tissue dissection risk
🔺 Sudden spinal cord compression potential
⚠️ 𝐌𝐚𝐣𝐨𝐫 𝐑𝐢𝐬𝐤𝐬
🔴 Epidural hematoma
🔴 Cord ischemia
🔴 Vasospasm
🔴 Nerve root injury
🔴 Pseudoaneurysm
🔴 Neurological deficit
🔴 Paralysis
🧬 𝐖𝐡𝐲 𝐀𝐫𝐭𝐞𝐫𝐢𝐚𝐥 𝐁𝐥𝐨𝐨𝐝 𝐈𝐬 𝐃𝐚𝐧𝐠𝐞𝐫𝐨𝐮𝐬
🔺 Unpredictable clot dynamics
🔺 Greater pressure-related trauma
🔺 Increased vascular injury
🔺 Higher catastrophic complication potential
5️⃣ 🕒 𝐓𝐈𝐌𝐈𝐍𝐆: 𝐀 𝐌𝐀𝐉𝐎𝐑 𝐃𝐄𝐓𝐄𝐑𝐌𝐈𝐍𝐀𝐍𝐓 𝐎𝐅 𝐒𝐔𝐂𝐂𝐄𝐒𝐒
𝐄𝐚𝐫𝐥𝐲 𝐄𝐁𝐏 (<𝟐𝟒 𝐡𝐨𝐮𝐫𝐬)
🔹 Faster relief in severe cases
🔸 Higher failure rates
🔸 Active CSF leakage may disrupt clot
𝐃𝐞𝐥𝐚𝐲𝐞𝐝 𝐄𝐁𝐏 (𝟐𝟒–𝟒𝟖 𝐡𝐨𝐮𝐫𝐬)
🔹 Better clot stabilization
🔹 Higher long-term efficacy
🔹 Reduced repeat procedure need
6️⃣ 📚 𝐄𝐁𝐏 - 𝐀𝐧 𝐀𝐃𝐕𝐀𝐍𝐂𝐄𝐃 𝐍𝐄𝐔𝐑𝐀𝐗𝐈𝐀𝐋 𝐏𝐑𝐀𝐂𝐓𝐈𝐂𝐄
𝐄𝐁𝐏 𝐢𝐧𝐭𝐞𝐠𝐫𝐚𝐭𝐞𝐬:
🔹 Detailed neuraxial anatomy
🔹 CSF physiology
🔹 Hemodynamic principles
🔹 Clot biology
🔹 Infection prevention
🔹 Procedural precision
🔹 Risk-benefit judgment
🎯 𝐅𝐈𝐍𝐀𝐋 𝐓𝐀𝐊𝐄𝐀𝐖𝐀𝐘𝐒 🏆
🩸 Right Blood (Venous)
📍 Right Space (Epidural)
⏱️ Right Timing (Clinical Judgment)
🔥 EBP represents one of regional anesthesia’s true 𝐆𝐑𝐀𝐘 𝐙𝐎𝐍𝐄𝐒, where science, skill, & clinical judgment must align to safely transform 𝐂𝐎𝐌𝐏𝐋𝐈𝐂𝐀𝐓𝐈𝐎𝐍 𝐢𝐧𝐭𝐨 𝐂𝐔𝐑𝐄.

How should #PDPH be managed after accidental dural puncture (#ADP)? Dziadzko et al. respond to recent correspondence, exploring new evidence and the challenges of heterogeneity in practice. Read their insights: https://t.co/fUgRB0fJ14 #Anaesthesia #PeriOpMed


🧠 Brain MRI in PDPH 🧠
118 PDPH patients, and 92% had NO intracranial hypotension findings on brain MRI. Not the paper's main focus, but a really important detail.
#PDPH #spinalCSFleak #Anes #Anaes #CSFleak

🚨New Paper Alert! 🚨
When should myelography play a role in PDPH evaluation? How do we avoid repeat dural punctures? How often does it help?
@issclsociety @TheAJNR @The_ASSR @spinalCSFleak @SpinalCSFCanada
https://t.co/QCs2zhWFgX

ラリージャパン 2025 Day2終了!
走行距離417.9km
いろいろあってもうDay3始まっとるやん笑
勝田貴元選手の優勝もあり得る!
頑張ってください!
寝ます!
#ラリージャパン2025 #WRC #勝田貴元 #Ford #GRヤリスrally2 #ラリー2 #rally2 #PdPh #TGR




@DebeshBhoi @aiims_newdelhi @KalagaraHari @ESRA_Society @ASRA_Society Thank you @DebeshBhoi 🙏 It was a privilege to be at @aiims_newdelhi, an institution with an outstanding reputation.
Truly impressed by the warm hospitality of Prof. Gangaprasad, Anjolie, & the enthusiastic team. I thoroughly enjoyed the interactive discussions on #PDPH


Nice to have the talk on #PDPH.. at AIIMS,New Delhi Thanks Prof Vishal Uppal..a great interactive talk..@aiims_newdelhi @Ropivacaine @KalagaraHari @ESRA_Society @ASRA_Society


Chronic post-dural puncture headache exists! However, MRI in these patients is mostly negative, contrary to the tremendous symptom burden. Read the full article here ⬇️
Big thanks to @Niklas_Luetzen and the whole #CSF Team at Universitätsklinikum Freiburg!
#PDPH @issclsociety

Open Access:
An MRI study using the Bern score finds that patients with chronic post-dural puncture #headache do not have typical imaging features of #intracranial #hypotension
https://t.co/BHghPObrt4
@ZanderCharlotte et al


Open Access:
An MRI study using the Bern score finds that patients with chronic post-dural puncture #headache do not have typical imaging features of #intracranial #hypotension
https://t.co/BHghPObrt4
@ZanderCharlotte et al

Continuing Professional Development
Postdural puncture headache in obstetrics - Canadian Journal of Anesthesia #CJA #CJA2025 #Anesthesia #Anesthesiology https://t.co/KkTWywot4w
#ProfessionalDevelopment #OBAnes #PDPH

Continuing Professional Development
Postdural puncture headache in obstetrics - Canadian Journal of Anesthesia #Anesthesia #Anesthesiology https://t.co/238Gv065QR
#CPD #ProfessionalDevelopment #OBAnes #PDPH


Continuing Professional Development
Postdural puncture headache in obstetrics - Canadian Journal of Anesthesia #CJA2025 #Anesthesia #Anesthesiology https://t.co/bRUZdWGClR
#CPD #ProfessionalDevelopment #OBAnes #PDPH


This week’s SPIN-POV: Post-LP CSF leaks are not uncommon in children. This child presented with a severe headache and MRI features of intracranial hypotension and was treated with targeted epidural blood patching. Using atraumatic pencil-point needles can reduce the risk.

Last Seen Hashtags on Sotwe
Trends for you
Most Popular Users

Elon Musk 
@elonmusk
241.7M followers

Barack Obama
@barackobama
119M followers

Cristiano Ronaldo
@cristiano
114.4M followers

Donald J. Trump
@realdonaldtrump
111.8M followers

Narendra Modi
@narendramodi
107.2M followers

Rihanna
@rihanna
98.7M followers

NASA
@nasa
92.4M followers

Justin Bieber
@justinbieber
91.8M followers

KATY PERRY
@katyperry
90M followers

Taylor Swift
@taylorswift13
83.9M followers

Lady Gaga
@ladygaga
75.4M followers

Virat Kohli
@imvkohli
73.3M followers

Kim Kardashian
@kimkardashian
70.9M followers

YouTube
@youtube
68.8M followers

Neymar Jr
@neymarjr
66.3M followers

Bill Gates
@billgates
65.1M followers

Selena Gomez
@selenagomez
63M followers

The Ellen Show
@theellenshow
62.3M followers

CNN
@cnn
61.8M followers

X
@x
60.7M followers