(1/x) Septic shock is the leading cause of death in most ICUs worldwide.
Unfortunately, the hemodynamics of sepsis are still often taught incorrectly in medical school.
A 🧵
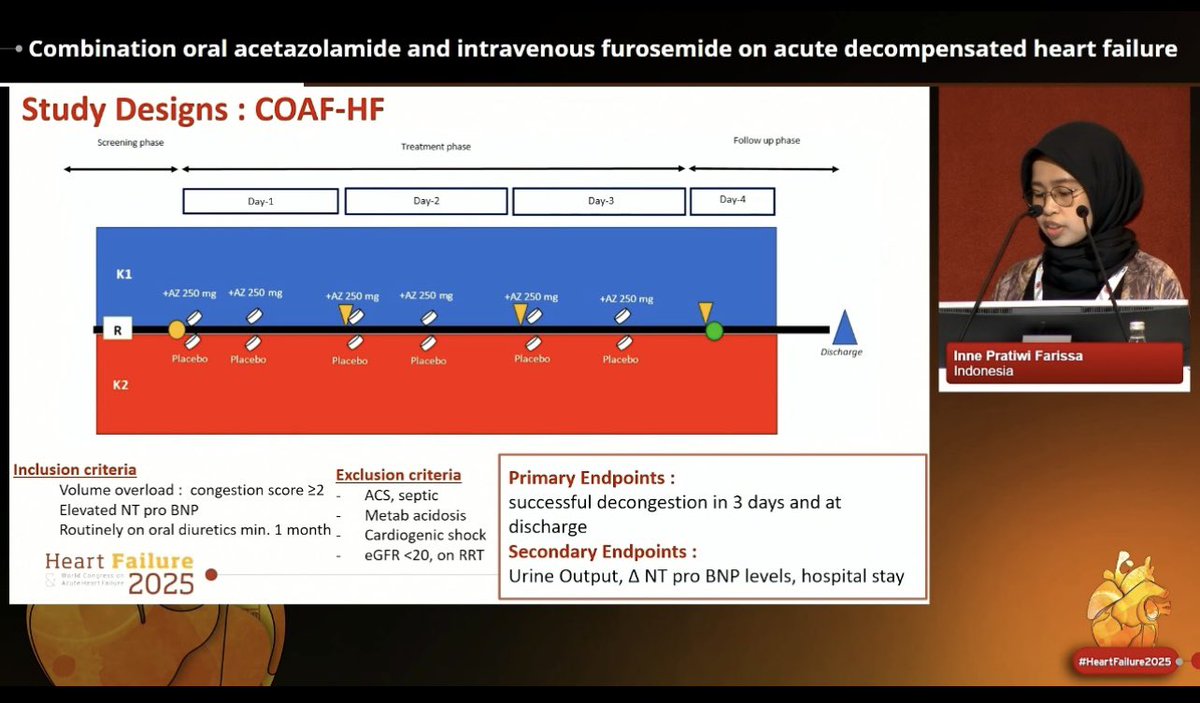
What if IV #acetazolamide isn’t available? Can oral be an option?💊
Insight from 🇮🇩Indonesia, @innefarissa at #HeartFailure2025:
Adding oral acetazolamide 250mg BD on top of 3 pillars of #GDMT:
📍Achieve effective decongestion, not within 3 days, but at discharge
📍⬆️urine output in first 3 days
📍Significant ⬇️in #NTproBNP over 3 days
📍No change in hospital length of stay
#GDMTworks
Intensive Blood-Pressure Control in Patients with Type 2 Diabetes: @NEJM
🥸 Day 3 of #AHA24 continues: Great work @AHAScience
😱 Let's summarize BPROAD trial
👇👇👇
#JACCHF state-of-the-art review provides an overview of the prevalence, pathophysiology, management, and prevention of #AFib in patients with #heartfailure, with emphasis on the subgroup with #HFrEF. https://t.co/xcEb3rwlPb
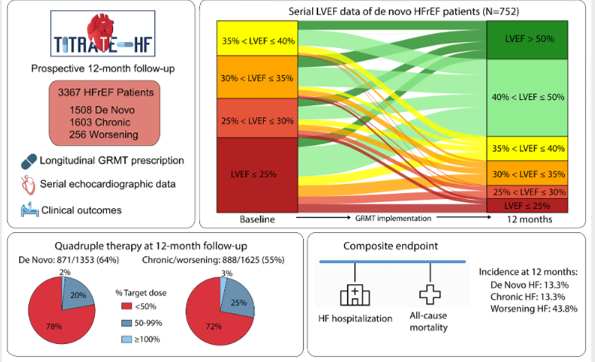
I already don't particularly like flow charts, but this one beats them all. The random curved arrows are a sign that at a certain point even the authors couldn't stand it anymore.
Heart failure with preserved ejection fraction: underdiagnosed and undertreated in patients with tricuspid regurgitation. Read this viewpoint in #EHJ 👉 https://t.co/GjgjHRbPF2
@RoccoMontone@ehj_ed
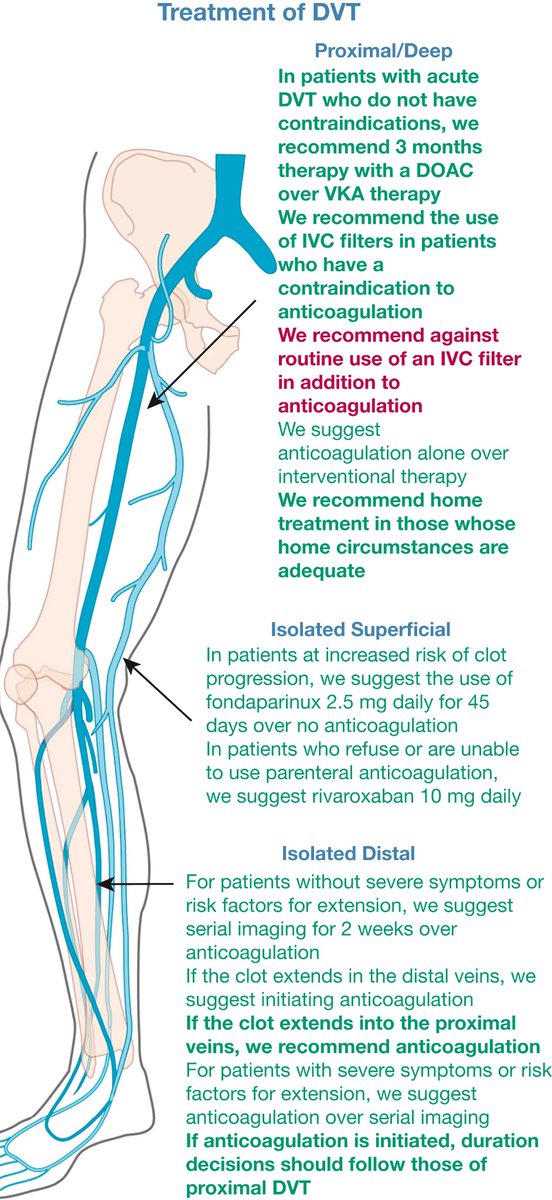
The American College of Chest Physicians Antithrombotic Therapy for Venous Thromboembolism Disease evidence-based guidelines
🔗 https://t.co/fH735iZ7DR
#FOAMed#FOAMcc#CriticalCare
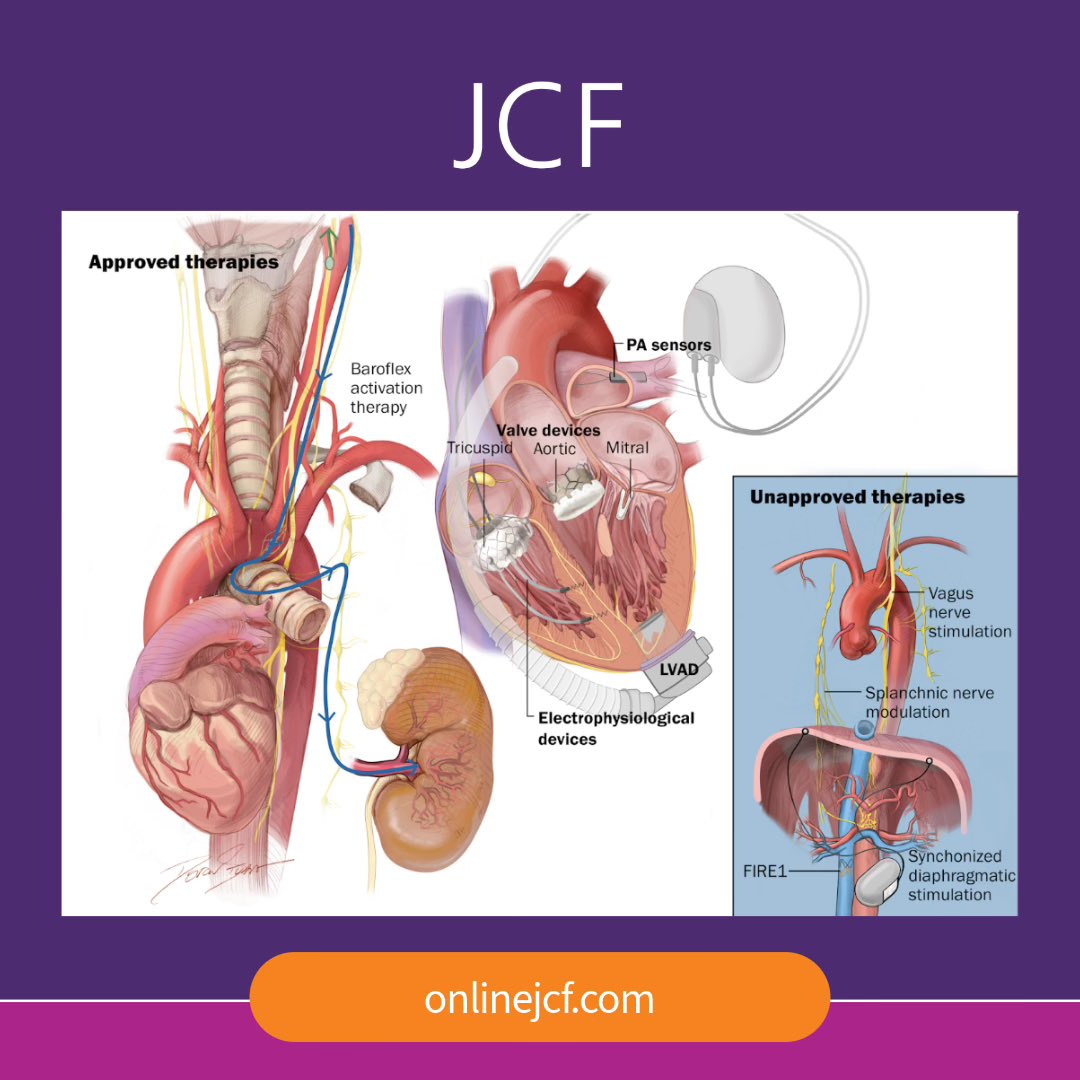
Understand the latest guidelines for HF device therapies & how patient selection & implementation can be optimized in HF workflows.
✅ Remote monitoring
✅ Valvular- & structural-based therapies
✅ Autonomic, EP & respiratory modulators
✅ Durable MCS
🔗 https://t.co/wRZYTCN92v
@FH_Verbrugge discusses the top 10 diuretic mistakes at #HR24 .
If you prescribe lasix you need to read these key mistakes👇
10 Diuretic mistakes 🧵
#1: Not getting the job finished.. don't stop diuresis too early. If you fail to decongest, outcomes are worse and there is a higher risk of readmission to hospital.
#2: Being distracted by serum Creatinine.. rising Cr does NOT indicate dying kidneys!!
#3: Giving oral loop diuretics for in-hospital pts. with clear fluid overload (instead of IV diuretics)...
When dosing loop diuretics, there is a threshold effect that until above that you get no effect, and then a ceiling effect where any more diuretics don't increase diuresis.
#4: Underdosing (loop) diuretics and compensating with increasing maintenance outpatients doses instead.
Lasix dose = 1-2 times oral maintenance dose only makes sense IF the maintenance dose was appropriate... might not be the best place to start.
Does house of god (book) have it right? Adjust based on GFR. If you have poor kidney function need higher dosing... general gestalt
GFR>45 --> 80 IV lasix
GFR 30-45--> 120 IV lasix
GFR <30 -->120 IV lasix
#5: Too infrequent dosing of loop diuretics
LaSIX --> lasts six hours.
If you dose too infrequently then you get Na resorption in-between diuretic doses.
Start BID or TID with Lasix, not once daily! (sometimes even QID)
#6: Using loop diuretic drips (No lasix infusions!)
Higher plasma-renin activity with diuretic infusions...
#7: Failure to recognize fluid overload when cardiac filling pressures are normal / not terribly elevated
You can be overloaded with normal filling pressures. Volume does NOT equal pressure.
If overload + high filling pressures --> diurese fast
If overload + low filling pressures --> diurese slow
#8: Mistaking one size fits all for diuretic resistance
Steps to treat diuretic resistance:
1. Maximize Loop Diuretic
2. Add thiazide like diuretic (e.g Metolazone)
3. Add other nephro segment blocker (Acetazolamide, Spiro, Empagliflozin, Amiloride)
4. Consider hyperdiuresis (3% saline with diuretics)
5. Consider diuresis
#9: Don't be afraid of combination diuretic therapy
ADVOR trial: acetazolamide added to loop diuretic improved decongestion. We need to start thinking about multi-modal diuresis!
#10: Don't mistake decongestion for dehydration
Decongestion is about removing sodium.
Positive sodium balance with net fluid loss still portends worse survival (Hodson et al 2019).
#echofirst #Cardiology #medtwitter #foamed #foamcc #pocus #physiology
The key is in the pee
Check urine sodium concentration 1-2 hours post diuretic ... want a urine Na > 100 ideally (<80 is diuretic resistance)