Radiation oncologist at @SirirajRadOnco, Thailand
Interested in basic, translational to clinical #RadOnc
@SirirajMedicine, @MWIT_Th Alum, Tweets my own
Dr. Hawkins #PLATO ACT5 RCT of dose-escalated #IMRT (58.8 or 61.6 Gy) w/fluoro + MMC X1 in T3/4N0 #analSCC ➡️ dose-escalation with similar toxicity but no improvement in early outcomes (6 month cCR by MRI TRG) vs standard #IMRT (53.2 Gy)
@OncoAlert#GI26
Unlike previous post-mastectomy RT trials which included regional nodal irradiation (BC, Danish, etc), SUPREMO primarily tested chest wall RT only. Let’s compare to 4 other studies which found that RNI for LN+ after ALND can reduce DM. 1/
In elderly patients stage 1 #BreastCancer:
❌Sentinel biopsy is not needed
💊Endocrine therapy provides little, if any, survival benefit
☢️Radiotherapy provides little, if any, survival benefit
✅Consider endocrine therapy and/or radiotherapy, with a preference for RT
@OncoAlert
🚨 Should RT Dose Be Personalized in NSCLC with Actionable Mutations?@OncoAlert
A real-world multicenter study explores dose escalation in EGFR/ALK+ 👥
🎯 Objective
•Investigate if standard RT doses are sufficient for NSCLC 👥 w/ EGFR/ALK mutations, given their unique tumor biology
🏥 Methods
•Multicenter retrospective study
•Patients: NSCLC Stage III w/ actionable mutations
•☢️Dose: Standard (60-66 Gy) vs. escalated dose
•🎯: Local control, OS & toxicity
📊 Key Findings
•Standard dose may be suboptimal for EGFR/ALK+ tumors
•Dose escalation 🔛 to improved local control
•N🚫 significant ⬆️ in toxicity
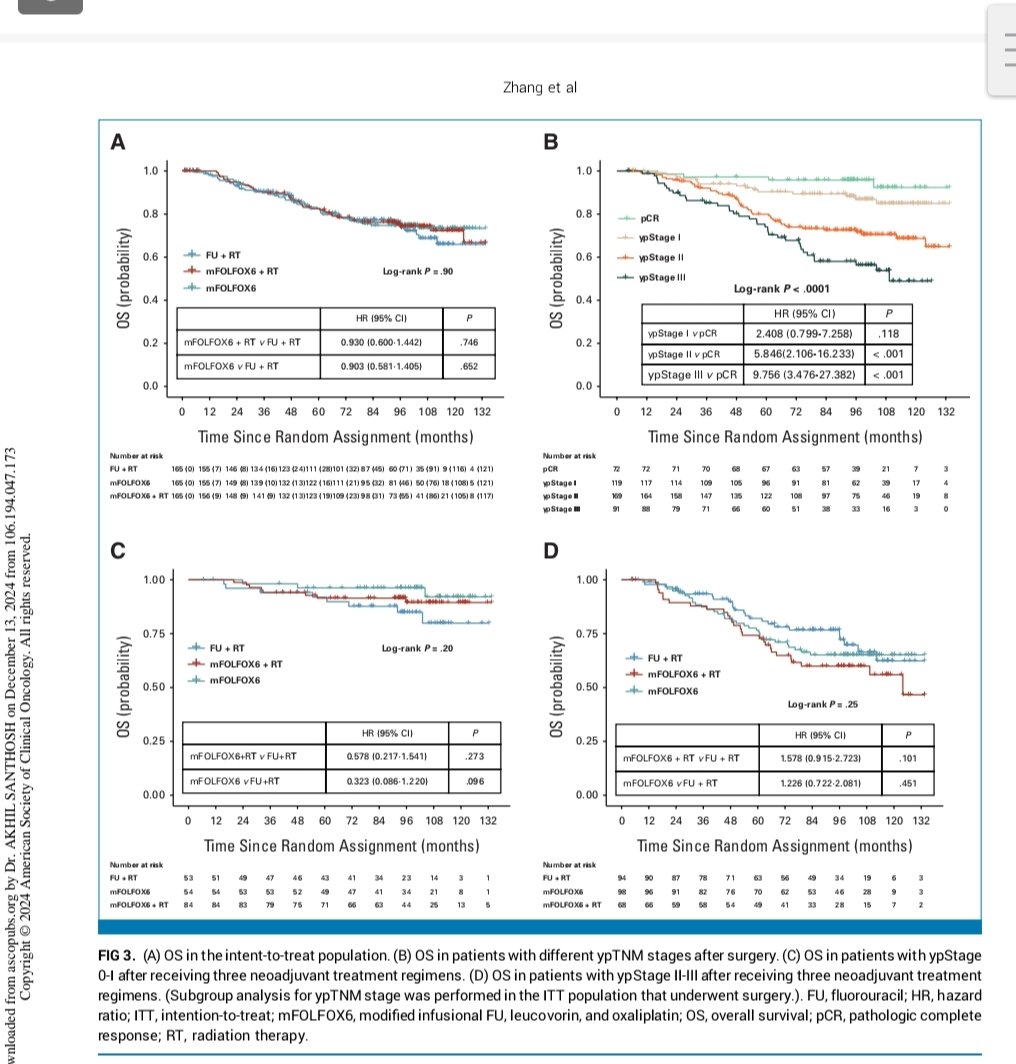
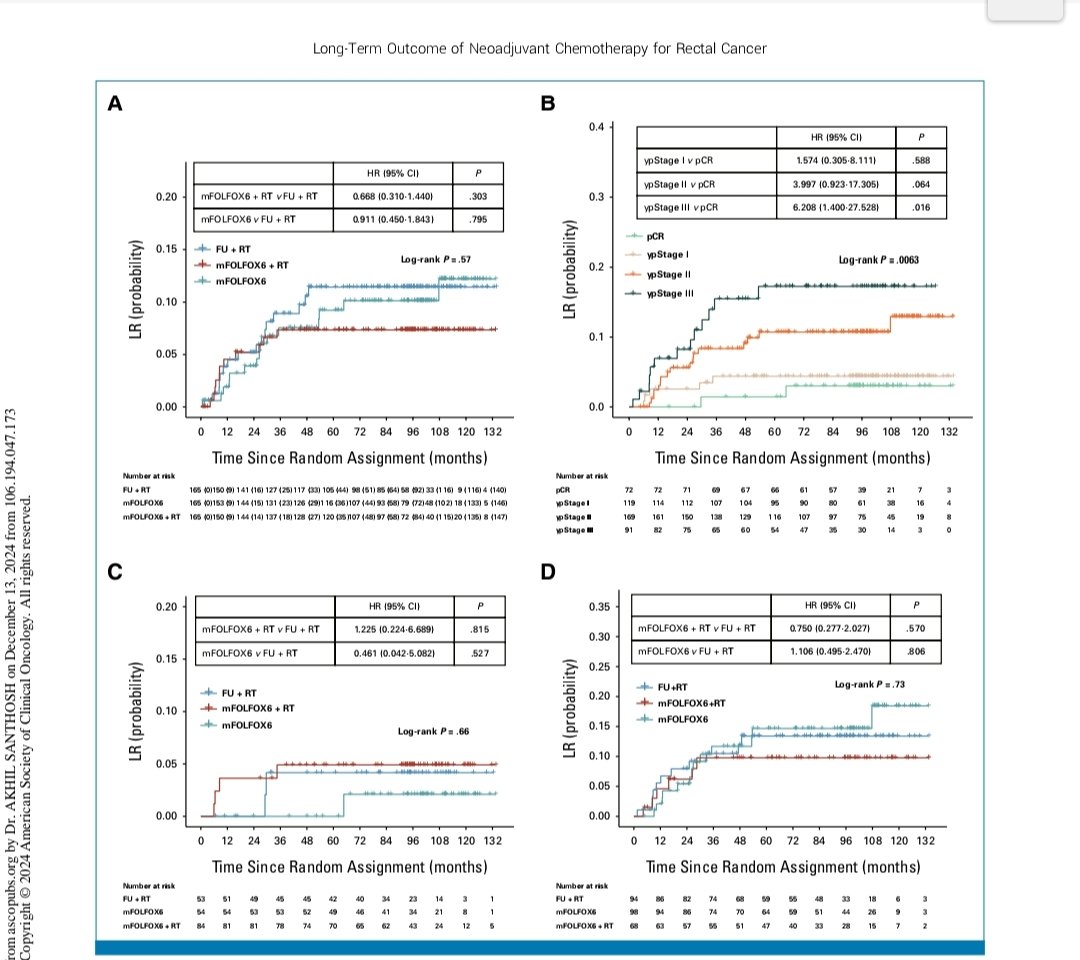
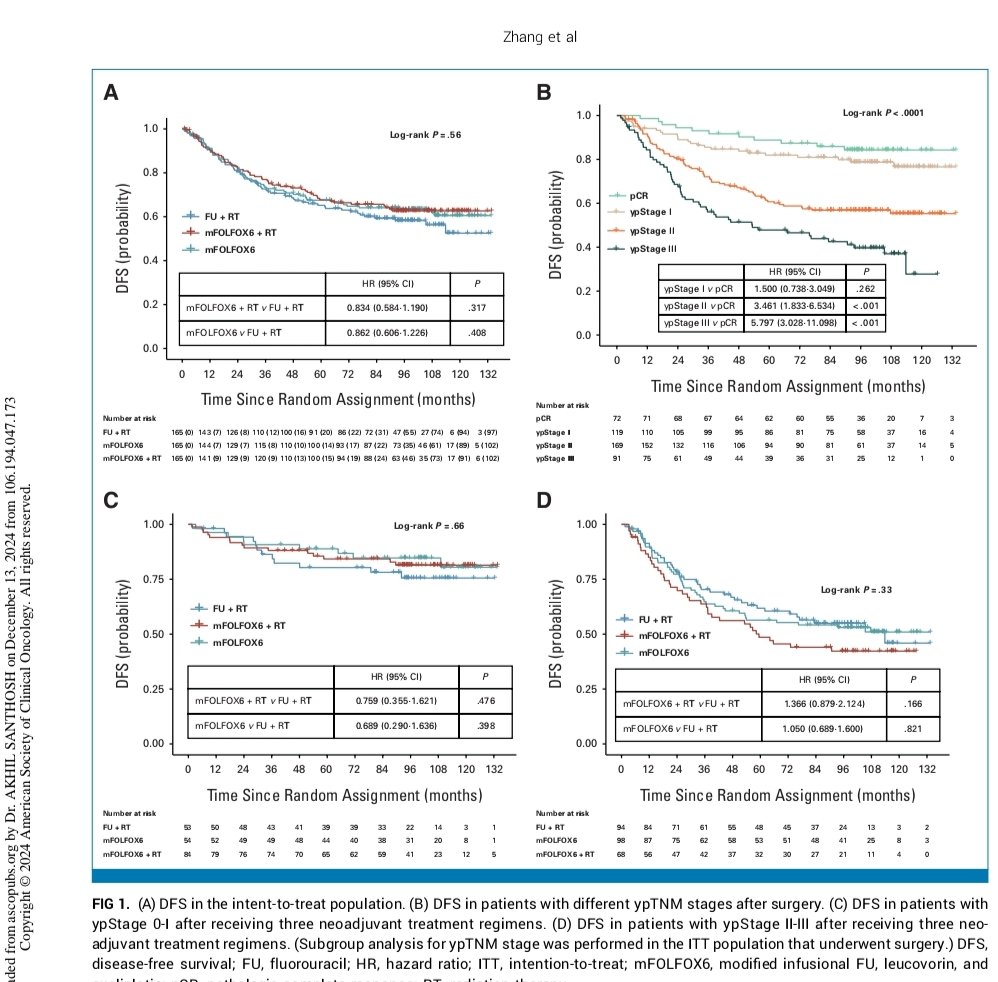
The 10 year results of FOWARC published in @JCO_ASCO today.
👉No diff in DFS, LR and OS between 5FU-RT, FOLFOX-RT and folfox alone for LA ca rectum
👉2nd study after PROSPECT questioning the role of RT
👉more LAR syndrome and persistent ostomy in CRT compared to chemo alone.
Presented at #SABCS24:
Interim results from the EUROPA trial:
Single-modality #endocrinetherapy vs #radiotherapy after breast-conserving surgery in women aged 70 years and older with luminal A-like early #breastcancer
https://t.co/ay6evWBQBG
RACE-GB is out! Congrats to authors for FIRST RCT of RT in gallbladder cancer.
N=135 w unresectable GBC, after 4c chemo, addition of RT (vs. obs) improved OS from 4 to 10 months.
Several limitations (single center, chemo gem/cis & 4 mo) but OS benefit shouldn’t be ignored.
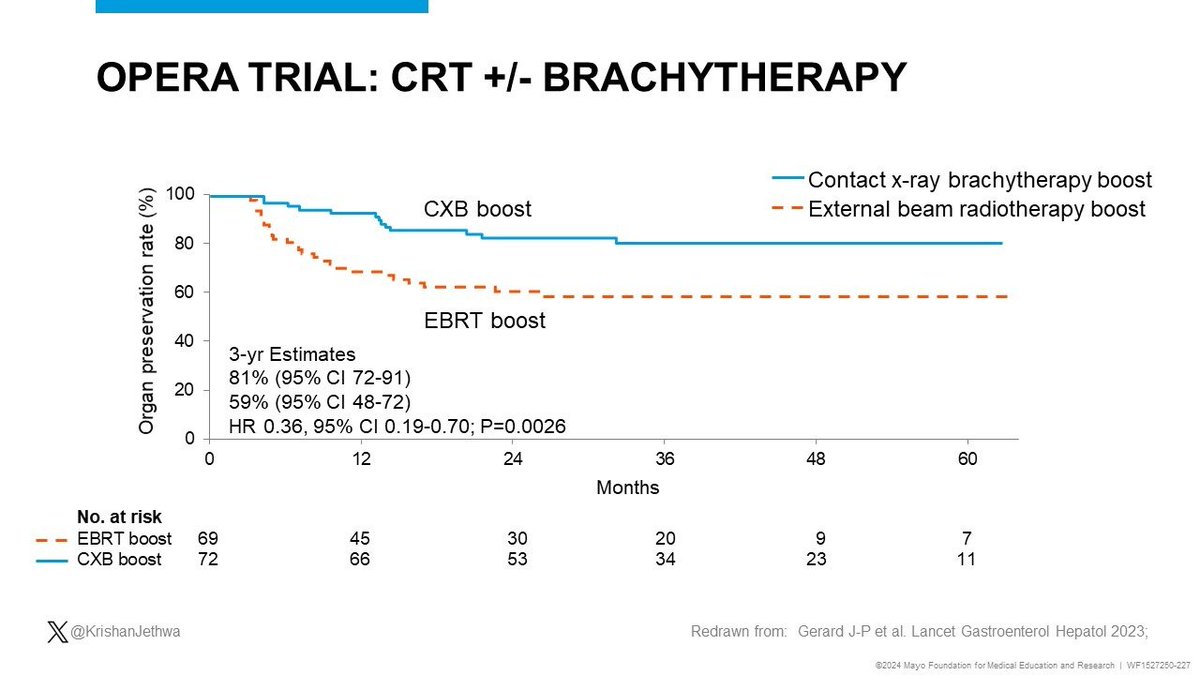
🔥Brachytherapy boost for high-risk localized rectal cancer🔥
OPERA ph3 RCT demonstrated improved organ preservation w/ brachy boost in favorable risk rectal cancer
🚨Retrospective study shows 3-year organ preservation of 80% for high risk disease‼️
https://t.co/pMwuNqq3M4
@hmaxi_MD delivers a lecture “Radiotherapy in HCC” today at FNCA Workshop on Radiation Oncology 2024 at Siriraj Hospital
It’s time for us to promote the role of RT in HCC!
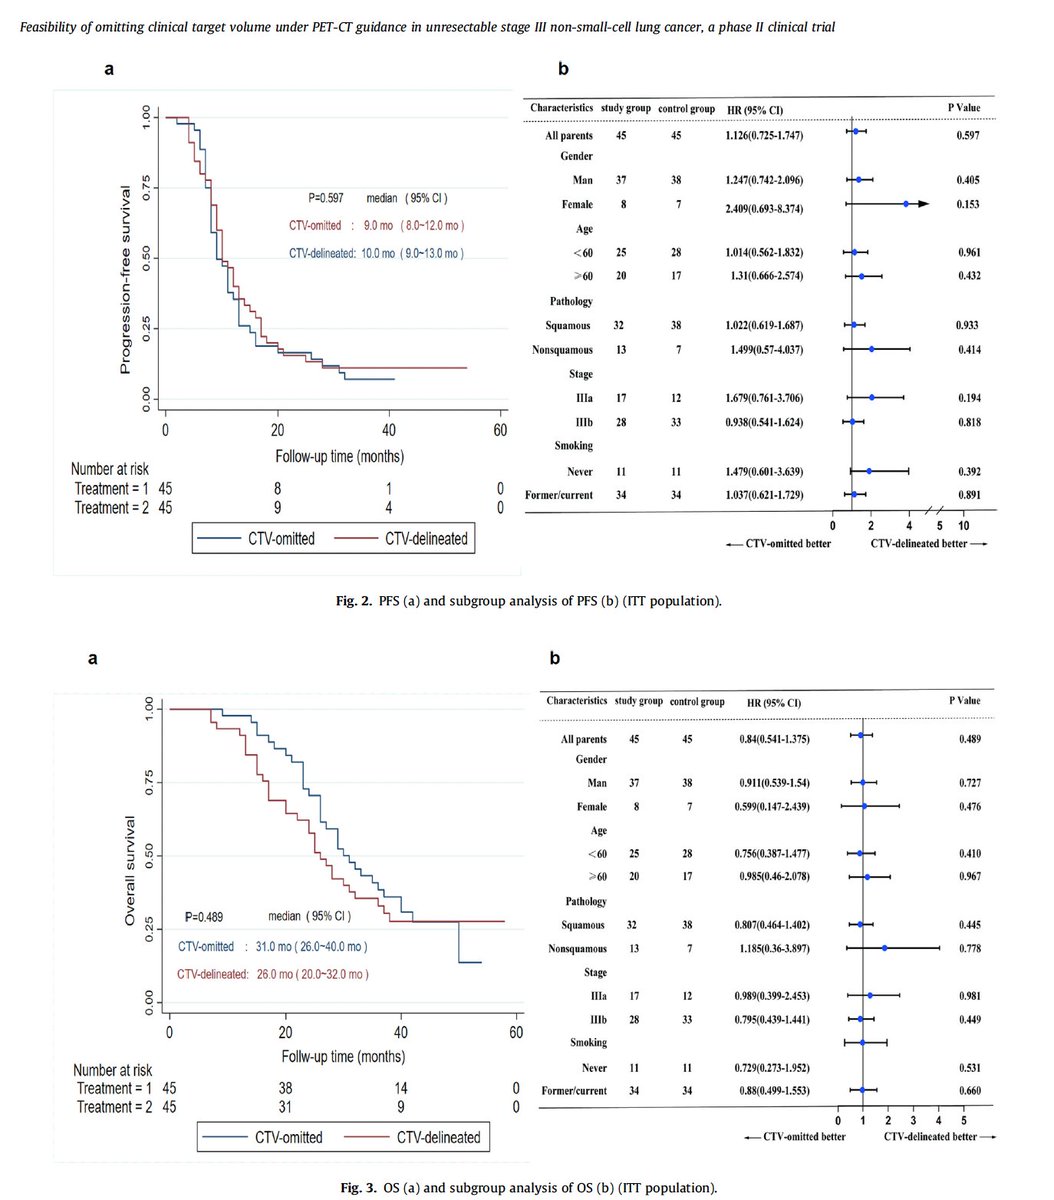
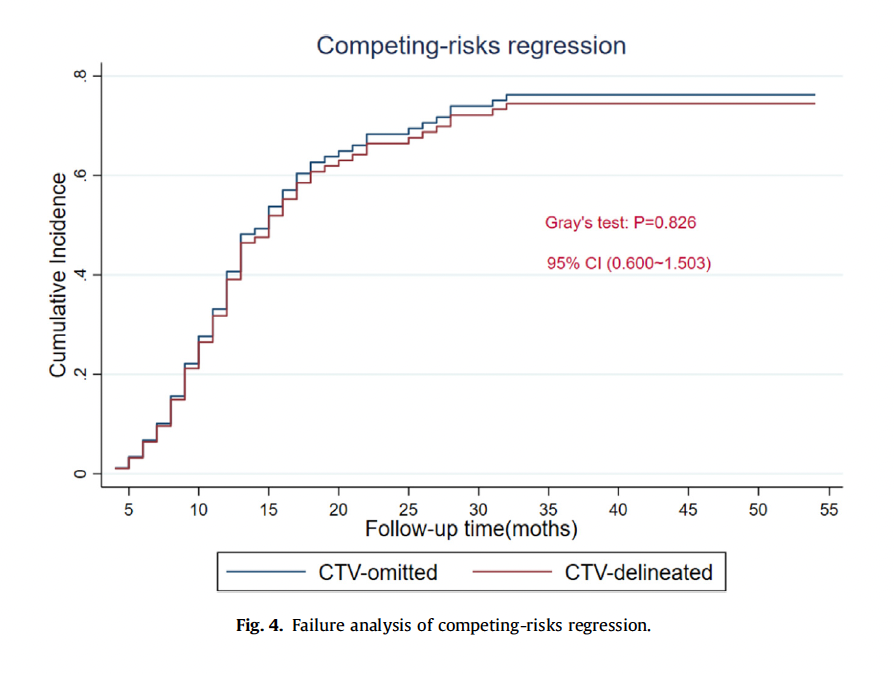
Here is a randomized phase II study (n=90) demonstrating what happened when locally advanced NSCLC was treated with CRT and without a CTV expansion (0 mm). #radonc https://t.co/j3pj1AJfyY
Refresher for the current & upcoming definitions of HER2 in breast oncology: Table 1 from the @myESMO consensus on HER2-low matches each pattern of HER2 IHC expression with the conclusion by the ASCO/CAP guidelines and by the Consensus group. 👉 https://t.co/axbCPl4Qfy
If radiation had an accelerated approval pathway - also based on surrogate endpoints like response rate - it would probably be approved in most settings.
Which doesn’t make sense. Just FYI.
@IBCradiation One thing is for sure, I’d be less likely to omit RT for low ER+!
10y local failure of 18.8% on PRIME2 😳 (read: most favorable candidates for omission. >= 65y, < 3 cm (only 10% 2-3 cm), pN0, SM >= 1mm, G1-2 (only 3% G3), LVSI (4%), G3 AND LVSI excluded)
Important IMvoke010 trial could shape future research in immunotherapy in locally advanced head & neck cancer after results of 1st phase III study in adjuvant therapy don't meet event-free survival endpoint. @DrHaddadRobert details findings presented at #AACR24.
CC: @DanaFarber