🇲🇽 Guadalajara 2026 | A great success!
The 2nd @society_eas LATAM Meeting was a tremendous success!
A sincere thank you to the Mexican Society of Nutrition and Endocrinology @SMNE_Oficial for the kind invitation and outstanding organization.
It was a privilege to share scientific insights, exchange perspectives, and strengthen collaboration among colleagues committed to advancing lipid management and cardiovascular prevention across Latin America.
Science, collaboration, and a shared mission: improving cardiovascular health in our region.
Looking forward to the next edition!
@society_eas@BNordestgaard@ProfKausikRay@lschreier1@MaximaMendez15@SMNE_Oficial@roopamehta2
Making the EAS the biggest global Atherosclerosis was a dream that became reality . Starting with the LATAM chapter. Started as an idea between myself and @drpablocorral
Now look at it
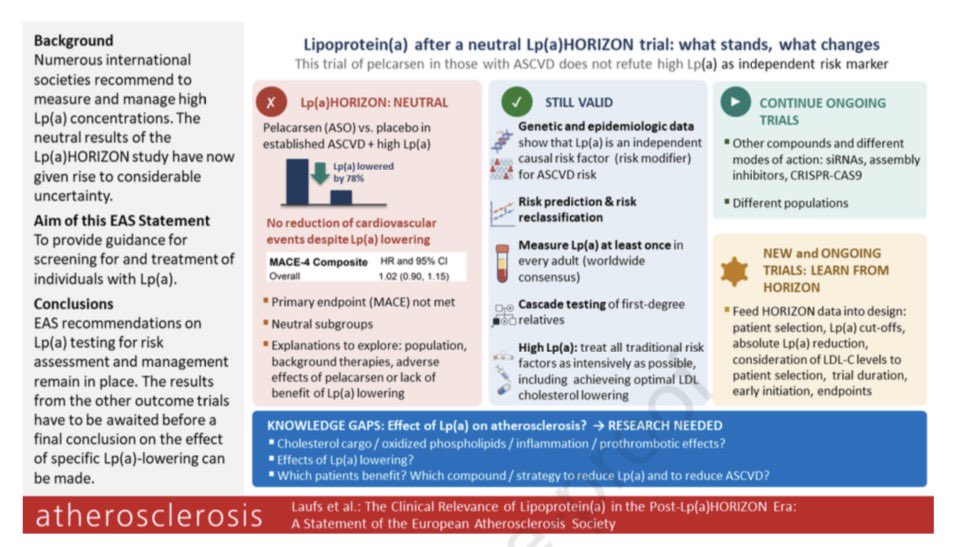
👉 MUST READ; A landmark EAS Statement in the post-Lp(a)HORIZON era in @ATHjournal
☝️The European Atherosclerosis Society @society_eas delivers a timely, evidence-based message following the neutral results of Lp(a)HORIZON.
1️⃣ 78% Lp(a) reduction ≠ cardiovascular benefit.
We must distinguish a causal risk factor from a validated therapeutic target.
2️⃣ Lp(a) remains a major cardiovascular risk factor.
Measure it at least once in every adult. Family screening remains essential.
3️⃣ LDL-C lowering is our strongest actionable strategy.
Intensive control of LDL-C and other risk factors can mitigate Lp(a)-associated risk.
4️⃣ Timing may be everything.
Can a few years of treatment reverse decades of cumulative atherogenic exposure?
5️⃣ The science is far from over. Ongoing RCTs with different Lp(a)-lowering agents are essential.
☝️My key takeaway: A negative trial should change our assumptions, not replace scientific evidence with speculation.
☝️ Measure Lp(a). Lower LDL-C. Control global risk.
Keep testing hypotheses with RCTs.
🔗 https://t.co/PkokhMCK0e
@BNordestgaard@ProfKausikRay@MeralKayikcoglu@KronenbergLab@j_rvl@SamiaMoraMD
The obesity adverse outcome story.
BMI is a poor and misleading way to quantify obesity
When the CAD-obesity definition is used, we see the increased risk of all-cause mortality (top graphs) and lesser risk for preclinical obesity (lower graphs)
@Nature
https://t.co/mxx5ENViwz
@DrDerekConnolly@drjohnm Derek when you do a non inferiority study with a small sample size you set it up to show this. If you state over two years stopping wont cause 15% more harm . Over 5 years with a larger sample size what do you think it would show
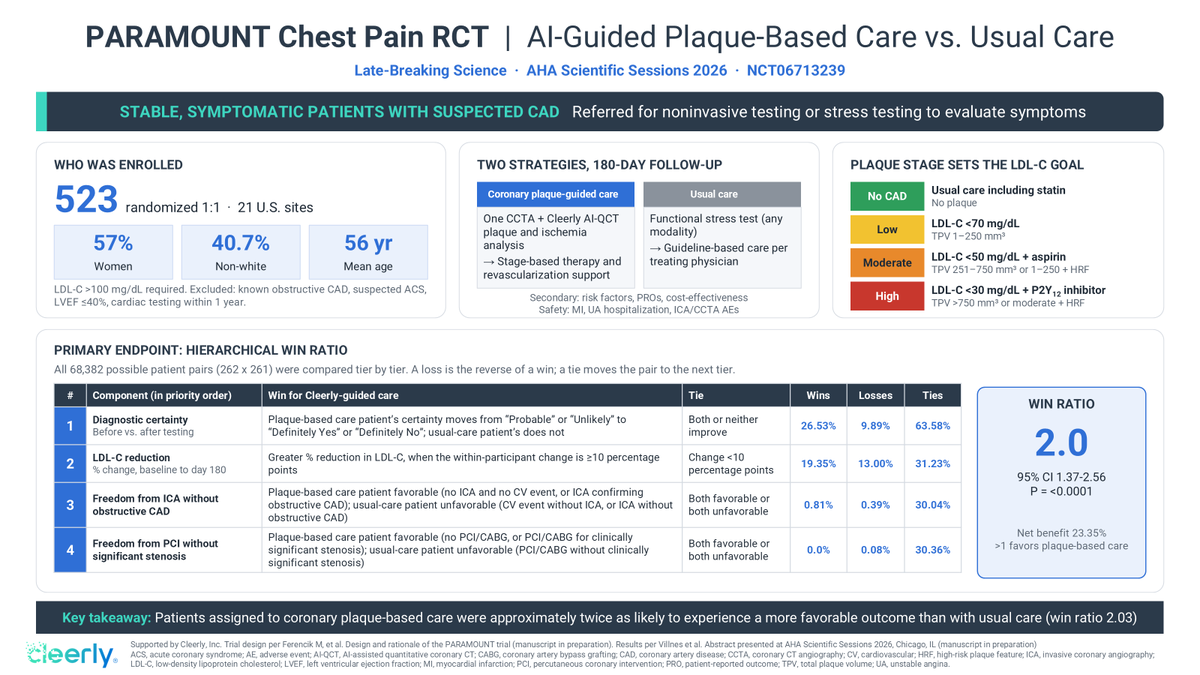
1/8: The #PARAMOUNT trial of #coronary plaque-based care was presented this morning at #AHA26. Here are the key findings and some context for interpreting the results. The trial and this post were sponsored by @CleerlyHealth, for whom I serve as a consultant.
7/8: In #PARAMOUNT, plaque-based care produced a win ratio of 2.0 versus usual care for the prespecified hierarchical composite. The difference was driven primarily by greater diagnostic certainty and lower LDL-C, important context when interpreting the overall trial result.