Surprise 1: Anthropic acquired a one-person biotech
.
.
.
Surprise 2: that person is me
Surprise 3: I’m here to tell you all about it
Yes, this is what you think it is; after 6 yrs of increasingly loose anonymity: the Professor Oak reveal post
…and yes, it has gotten so boring around here that I’m literally doxxing myself to spice up the timeline
-------
Ok, allow me to introduce myself. My name is Cody Tranbarger. I mostly tweet, but occasionally find time to dabble in drug dev & starting/building biotechs. My past lives span the VC, crossover, startup continuum; Prof Oak has been my way of keeping a digital foot in those worlds, despite having my physical feet planted elsewhere.
The past 18 mo, ‘elsewhere’ was Mithril Medicine, a co. I founded to develop bsAbs for LAMA2-CMD & other ECM-related genetic diseases.
Mithril was born out of hands-on building with @MikeNGladstone, @JasonPaulRhodes, @LifeSciVC, & team @atlasventure. Somehow, I made enough half-decent calls along the way (even a broken clock is right twice a day, eh?) to convince them Mithril/I warranted a small seed. While I can hardly rationalize such an outrageously cavalier bet, I’m grateful for it, & I'd partner with Atlas again in a heartbeat.
In typical AV fashion, Mithril’s primordial form was virtual, decentralized, & ultra-lean. This stage tends to be short-lived, but for Mithril, it worked surprisingly well, for surprisingly long, thanks in part to the rapid maturation of the AI tools I used liberally.
Eventually, Mithril became a bit of an experiment itself - to find the upper bound of how far it could scale as a single operator + a bunch of Claude (+ a stellar bench of part-time consultants).
In parallel, I started spending time with @nc_frey, @an1lam, & @CoefficientBio team; and promptly experienced, for the 1st time, AI at the frontier. Soon thereafter, Mithril stopped looking like an experiment, & started looking like a preview of an entirely new operating model.
From that spark came “Pipeline-in-a-Person.” The idea immediately resonated when we shared it here back in April; and it was central to the shared vision that led to Anthropic’s acquisition of Mithril, & my joining the team.
Why join Anthropic? Three reasons.
(1) For Mithril, the programs continue, with more resources & infrastructure behind them, and as much Claude as I can put to work.
(2) For me, the chance to start several more programs, & find out how many one person can actually run in parallel - an almost unprecedented luxury for a curious drug hunter.
(3) For our mission, a path to institutionalize & scale this new way of working, then put it in the hands of all of biopharma, all over the world - which, candidly, I find the most energizing.
Will AI x Bio cure diseases? Unequivocally yes, imo… but not by the route that gets the most airtime. Rather than timeline acceleration & compression, I see orchestration & parallelization as today's low-hanging fruit.
Most drug hunters see a handful of go/no-go calls in a career, & spend entirely too much of the rest trading emails (my inbox can attest).
Give them the bandwidth to run several programs at once, and the time to focus on scientific judgment, and I’m willing to bet they’ll make better calls. And at scale, better calls translate to more drugs, higher hit rates, broader patient impact, & likely, a disease or 10 or 100 cured. I couldn't be more excited to build toward that future @AnthropicAI.
Finally, a heartfelt thank you to BioTwitter/X. The end of anonymity is bittersweet, but if anyone’s earned a proper introduction, you all have.
It’s difficult to overstate how much this app has done for me: a decade of education, plenty of friends, many job opportunities, several mentors, a few investors, even a co-founder (fmr). It was the generosity of this community that inspired me to start posting 6 years ago, after just as many years lurking. I hope I’ve been able to pay it forward, in my own small way.
But, to be clear, Prof Oak isn’t going anywhere. Same beat, same themes, and now, a front-row seat to drug development at the frontier. Stay tuned for dispatches from the trenches; and remember...
Gotta Cure 'Em All
This was published in 2020, and yet none of the 11 problems are fully solved. Some are very simple, like "how do we handle the fact that RNA sequencing data often doesn't detect a gene sequence?" Many others are plain software engineering or machine learning problems.
I want to show you guys something really wild.
Claude Opus 5.5 basically one-shotted an explainer video for this paper, and it's incredible!
After watching the video, I feel like I have a decent understanding of how JEM works!
Check it out:
i opened up an AI's brain tonight with @_lyraaaa_'s neuron explorer
qwen 3.5 4b has 294,912 neurons
push just one and it becomes someone else
here's who i found 🧵
If you've ever wondered why smart TVs are so cheap, this is why.
@log4j rooted his Samsung and found an always-on hot mic, automatic content recognition, geolocation, network mapping, ad targeting and user profiling, shared with Samsung's "400 partners".
A lot of it can be blocked in <15 min, wrote a basic guide below.
What your TV is doing
The main culprit is ACR (automatic content recognition). Your TV screenshots what's on screen, fingerprints it, and sends it home to build your ad profile. Samsung does it every 500ms, LG every 10ms [1].
What is insane: it happens on connected devices too.
Plug in your laptop, your console, your work machine, and your TV can fingerprint that via HDMI [1].
He also found that if your Samsung doesn't have a mic, it'll look for one from a connected soundbar or bluetooth device.
https://t.co/vNdTnIQ6KF
It's on by default, and you likely agreed to it on the setup screen you clicked through in 10 seconds.
Step 1: Turn off ACR
Samsung: Terms & Privacy → Viewing Information Services
LG: Live Plus
Vizio: Viewing Data
Roku: "Use info from TV inputs"
Sony/Google TV: Samba Interactive TV
Menus vary by model, but those are the names to look for. While you're in there, opt out of interest-based ads, reset your advertising ID, decline every optional privacy agreement, turn off voice recognition, and delete apps you never open.
Step 2: Give smart devices their own network
Put the TV, cameras, speakers and vacuum on your router's guest/IoT network. The logic is simple: these devices rarely get patched. If one gets compromised (getting drastically more frequent with AI), it shouldn't be able to see your other devices or home network.
Step 3: Block trackers for the whole house with DNS-level filtering
NextDNS (cloud-based) is easy and has a solid free plan. Pi-hole is a little bit more work if you prefer self hosting. For simplicity we'll focus on the former.
1. Sign up at https://t.co/IwhafVWVM8 (free tier is plenty)
2. Privacy tab: add a blocklist (OISD is a good bet) and turn on Native Tracking Protection for Samsung, LG, Roku, Amazon (see attached image)
3. Setup tab: copy your endpoint
4. Paste it into your router's DNS settings as DNS-over-HTTPS/TLS (or use the IPs + "Link IP" if your router only does plain DNS)
5. Bonus: block outbound port 53 except to your router. Some devices hardcode their own DNS to get around you
Then open the NextDNS logs and watch how often your TV phones home. It's eye-opening. If an app or update breaks, find the domain in the logs and allowlist it.
Why they do this
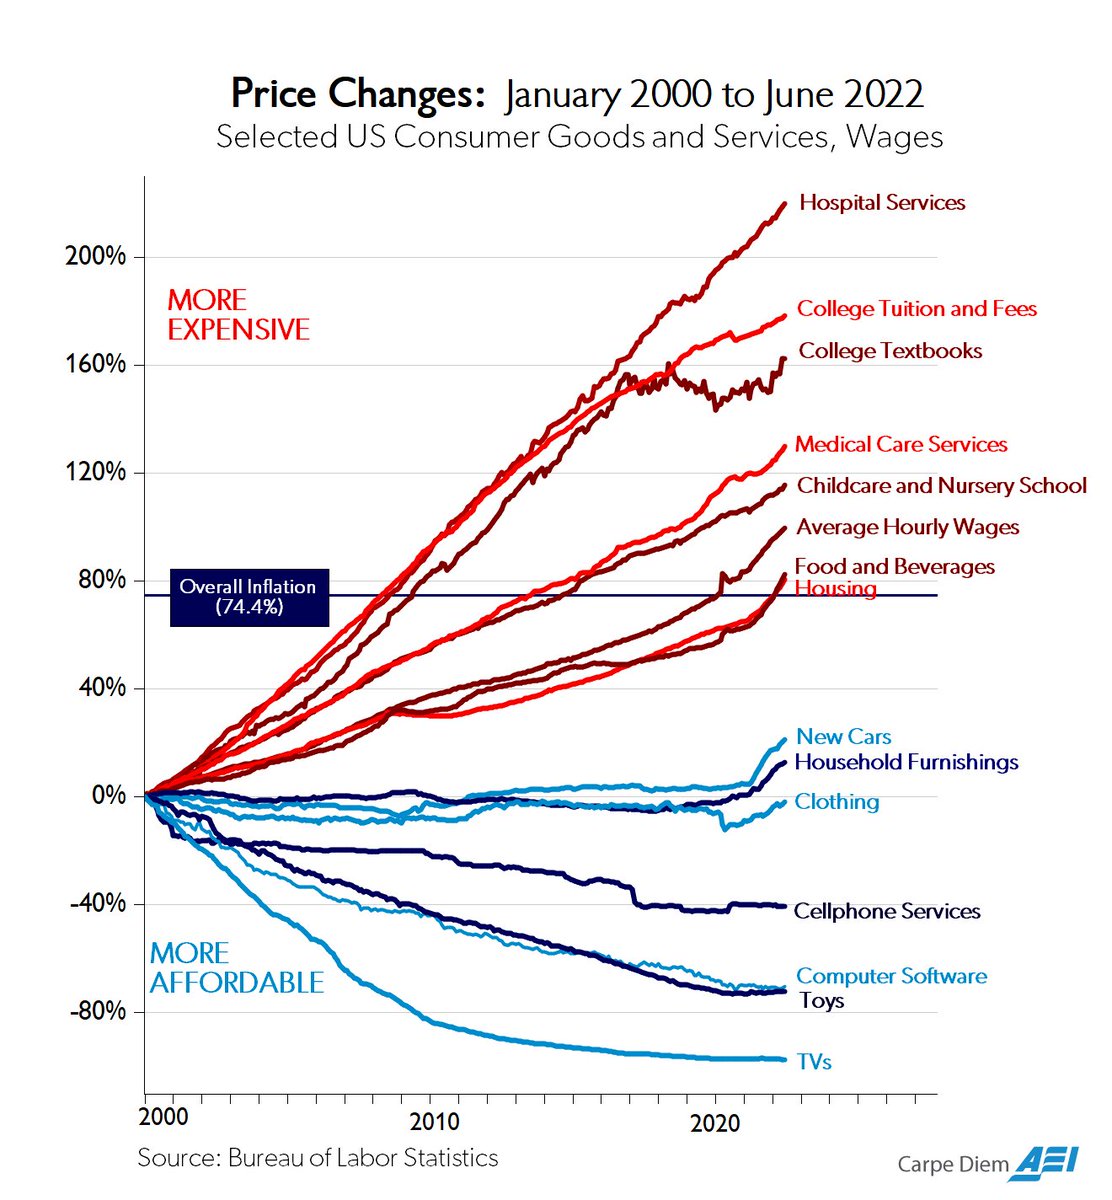
TV prices are down 97% since 2000 [2]. Most of that is better manufacturing and brutal competition. But once margins on the hardware hit zero, the cost moved to you.
In Q3 2024, Vizio lost $6.7M selling TVs and made $115.8M in gross profit from ads and viewing data [3]. They've said on earnings calls that they keep TV prices low to grow the audience they sell to advertisers. Walmart bought them in 2024.
This isn't a conspiracy theory either. Vizio paid $2.2M to the FTC in 2017 for tracking 11 million TVs without consent. Last December, Texas sued Samsung, LG, Sony, Hisense and TCL over ACR. Samsung and LG have since agreed to stop collecting that data without explicit consent [4].
TL;DR
1. ACR off
2. Ads + voice off
3. Smart devices on their own network
4. NextDNS filtering on the router
Sources:
[1] ACR study: https://t.co/S1IS8lXNbA
[2] Cost of US consumer goods: https://t.co/nclXELXcbd
[3] Vizio Q3 2024: https://t.co/CrVbwc9ZXk
[4] Texas v. Samsung: https://t.co/wFOUdeh1if
Diagnostic Accuracy of NT-proBNP thresholds in Dyspneic Patients in the Emergency Department according to patients’ characteristics: A Systematic Review and Meta-Analysis
A threshold ≤300 ng/L provides excellent rule-out performance for AHF, while age-dependent NT-proBNP thresholds offer superior diagnostic performance for ruling in AHF in the ED compared to fixed thresholds, and demonstrate consistent accuracy across subgroups.
@hfcollaboratory@HFSA@HFA_President@DrMarthaGulati@gcfmd@SJGreene_md
https://t.co/TegU7SeMxd
I feel a bit sad that there will be no more humans who have the skills of diagnosing Mitral Stenosis by listening to the diastolic rumbling murmur wand the pre-systolic accentuation with the bell, then flip to diaphragm and hear the opening snap..
And oh: the splitting of S2 🦕😢
There's a whole new role emerging in clinical AI called Physician AI engineer. It describes a doctor who understands and builds AI systems for clinical purposes. I think the role will only get more common with time.
Today in @Nature, we’re sharing the breakthrough research behind the Personal Health Agent (PHA)—the foundational science that was fundamental to how we built the Google Health Coach in the Google Health App.
The hardest part of cardiology 🫀fellowship?? Holding the pager at night.
I built the Cardiology Night Float Application 💻
7 PM: STEMI, shock, VT storm, a crashing Impella, and more. You can call your attending
Work them up and Survive till 7 AM 🕖
https://t.co/vwpL06Ptf0
An alternative for upper GI endoscopy showcased at #UEGWeek 🆕🚀
The OMOM robotic system involves swallowing a pill sized capsule endoscope for examination of the upper GI tract and small bowel. The capsule is navigated with an external magnet, which is now AI-assisted for autonomous navigation, although manual override is also possible.
The technology enables sedation-free endoscopy, but limitations include the inability to biopsy, cost and real estate needed to house the unit.
Would you welcome this as a potential patient?