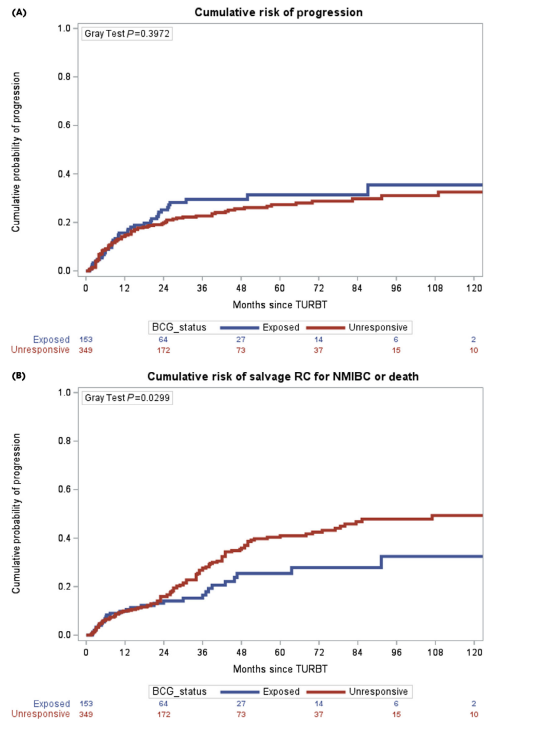
❓️Can we avoid ReTURBT in selected patients with T1 NMIBC? ✅️ According to our study YES!
👥️A response-based approach can spare up to 71% of ReTURBT reducing overtreatment
Full paper➡️https://t.co/dmugDLY4Wm
@EurUrolOncol@urotoday@Uroweb@oncodaily@IBCG_BladderCA
🩺 UROTHELIAL CANCER UPDATE 2026 🔬 Meets the Guidelines, Challenges the Decisions. Join international experts for a turning point in urothelial cancer management!
🗓️ 18/09 @unito@cittasalute_to@UroMolinette
👨🏫 Chairs: Prof. @paolo_gontero & Prof F Soria
https://t.co/WMnVmJYwej
Congratulations to @LauraBukavinaMD@jaymsiva@drjkaouk and @ClevelandClinic team on largest external validation of the IBCG IR NMIBC substratification model
📊 2822 patients | 20 years | 3-year recurrence by subgroup:
🟢 IR-low: 12%
🟡 IR-intermediate: 38%
🔴 IR-high: 77%
Progression followed the same stepwise pattern. Fine-Gray competing-risk models confirmed significance (p<0.001) - separation held on 12-month landmark analysis, ruling out early-event bias.
Yet more evidence that trials enrolling IR NMIBC should stratify by IBCG subgroup at enrollment to be clinically meaningful.
Conflating patients with 12% and 77% recurrence risk in the same trial arm is a fundamental problem.
Full text:
https://t.co/XsO8CUY3WS @IBCG_BladderCA
A multi-center study examines maintenance schedules for intermediate-risk #NMIBC. @RobertoContieri@IstTumori joins @UroDocAsh@UTMDAnderson to discuss the results which include two-year recurrence-free survival of 55% with no maintenance versus 78% with any maintenance. Classification and regression tree analysis identified optimal cutoff at more than six monthly instillations. #WatchNow on UroToday > https://t.co/G4Mw1OB0cA
1) Approval based on marginal improvements in efficacy (without improvement to CSS/OS)
2) Toxicity that isn't G5 (death) doesn't seem to impact approval. 10-15% serious autoimmune AEs in NMIBC is deemed ok
3) little weight given to efficacy vs toxicity balance of a drug
Excellent lecture by @SScagliarini_ on the growing importance of patient-reported outcomes in oligometastatic RCC. A crucial reminder that beyond oncologic endpoints, understanding the patient perspective is essential to truly optimize treatment strategies.
@Synergy_Uro@Uroweb
Great pleasure having Prof. Axel Bex at @Synergy_Uro discussing the evolving landscape of locally advanced RCC. Excellent insights and stimulating discussion on current challenges and future directions in kidney cancer care. @eau_yuo@EAUYAU_RenalCa@UrowebESU@EAU_Uroonco
The definitive #SYNERGY26 programme is out
📆 28–29 May | 📍 Naples
Locally-advanced & Oigometastatic GU cancers Edition.
Program: https://t.co/Gx1pBWHGEk
As every year, a packed room for the AUA-IBCG Forum, taking place right now in Salon H.
Great discussions and energy around the future of bladder cancer care and research.
#AUA2026#BladderCancer@IBCG_BladderCA@UroDocAsh
To escalate or de-escalate treatment in BCG-naive HR NMIBC?
Our thoughts on the recent JCOG1019 trial by Kitamura et al @EUplatinum
Free access to full text 👇🏽
https://t.co/xH5ios6rmT
@RobertoContieri@LAUrology_NL@UroDocAsh
A multi-center study examines maintenance schedules for intermediate-risk #NMIBC. @RobertoContieri@IstTumori joins @UroDocAsh@UTMDAnderson to discuss the results which include two-year recurrence-free survival of 55% with no maintenance versus 78% with any maintenance. Classification and regression tree analysis identified optimal cutoff at more than six monthly instillations. #WatchNow on UroToday > https://t.co/G4Mw1OB0cA
The International Bladder Cancer Group Travel Award to support outstanding fellows and early-career academic faculty committed to advancing the field of bladder cancer is now offered annually to provide emerging leaders the opportunity to participate in the IBCG Annual Retreat.
Details at link: https://t.co/y8zbYkeLac
#BladderCancer #IBCG26